


School Personnel Health Record (H511.340) at a glance
What it is: School Personnel Health Record, H511.340 (Rev. 5/2019), for use after offer of employment has been made.
Who signs: Enter the Physician Name (Print), Signature of Examiner and Date. Enter the Signature of Employee and Date.
A filled-in School Personnel Health Record (H511.340) example: a hepatitis B record

How to fill out School Personnel Health Record (H511.340), box by box
I. INFORMATION
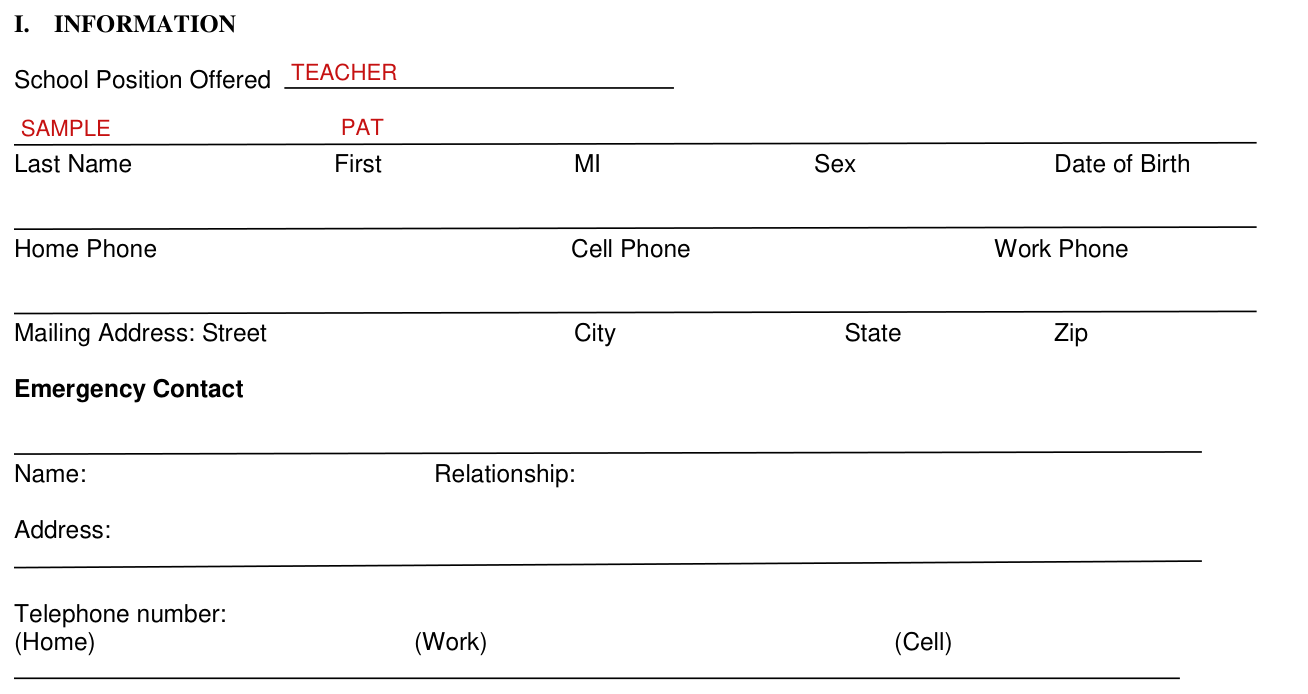
In I. INFORMATION, enter the School Position Offered, Last Name, First, MI, Sex and Date of Birth.
Enter the Home Phone, Cell Phone and Work Phone.
Enter the Mailing Address: Street, City, State and Zip.
For the Emergency Contact, enter the Name, Relationship, Address and Telephone number (Home) (Work) (Cell).
II. IMMUNIZATION HISTORY
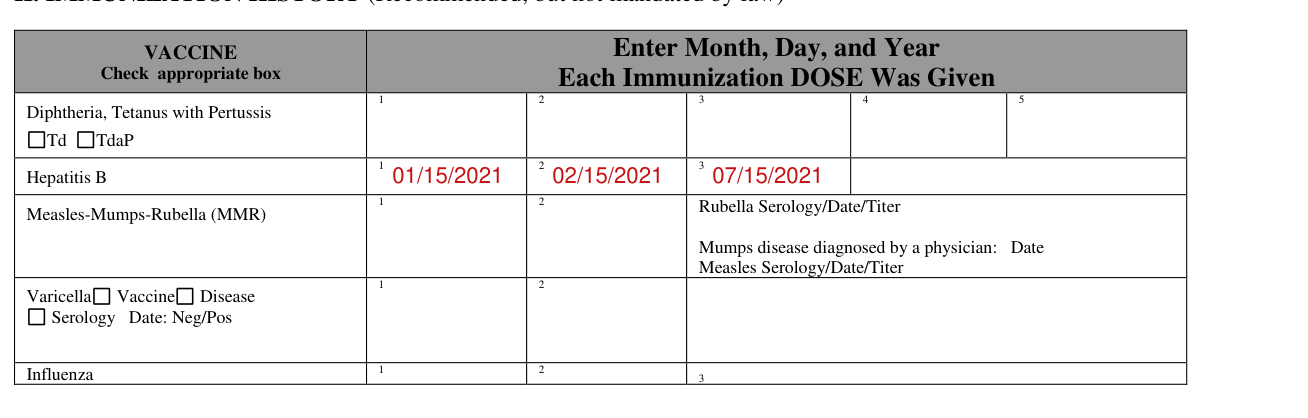
II. IMMUNIZATION HISTORY is recommended, but not mandated by law. Enter Month, Day, and Year Each Immunization DOSE Was Given.
Under VACCINE, check the appropriate box. For Diphtheria, Tetanus with Pertussis, the boxes are Td and TdaP, for DOSE 1, 2, 3, 4 and 5.
For Hepatitis B, enter DOSE 1, 2 and 3.
For Measles-Mumps-Rubella (MMR), enter DOSE 1 and 2, the Rubella Serology/Date/Titer, the Date for Mumps disease diagnosed by a physician and the Measles Serology/Date/Titer.
Varicella lists Vaccine, Disease and Serology, with DOSE 1 and 2 and a Serology Date: Neg/Pos.
For Influenza, enter DOSE 1, 2 and 3.
III. TUBERCULOSIS SKIN TEST RESULTS
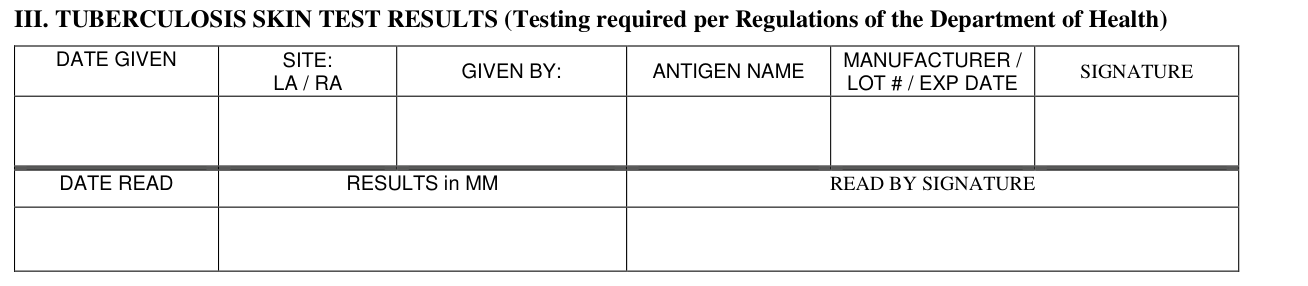
III. TUBERCULOSIS SKIN TEST RESULTS: testing required per Regulations of the Department of Health.
Enter the DATE GIVEN, SITE: LA / RA, GIVEN BY, ANTIGEN NAME, MANUFACTURER / LOT # / EXP DATE and SIGNATURE.
Enter the DATE READ, RESULTS in MM, and READ BY SIGNATURE.
IGRA TEST RESULTS
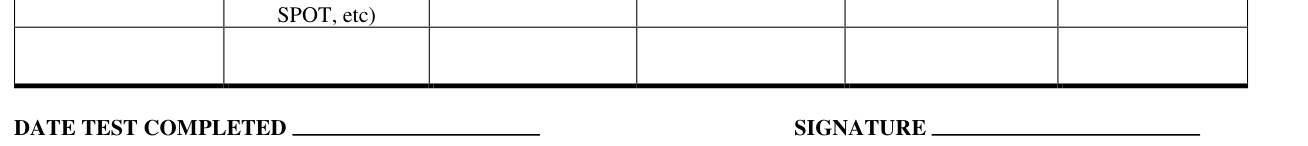
The form prints OR before IGRA TEST RESULTS.
For IGRA TEST RESULTS, enter the DATE COLLECTED and the TEST NAME (QFT-GIT, T-SPOT, etc).
For RESULT, the form lists POSITIVE, NEGATIVE, INDETERMINATE and QUANTITATIVE.
Enter the DATE TEST COMPLETED and SIGNATURE.
Previously known/new positive reactors
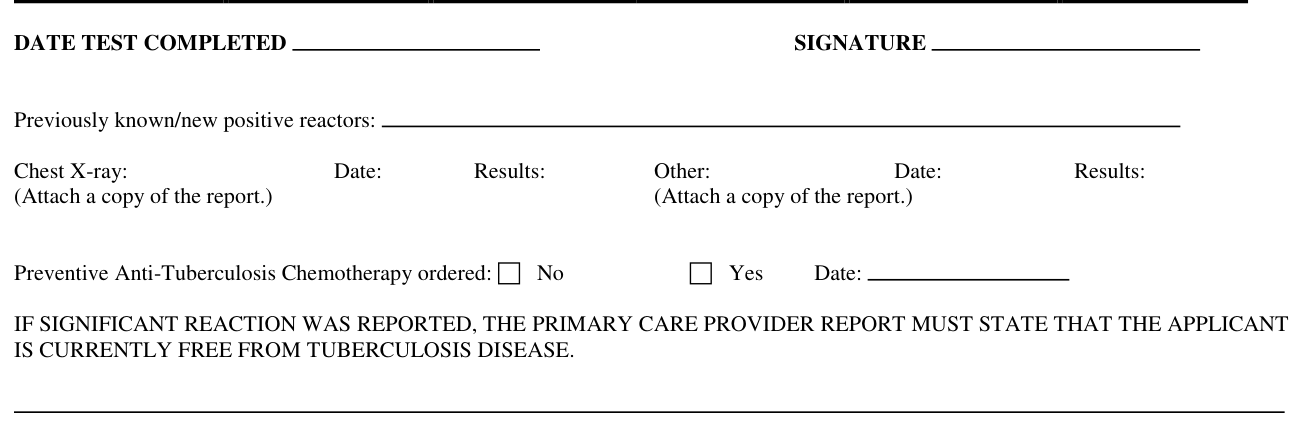
Under Previously known/new positive reactors, enter the Date and Results for the Chest X-ray, and for Other, enter the test, Date and Results. Attach a copy of the report, which the form prints for the Chest X-ray and for Other.
For Preventive Anti-Tuberculosis Chemotherapy ordered, mark No or Yes and enter the Date.
If significant reaction was reported, the primary care provider report must state that the applicant is currently free from tuberculosis disease.
IV. MEDICAL CONDITIONS
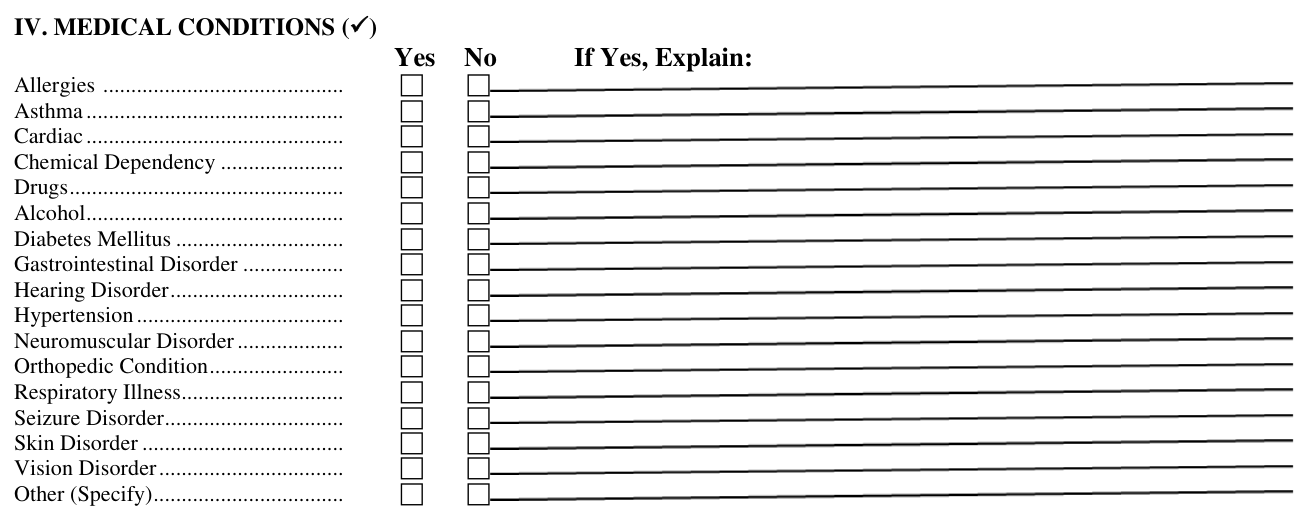
In IV. MEDICAL CONDITIONS, check (✓) Yes or No for each of these: Allergies, Asthma, Cardiac, Chemical Dependency, Drugs, Alcohol, Diabetes Mellitus, Gastrointestinal Disorder, Hearing Disorder, Hypertension, Neuromuscular Disorder, Orthopedic Condition, Respiratory Illness, Seizure Disorder, Skin Disorder, Vision Disorder and Other (Specify). If Yes, Explain.
V. PHYSICAL EXAMINATION
In V. PHYSICAL EXAMINATION (✓), each line has NORMAL, ABNORMAL, NOT EXAMINED and COMMENTS.
Enter the Height (inches), Weight (pounds), Pulse and Blood Pressure.
The lines are Hair/Scalp, Skin, Eyes - Visual Acuity: R L, Eyes - Color Vision, Ears - Hearing (dB) R L, Nose and Throat, Teeth and Gingiva, Lymph Glands, Heart - Murmur, etc, Lungs - Adventious Findings, Abdomen, Genitourinary, Neuromuscular System and Extremities.
Special medical problems and special equipment or accommodations

Are there any special medical problems or chronic diseases which require restriction of activity, medication which might affect his/her work role? If so, specify.
Are there any special equipment or accommodations needed to enable this person to perform their duties? If so, specify.
Signature of Examiner and Signature of Employee

Enter the Physician Name (Print), Signature of Examiner and Date.
Enter the Physician Address.
Next to Physician Address, the form states that the statements and answers as recorded in the form are full, complete and true to the best of my knowledge and belief.
The form prints: "I understand that any false or misleading statements may cause termination of my employment."
The form prints: "I authorize the physician or other person to disclose any knowledge or information pertaining to my health to the employing authority for whom this examination is performed."
Enter the Signature of Employee and Date.
Sources
[1] School Personnel Health Record (H511.340 (Rev. 5/2019)), Pennsylvania Department of Health (the Official source link on this page).