


Hockey Canada Medical Information Sheet at a glance
What it is: The Hockey Canada Safety Program MEDICAL INFORMATION SHEET, Revised 2015-07-31.
Who signs: Enter the Date and the Signature of Player, and the Date and the Signature of Parent or Guardian.
A filled-in Hockey Canada Medical Information Sheet example: a parent fills in the sheet for a player
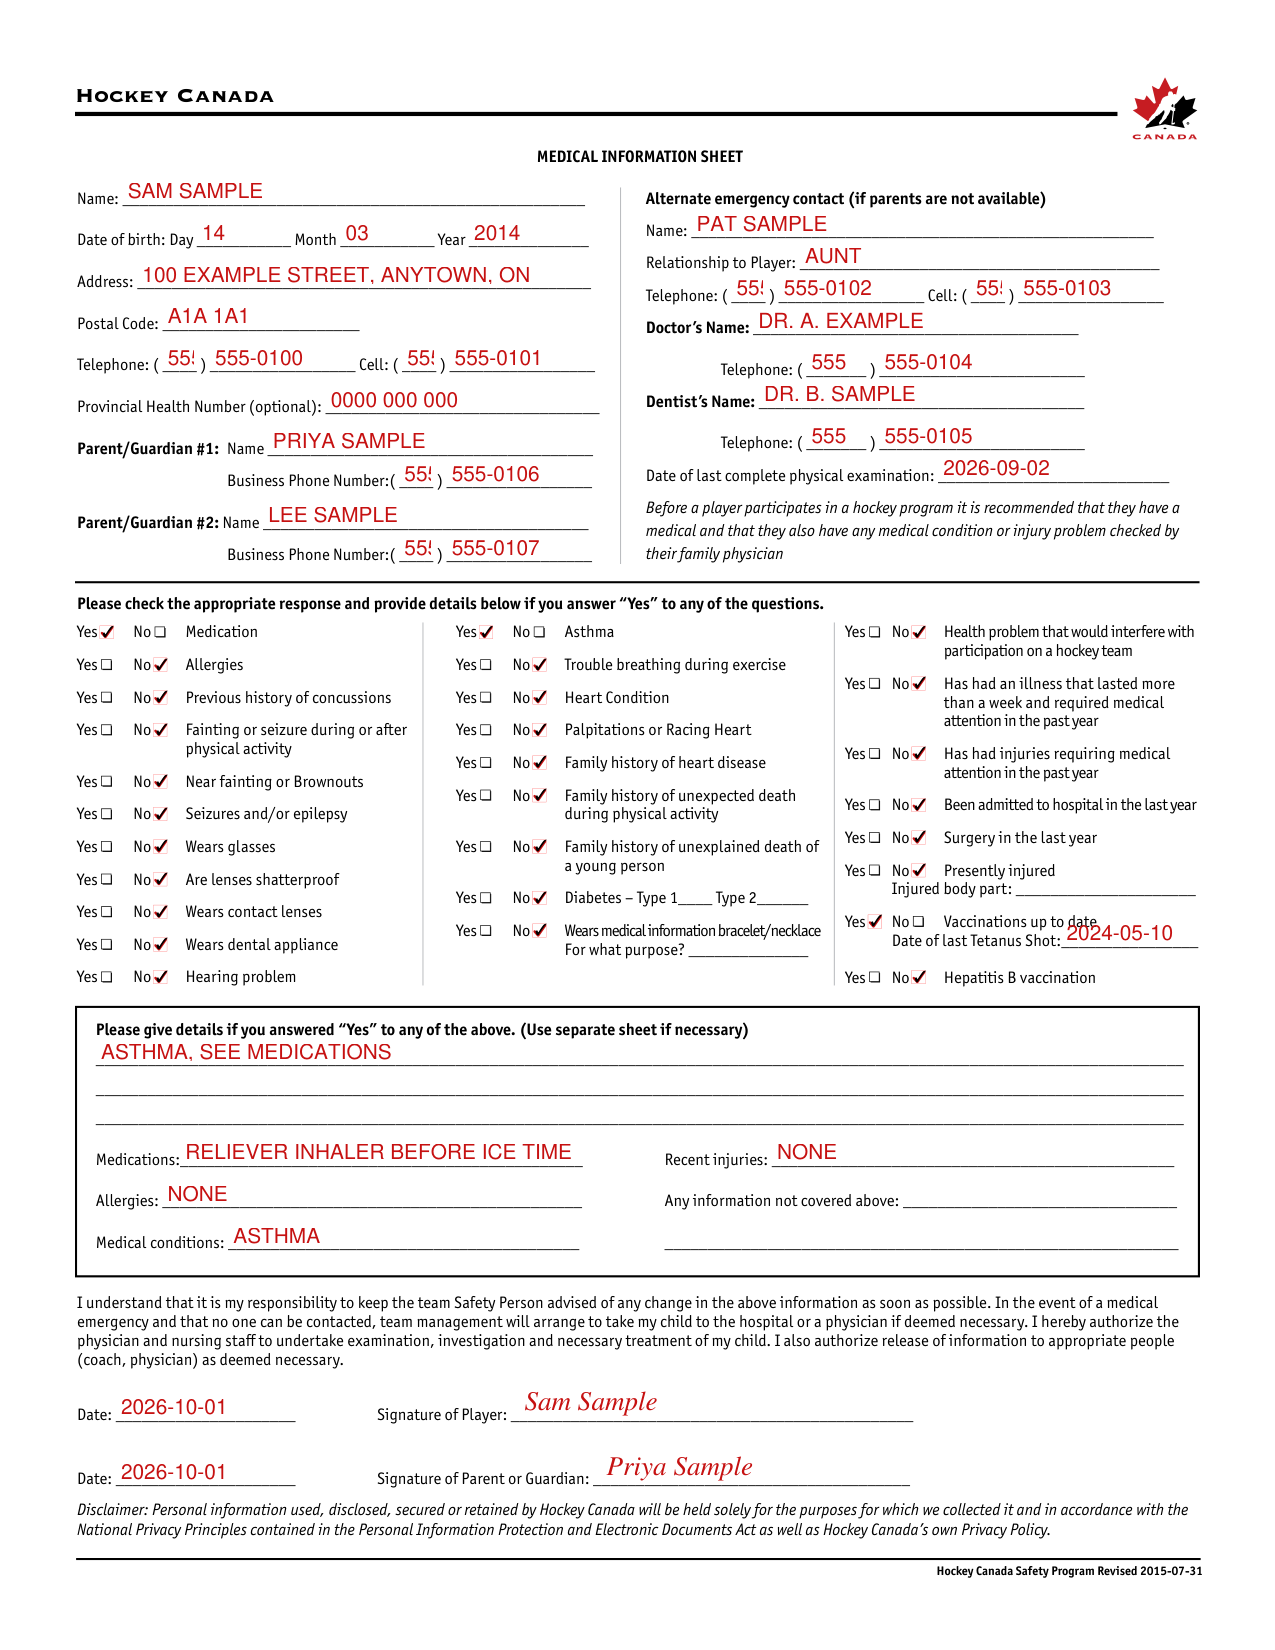
How to fill out Hockey Canada Medical Information Sheet, box by box
Name, Date of birth, Address, Postal Code, Telephone and Cell

Enter the Name, the Date of birth (Day, Month and Year), the Address and the Postal Code.
Enter the Telephone and the Cell number.
Alternate emergency contact (if parents are not available)

Under Alternate emergency contact (if parents are not available), enter the Name and the Relationship to Player.
For the Alternate emergency contact (if parents are not available), enter the Telephone and the Cell number.
Doctor's Name and Dentist's Name
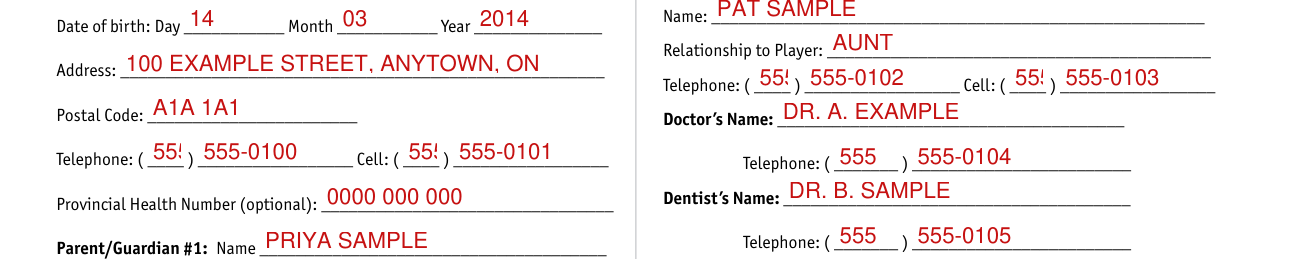
Enter the Doctor's Name and the Telephone.
Enter the Dentist's Name and the Telephone.
Provincial Health Number (optional)

Provincial Health Number is optional.
Parent/Guardian #1 and Parent/Guardian #2

For Parent/Guardian #1, enter the Name and the Business Phone Number.
For Parent/Guardian #2, enter the Name and the Business Phone Number.
Date of last complete physical examination

Before a player participates in a hockey program it is recommended that they have a medical and that they also have any medical condition or injury problem checked by their family physician.
Enter the Date of last complete physical examination.
Check the appropriate response

Please check the appropriate response and provide details if you answer “Yes” to any of the questions.
Check Yes or No for Medication, Asthma, Health problem that would interfere with participation on a hockey team, Allergies, Trouble breathing during exercise, Has had an illness that lasted more than a week and required medical attention in the past year, and Previous history of concussions.
Check Yes or No for Heart Condition, Fainting or seizure during or after physical activity, Palpitations or Racing Heart, Has had injuries requiring medical attention in the past year, Family history of heart disease, Near fainting or Brownouts, and Family history of unexpected death during physical activity.
Check Yes or No for Been admitted to hospital in the last year, Seizures and/or epilepsy, Surgery in the last year, Wears glasses, Family history of unexplained death of a young person, Are lenses shatterproof, and Wears contact lenses.
Check Yes or No for Wears dental appliance, Hearing problem, and Hepatitis B vaccination.
Check Yes or No for Presently injured, and enter the Injured body part.
Check Yes or No for Diabetes, and enter Type 1 and Type 2.
Check Yes or No for Vaccinations up to date, and enter the Date of last Tetanus Shot.
Check Yes or No for Wears medical information bracelet/necklace, and enter For what purpose?
Please give details

Please give details if you answered “Yes”. (Use separate sheet if necessary)
Enter Medications, Recent injuries, Allergies, Any information not covered, and Medical conditions.
Signature of Player and Signature of Parent or Guardian

I understand that it is my responsibility to keep the team Safety Person advised of any change in the information as soon as possible. In the event of a medical emergency and that no one can be contacted, team management will arrange to take my child to the hospital or a physician if deemed necessary. I hereby authorize the physician and nursing staff to undertake examination, investigation and necessary treatment of my child. I also authorize release of information to appropriate people (coach, physician) as deemed necessary.
Enter the Date and the Signature of Player, and the Date and the Signature of Parent or Guardian.
Sources
[1] Hockey Canada Safety Program Medical Information Sheet (Revised 2015-07-31), Hockey Canada (the Official source link on this page).