

EMSA #111 B at a glance
What it is: EMSA #111 B (Effective 4/1/2017) is the Physician Orders for Life-Sustaining Treatment (POLST) form, approved by the California Emergency Medical Services Authority in cooperation with the statewide POLST Task Force.
Where to get it: For more information or a copy of the form, visit www.caPOLST.org.
Completing a POLST form is voluntary.
A filled-in EMSA #111 B example: a physician completes a POLST for a patient with capacity
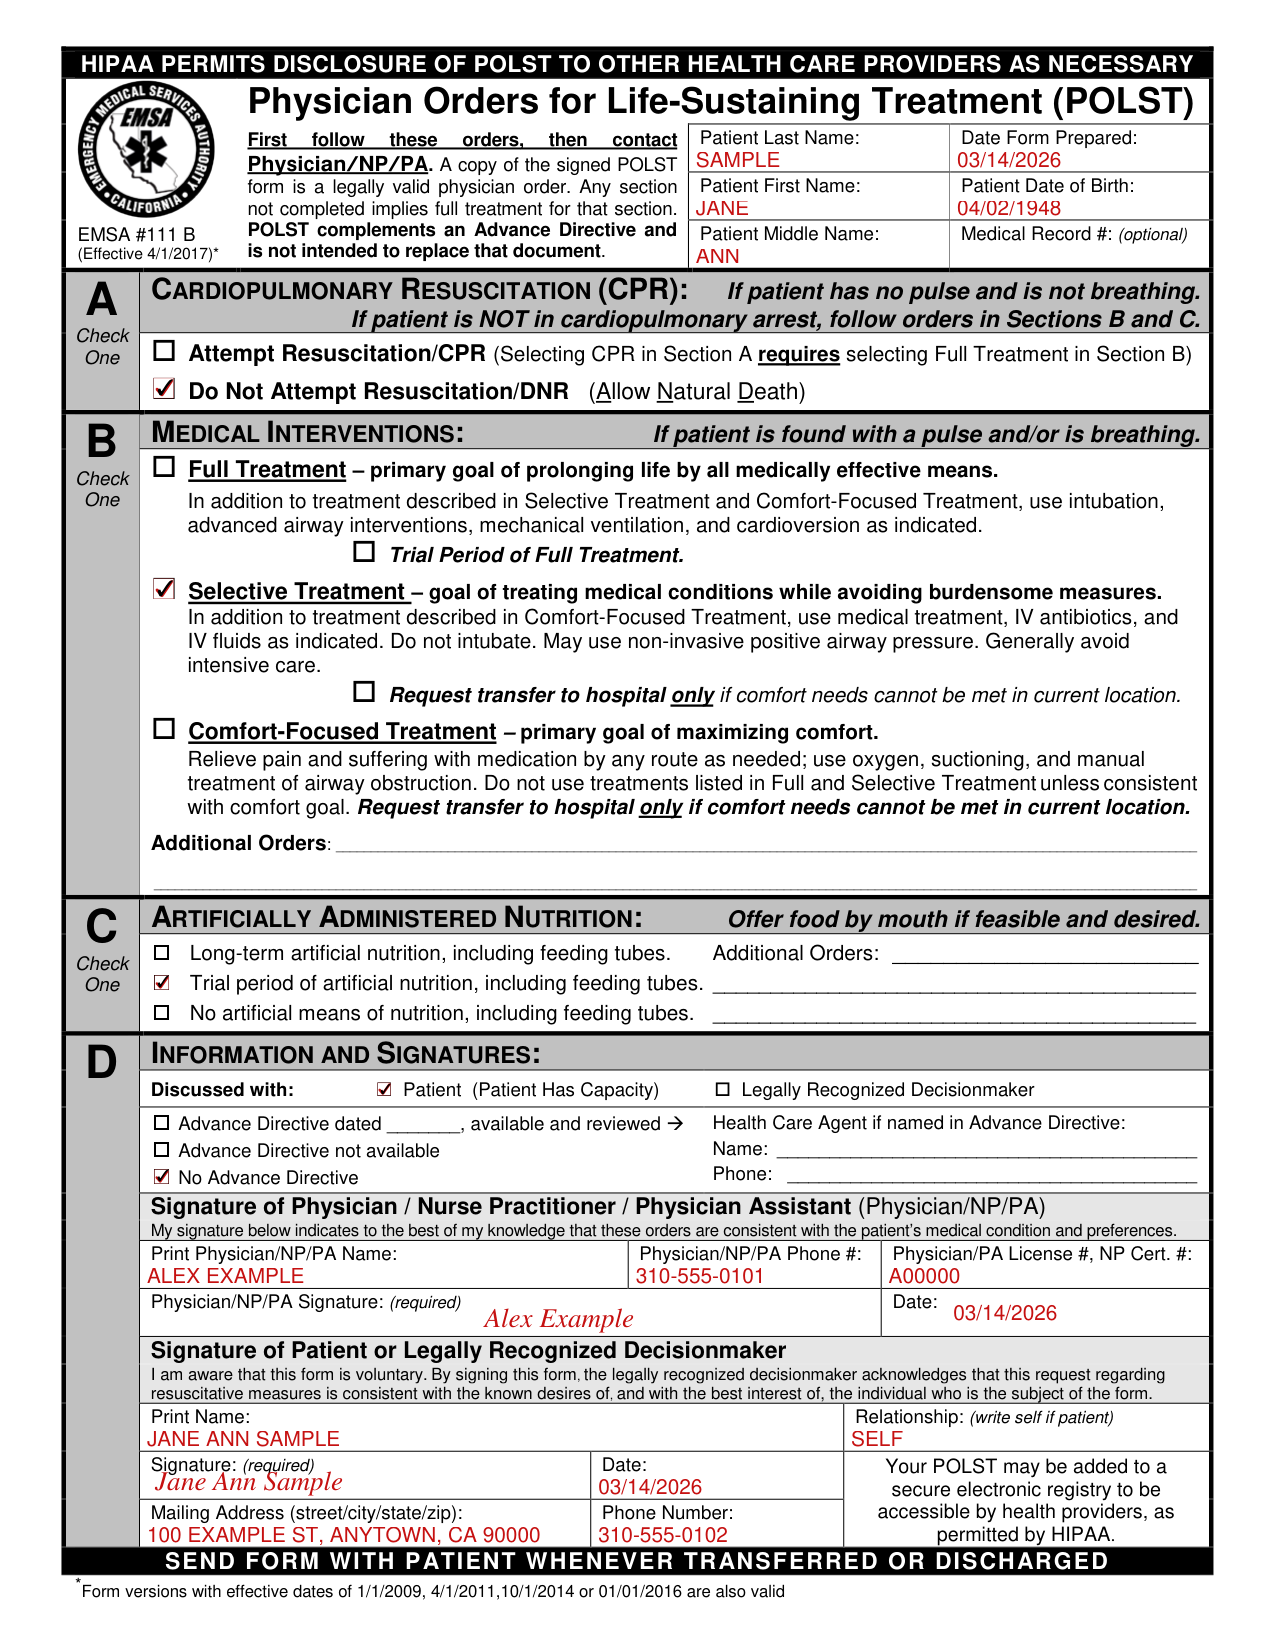
How to fill out EMSA #111 B, box by box
Patient Name, Date Form Prepared, Date of Birth and Medical Record #
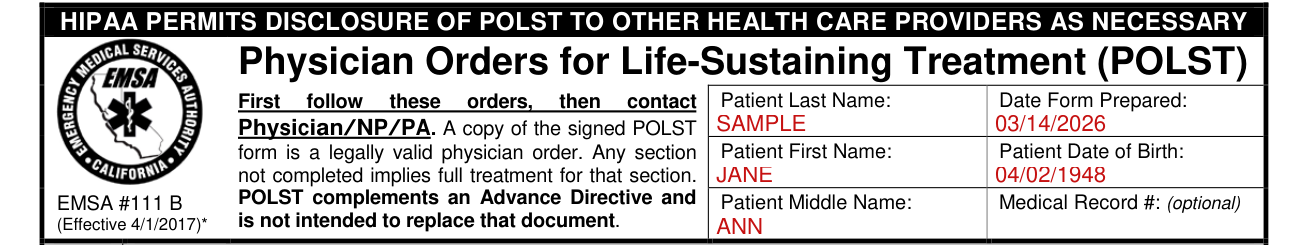
Enter the Patient Last Name, Patient First Name and Patient Middle Name. Enter the Date Form Prepared and the Patient Date of Birth. The Medical Record # is optional.
Section A: Cardiopulmonary Resuscitation (CPR)

If patient has no pulse and is not breathing, check one: Attempt Resuscitation/CPR or Do Not Attempt Resuscitation/DNR (Allow Natural Death).
If patient is not in cardiopulmonary arrest, follow orders in Sections B and C.
Selecting CPR in Section A requires selecting Full Treatment in Section B.
If found pulseless and not breathing, no defibrillator (including automated external defibrillators) or chest compressions should be used on a patient who has chosen Do Not Attempt Resuscitation.
Section B: Medical Interventions

If patient is found with a pulse and/or is breathing, check one.
Full Treatment: primary goal of prolonging life by all medically effective means. In addition to treatment described in Selective Treatment and Comfort-Focused Treatment, use intubation, advanced airway interventions, mechanical ventilation, and cardioversion as indicated. Next is the box Trial Period of Full Treatment.
Selective Treatment: goal of treating medical conditions while avoiding burdensome measures. In addition to treatment described in Comfort-Focused Treatment, use medical treatment, IV antibiotics, and IV fluids as indicated. Do not intubate. May use non-invasive positive airway pressure. Generally avoid intensive care.
Non-invasive positive airway pressure includes continuous positive airway pressure (CPAP), bi-level positive airway pressure (BiPAP), and bag valve mask (BVM) assisted respirations.
Comfort-Focused Treatment: primary goal of maximizing comfort. Relieve pain and suffering with medication by any route as needed; use oxygen, suctioning, and manual treatment of airway obstruction. Do not use treatments listed in Full and Selective Treatment unless consistent with comfort goal. Request transfer to hospital only if comfort needs cannot be met in current location.
When comfort cannot be achieved in the current setting, the patient, including someone with Comfort-Focused Treatment, should be transferred to a setting able to provide comfort (e.g., treatment of a hip fracture).
IV antibiotics and hydration generally are not Comfort-Focused Treatment.
Treatment of dehydration prolongs life.
If a patient desires IV fluids, indicate Selective Treatment or Full Treatment.
Write Additional Orders on the two lines. Depending on local EMS protocol, Additional Orders written in Section B may not be implemented by EMS personnel.
Section C: Artificially Administered Nutrition
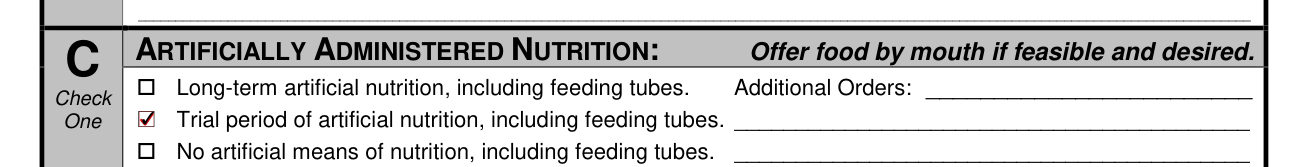
Offer food by mouth if feasible and desired.
Check one: Long-term artificial nutrition, including feeding tubes; Trial period of artificial nutrition, including feeding tubes; or No artificial means of nutrition, including feeding tubes. Write Additional Orders on the lines.
Discussed with

Under Discussed with, the boxes are Patient (Patient Has Capacity) and Legally Recognized Decisionmaker.
Advance Directive and Health Care Agent
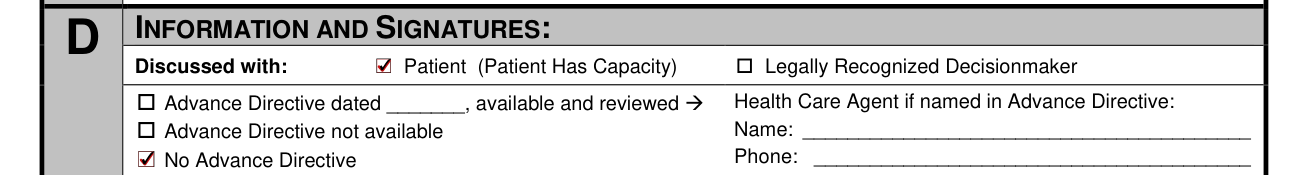
The Advance Directive boxes are: Advance Directive dated (write the date), available and reviewed; Advance Directive not available; and No Advance Directive.
Health Care Agent if named in Advance Directive: write the Name and Phone.
When available, review the Advance Directive and POLST form to ensure consistency, and update forms appropriately to resolve any conflicts.
Signature of Physician, Nurse Practitioner or Physician Assistant

Print the Physician/NP/PA Name. Write the Physician/NP/PA Phone # and the Physician/PA License #, NP Cert. #.
The Physician/NP/PA Signature is required. Write the Date.
The Physician/NP/PA signature indicates, to the best of the signer's knowledge, that these orders are consistent with the patient's medical condition and preferences.
Signature of Patient or Legally Recognized Decisionmaker
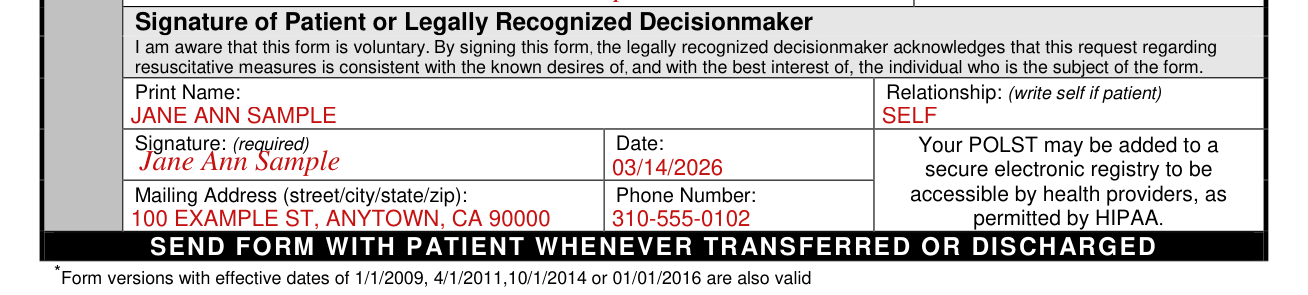
By signing this form, the legally recognized decisionmaker acknowledges that this request regarding resuscitative measures is consistent with the known desires of, and with the best interest of, the individual who is the subject of the form.
Print Name and Relationship; write self if patient.
The Signature is required. Write the Date.
Write the Mailing Address (street/city/state/zip) and Phone Number.
A legally recognized decisionmaker may include a court-appointed conservator or guardian, agent designated in an Advance Directive, orally designated surrogate, spouse, registered domestic partner, parent of a minor, closest available relative, or person whom the patient's physician/NP/PA believes best knows what is in the patient's best interest and will make decisions in accordance with the patient's expressed wishes and values to the extent known.
A legally recognized decisionmaker may execute the POLST form only if the patient lacks capacity or has designated that the decisionmaker's authority is effective immediately.
Patient Information (page 2)

Under Patient Information, enter the Name (last, first, middle), the Date of Birth and the Gender, M or F.
NP/PA's Supervising Physician and Preparer Name

Enter the Name of the NP/PA's Supervising Physician. Enter the Preparer Name (if other than signing Physician/NP/PA): the Name/Title and the Phone #.
Additional Contact

Under Additional Contact, check None or write the Name, Relationship to Patient and Phone #.
More rules for EMSA #111 B
HIPAA permits disclosure of POLST to other health care providers as necessary.
First follow these orders, then contact Physician/NP/PA.
Use of original form is strongly encouraged.
Form versions with effective dates of 1/1/2009, 4/1/2011, 10/1/2014 or 01/01/2016 are also valid.
If your situation is different
A section is incomplete
Any incomplete section of POLST implies full treatment for that section.
A translated form is used
If a translated form is used with patient or decisionmaker, attach it to the signed English POLST form.
Verbal orders
Verbal orders are acceptable with follow-up signature by physician/NP/PA in accordance with facility/community policy.
Reviewing POLST
It is recommended that POLST be reviewed periodically. Review is recommended when: the patient is transferred from one care setting or care level to another, or there is a substantial change in the patient's health status, or the patient's treatment preferences change.
Modifying and Voiding POLST
A patient with capacity can, at any time, request alternative treatment or revoke a POLST by any means that indicates intent to revoke.
It is recommended that revocation be documented by drawing a line through Sections A through D, writing VOID in large letters, and signing and dating the line.
A legally recognized decisionmaker may request to modify the orders, in collaboration with the physician/NP/PA, based on the known desires of the patient or, if unknown, the patient's best interests.
Common questions about EMSA #111 B
Does a POLST have to be on pink paper?
A copy should be retained in patient's medical record, on Ultra Pink paper when possible. Photocopies and FAXes of signed POLST forms are legal and valid.
Is a POLST form legally binding?
California law requires that a POLST form be followed by healthcare providers, and provides immunity to those who comply in good faith. A copy of the signed POLST form is a legally valid physician order.
Can a nurse fill out a POLST?
POLST must be completed by a health care provider based on patient preferences and medical indications. To be valid a POLST form must be signed by (1) a physician, or by a nurse practitioner or a physician assistant acting under the supervision of a physician and within the scope of practice authorized by law and (2) the patient or decisionmaker.
Where do I file it?
Send the form with the patient whenever transferred or discharged. Your POLST may be added to a secure electronic registry to be accessible by health providers, as permitted by HIPAA.
When is this form not the right one?
POLST does not replace the Advance Directive.
Sources
[1] EMSA #111 B (Effective 4/1/2017), Physician Orders for Life-Sustaining Treatment (POLST), California Emergency Medical Services Authority (the Official source link on this page).
