

Physical Therapy Observation Hours Verification Form at a glance
What it is: Physical Therapy Observation Hours VERIFICATION FORM: Extra Form is only intended for use by individuals who need a PT signature for a future admissions cycle.
Who signs: The Signature of Physical Therapist line is signed by the physical therapist.
What to bring and attach to Physical Therapy Observation Hours Verification Form
Once you are ready to apply via PTCAS, enter all of your PT experiences on the PTCAS application exactly as they appear on this signed form. Select "paper" verification type.
The PT does not need to sign the new (bar-coded) PTCAS verification form, if no changes.
A filled-in Physical Therapy Observation Hours Verification Form example: a PT verifies volunteer observation hours at a clinic

How to fill out Physical Therapy Observation Hours Verification Form, box by box
Name of Applicant and Name of Facility

Enter the Name of Applicant. Leave the PTCAS ID# blank.
Enter the Name of Facility.
Enter the Street Address for Facility.
Enter the City, State, Zip/ Postal Code and Country.
Name of Physical Therapist
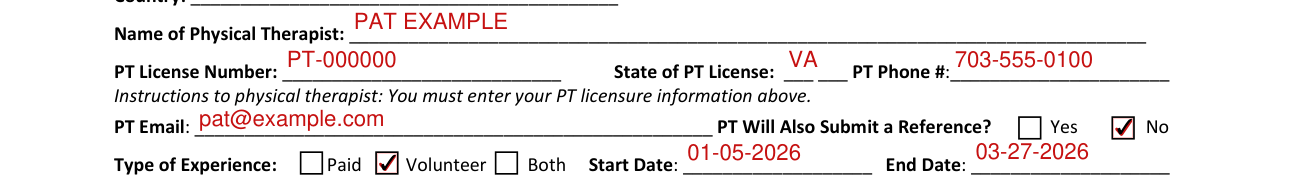
Enter the Name of Physical Therapist.
Physical therapist: you must enter your PT licensure information, the PT License Number, the State of PT License and the PT Phone #.
Enter the PT Email. Mark Yes or No for PT Will Also Submit a Reference?
Type of Experience

For Type of Experience, mark Paid, Volunteer or Both. Enter the Start Date and the End Date.
PT Settings and Hours of Experience
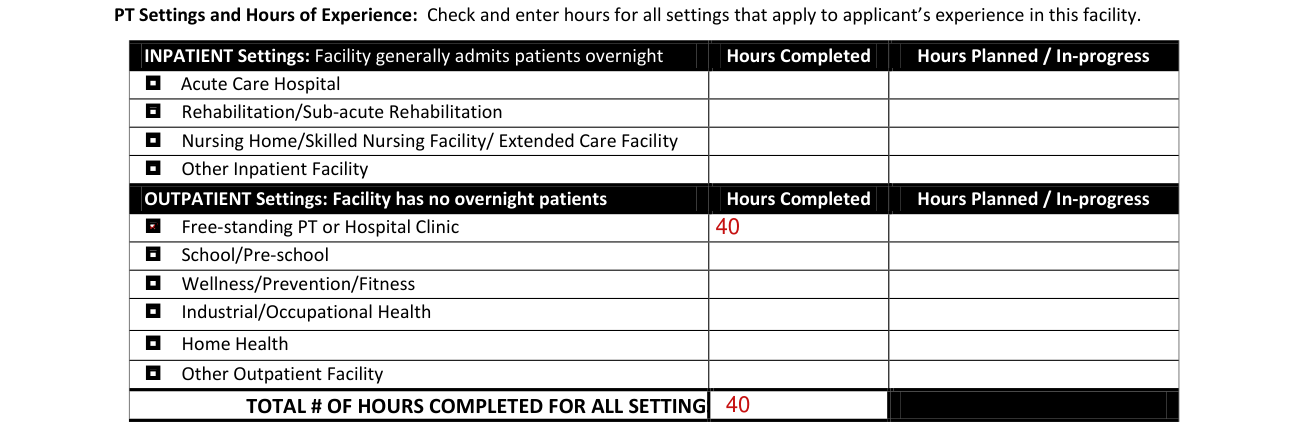
Check and enter hours for all settings that apply to the applicant's experience in this facility.
Under INPATIENT Settings (facility generally admits patients overnight), enter Hours Completed and Hours Planned / In-progress for Acute Care Hospital, Rehabilitation/Sub-acute Rehabilitation, Nursing Home/Skilled Nursing Facility/ Extended Care Facility or Other Inpatient Facility.
Under OUTPATIENT Settings (facility has no overnight patients), enter Hours Completed and Hours Planned / In-progress for Free-standing PT or Hospital Clinic, School/Pre-school, Wellness/Prevention/Fitness, Industrial/Occupational Health, Home Health or Other Outpatient Facility.
Enter the TOTAL # OF HOURS COMPLETED FOR ALL SETTINGS.
PT Patient Diagnoses/Populations Observed

Check all that apply to the applicant's experience at this facility. If the applicant did not directly observe a PT with a particular patient population, do not check box, regardless of whether the facility provides related services.
The boxes are General Orthopedic (musculoskeletal), Neurologic (neuromuscular), Cardiovascular / Pulmonary, Integumentary (wound management), Geriatrics, Pediatrics, Sports, Aquatics, WoŵeŶ's Health and Other.
How you think this person would perform as a health care provider

Physical Therapist, taking into consideration these characteristics, how do you think this person would perform as a health care provider? I highly recommend this applicant as a health care provider. I recommend this applicant as a health care provider. I recommend this applicant as a health care provider, but with some reservations. I am not able to recommend this applicant as a health care provider. I do not have sufficient information about the applicant to respond to this question.
Signature of Physical Therapist

The physical therapist signs the Signature of Physical Therapist line and enters the Date next to it.
More rules for Physical Therapy Observation Hours Verification Form
If there are any changes to your PT experience after this form is signed, a PT must sign a new form to verify your revised hours.
Before you go
Some programs require a licensed PT to verify your physical therapy experiences.
If required, provide this completed form to the appropriate PT for signature.
Type or neatly handwrite your information directly onto this form, leaving your PTCAS ID number blank.
Common questions about Physical Therapy Observation Hours Verification Form
Where do I file it?
Print and attach the new (bar-coded) PTCAS verification form to this signed form. Send both forms in a single envelope to PTCAS.
Sources
[1] Physical Therapy Observation Hours VERIFICATION FORM: Extra Form (PTCAS), the served file; no edition is printed (the Official source link on this page).
