

QME Form 111 at a glance
What it is: The Qualified Medical Evaluator's Findings Summary Form is for unrepresented injured employee cases only.
Who signs: QME Signature: Remember under the Labor Code, all your reports must be signed under the penalty of perjury.
The QME is required by Labor Code section 4062.3(i) to summarize the medical findings from the comprehensive medical-legal evaluation on the form prescribed by the Administrative Director.
A filled-in QME Form 111 example: a QME summarizes findings
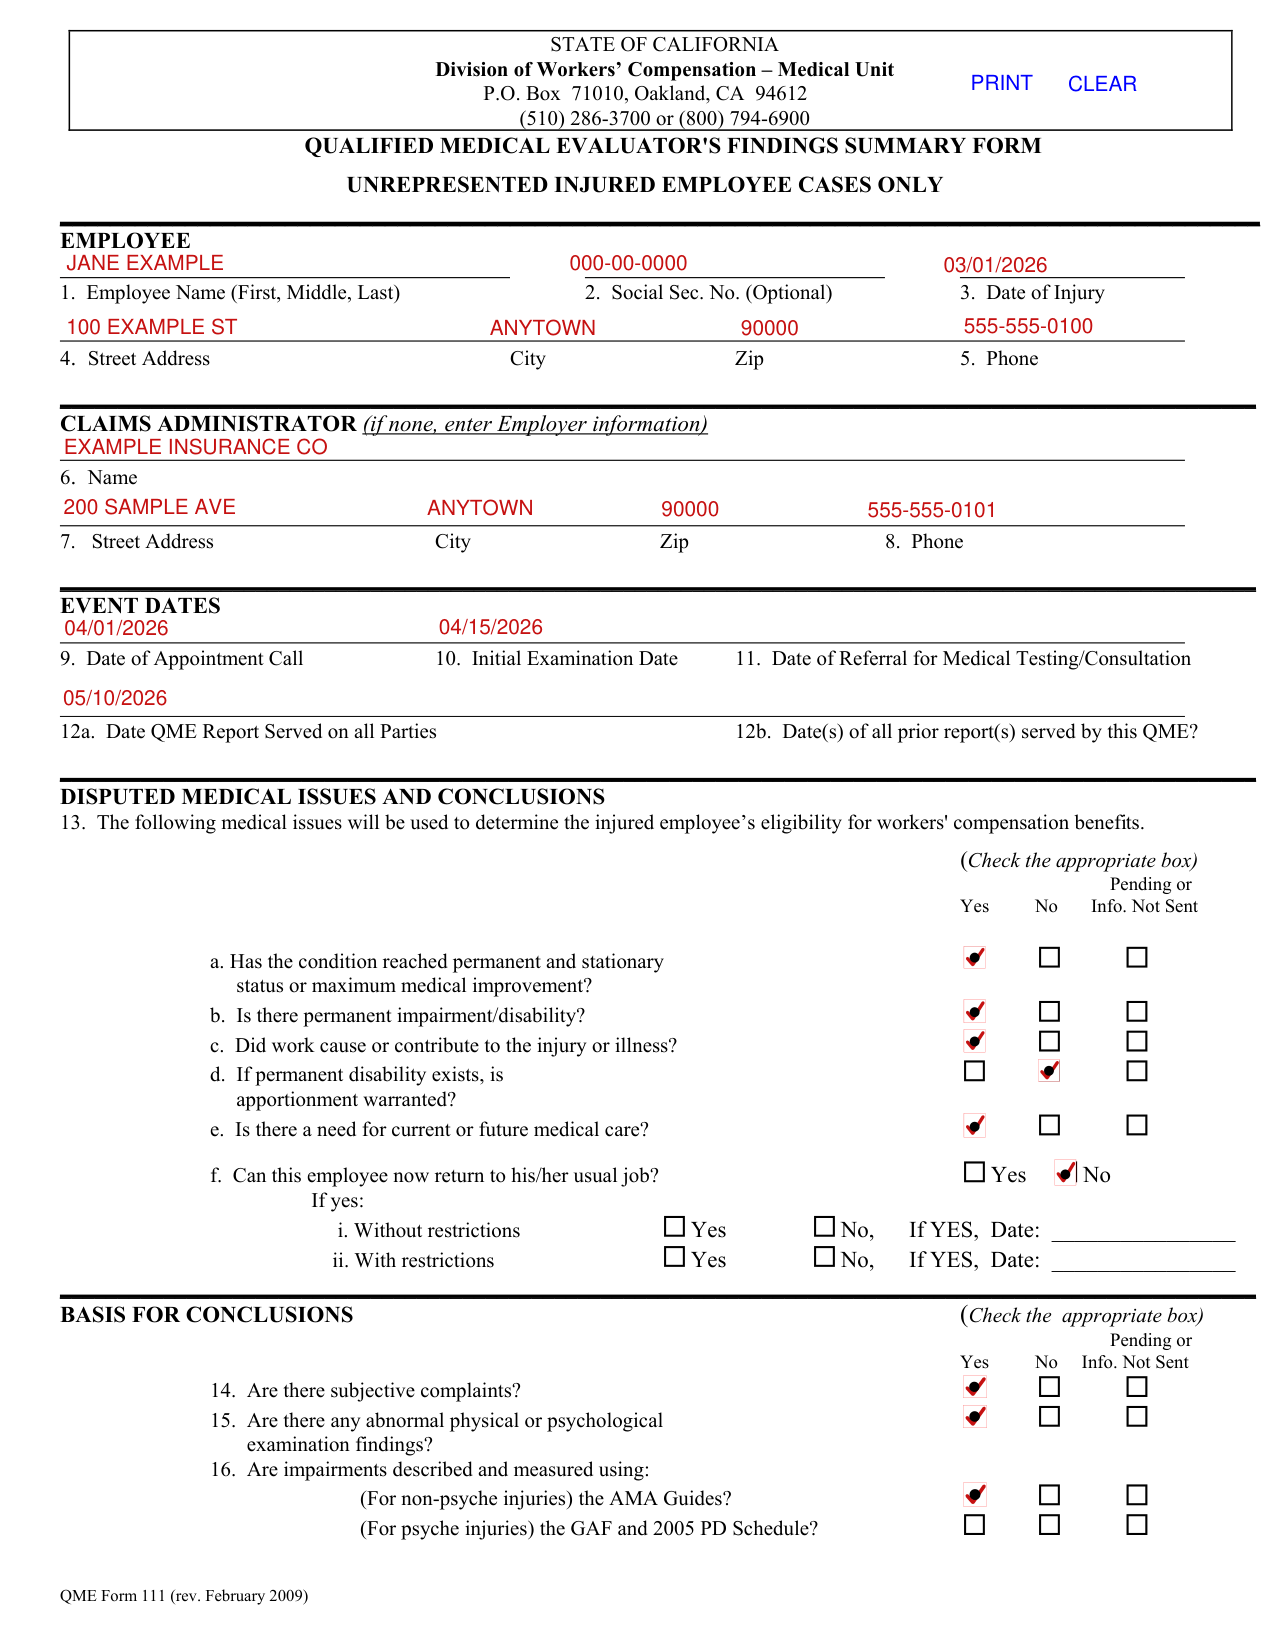
How to fill out QME Form 111, box by box
Employee
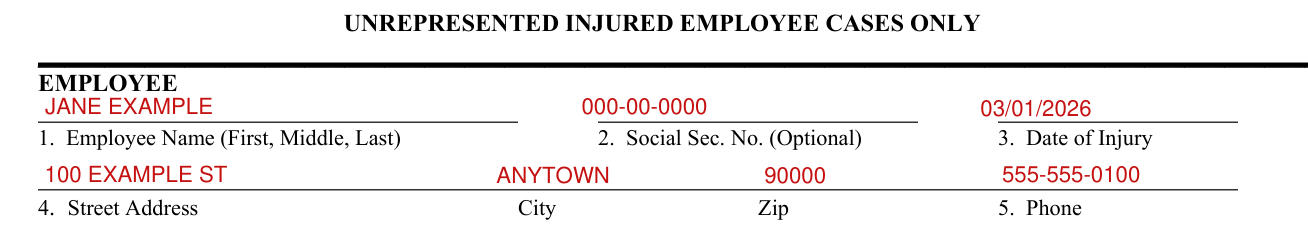
Fill in the employee's full name, address, telephone number and date of injury: 1. Employee Name (First, Middle, Last), 2. Social Sec. No. (Optional), 3. Date of Injury, 4. Street Address City Zip and 5. Phone.
Please complete the form in its entirety.
Claims administrator (if none, enter Employer information)
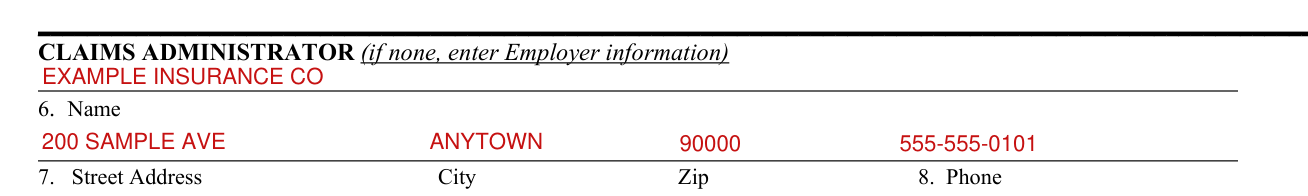
For the CLAIMS ADMINISTRATOR (if none, enter Employer information), enter 6. Name, 7. Street Address City Zip and 8. Phone.
Event dates
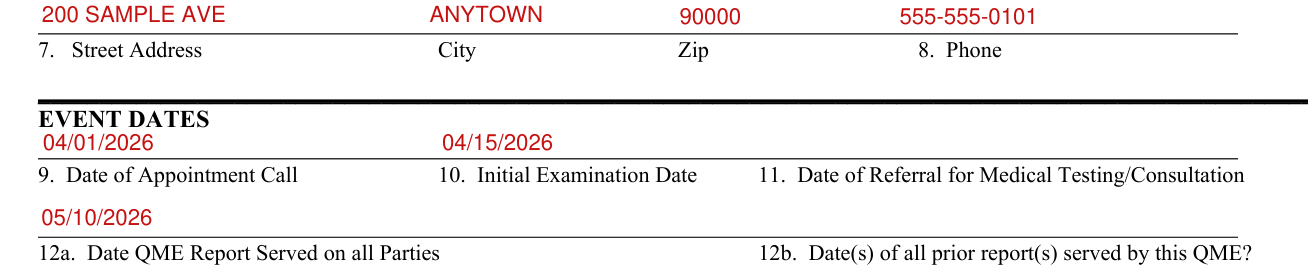
Complete dates that patient called for an appointment, date of initial examination, date referred for consultation(s), if any, and date(s) report(s) served on all parties. Supplying these dates is a legal requirement.
Enter 9. Date of Appointment Call, 10. Initial Examination Date, 11. Date of Referral for Medical Testing/Consultation, 12a. Date QME Report Served on all Parties and 12b. Date(s) of all prior report(s) served by this QME.
Disputed medical issues and conclusions
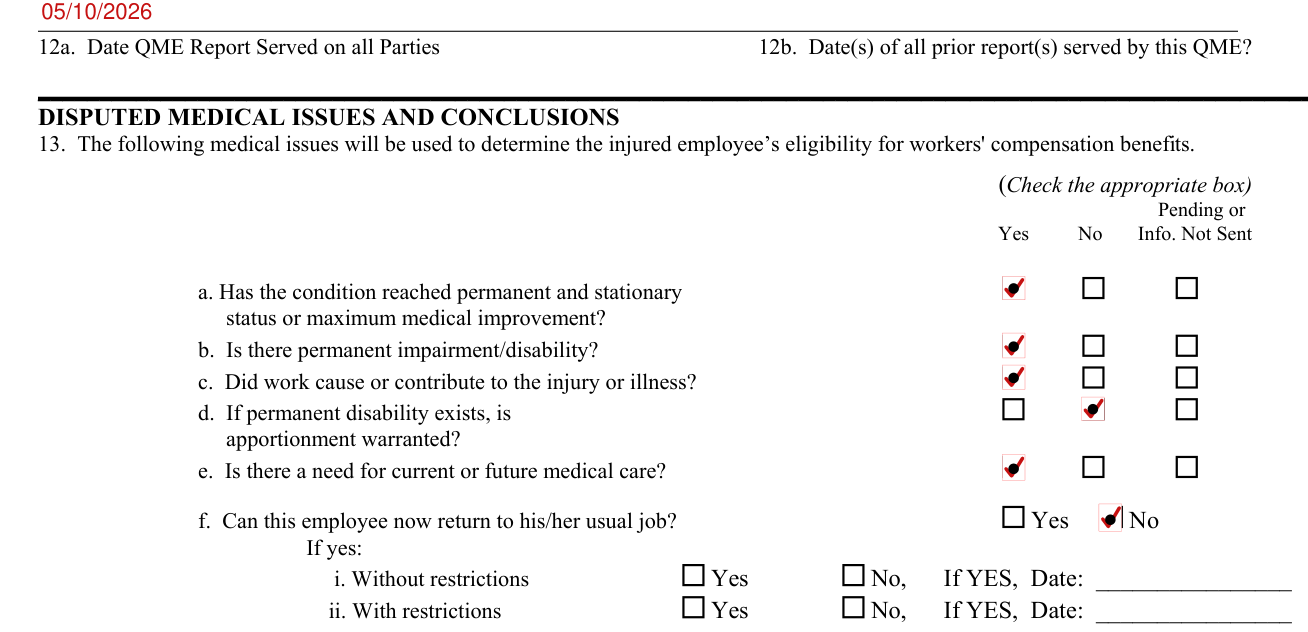
Complete this section by checking appropriate box and stating what page(s) or section of the medical legal report contain the narrative for details.
Under 13. The following medical issues will be used to determine the injured employee's eligibility for workers' compensation benefits, check the appropriate box (Yes, No or Pending or Info. Not Sent) for a. Has the condition reached permanent and stationary status or maximum medical improvement? b. Is there permanent impairment/disability? c. Did work cause or contribute to the injury or illness? d. If permanent disability exists, is apportionment warranted? e. Is there a need for current or future medical care?
If diagnostic or laboratory tests have been ordered and the results or a medical records request is pending, check that box.
If you cannot render opinions because of pending information, please complete and serve the report to comply with the 30-day time requirement and state what issues could not be evaluated.
f. Can this employee now return to his/her usual job? Yes No. If yes: i. Without restrictions Yes No, if YES, enter the Date; ii. With restrictions Yes No, if YES, enter the Date.
Basis for Conclusions 14 to 16

Check appropriate box for each question on form: 14. Are there subjective complaints? 15. Are there any abnormal physical or psychological examination findings? 16. Are impairments described and measured using: (For non-psyche injuries) the AMA Guides? (For psyche injuries) the GAF and 2005 PD Schedule?
Each evaluator is expected to address permanent impairment consistent with the AMA guides for the evaluator's specialty, or for disputed injuries to the psyche consistent with the global assessment of functioning (GAF) as directed in the 2005 Permanent Disability Schedule adopted by the Administrative Director effective 1/1/2005.
Basis for Conclusions 17 to 21

Check appropriate box (Yes, No or Pending or Info. Not Sent) for 17. If the AMA Guides are used, are percentages of impairment stated? 18. Are there any relevant diagnostic test results (x-ray/laboratory)? 19. What are the diagnoses? (List) 20. Were medical records reviewed? 21. Were other physicians consulted?
For diagnoses, please briefly summarize the diagnoses in lay terms where possible, except when you deem that not advisable in disputed claims involving injury to the psyche. Also, list the name and specialty for other physicians who provided information used in the medical legal report.
Need for Additional Evaluation in Another Specialty

Need for Additional Evaluation in Another Specialty: Labor Code section 4062.3 directs each evaluator to address all contested medical issues arising from all injuries reported on one or more claim forms prior to the evaluator's initial evaluation.
In the event there are contested medical issues outside of the scope of your licensure or clinical competence that require evaluation by a physician in a different specialty, complete the information required in questions 22 through 24, and serve a copy of your report on the Medical Unit of DWC.
22. Are there any unresolved disputed issues beyond the scope of your licensure or clinical competence that should be addressed by an evaluator in a different specialty? 23. If the answer to # 22 is yes, what disputed issue(s)? 24. Based on the answer in # 23, what specialty (or specialties)?
QME signature

Sign on the QME Signature line and enter the Date, the Name and Specialty, the Street Address, City and Zip, and the Phone and Cal. License No.
Declaration of Service of Medical - Legal Report

Declaration of Service of Medical - Legal Report (Lab. Code § 4062.3(i)): print the Name after I, declare: I am over the age of 18 and I am not a party to this case. Enter your business address after My business address is.
On the Date, you served this QME Findings Summary Form with the original, or a true and correct copy of the original, comprehensive medical-legal report, which is attached, on each of the persons or firms named in Addressee and Address, by placing it in a sealed envelope addressed to the person or firm named in Addressee and Address.
Means of service, date and addressee

For each addressee, Enter A - E as appropriate under Means of service, with the Date and Addressee and Address.
A depositing the sealed envelope with the U.S. Postal Service with the postage fully prepaid.
B placing the sealed envelope for collection and mailing following ordinary business practices.
C placing the sealed envelope for collection and overnight delivery at an office or a regularly utilized drop box of the overnight delivery carrier.
D placing the sealed envelope for pick up by a professional messenger service for service. (Messenger must return to you a completed declaration of personal service.)
E personally delivering the sealed envelope to the person or firm named in Addressee and Address at the address shown in Addressee and Address.
When report addresses PD

When report addresses PD: enter the Disability Evaluation Unit, DWC, address.
Signature of Declarant

Please complete the proof of service to show the date the report was served on the parties and the Disability Evaluation Unit.
Sign under "I declare under penalty of perjury under the laws of the State of California that the foregoing is true and correct." and enter the Date Signed.
Sign the Signature of Declarant line and enter the Print Name.
More rules for QME Form 111
The QME is required to serve the medical legal report and this form on the employee (unless the claim involves a disputed injury to the psyche and section 36.5 of Title 8 of the California Code of Regulations applies and provides for a different method of service), the claims administrator (if none, the employer) and whenever the report finds permanent impairment and permanent disability, on the Disability Evaluation Unit (DEU) having jurisdiction over the employee's area of residence.
Common questions about QME Form 111
Is there a deadline?
Labor Code sections 139.2(j)(1)(A) and 4062.3 (i) and section 38 of Title 8 of the California Code of Regulations require the QME to serve the medical-legal report and this form on the claims administrator, or if none the employer, and the injured worker (except when section 36.5 of Title 8 of the California Code of Regulations applies) within 30 days from the commencement of the examination, unless certain conditions are met.
When is this form not the right one?
Use this form only when the injured employee is unrepresented.
Sources
[1] QME Form 111 (rev. February 2009), Qualified Medical Evaluator's Findings Summary Form, Division of Workers' Compensation, California Department of Industrial Relations (the Official source link on this page).