

Refusal of Medical Treatment Form at a glance
What it is: Refusal of Medical Treatment Form, a notice of injury and refusal of medical care, for an employee who has been offered the opportunity to have medical care for the stated injury by the employer.
Who signs: Employee's Signature / Firma de empleado, with Date / Fecha. Supervisor's or Foreman's signature / Firma de supervisor o mayordomo, with Date / Fecha. Witness Signature or Name, with Date.
A filled-in Refusal of Medical Treatment Form example: an employee refuses care for a hand injury

How to fill out Refusal of Medical Treatment Form, box by box
Employee, injury and time
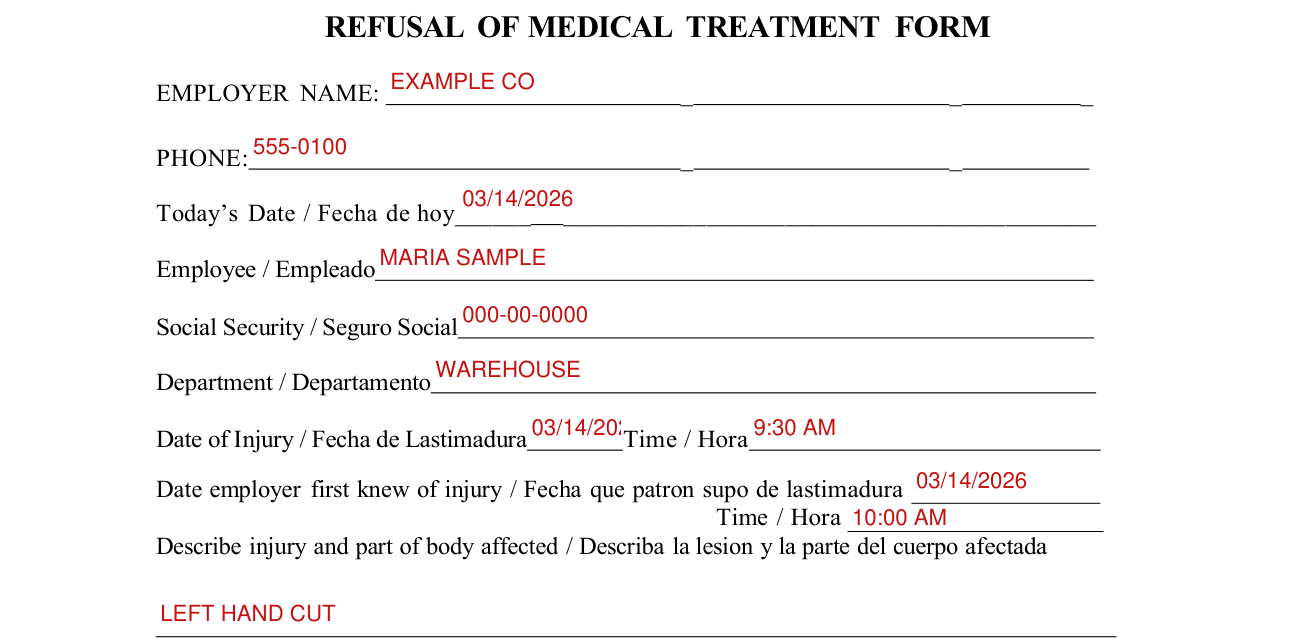
Enter the Employer Name, Phone, Today's Date, Employee, Social Security, Department, Date of Injury, Time, Date employer first knew of injury, Time /Hora, and describe the injury and part of body affected.
Refusing medical care

The employee states: I feel as though I do not require medical care at this time.
Should the employee feel the need to have care, the employee will immediately report to the employer's office to request medical care.
The employee understands this is the obligation under the California Labor Code 4600.
Signing this statement only acknowledges that the employee has been given the opportunity to be examined and treated and in no way waves the right under worker's compensation laws.
The employee also acknowledges the employee has been given a claim form DWC-1 which protects the employee's rights.
Signatures and dates

Employee's Signature / Firma de empleado, with Date / Fecha.
Supervisor's or Foreman's signature / Firma de supervisor o mayordomo, with Date / Fecha.
Witness Signature or Name, with Date.
Sources
[1] Refusal of Medical Treatment Form (the served file; no issuer file found) (the Official source link on this page).
