Provider Treatment Plan PDF Details

The Provider Treatment Plan form stands as a critical document within healthcare and insurance sectors, offering a streamlined manner to submit necessary patient treatment information to insurance companies following incidents necessitating medical attention. This meticulously structured form accommodates both initial and follow-up submissions—a functionality ensuring the continuity and adequacy of patient care information. Fields soliciting information about the patient include name, address, birthdate, Social Security number, insurance details, and specifics regarding the incident leading to the medical condition at hand, such as whether it's related to employment, an auto accident, or other types of accidents. It queries if the patient’s condition has rendered them unable to work, setting a stage for assessing claims related to loss of employment due to the accident. Provider details are equally solicited, encompassing identification, specialty, contact information, and a comprehensive account of the treatment provided, including medical history, diagnosis codes, proposed treatment course, and treatment dates, underscoring the form's role in ensuring a detailed communication between healthcare providers and insurance entities. This form further necessitates the inclusion of supporting documents for the submitted claims, like test results and prescriptions, highlighting its function as a tool for transparency and fraud prevention, as underscored by its stern warning against the submission of false information. Hence, the Provider Treatment Plan form encapsulates a multifaceted approach to documenting and submitting medical treatment plans, serving as a pivotal link between healthcare provision and insurance claims processing.

QuestionAnswer
Form NameProvider Treatment Plan
Form Length1 pages
Fillable?Yes
Fillable fields243
Avg. time to fill out24 min 25 sec
Other namesattending treatment plan, atpt form, attending provider treatment plan 2021, attending provider treatment plan

How to Fill Out Attending Provider Treatment Plan (APTP)

Attending Provider Treatment Plan (APTP) at a glance

What it is: The Attending Provider Treatment Plan, APTP Form Version 2.1 (3/2016), is an Initial Submission or a Follow-up Submission.

Who signs: Sign in Box 39 (Signature of Provider) and enter the Date.

A filled-in Attending Provider Treatment Plan (APTP) example: an initial treatment plan after an auto accident
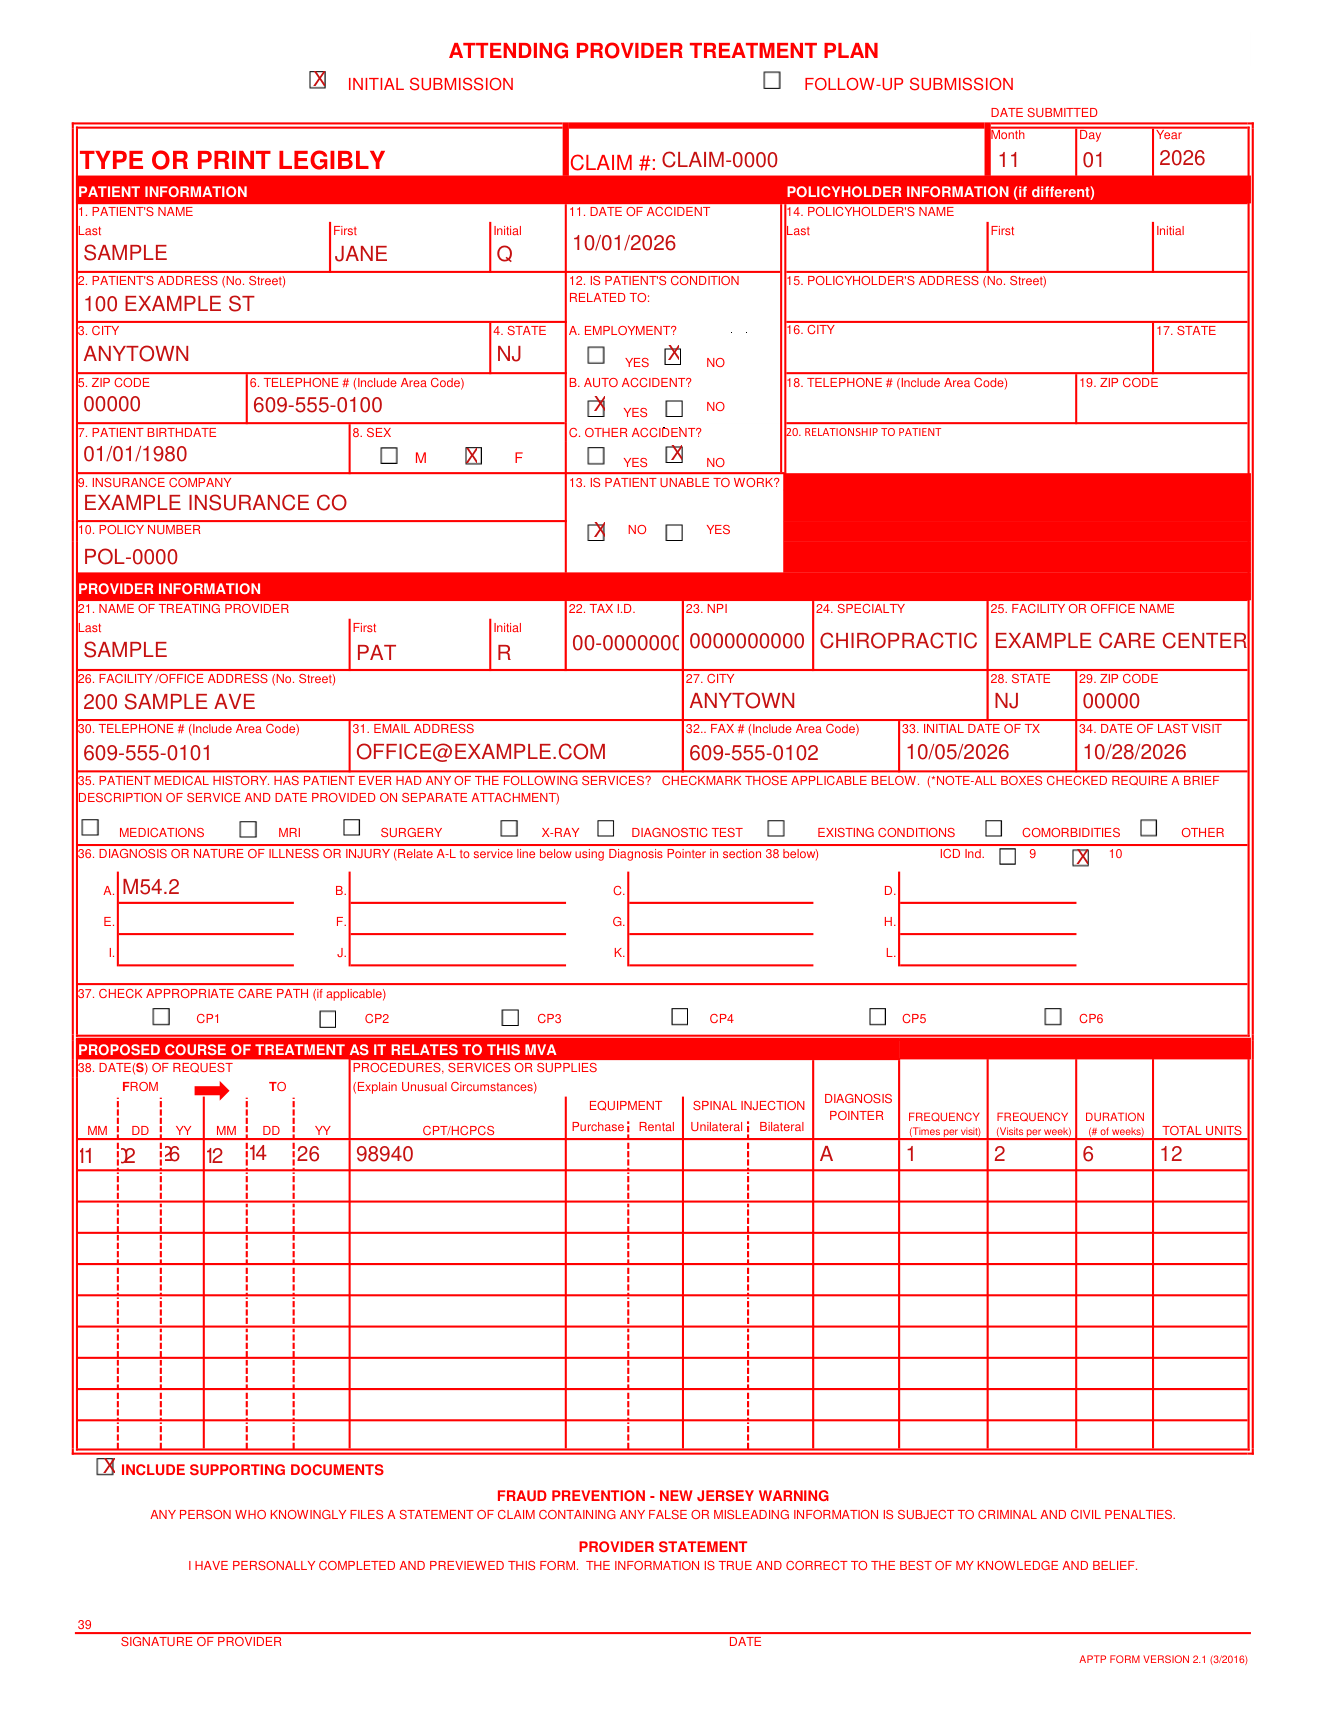
Attending Provider Treatment Plan (APTP) example filled out, example: an initial treatment plan after an auto accident
A treating provider submits an Attending Provider Treatment Plan. The patient was hurt in an auto accident and needs 2 visits a week for 6 weeks. The picture shows the first page filled; all its values are invented. The patient is also the policyholder, so Policyholder Information stays empty. The patient has no listed history, so Patient Medical History stays empty. The injury is not work-related and the patient can work. There is one diagnosis, so the other boxes in Diagnosis or Nature of Illness or Injury stay empty. No care path applies, so Care Path stays empty. Nothing else goes in Proposed Course of Treatment because one service is requested and it is not equipment or a spinal injection. The 2 visits a week for 6 weeks, at 1 time per visit, make 12 total units. The provider includes Supporting Documents.

How to fill out Attending Provider Treatment Plan (APTP), box by box

Initial or follow-up submission and date
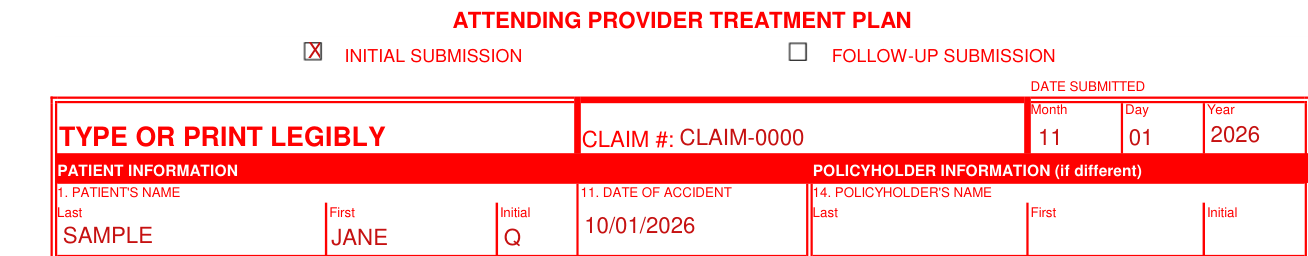
Attending Provider Treatment Plan (APTP) example filled out, initial or follow-up submission and date

Check Initial Submission or Follow-up Submission.

Enter the Date Submitted as Month, Day and Year.

Patient information
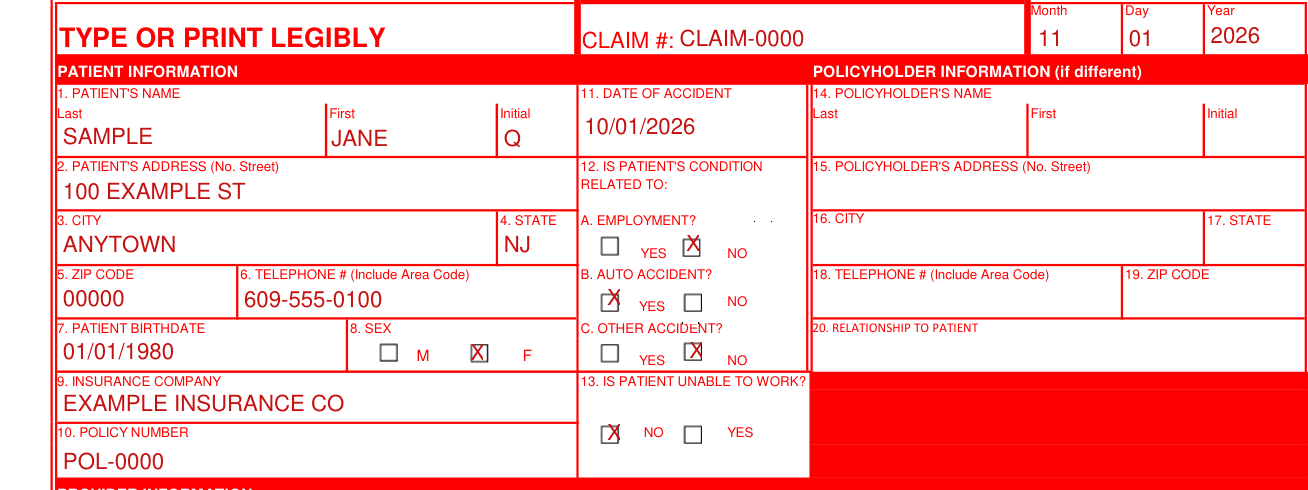
Attending Provider Treatment Plan (APTP) example filled out, patient information

Type or print legibly under Patient Information and Policyholder Information (if different), and enter the Claim #.

In Box 1, enter the Patient's Name: Last, First and Initial.

Enter the Patient's Address (No. Street) in Box 2, the City in Box 3, the State in Box 4 and the Zip Code in Box 5.

Enter the Telephone # (Include Area Code) in Box 6.

Enter the Patient Birthdate in Box 7 and the Sex, M or F, in Box 8.

Enter the Insurance Company in Box 9 and the Policy Number in Box 10.

Date of accident and the patient's condition
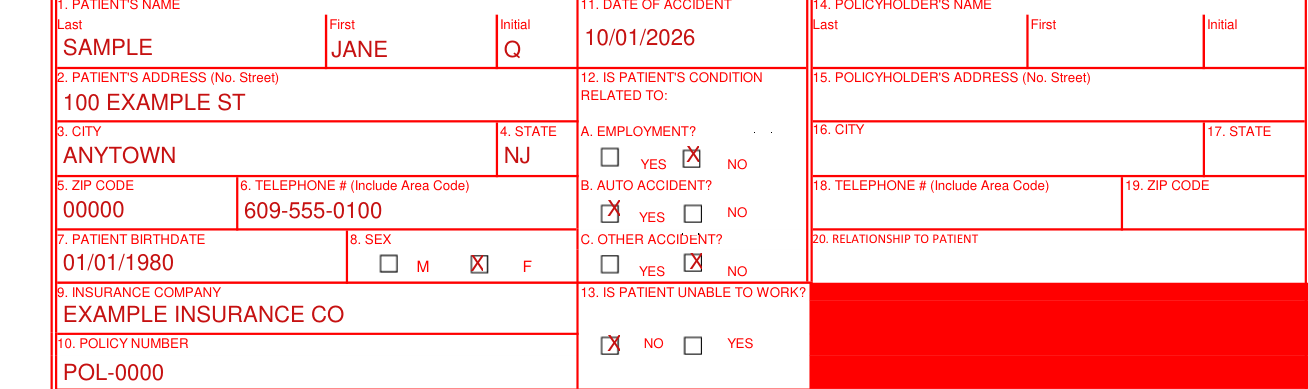
Attending Provider Treatment Plan (APTP) example filled out, date of accident and the patient's condition

Enter the Date of Accident in Box 11.

In Box 12, check YES or NO for Is Patient's Condition Related To: A. Employment?, B. Auto Accident? and C. Other Accident?

In Box 13, check NO or YES for Is Patient Unable To Work?

Policyholder information (if different)
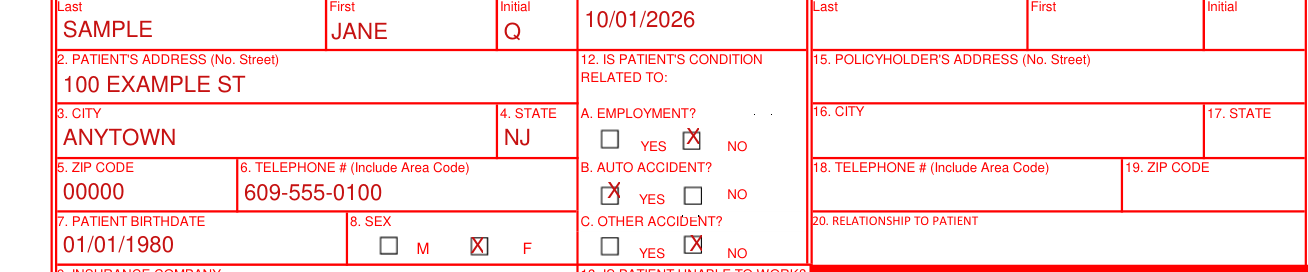
Attending Provider Treatment Plan (APTP) example filled out, policyholder information (if different)

If different, enter the Policyholder's Name in Box 14: Last, First and Initial.

Enter the Policyholder's Address (No. Street) in Box 15, the City in Box 16, the State in Box 17 and the Zip Code in Box 19.

Enter the Telephone # (Include Area Code) in Box 18.

Enter the Relationship to Patient in Box 20.

Provider information
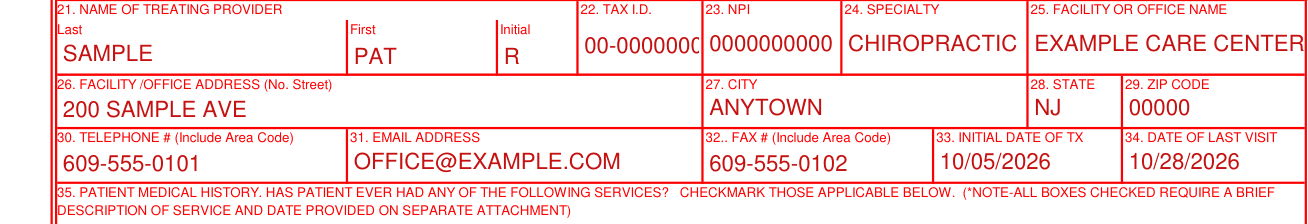
Attending Provider Treatment Plan (APTP) example filled out, provider information

Under Provider Information, enter the Name of Treating Provider in Box 21: Last, First and Initial.

Enter the Tax I.D. in Box 22, the NPI in Box 23, the Specialty in Box 24 and the Facility or Office Name in Box 25.

Enter the Facility/Office Address (No. Street) in Box 26, the City in Box 27, the State in Box 28 and the Zip Code in Box 29.

Enter the Telephone # (Include Area Code) in Box 30, the Email Address in Box 31, the Fax # (Include Area Code) in Box 32 and the Initial Date of TX in Box 33.

Enter the Date of Last Visit in Box 34.

Patient medical history

Attending Provider Treatment Plan (APTP) example filled out, patient medical history

In Box 35, check the services the patient has ever had: Medications, MRI, Surgery, X-Ray, Diagnostic Test, Existing Conditions, Comorbidities or Other.

All boxes checked require a brief description of service and date provided on a separate attachment.

Diagnosis or nature of illness or injury
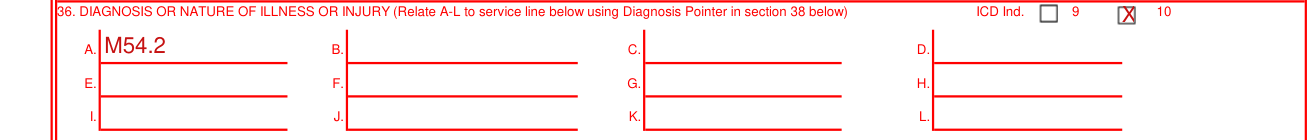
Attending Provider Treatment Plan (APTP) example filled out, diagnosis or nature of illness or injury

In Box 36, enter the Diagnosis or Nature of Illness or Injury in A to L, with the ICD Ind. 9 or 10, and relate A-L to the service line below using the Diagnosis Pointer in section 38.

Care path

Attending Provider Treatment Plan (APTP) example filled out, care path

In Box 37, check the appropriate Care Path (if applicable): CP1, CP2, CP3, CP4, CP5 or CP6.

Proposed course of treatment
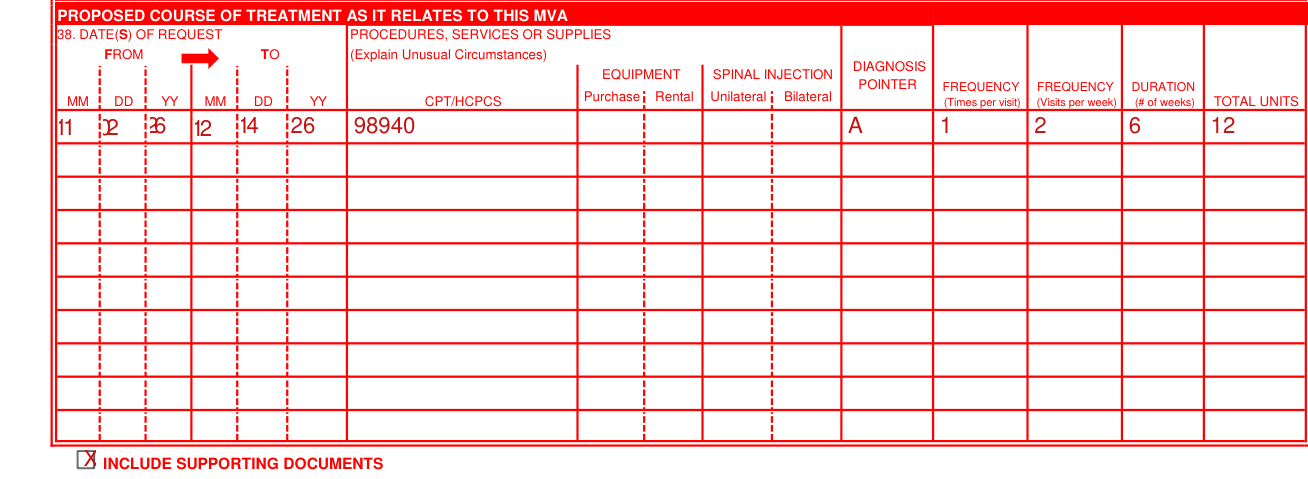
Attending Provider Treatment Plan (APTP) example filled out, proposed course of treatment

For the Proposed Course of Treatment as it relates to this MVA, enter the Date(s) of Request in Box 38: FROM and TO, each as MM, DD and YY.

Enter the Procedures, Services or Supplies (Explain Unusual Circumstances) as the CPT/HCPCS.

For Equipment, check Purchase or Rental; for Spinal Injection, check Unilateral or Bilateral.

Enter the Diagnosis Pointer.

Enter the Frequency (Times per visit), the Frequency (Visits per week), the Duration (# of weeks) and the Total Units.

Supporting documents

Attending Provider Treatment Plan (APTP) example filled out, supporting documents

Include Supporting Documents.

Common questions about Attending Provider Treatment Plan (APTP)

Who signs it?

Sign in Box 39 (Signature of Provider) and enter the Date.

Is there a penalty?

Any person who knowingly files a statement of claim containing any false or misleading information is subject to criminal and civil penalties.

What am I certifying when I sign?

The provider has personally completed and previewed this form, and the information is true and correct to the best of the provider's knowledge and belief.

Sources

[1] Attending Provider Treatment Plan, APTP Form Version 2.1 (3/2016), New Jersey Department of Banking and Insurance (the Official source link on this page).

Please rate Provider Treatment Plan

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .