

Pre-Authorization Request Form at a glance
What it is: Pre-Authorization Request Form, used for skilled nursing (SNF), long term acute care (LTAC), inpatient rehabilitation (IP Rehab), behavioral health services, and medical services.
Where and when to file: Medical Services/Supplies: Commercial, Individual, Medicare, FEP members: Fax 1 (855) 207-1209. Administrative Services Only (ASO) members: Fax 1 (844) 679-7763. Behavioral Health Services: Fax 1 (888) 496-1540. SNF, LTAC, IP Rehab: Fax 1 (855) 848-8220. Mail to: PO Box 1271, WW5-53, Portland, OR 97207-1271.
A filled-in Pre-Authorization Request Form example: a surgeon's office requests approval for a surgery
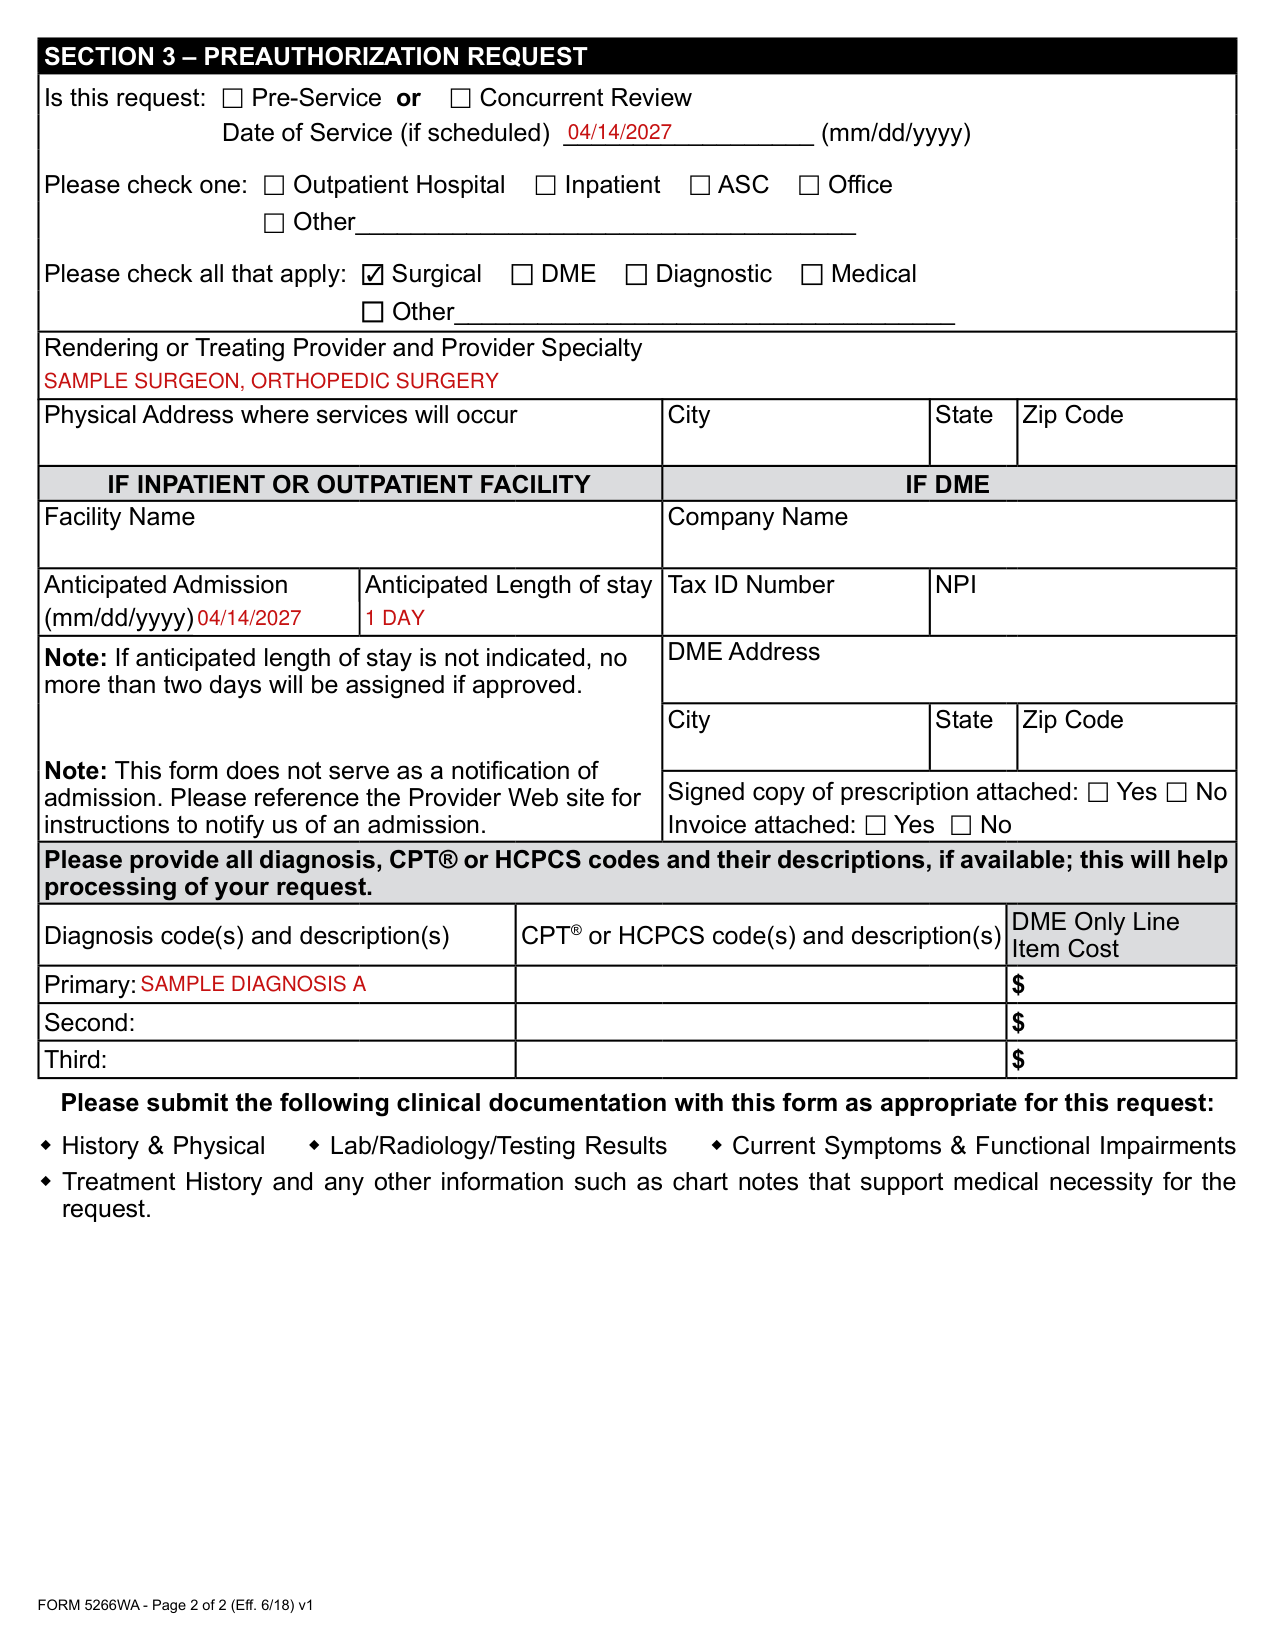
How to fill out Pre-Authorization Request Form, box by box
Is this request New or an Extension, and the authorization number
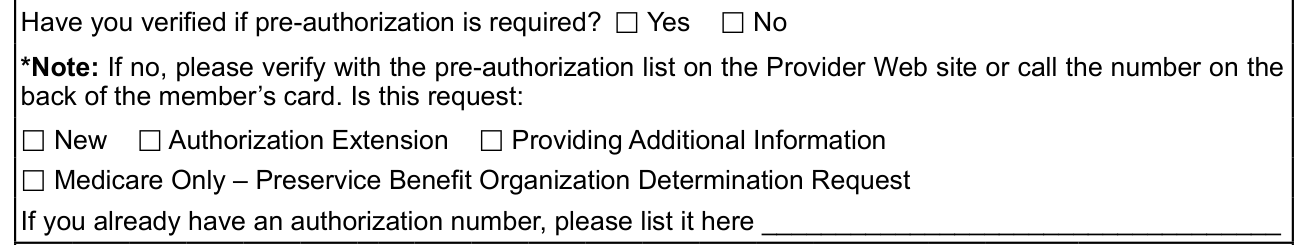
Have you verified if pre-authorization is required? If no, please verify with the pre-authorization list on the Provider Web site or call the number on the back of the member's card.
Mark if the request is New, an Authorization Extension, Providing Additional Information, or a Medicare Only Preservice Benefit Organization Determination Request. If you already have an authorization number, please list it here.
Expedited request

Expedited request: when the Member or his/her physician believes that waiting for a decision under the standard time frame could place the Member's life, health, or ability to regain maximum function in serious jeopardy, attest by checking the expedited request box and fax to 1 (855) 240-6498.
Section 1 - Patient information
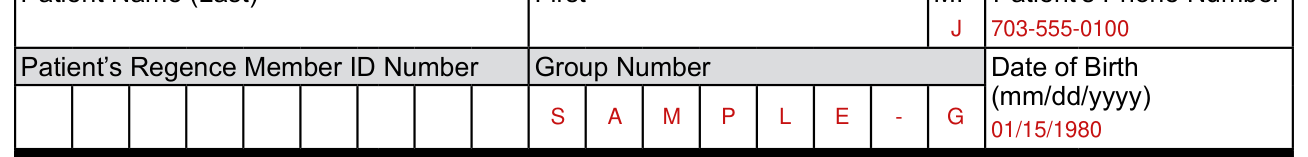
Enter the Patient Name (Last), First, MI and the Patient's Phone Number. Enter the Patient's Regence Member ID Number, Group Number and Date of Birth (mm/dd/yyyy).
Section 2 - Provider information
Please check one: Requesting Provider, Rendering Provider or DME Supplier. Enter the Provider Name, Tax ID Number, NPI, Phone Number, Fax Number, Provider Address, City, State and Zip Code, and mark Confidential Voice Mail Yes or No.
If additional information is required, enter the contact Name, Phone Number, Ext. and Fax Number for additional information, and mark Confidential Voice Mail Yes or No.
Is this request: Pre-Service or Concurrent Review

Mark if the request is Pre-Service or Concurrent Review, and enter the Date of Service (if scheduled) as mm/dd/yyyy.
Please check one: Outpatient, Hospital, Inpatient, ASC, Office

Please check one: Outpatient, Hospital, Inpatient, ASC, Office or Other.
Please check all that apply: Surgical, DME, Diagnostic, Medical
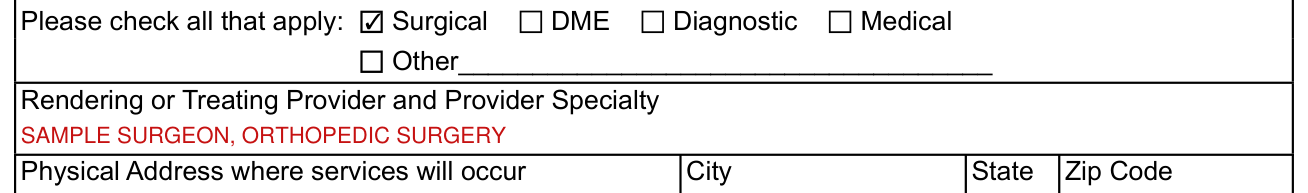
Please check all that apply: Surgical, DME, Diagnostic, Medical or Other. Enter the Rendering or Treating Provider and Provider Specialty.
Where services will occur
Enter the Physical Address where services will occur, with City, State and Zip Code. If inpatient or outpatient, enter the Facility Name.
Anticipated Admission and Anticipated Length of stay

Enter the Anticipated Admission (mm/dd/yyyy) and the Anticipated Length of stay. If anticipated length of stay is not indicated, no more than two days will be assigned if approved.
Diagnosis code(s) and description(s)

Please provide all diagnosis, CPT or HCPCS codes and their descriptions, if available; this will help processing of your request. Enter the Primary, Second and Third diagnosis code(s) and description(s). Signed copy of prescription attached: Yes No. Invoice attached: Yes No.
More rules for Pre-Authorization Request Form
This form should be filled out by the provider requesting the service or DME. Please complete all applicable fields. Prior to completing this form, please confirm the patient's benefits, eligibility and if pre-authorization is required for the service.
Please submit the following clinical documentation with this form as appropriate for this request.
History & Physical, Lab/Radiology/Testing Results, Current Symptoms & Functional Impairments, Treatment History and any other information such as chart notes that support medical necessity for the request.
Common questions about Pre-Authorization Request Form
When is this form not the right one?
This form does not serve as a notification of admission.
Sources
[1] Regence BlueCross BlueShield Pre-Authorization Request Form 5266WA (the Official source link on this page).
