

Motor Vehicle Accident Report at a glance
What it is: Motor Vehicle Accident Report of the State of Rhode Island Division of Motor Vehicles, Accident Office. Use blue or black ink only.
Who signs: OPERATOR'S SIGNATURE (THIS REPORT MUST BE SIGNED): also fill in PRINT YOUR NAME and DATE.
If you were directly or indirectly involved in a motor vehicle accident, you must submit one or more of the following (if applicable) pursuant to R.I.G.L. § 31-31.
If there was damage to your vehicle and the amount of damage is in excess of $1000.00 you must provide any and all documents to this department (i.e. itemized estimates of repair, completed and signed by the repair shop and/or a letter from an insurance company, if vehicle was totaled) (checked November 12, 2026).
If there was damage to your property (non-vehicle) and the amount of damage is in excess of $1000.00 you must provide any and all documents to this department (checked November 12, 2026).
If you incurred medical expenses as a result of an injury stemming from an accident please provide an attending physician report detailing the description of injuries, probable period of disability, whether or not hospitalization was needed and the total estimated expenses, including fees.
In addition to providing an attending physician report, if you have experienced the loss of wages as a result of a motor vehicle accident you must provide verification of loss of wages from your employer which details number of hours missed, hourly rate or salary, and a calculated estimate of wages lost per time period stated. The Division of Motor Vehicles Accident Office will not accept this form unless it is also signed by the injured party.
A filled-in Motor Vehicle Accident Report example: a one-vehicle accident at an intersection
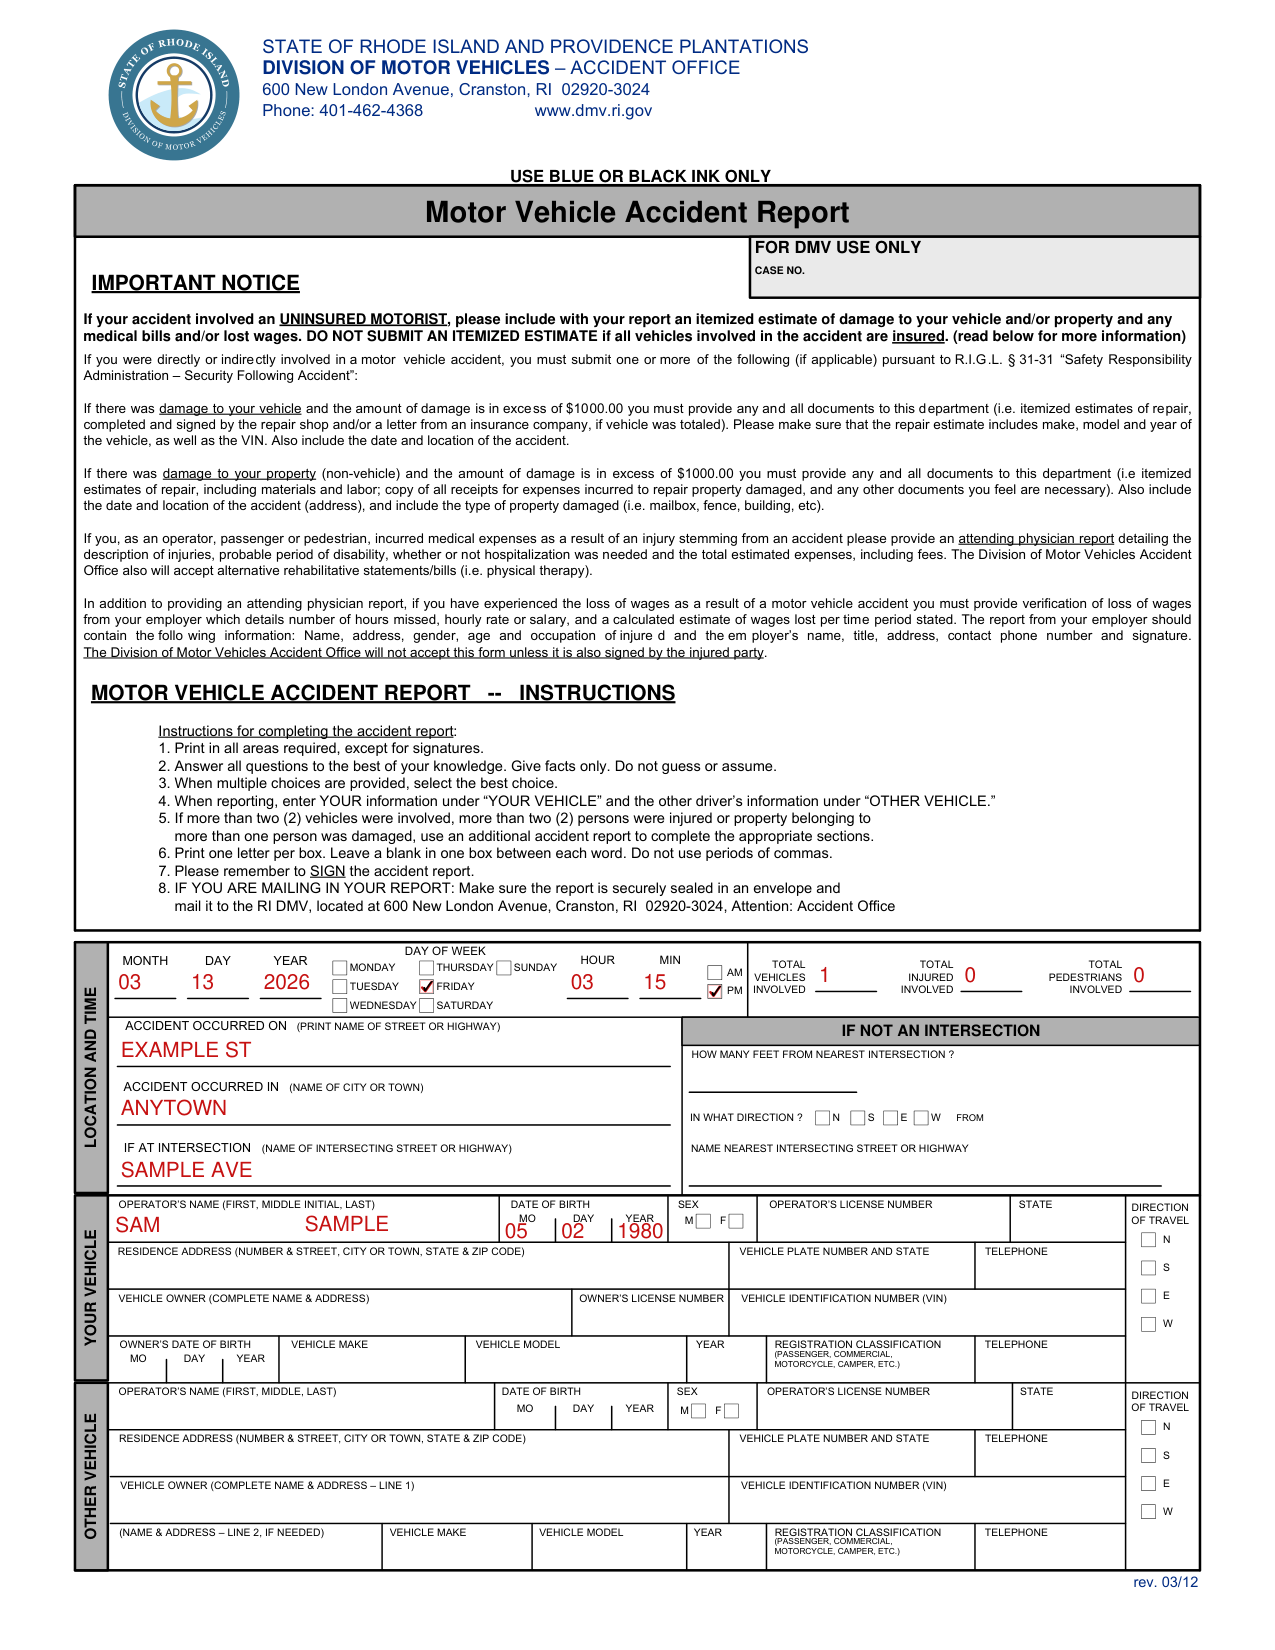
How to fill out Motor Vehicle Accident Report, box by box
Month, day, year, day of week, hour and min

Enter MONTH, DAY, YEAR, DAY OF WEEK, HOUR and MIN.
Total vehicles, injured and pedestrians involved

Enter total vehicles involved, total injured involved and total pedestrians involved.
Accident occurred on and in
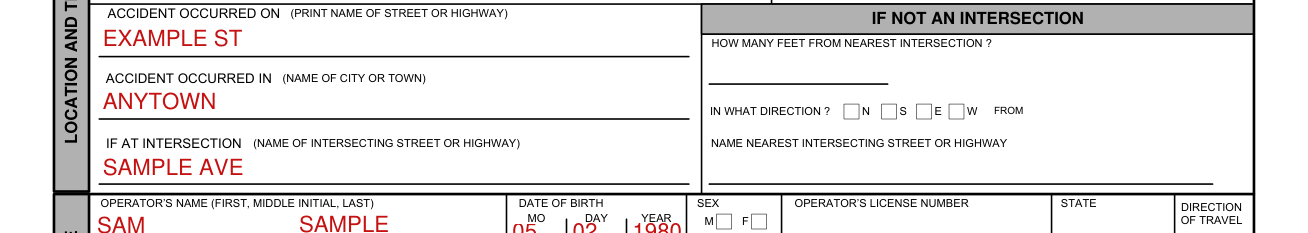
Print the name of the street or highway under ACCIDENT OCCURRED ON, and the name of the city or town under ACCIDENT OCCURRED IN.
If at an intersection, enter the name of the intersecting street or highway under IF AT INTERSECTION.
If not an intersection, enter how many feet from the nearest intersection, in what direction (N, S, E or W) from, and the name of the nearest intersecting street or highway.
Your vehicle and its operator

Under YOUR VEHICLE, enter the operator's name (first, middle initial, last), date of birth, and operator's license number and state.
Enter the residence address (number & street, city or town, state & zip code), telephone, and vehicle plate number and state.
Vehicle owner and vehicle identification number

Enter the vehicle owner (complete name & address), owner's license number and vehicle identification number (VIN).
Other vehicle

Under OTHER VEHICLE, enter the operator's name (first, middle, last), date of birth and sex.
Describing what happened and signing
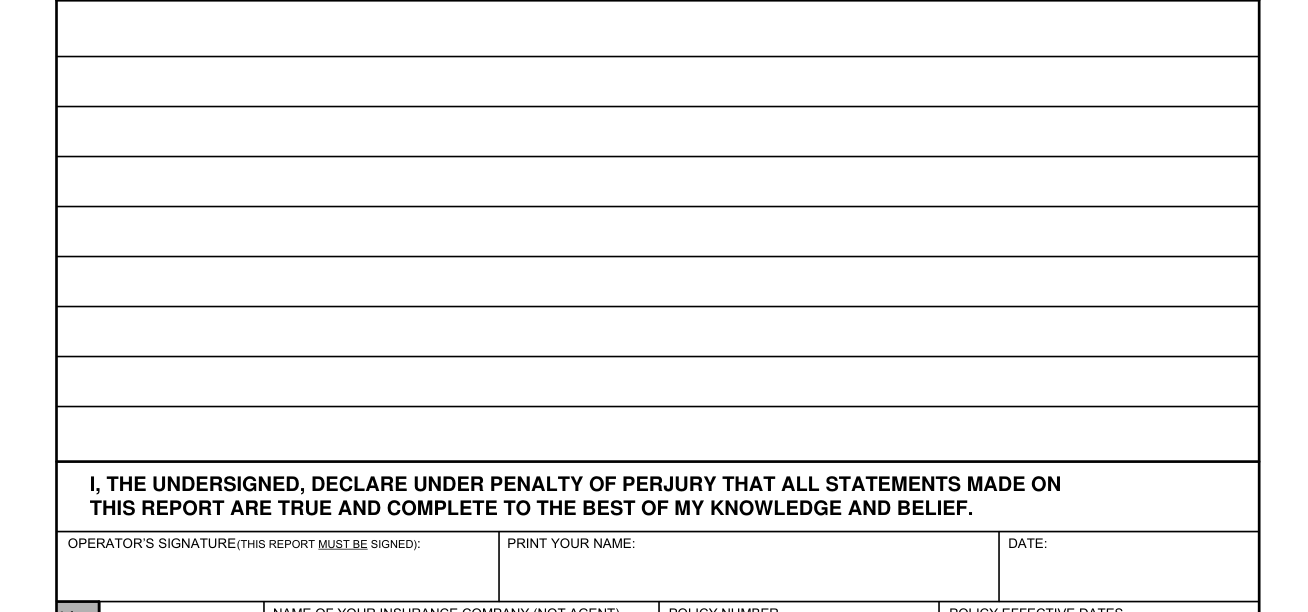
In your own words, please describe what happened.
You declare under penalty of perjury that all statements made on this report are true and complete to the best of your knowledge and belief.
Instructions for completing the accident report: 1. Print in all areas required, except for signatures. 2. Answer all questions to the best of your knowledge. Give facts only. Do not guess or assume. 3. When multiple choices are provided, select the best choice. 4. When reporting, enter YOUR information under "YOUR VEHICLE" and the other driver's information under "OTHER VEHICLE." 5. If more than two (2) vehicles were involved, more than two (2) persons were injured or property belonging to more than one person was damaged, use an additional accident report to complete the appropriate sections. 6. Print one letter per box. Leave a blank in one box between each word. Do not use periods or commas. 7. Please remember to SIGN the accident report. 8. IF YOU ARE MAILING IN YOUR REPORT: Make sure the report is securely sealed in an envelope and mail it to the RI DMV, located at 600 New London Avenue, Cranston, RI 02920-3024, Attention: Accident Office
More rules for Motor Vehicle Accident Report
If your accident involved an UNINSURED MOTORIST, please include with your report an itemized estimate of damage to your vehicle and/or property and any medical bills and/or lost wages.
DO NOT SUBMIT AN ITEMIZED ESTIMATE if all vehicles involved in the accident are insured.
Was your vehicle or the vehicle you were operating insured (liability insurance) at the time of the accident? YES or NO. If "YES", complete attached form.
Enter the name of your insurance company (not agent), the policy number and the policy effective dates.
Sources
[1] Motor Vehicle Accident Report (rev. 03/12), State of Rhode Island Division of Motor Vehicles (the Official source link on this page).
