

Form E3067 at a glance
What it is: The Employer's Report of Occupational Injury or Illness, e3067, of the State Compensation Insurance Fund.
Who signs: Complete the Completed By (type or print), Signature & Title and Date (mm/dd/yy) lines.
A filled-in Form E3067 example: a roofer burns a hand
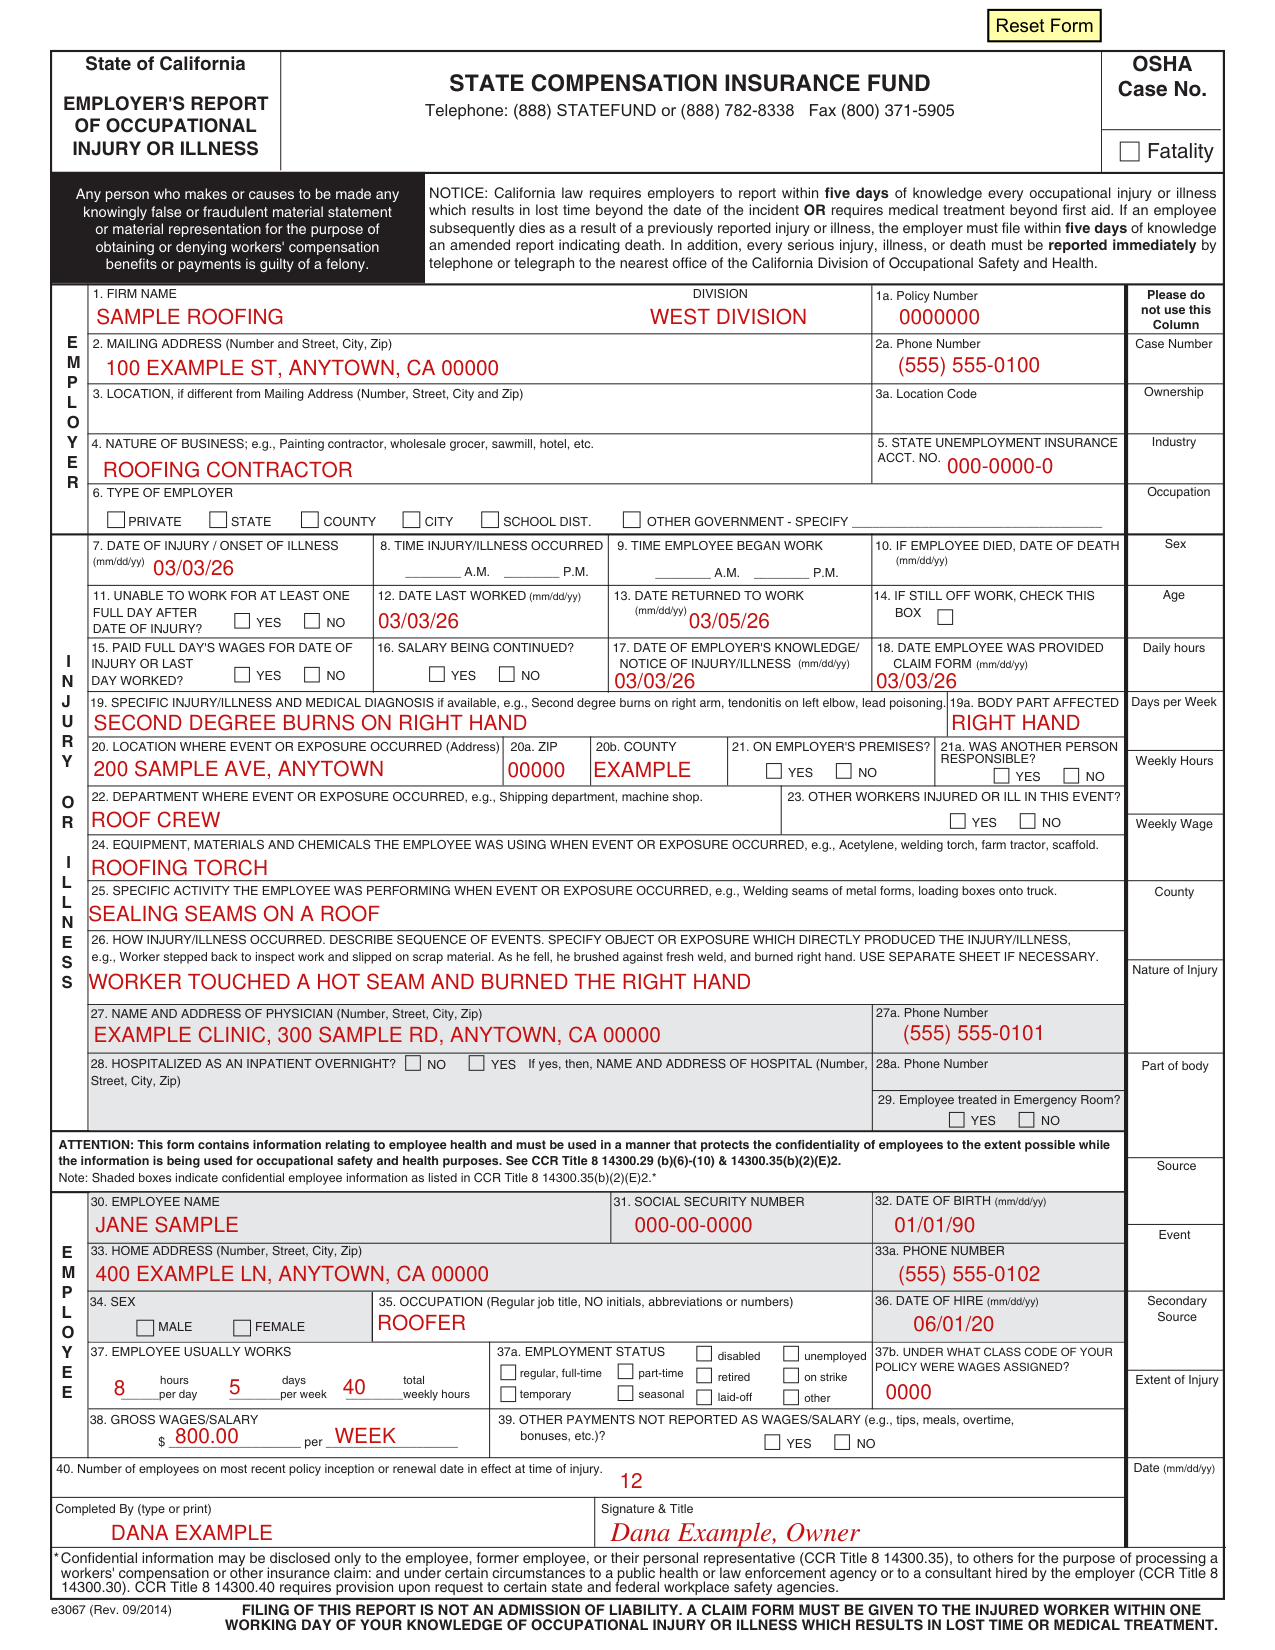
How to fill out Form E3067, box by box
The employer, boxes 1 to 6
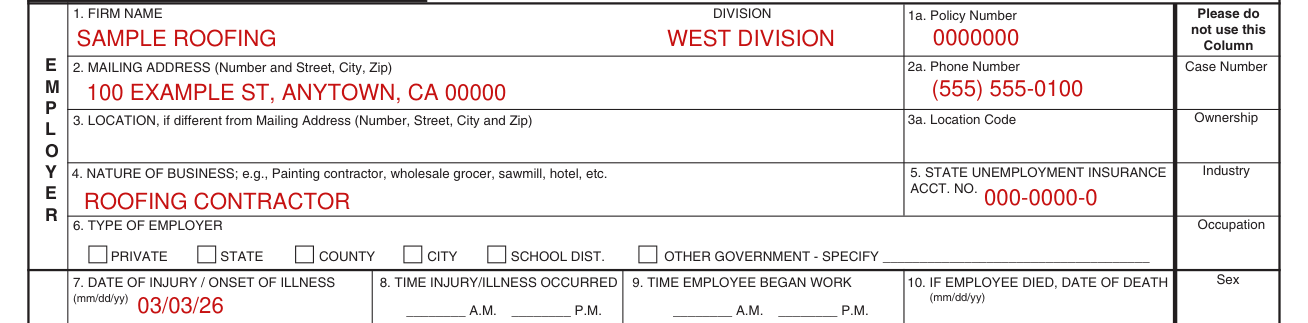
Enter the Firm Name and Division in Box 1, the Policy Number in 1a, the Mailing Address (Number and Street, City, Zip) in Box 2 and the Phone Number in 2a.
Enter the Location, if different from Mailing Address (Number, Street, City and Zip), in Box 3 and the Location Code in 3a; enter the Nature of Business in Box 4 and the State Unemployment Insurance Acct. No. in Box 5.
Box 6, Type of Employer: PRIVATE, STATE, COUNTY, CITY, SCHOOL DIST. or OTHER GOVERNMENT - SPECIFY.
Dates and times of the injury, boxes 7 to 14
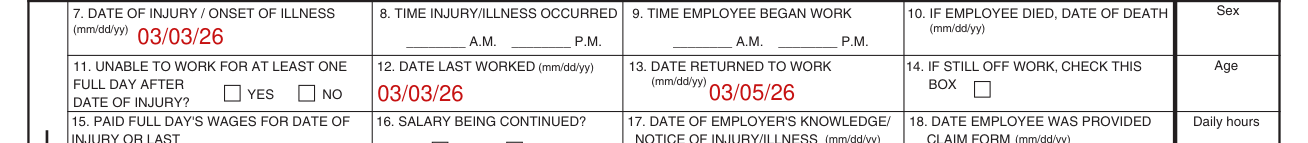
Enter the Date of Injury / Onset of Illness (mm/dd/yy) in Box 7, the Time Injury/Illness Occurred in Box 8 and the Time Employee Began Work in Box 9, each as A.M. or P.M.
If the employee died, enter the Date of Death (mm/dd/yy) in Box 10.
Box 11, Unable to Work for at Least One Full Day After Date of Injury?, is YES or NO; enter the Date Last Worked (mm/dd/yy) in Box 12 and the Date Returned to Work (mm/dd/yy) in Box 13.
If still off work, check the box in Box 14.
Notice and the injury, boxes 15 to 19
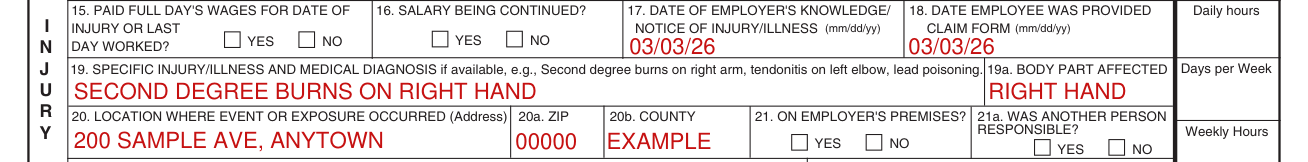
Box 15, Paid Full Day's Wages for Date of Injury or Last Day Worked?, and Box 16, Salary Being Continued?, are each YES or NO.
Enter the Date of Employer's Knowledge/Notice of Injury/Illness (mm/dd/yy) in Box 17 and the Date Employee was Provided Claim Form (mm/dd/yy) in Box 18.
In Box 19, enter the Specific Injury/Illness and Medical Diagnosis if available, e.g., Second degree burns on right arm, tendonitis on left elbow, lead poisoning, and the Body Part Affected in 19a.
Where and how the event occurred, boxes 20 to 26

Enter the Location Where Event or Exposure Occurred (Address) in Box 20, with the Zip in 20a and the County in 20b; Box 21, On Employer's Premises?, and Box 21a, Was Another Person Responsible?, are each YES or NO.
Enter the Department Where Event or Exposure Occurred in Box 22, e.g., Shipping department, machine shop; Box 23, Other Workers Injured or Ill in This Event?, is YES or NO.
Enter the Equipment, Materials and Chemicals the employee was using when the event or exposure occurred in Box 24, e.g., Acetylene, welding torch, farm tractor, scaffold, and the Specific Activity the employee was performing in Box 25, e.g., Welding seams of metal forms, loading boxes onto truck.
In Box 26, describe the sequence of events and specify the object or exposure which directly produced the injury/illness; use a separate sheet if necessary.
Physician and hospital, boxes 27 to 29

Enter the Name and Address of Physician (Number, Street, City, Zip) in Box 27 and the Phone Number in 27a; in Box 28, Hospitalized as an Inpatient Overnight?, mark NO or YES, and if yes, then enter the Name and Address of Hospital (Number, Street, City, Zip) and the Phone Number in 28a.
Box 29, Employee treated in Emergency Room?, is YES or NO.
The employee, boxes 30 to 40
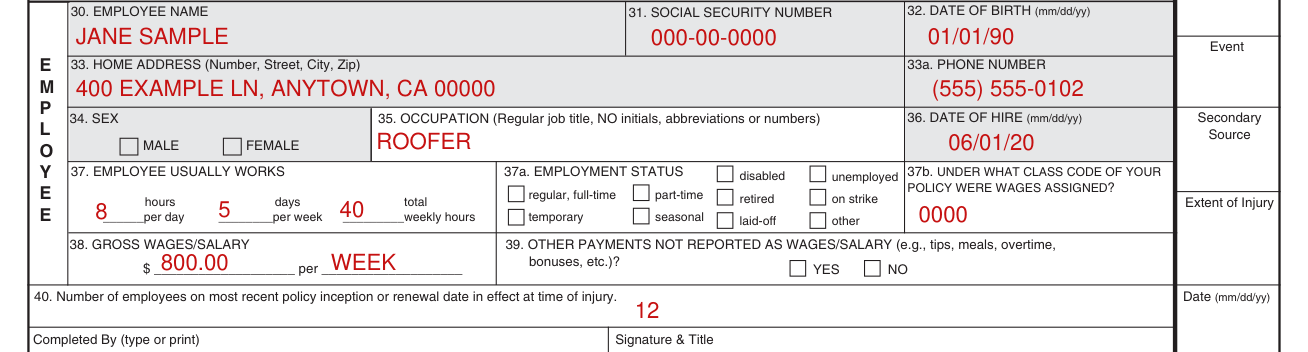
This form contains information relating to employee health and must be used in a manner that protects the confidentiality of employees to the extent possible while the information is being used for occupational safety and health purposes.
Shaded boxes indicate confidential employee information as listed in CCR Title 8 14300.35(b)(2)(E)2.
Enter the Employee Name in Box 30, the Social Security Number in Box 31, the Date of Birth (mm/dd/yy) in Box 32, the Home Address (Number, Street, City, Zip) in Box 33 and the Phone Number in 33a.
Mark MALE or FEMALE in Box 34, enter the Occupation (Regular job title, NO initials, abbreviations or numbers) in Box 35 and the Date of Hire (mm/dd/yy) in Box 36.
In Box 37, Employee Usually Works, enter hours per day, days per week and total weekly hours; enter in 37b the class code: Under What Class Code of Your Policy Were Wages Assigned?
In 37a, Employment Status, mark regular, full-time, part-time, temporary, seasonal, disabled, retired, laid-off, unemployed, on strike or other.
Enter the Gross Wages/Salary in Box 38 ($ ___ per ___); Box 39, Other Payments Not Reported as Wages/Salary (e.g., tips, meals, overtime, bonuses, etc.)?, is YES or NO.
Enter in Box 40 the number of employees on most recent policy inception or renewal date in effect at time of injury.
Completed By, Signature & Title and Date

Complete the Completed By (type or print), Signature & Title and Date (mm/dd/yy) lines.
More rules for Form E3067
Every serious injury, illness, or death must be reported immediately by telephone or telegraph to the nearest office of the California Division of Occupational Safety and Health.
A claim form must be given to the injured worker within one working day of your knowledge of occupational injury or illness which results in lost time or medical treatment.
Filing of this report is not an admission of liability.
Confidential information may be disclosed only to the employee, former employee, or their personal representative (CCR Title 8 14300.35), to others for the purpose of processing a workers' compensation or other insurance claim: and under certain circumstances to a public health or law enforcement agency or to a consultant hired by the employer (CCR Title 8 14300.30). CCR Title 8 14300.40 requires provision upon request to certain state and federal workplace safety agencies.
Common questions about Form E3067
Is there a deadline?
California law requires employers to report within five days of knowledge every occupational injury or illness which results in lost time beyond the date of the incident OR requires medical treatment beyond first aid. If an employee subsequently dies as a result of a previously reported injury or illness, the employer must file within five days of knowledge an amended report indicating death.
Is there a penalty?
Any person who makes or causes to be made any knowingly false or fraudulent material statement or material representation for the purpose of obtaining or denying workers' compensation benefits or payments is guilty of a felony.
Sources
[1] Form E3067 (Rev. 09/2014), Employer's Report of Occupational Injury or Illness, State Compensation Insurance Fund (the Official source link on this page).
