


Form LDSS-4310 at a glance
What it is: The LDSS-4310 Periodic Report helps gather information about any changes you may have had since the last time you were in contact with your eligibility worker.
Who signs: You must sign and return this form.
You must answer all questions on this Report. Answer all questions on this Report for everyone who is getting, or anyone who is legally responsible for someone getting, Child Assistance (CAP), Child Care, and/or SNAP Benefits.
What to bring and attach to Form LDSS-4310
Send in proof of all income that any household member got during the entire month of _______________________.
Since you participate in the Child Assistance Program (CAP), send proof of earnings, other income, and child care costs for _________________________, __________________________, __________________________.
A filled-in Form LDSS-4310 example: a SNAP household reports a rent increase
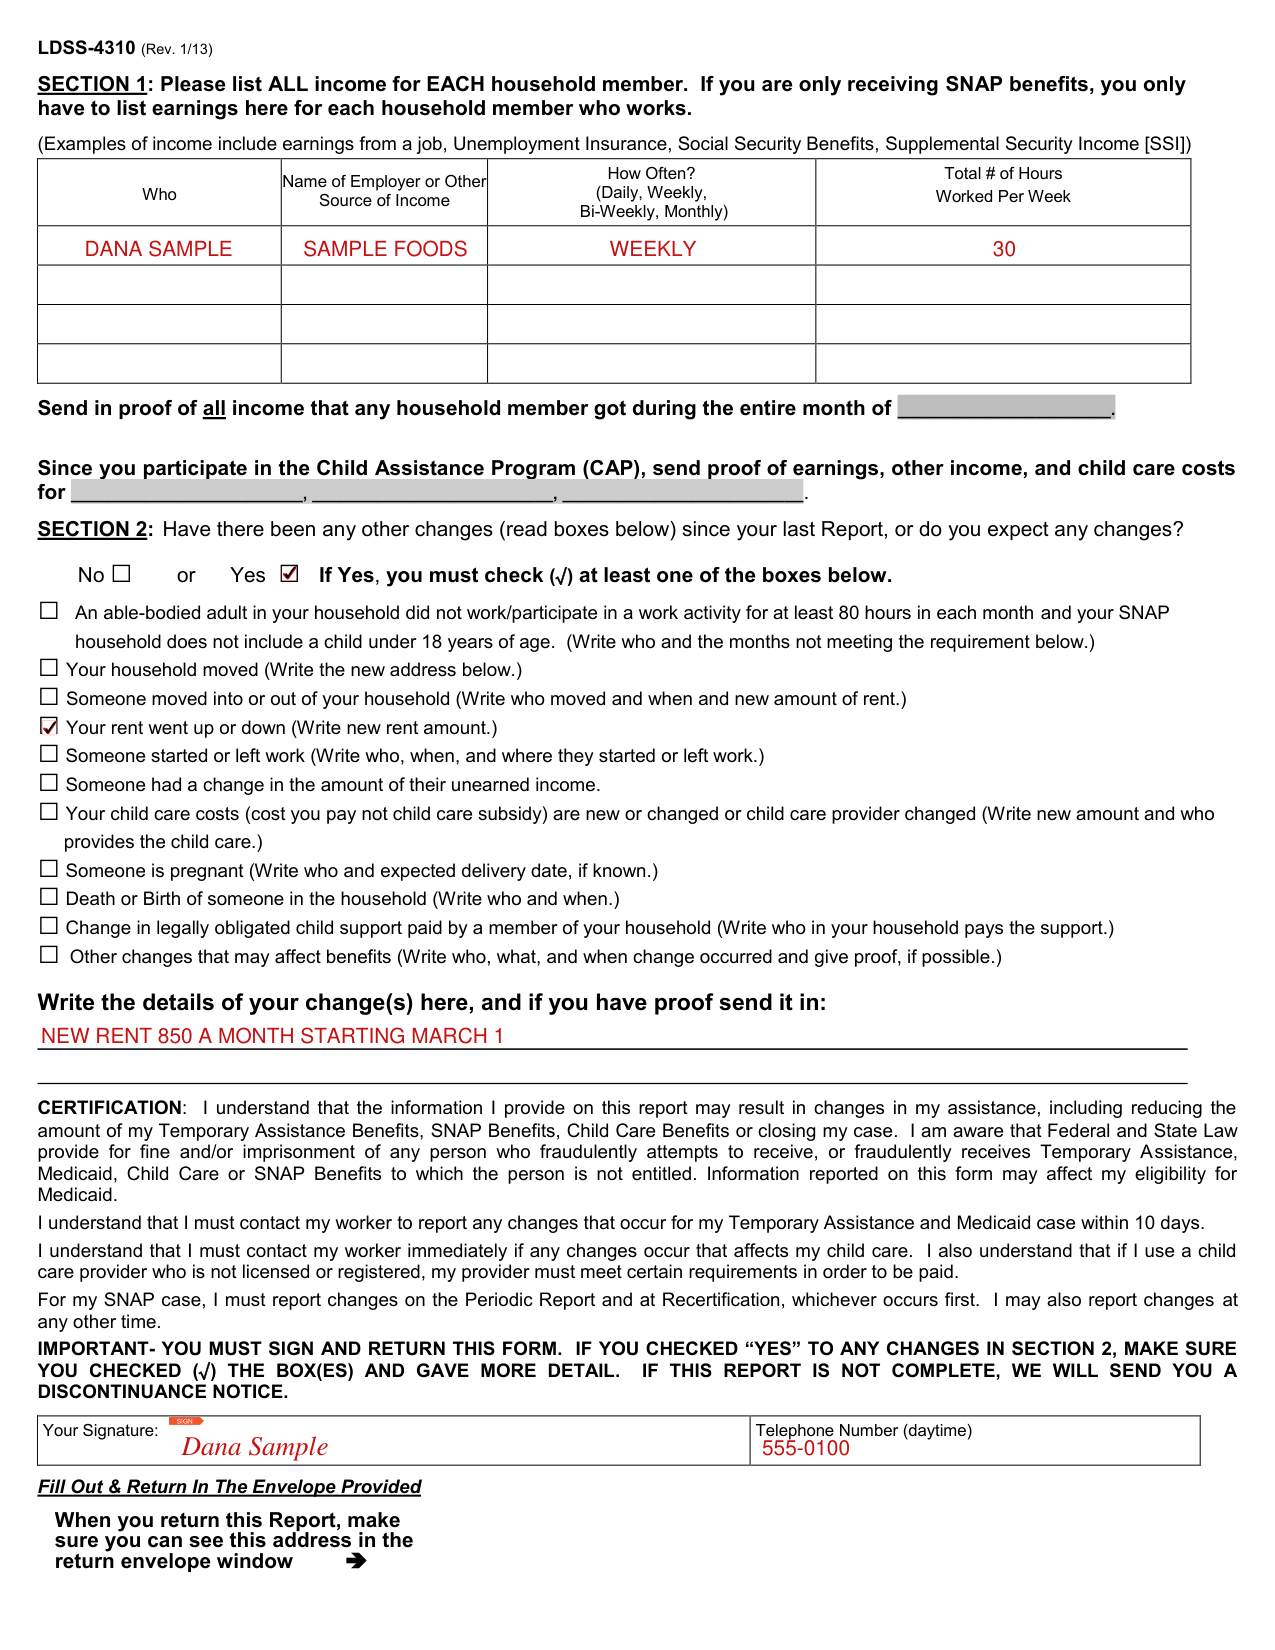
How to fill out Form LDSS-4310, box by box
Your completed Report: questions, return by and the address
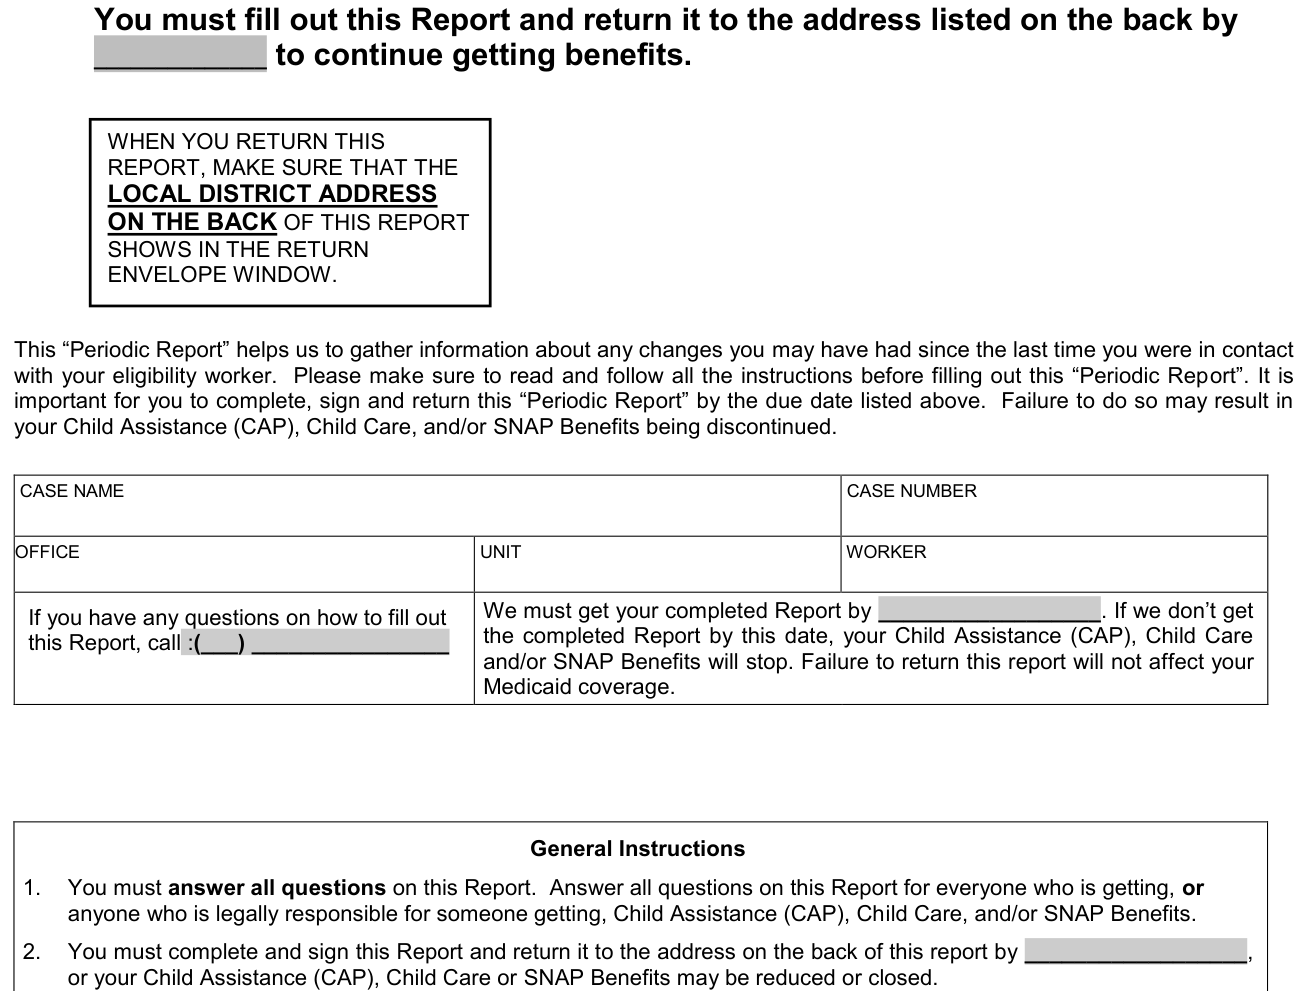
The WORKER must get your completed Report by __________________. If they don't get the completed Report by this date, your Child Assistance (CAP), Child Care and/or SNAP Benefits will stop. Failure to return this report will not affect your Medicaid coverage.
You must complete and sign this Report and return it by __________________, or your Child Assistance (CAP), Child Care or SNAP Benefits may be reduced or closed. Reminder: If you are also receiving Temporary Assistance and Medicaid, you must report any changes to your worker within 10 days. For SNAP, you must report within ten days after the end of the month if your total monthly gross income exceeds the 130% limit you have been given. Otherwise, you do not need to report changes at any time other than on this Periodic Report or at Recertification, whichever occurs first. You must contact your worker immediately if any changes occur that affect your Child Care.
Fill out and return the Report in the envelope provided. When you return this Report, make sure that the local district address on the back of this report shows in the return envelope window.
If you have any questions on how to fill out this Report, call the number on the form.
SECTION 1: income for each household member
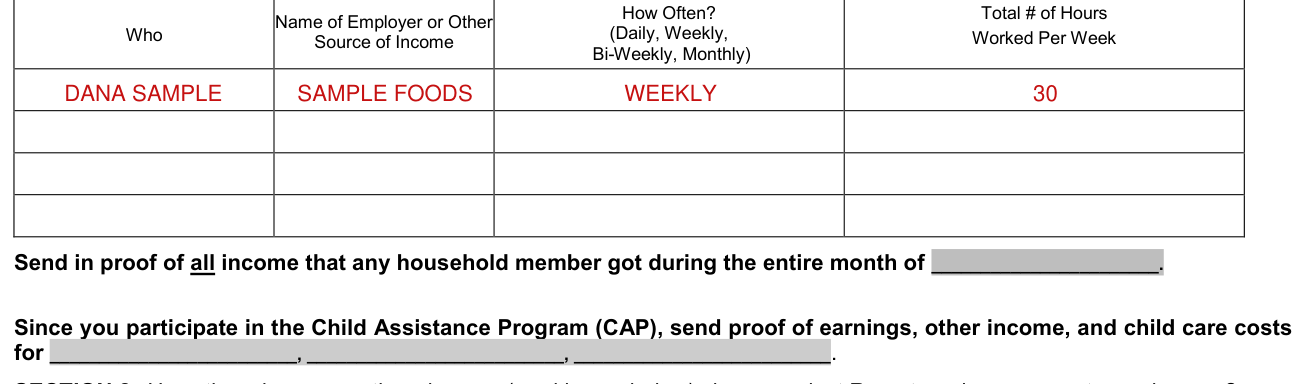
SECTION 1: List ALL income for EACH household member. If you are only receiving SNAP benefits, you only have to list earnings here for each household member who works.
Examples of income include earnings from a job, Unemployment Insurance, Social Security Benefits, Supplemental Security Income [SSI].
For each income, write Who, the Name of Employer or Other Source of Income, How Often? (Daily, Weekly, Bi-Weekly, Monthly) and the Total # of Hours Worked Per Week.
SECTION 2: other changes

SECTION 2: Have there been any other changes since your last Report, or do you expect any changes? Mark No or Yes. If Yes, you must check (√) at least one of the boxes in SECTION 2. Check the box for: An able-bodied adult in your household did not work/participate in a work activity for at least 80 hours in each month and your SNAP household does not include a child under 18 years of age.
For that box, write who and the months not meeting the requirement.
Check Your household moved and write the new address.
Check Someone moved into or out of your household and write who moved and when and new amount of rent.
Check Your rent went up or down and write new rent amount.
Check Someone started or left work and write who, when, and where they started or left work.
Check Someone had a change in the amount of their unearned income.
Check Your child care costs (cost you pay not child care subsidy) are new or changed or child care provider changed, and write new amount and who provides the child care.
Check Someone is pregnant and write who and expected delivery date, if known.
Check Death or Birth of someone in the household and write who and when.
Check Change in legally obligated child support paid by a member of your household and write who in your household pays the support.
Check Other changes that may affect benefits and write who, what, and when change occurred and give proof, if possible.
Write the details of your change(s) here, and if you have proof send it in.
CERTIFICATION, Your Signature and Telephone Number (daytime)

Sign on Your Signature and write your Telephone Number (daytime).
If you checked “YES” to any changes in Section 2, make sure you checked (√) the box(es) and gave more detail.
The information you provide on this report may result in changes in your assistance, including reducing the amount of your Temporary Assistance Benefits, SNAP Benefits, Child Care Benefits or closing your case.
Information reported on this form may affect your eligibility for Medicaid.
Federal and State Law provide for fine and/or imprisonment of any person who fraudulently attempts to receive, or fraudulently receives Temporary Assistance, Medicaid, Child Care or SNAP Benefits to which the person is not entitled.
If you use a child care provider who is not licensed or registered, your provider must meet certain requirements in order to be paid.
For your SNAP case, you must report changes on the Periodic Report and at Recertification, whichever occurs first. You may also report changes at any other time.
More rules for Form LDSS-4310
Read and follow all the instructions before filling out this Periodic Report. It is important for you to complete, sign and return this Periodic Report by the due date. Failure to do so may result in your Child Assistance (CAP), Child Care, and/or SNAP Benefits being discontinued.
Supplemental Nutrition Assistance Program (SNAP) is the new name for the Food Stamp Program.
Sources
[1] Form LDSS-4310 (Rev. 1/13), Periodic Report, New York State Office of Temporary and Disability Assistance (the Official source link on this page).