

SOC 821 at a glance
What it is: This is the Assessment of Need for Protective Supervision for In-Home Supportive Services Program, a California Department of Social Services form.
Where and when to file: RETURN THIS FORM TO the COUNTY'S MAILING ADDRESS, CITY, CA, ATTN; SW-NAME.
A filled-in SOC 821 example: a physician completes the assessment

How to fill out SOC 821, box by box
Patient, county and your mailing address

Mark Release of Information Attached if a release of information is attached.
Enter the PATIENT'S NAME, PATIENT'S DOB, MEDICAL ID# (IF AVAILABLE) and COUNTY ID#.
Enter the Physician's / Attending Medical Professional's mailing address.
Enter the IHSS SOCIAL WORKER'S NAME, the COUNTY CONTACT TELEPHONE # and the COUNTY FAX #.
Date patient last seen, diagnosis and prognosis

Enter the DATE PATIENT LAST SEEN BY YOU and the LENGTH OF TIME YOU HAVE TREATED PATIENT.
Enter the DIAGNOSIS/MENTAL CONDITION, and for PROGNOSIS mark Permanent or Temporary - Timeframe.
Memory

PLEASE CHECK THE APPROPRIATE BOXES under MEMORY: No deficit problem, Moderate or intermittent deficit (explain) or Severe memory deficit (explain), and write the Explanation.
Orientation

Under ORIENTATION, check No disorientation, Moderate disorientation/confusion (explain) or Severe disorientation (explain), and write the Explanation.
Judgment
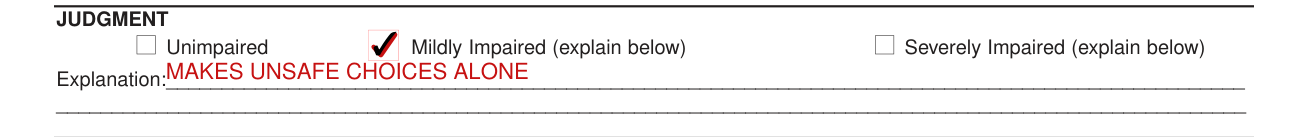
Under JUDGMENT, check Unimpaired, Mildly Impaired (explain) or Severely Impaired (explain), and write the Explanation.
Injury, accident, hazard and additional comments

Are you aware of any injury or accident that the patient has suffered due to deficits in memory, orientation or judgment? Mark Yes or No. If Yes, please specify.
Does this patient retain the mobility or physical capacity to place him/herself in a situation which would result in injury, hazard or accident? Mark Yes or No.
Write any additional information or comments.
Signature of physician or medical professional

Sign on the SIGNATURE OF PHYSICIAN OR MEDICAL PROFESSIONAL line, and enter the MEDICAL SPECIALTY, DATE, ADDRESS, LICENSE NO. and TELEPHONE.
If your situation is different
Your patient is an applicant/recipient of IHSS assessed for Protective Supervision
Your patient is an applicant/recipient of In-Home Supportive Services (IHSS) and is being assessed for the need for Protective Supervision. Protective Supervision is available to safeguard against accident or hazard by observing and/or monitoring the behavior of non self-directing, confused, mentally impaired or mentally ill persons. This service is not available in the following instances: (1) When the need for protective supervision is caused by a physical condition rather than a mental impairment; (2) For friendly visitation or other social activities; (3) When the need for supervision is caused by a medical condition and the form of supervision required is medical; (4) In anticipation of a medical emergency (such as seizures, etc.); (5) To prevent or control antisocial or aggressive recipient behavior. Please complete this form and return it promptly. (Welfare and Institutions Code §12301.21)
CERTIFICATION: "I certify that I am licensed to practice in the State of California and that the information provided above is correct."
Common questions about SOC 821
Where do I file it?
RETURN THIS FORM TO the COUNTY'S MAILING ADDRESS, CITY, CA, ATTN; SW-NAME.
Sources
[1] Form SOC 821 (3/06), Assessment of Need for Protective Supervision for In-Home Supportive Services Program, California Department of Social Services (the Official source link on this page).
