

Form SSA-1724-F4 at a glance
What it is: The Social Security Administration form is the CLAIM FOR AMOUNTS DUE IN THE CASE OF A DECEASED BENEFICIARY.
A filled-in Form SSA-1724-F4 example: a widow who lived apart files the claim

How to fill out Form SSA-1724-F4, box by box
Tap a group of boxes to open it, and a picture to see it full size.
This claim for the amounts due, and the deceased

The deceased may have been due a Social Security payment and/or a Medicare Premium refund. The Social Security Act provides that amounts due a deceased may be paid to the next of kin or the legal representative of the estate under priorities established in the law. To help us decide who should receive any payment due, please COMPLETE THIS ENTIRE FORM and RETURN it to us in the enclosed envelope.
PRINT NAME OF DECEASED and SOCIAL SECURITY NUMBER OF DECEASED.
If the deceased received benefits on another person's record, print name of that worker in NAME OF THE WORKER.
Who died on, and the state lived in

This claim for the amounts due is being made on behalf of the family or the estate of (name of deceased), who died on day of (month) (year), and who lived in the state of.
The applicant

PRINT NAME OF APPLICANT and RELATIONSHIP TO DECEASED (Widow, Son, Legal Representative, etc.).
Item 1, the surviving widow(er)

Common mistake: 1. NAME OF SURVIVING WIDOW(ER) (Please print. If none, state "NONE").
ADDRESS OF SURVIVING WIDOW(ER) (Please print house number, street, apt. number, P.O. Box, rural route, city, state, and ZIP code).
ENTER SOCIAL SECURITY NUMBER(S) OF WIDOW(ER) NAMED ABOVE.
WAS THE WIDOW(ER) NAMED ABOVE LIVING IN THE SAME HOUSEHOLD WITH THE DECEASED AT THE TIME OF DEATH? If "YES", then SKIP items 2,3,4,5 and SIGN at bottom of page 2. YES or NO.
WAS HE OR SHE ENTITLED TO A MONTHLY BENEFIT ON THE SAME EARNINGS RECORD AS THE DECEASED AT THE TIME OF DEATH? If "YES", then SKIP items 2,3,4,5 and SIGN at bottom of page 2. If NO, go on to item 2.
Item 2, the living children of the deceased
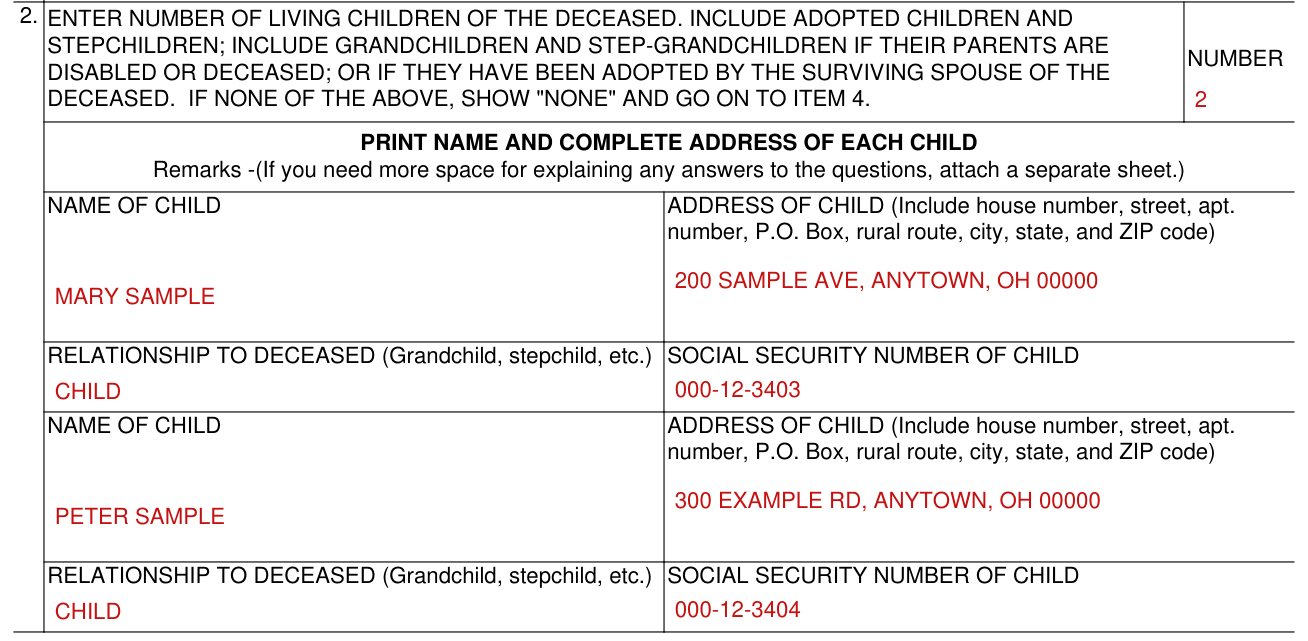
Common mistake: 2. ENTER NUMBER OF LIVING CHILDREN OF THE DECEASED. INCLUDE ADOPTED CHILDREN AND STEPCHILDREN; INCLUDE GRANDCHILDREN AND STEP-GRANDCHILDREN IF THEIR PARENTS ARE DISABLED OR DECEASED; OR IF THEY HAVE BEEN ADOPTED BY THE SURVIVING SPOUSE OF THE DECEASED. IF NONE OF THE ABOVE, SHOW "NONE" AND GO ON TO ITEM 4.
PRINT NAME AND COMPLETE ADDRESS OF EACH CHILD.
NAME OF CHILD, ADDRESS OF CHILD (Include house number, street, apt. number, P.O. Box, rural route, city, state, and ZIP code), RELATIONSHIP TO DECEASED (Grandchild, stepchild, etc.) and SOCIAL SECURITY NUMBER OF CHILD.
Item 3, a child with a different name, and item 4, the living parents
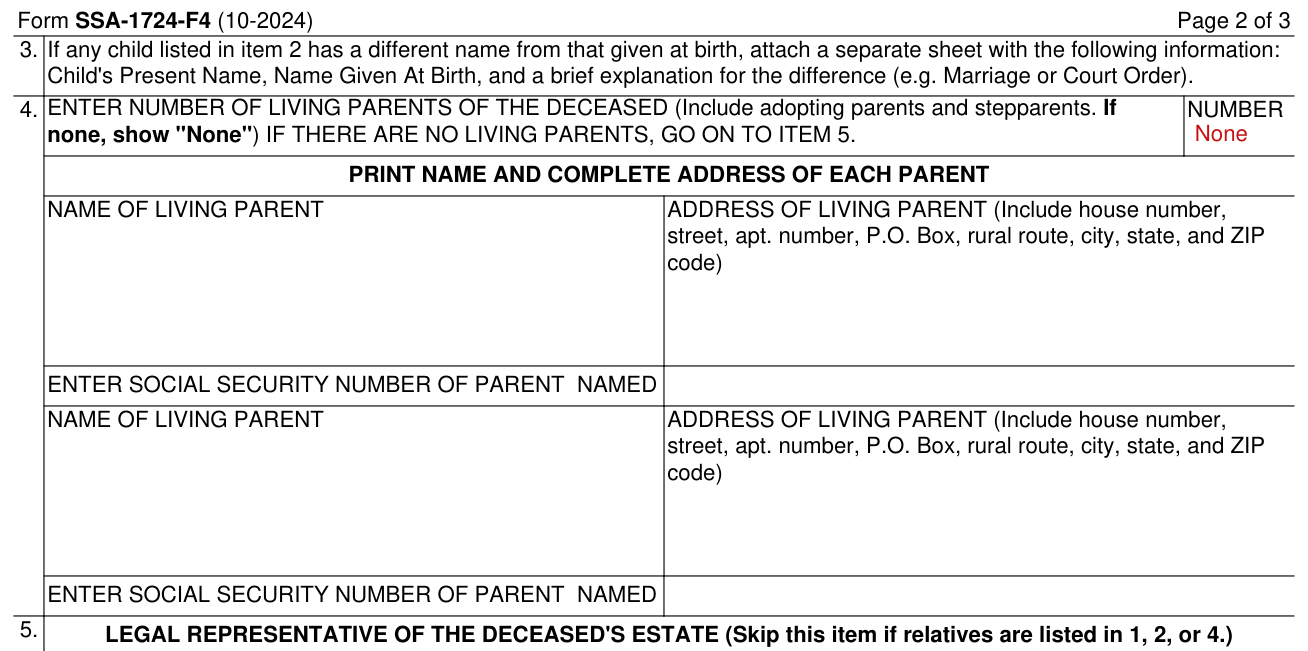
If any child listed in item 2 has a different name from that given at birth, attach a separate sheet with the following information: Child's Present Name, Name Given At Birth, and a brief explanation for the difference (e.g. Marriage or Court Order).
4. ENTER NUMBER OF LIVING PARENTS OF THE DECEASED (Include adopting parents and stepparents).
Common mistake: If none, show "None". IF THERE ARE NO LIVING PARENTS, GO ON TO ITEM 5.
PRINT NAME AND COMPLETE ADDRESS OF EACH PARENT: NAME OF LIVING PARENT and ADDRESS OF LIVING PARENT (Include house number, street, apt. number, P.O. Box, rural route, city, state, and ZIP code).
ENTER SOCIAL SECURITY NUMBER OF PARENT NAMED.
Item 5, the legal representative of the estate

5. LEGAL REPRESENTATIVE OF THE DECEASED'S ESTATE (Skip this item if relatives are listed in 1, 2, or 4.)
NAME OF LEGAL REPRESENTATIVE (Please print) and ADDRESS OF LEGAL REPRESENTATIVE (Please print house number, street, apt. number, P.O. Box, rural route, city, state, and ZIP code.)
NOTE: If you are applying as legal representative, please submit a certified copy of your letters of appointment.
Signature, date, telephone and mailing address
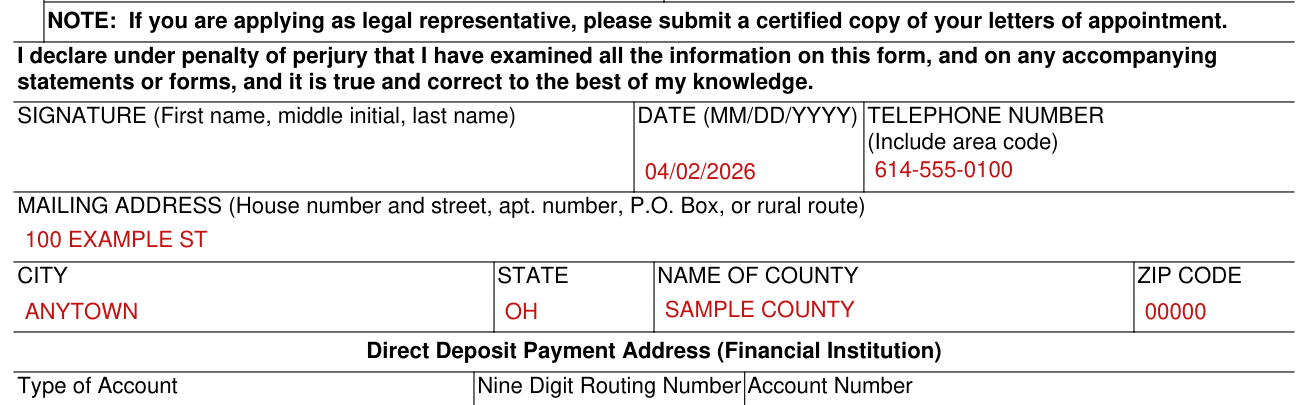
I declare under penalty of perjury that I have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of my knowledge.
SIGNATURE (First name, middle initial, last name), DATE (MM/DD/YYYY) and TELEPHONE NUMBER (Include area code).
MAILING ADDRESS (House number and street, apt. number, P.O. Box, or rural route), CITY, STATE, NAME OF COUNTY and ZIP CODE.
Direct deposit

Direct Deposit Payment Address (Financial Institution): Type of Account Checking or Savings, Nine Digit Routing Number and Account Number.
Witnesses, only if signed by mark (X)
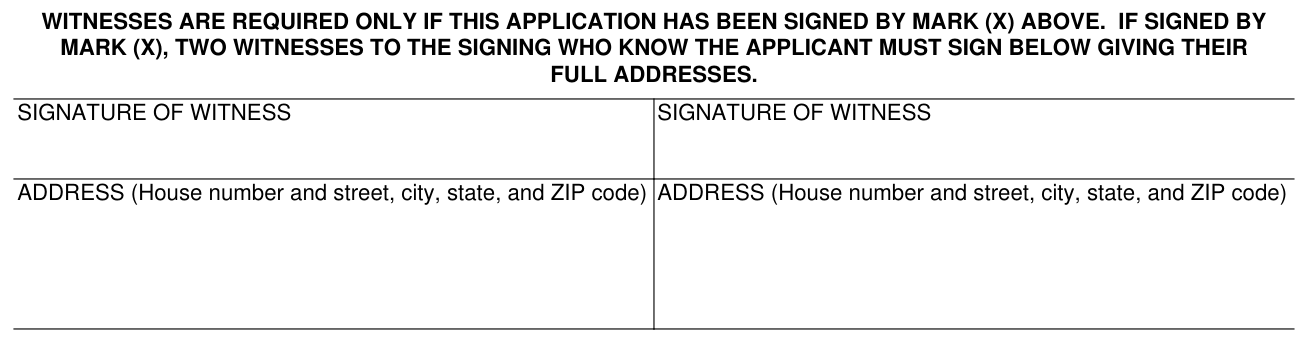
Common mistake: WITNESSES ARE REQUIRED ONLY IF THIS APPLICATION HAS BEEN SIGNED BY MARK (X) ABOVE. IF SIGNED BY MARK (X), TWO WITNESSES TO THE SIGNING WHO KNOW THE APPLICANT MUST SIGN BELOW GIVING THEIR FULL ADDRESSES.
SIGNATURE OF WITNESS and ADDRESS (House number and street, city, state, and ZIP code).
More rules for Form SSA-1724-F4
Remarks: If you need more space for explaining any answers to the questions, attach a separate sheet.
Common questions about Form SSA-1724-F4
What is form SSA-1724 for?
The Social Security Administration form is the CLAIM FOR AMOUNTS DUE IN THE CASE OF A DECEASED BENEFICIARY.
Who qualifies for SSA 1724?
The deceased may have been due a Social Security payment and/or a Medicare Premium refund. The Social Security Act provides that amounts due a deceased may be paid to the next of kin or the legal representative of the estate under priorities established in the law. To help us decide who should receive any payment due, please COMPLETE THIS ENTIRE FORM and RETURN it to us in the enclosed envelope.
Sources
[1] Form SSA-1724-F4 (10-2024), Claim for Amounts Due in the Case of a Deceased Beneficiary, Social Security Administration (the Official source link on this page).
