
Form SSA-789 at a glance
What it is: Form SSA-789 (04-2026) is the Request for Reconsideration, Disability Cessation Right to Appear of the Social Security Administration.
Who signs: c. No signature is required on the SSA-789 to process a reconsideration request.[2]
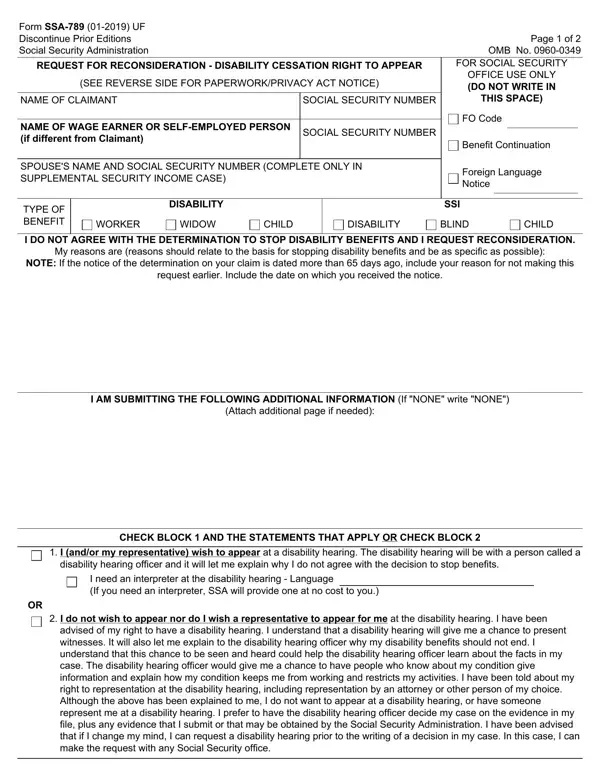
A filled-in Form SSA-789 example: a worker asks for a disability hearing

How to fill out Form SSA-789, box by box
Claimant, wage earner and spouse

Enter the Name of Claimant and the Social Security Number.
Enter the Name of Wage Earner or Self-Employed Person (if different from Claimant) and the Social Security Number.
Complete the Spouse's Name and Social Security Number only in a Supplemental Security Income case.
Type of benefit

Under Type of Benefit, mark Worker, Widow or Child under Disability, or Disability, Blind or Child under SSI.
Your reasons and the notice date

Your reasons for not agreeing with the determination to stop disability benefits should relate to the basis for stopping disability benefits and be as specific as possible. If the notice of the determination on your claim is dated more than 65 days ago, include your reason for not making this request earlier. Include the date on which you received the notice.
Additional information

If "NONE" write "NONE" under the additional information you are submitting (attach additional page if needed). You do not need to provide additional information or evidence to submit this form. You will be able to provide additional evidence until the date of the hearing. It is preferable that you provide additional information or evidence at the earliest possible time.
The disability hearing

Check block 1 and the statements that apply or check block 2.
I (and/or my representative) wish to appear at a disability hearing. The disability hearing will be with a person called a disability hearing officer and it will let me explain why I do not agree with the decision to stop benefits.
If you need an interpreter at the disability hearing, write the Language; SSA will provide one at no cost to you.
I do not wish to appear nor do I wish a representative to appear for me at the disability hearing and I request that a decision be made based on the evidence in my case (Complete SSA-773 Waiver of Right to Appear - Disability Hearing).
Addresses for the claimant and representative
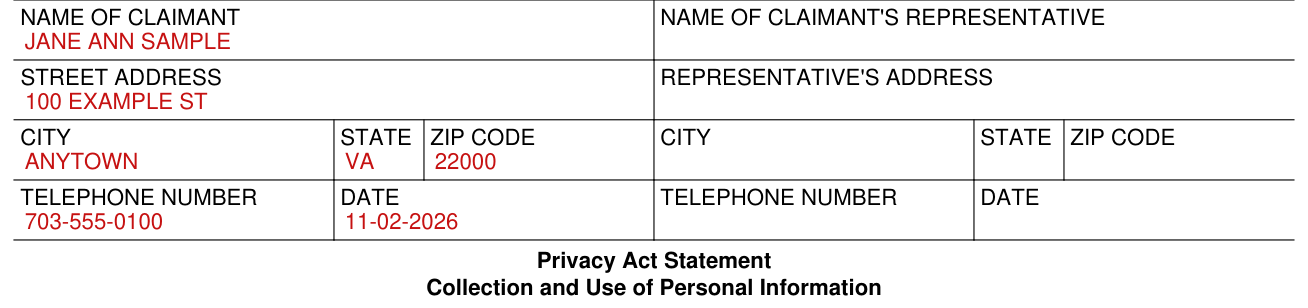
Enter addresses for both the claimant and representative (if represented): the Name of Claimant, Street Address, City, State, Zip Code, Telephone Number and Date, and the Name of Claimant's Representative, Representative's Address, City, State, Zip Code, Telephone Number and Date.
Common questions about Form SSA-789
Who signs it?
c. No signature is required on the SSA-789 to process a reconsideration request.[2]
Is there a penalty?
Anyone who knowingly makes or causes to be made a false statement or representation of material fact for use in determining a payment under the Social Security Act, or knowingly conceals or fails to disclose an event with an intent to affect an initial or continued right to payment, or submits or causes to be submitted any false statement or document knowing the same to contain any misrepresentation of material fact, commits a crime punishable under Federal law by fine, imprisonment, or both, and may be subject to administrative sanctions.
Sources
[1] Form SSA-789 (04-2026), Request for Reconsideration - Disability Cessation Right to Appear, Social Security Administration (the Official source link on this page).
[2] secure.ssa.gov, signature_rule (secure.ssa.gov). Accessed November 2, 2026.