
How to Fill Out Form HA-4631

Form HA-4631 at a glance

What it is: Form HA-4631, Claimant's Recent Medical Treatment, is a form of the Social Security Administration Office of Disability Adjudication.

A filled-in Form HA-4631 example: one doctor visit and no hospital stay

Form HA-4631 example filled out, example: one doctor visit and no hospital stay
Jane Ann Sample completes B of Form HA-4631 for her claim. The Hearing Office completes A. She saw one doctor since the date in A and was not hospitalized. The picture shows page 1, and its names and figures are sample values. The Wage Earner box is left blank because the wage earner is the claimant. The hospital lines stay empty because she was not hospitalized.

How to fill out Form HA-4631, box by box

A. To be completed by Hearing Office

Form HA-4631 example filled out, a. To be completed by Hearing Office

The Hearing Office completes A.

The Hearing Office enters the Claimant and Social Security Number, and the Wage Earner and Social Security Number (leave blank if same as claimant).

The Hearing Office enters the date for the last time your case was brought up-to-date.

1. Treated or examined by a doctor
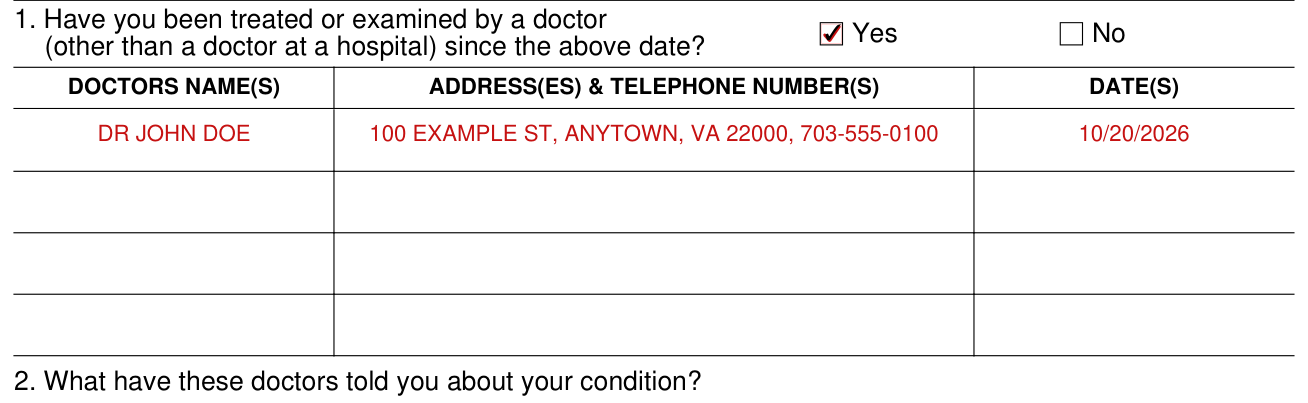
Form HA-4631 example filled out, 1. Treated or examined by a doctor

The Claimant completes B. PLEASE PRINT and answer the following questions.

For 1, mark Yes or No: have you been treated or examined by a doctor (other than a doctor at a hospital) since the date in A?

Under DOCTORS NAME(S), ADDRESS(ES) & TELEPHONE NUMBER(S) and DATE(S), enter each doctor's name, address and telephone number, and the date or dates.

2. What the doctors told you about your condition
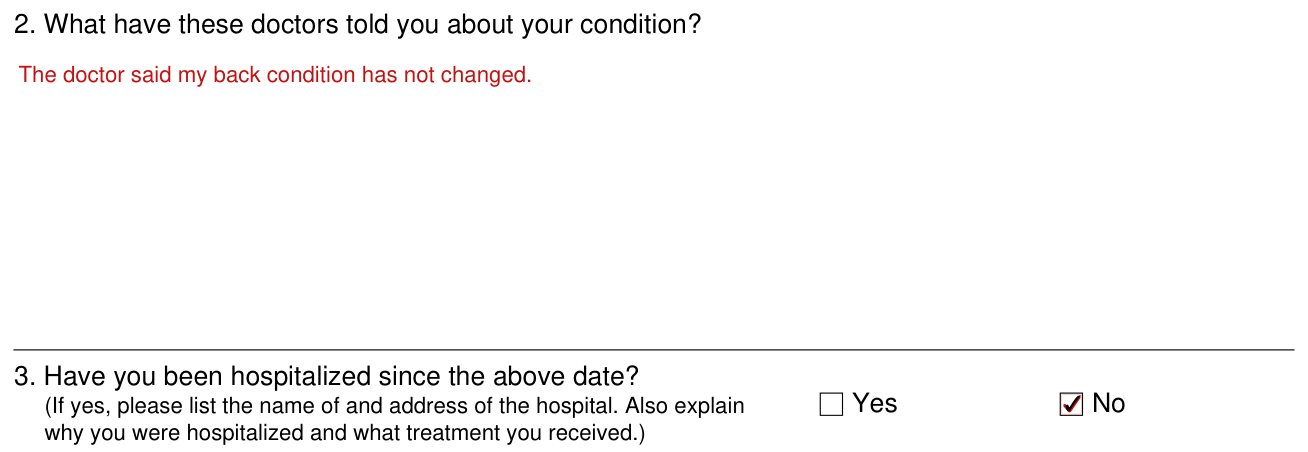
Form HA-4631 example filled out, 2. What the doctors told you about your condition

For 2, write what these doctors have told you about your condition.

3. Hospitalized since the date in A
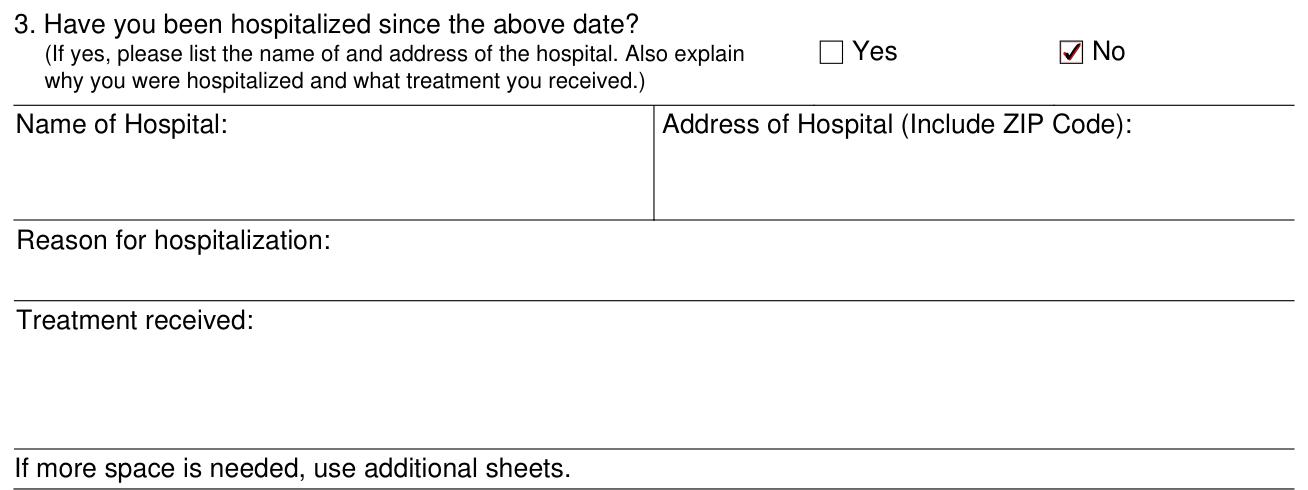
Form HA-4631 example filled out, 3. Hospitalized since the date in A

For 3, mark Yes or No: have you been hospitalized since the date in A? If yes, list the name of and address of the hospital, and explain why you were hospitalized and what treatment you received.

If yes, enter the Name of Hospital and the Address of Hospital (include ZIP Code).

If yes, enter the Reason for hospitalization and the Treatment received.

More rules for Form HA-4631

If more space is needed, use additional sheets.

Sources

[1] Form HA-4631 (09-2026), Claimant's Recent Medical Treatment, Social Security Administration (the Official source link on this page).

Form HA-4631 PDF Details

To be completed by the Claimant: please print and answer the following questions.

Above date: the last time the case was brought up-to-date is in A, to be completed by Hearing Office.

Doctors: have you been treated or examined by a doctor (other than a doctor at a hospital) since the above date?

Hospital: have you been hospitalized since the above date? If yes, list the name and address of the hospital, why you were hospitalized and what treatment you received.

More space: if more space is needed, use additional sheets.

Voluntary: providing the information is voluntary, but not providing all or part of the information may prevent an accurate and timely decision on any claim filed.

QuestionAnswer
Form NameForm HA-4631
Form Length2 pages
Fillable?Yes
Fillable fields26
Avg. time to fill out5 min
EditionRev 09-2026
Issuing agencySocial Security Administration Office of Disability Adjudication
Other namesHA-4631, HA4631, Form HA-4631, SSA HA-4631, Claimant's Recent Medical Treatment
Official sourceForm HA-4631 (Rev 09-2026), Social Security Administration Office of Disability Adjudication