

State Form 42070 at a glance
What it is: State Form 42070 is the Application for Disability License Plate or Parking Placard of the Indiana Bureau of Motor Vehicles.
Where and when to file: Applications may be mailed to the Winchester Mail Processing Center, Bureau of Motor Vehicles, PO Box 100, Winchester, IN 47394.
To apply for a new disability license plate, complete Sections 1 and 2.
To apply for a disability parking placard, complete Sections 1 and 3.
A filled-in State Form 42070 example: an applicant with a permanent placard applies for a disability license plate
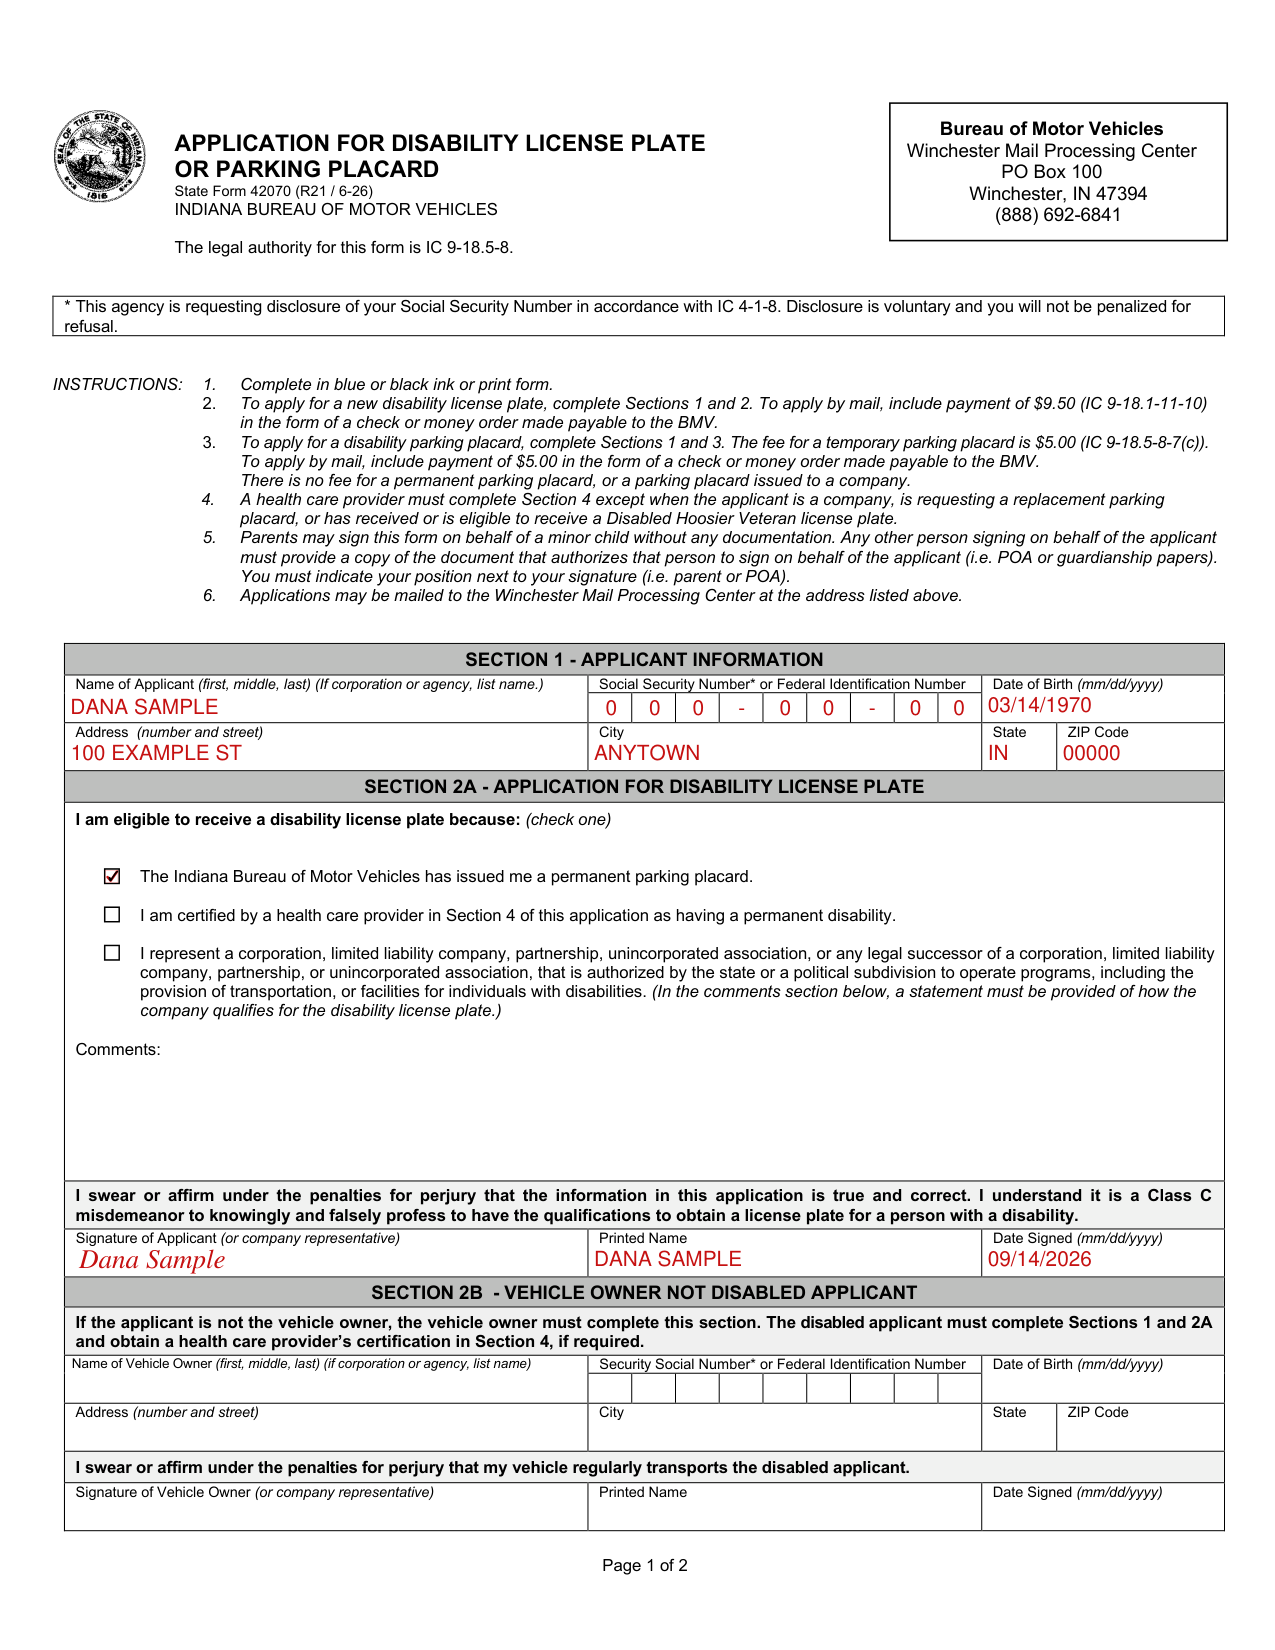
How to fill out State Form 42070, box by box
Section 1 - Applicant Information
Enter the Name of Applicant (first, middle, last). If corporation or agency, list name.
With the Name of Applicant, the Social Security Number* or Federal Identification Number: this agency is requesting disclosure of your Social Security Number in accordance with IC 4-1-8. Disclosure is voluntary and you will not be penalized for refusal.
Enter the Date of Birth (mm/dd/yyyy), then the Address (number and street), City, State and ZIP Code.
Section 2A - Application for Disability License Plate
Check one box under "I am eligible to receive a disability license plate because". The Indiana Bureau of Motor Vehicles has issued you a permanent parking placard.
You are certified by a health care provider in Section 4 of this application as having a permanent disability.
You represent a corporation, limited liability company, partnership, unincorporated association, or any legal successor of a corporation, limited liability company, partnership, or unincorporated association, that is authorized by the state or a political subdivision to operate programs, including the provision of transportation, or facilities for individuals with disabilities.
To apply by mail, include payment of $9.50 (IC 9-18.1-11-10) in the form of a check or money order made payable to the BMV (checked October 20, 2026).
Section 2A - Comments
If you represent a company, enter in Comments a statement of how the company qualifies for the disability license plate.
Section 2A - Signature of Applicant (or company representative), Printed Name and Date Signed
Sign in Signature of Applicant (or company representative) and enter the Printed Name and Date Signed (mm/dd/yyyy) to swear or affirm under the penalties for perjury that the information in this application is true and correct.
It is a Class C misdemeanor to knowingly and falsely profess to have the qualifications to obtain a license plate for a person with a disability.
Section 2B - Vehicle Owner Not Disabled Applicant
If the applicant is not the vehicle owner, the vehicle owner must complete this section.
The disabled applicant must complete Sections 1 and 2A and obtain a health care provider's certification in Section 4, if required.
Enter the Name of Vehicle Owner (first, middle, last) (if corporation or agency, list name), the Social Security Number* or Federal Identification Number, the Date of Birth (mm/dd/yyyy), and the Address (number and street), City, State and ZIP Code.
Sign in Signature of Vehicle Owner (or company representative) and enter the Printed Name and Date Signed (mm/dd/yyyy) to swear or affirm under the penalties for perjury that your vehicle regularly transports the disabled applicant.
Section 3 - I am applying for the following type of disability parking placard
Under "I am applying for the following type of disability parking placard", check one box.
Permanent: the placard expires only upon the health care provider's certification that the person's disability is no longer permanent.
Temporary: the placard expires on the date indicated by the health care provider or one (1) year after the date of issuance, whichever occurs first.
Company: the placard expires on January 1 of the fourth year after the year in which the placard is issued or the date on which the company ceases operations, whichever occurs first.
The fee for a temporary parking placard is $5.00 (IC 9-18.5-8-7(c)) (checked October 20, 2026).
To apply by mail, include payment of $5.00 in the form of a check or money order made payable to the BMV (checked October 20, 2026).
There is no fee for a permanent parking placard, or a parking placard issued to a company.
Section 3 - I am eligible to receive a disability parking placard because
Check one box under "I am eligible to receive a disability parking placard because". You are certified by a health care provider in Section 4 of this application as having a permanent or temporary disability.
You are applying for a duplicate placard because the permanent or temporary placard previously issued to you has been lost, stolen, damaged, or destroyed.
You have been issued or are otherwise eligible to receive a Disabled Hoosier Veteran license plate.
If you represent a company, enter in Comments a statement of how the company qualifies for the disability parking placard.
Section 3 - Signature of Applicant (or company representative), Printed Name and Date Signed
Sign in Signature of Applicant (or company representative) and enter the Printed Name and Date Signed (mm/dd/yyyy).
It is a Class C misdemeanor to knowingly and falsely profess to have the qualifications to obtain a disability parking placard.
Section 4 - Health Care Provider's Certification
A health care provider must complete Section 4 except when the applicant is a company, is requesting a replacement parking placard, or has received or is eligible to receive a Disabled Hoosier Veteran license plate.
Enter the Name of Disabled Applicant (first, middle, last) and Date of Birth (mm/dd/yyyy). Certify that the applicant has a qualifying disability as described in IC 9-18.5-8 and that such disability is: (check one)
Check Permanent, or check "Temporary and is expected to end on:" and enter / / (mm/dd/yyyy).
Check one box under "I further certify that the applicant has/is". A physical disability that requires the use of a wheelchair, a walker, braces, or crutches.
Lost the use of one (1) or both legs.
A severe restriction in mobility due to a pulmonary or cardiovascular disability, an arthritic condition, or an orthopedic, neurological impairment or autism spectrum disorder.
Blind (as defined in IC 12-7-2.1-38(2)) or visually impaired (as defined in IC 12-7-2.1-349).
Check one box under "I certify that I am".
Sign in Signature of Health Care Provider and enter the Printed Name, Date Signed (mm/dd/yyyy), Telephone Number, License Number, and Address (number and street), City, State and ZIP Code.
If your situation is different
You apply by mail
Applications may be mailed to the Winchester Mail Processing Center, Bureau of Motor Vehicles, PO Box 100, Winchester, IN 47394.
You sign on behalf of the applicant
Parents may sign this form on behalf of a minor child without any documentation.
Any other person signing on behalf of the applicant must provide a copy of the document that authorizes that person to sign on behalf of the applicant (i.e. POA or guardianship papers).
You must indicate your position next to your signature (i.e. parent or POA).
A health care provider certifies that a person's disability is no longer permanent
A health care provider may certify that a person's disability is no longer permanent by mailing a letter to the Indiana BMV explaining the person is no longer permanently disabled.
Please provide as much of the person's information as possible.
Mail the letter to the Indiana Bureau of Motor Vehicles, Registrations Department, 100 N. Senate Avenue, N483, Indianapolis, IN 46204.
Before you go
Complete in blue or black ink or print form.
Sources
[1] State Form 42070, Application for Disability License Plate or Parking Placard, Indiana Bureau of Motor Vehicles (the Official source link on this page).
