

State Form 54648 at a glance
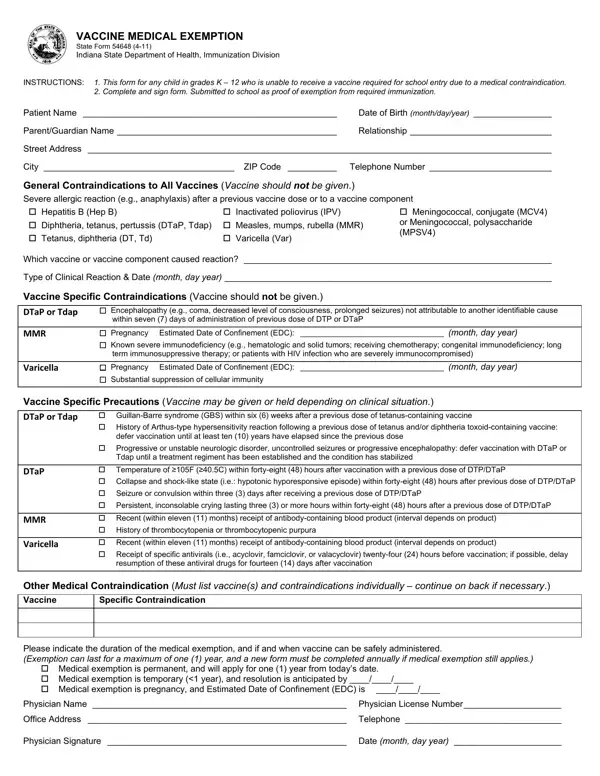
What it is: State Form 54648 is the Vaccine Medical Exemption form of the Indiana Department of Health, Immunization Division.
Who signs: Sign the Physician Signature and enter the Date (month, day year).
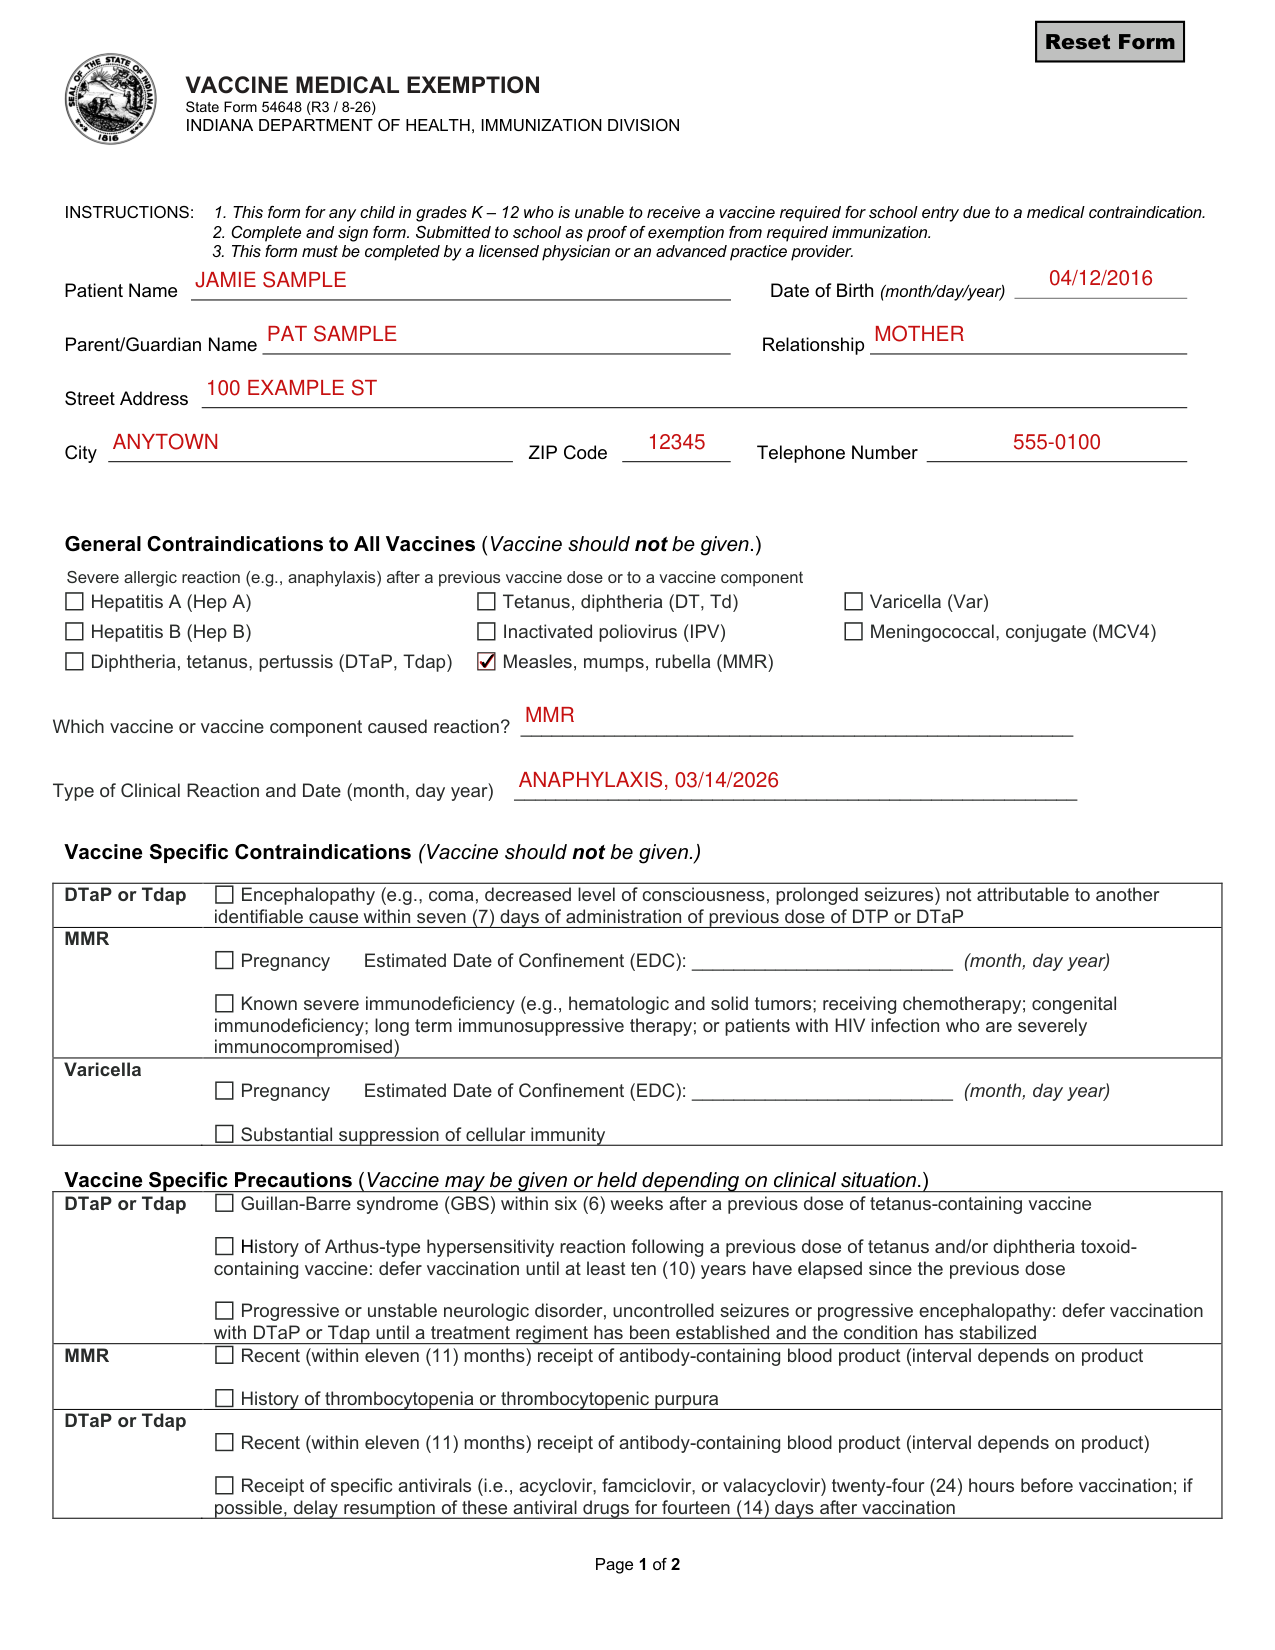
A filled-in State Form 54648 example: a child with a severe allergic reaction to a measles dose
How to fill out State Form 54648, box by box
Patient Name, Parent/Guardian Name and Street Address

Enter the Patient Name and the Date of Birth (month/day/year).
Enter the Parent/Guardian Name and the Relationship.
Enter the Street Address.
Enter the City, ZIP Code and Telephone Number.
General Contraindications to All Vaccines

Severe allergic reaction (e.g., anaphylaxis) after a previous vaccine dose or to a vaccine component is a General Contraindication to All Vaccines (Vaccine should not be given.).
Mark: Hepatitis A (Hep A), Hepatitis B (Hep B), Diphtheria, tetanus, pertussis (DTaP, Tdap), Tetanus, diphtheria (DT, Td), Inactivated poliovirus (IPV), Measles, mumps, rubella (MMR), Varicella (Var), Meningococcal, conjugate (MCV4).
Write which vaccine or vaccine component caused reaction, and the Type of Clinical Reaction and Date (month, day year).
Vaccine Specific Contraindications

Vaccine Specific Contraindications: Vaccine should not be given.
Encephalopathy (e.g., coma, decreased level of consciousness, prolonged seizures) not attributable to another identifiable cause within seven (7) days of administration of previous dose of DTP or DTaP. MMR: Pregnancy, Estimated Date of Confinement (EDC): (month, day year).
MMR: Known severe immunodeficiency (e.g., hematologic and solid tumors; receiving chemotherapy; congenital immunodeficiency; long term immunosuppressive therapy; or patients with HIV infection who are severely immunocompromised). Varicella: Pregnancy, Estimated Date of Confinement (EDC): (month, day year); Substantial suppression of cellular immunity.
Vaccine Specific Precautions

Vaccine Specific Precautions: Vaccine may be given or held depending on clinical situation. DTaP or Tdap: Guillan-Barre syndrome (GBS) within six (6) weeks after a previous dose of tetanus-containing vaccine.
History of Arthus-type hypersensitivity reaction following a previous dose of tetanus and/or diphtheria toxoid-containing vaccine: defer vaccination until at least ten (10) years have elapsed since the previous dose.
Progressive or unstable neurologic disorder, uncontrolled seizures or progressive encephalopathy: defer vaccination with DTaP or Tdap until a treatment regiment has been established and the condition has stabilized.
MMR: Recent (within eleven (11) months) receipt of antibody-containing blood product (interval depends on product); History of thrombocytopenia or thrombocytopenic purpura. DTaP or Tdap: Recent (within eleven (11) months) receipt of antibody-containing blood product (interval depends on product).
Receipt of specific antivirals (i.e., acyclovir, famciclovir, or valacyclovir) twenty-four (24) hours before vaccination; if possible, delay resumption of these antiviral drugs for fourteen (14) days after vaccination.
Other Medical Contraindication
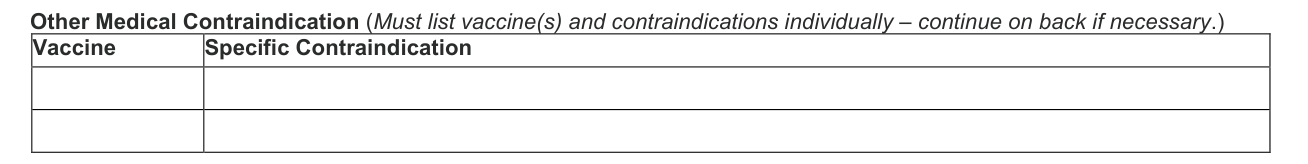
Other Medical Contraindication: Must list vaccine(s) and contraindications individually - continue on back if necessary. Enter the Vaccine and the Specific Contraindication.
Duration of the medical exemption

Please indicate the duration of the medical exemption, and if and when vaccine can be safely administered: Medical exemption is permanent, and will apply for one (1) year from today's date; Medical exemption is temporary (<1 year), and resolution is anticipated by (month, day, year); or Medical exemption is pregnancy, and Estimated Date of Confinement (EDC) is (month, day, year).
Exemption can last for a maximum of one (1) year, and a new form must be completed annually if medical exemption still applies.
Physician License Number, Office Address and Physician Signature

This form is for any child in grades K - 12 who is unable to receive a vaccine required for school entry due to a medical contraindication. Complete and sign form. Submitted to school as proof of exemption from required immunization. This form must be completed by a licensed physician or an advanced practice provider.
Enter the Physician License Number.
Enter the Office Address and Telephone.
Sources
[1] State Form 54648 (R3 / 8-26), Vaccine Medical Exemption, Indiana Department of Health, Immunization Division (the Official source link on this page).