


State Form 9977 at a glance
What it is: State Form 9977 is the Radiation Machine Registration Application of the Indiana Department of Health, Division of Radiology and Weights and Measures.
Who signs: The agreement should be signed by a person who has legal responsibility for the radiation machine(s) at the facility (i.e. owner, hospital administrator, corporation director, etc.)
A filled-in State Form 9977 example: a new dental practice registers

How to fill out State Form 9977, box by box
Please check one

Please check one: New Facility, Update Facility (new machine, new location, etc.), Routine Inspection.
This registration must also be updated whenever the information contained in it changes (such as change in location, ownership, or name).
Facility information

Under FACILITY INFORMATION, enter the Facility registration number, Name of facility, Date (month, day, year), Address (number and street), City, state, and ZIP code, and County.
If this is a previously unregistered facility, leave the Facility registration number box blank.
If the facility has no name, list the doctor's name.
Mailing address, if different from physical address
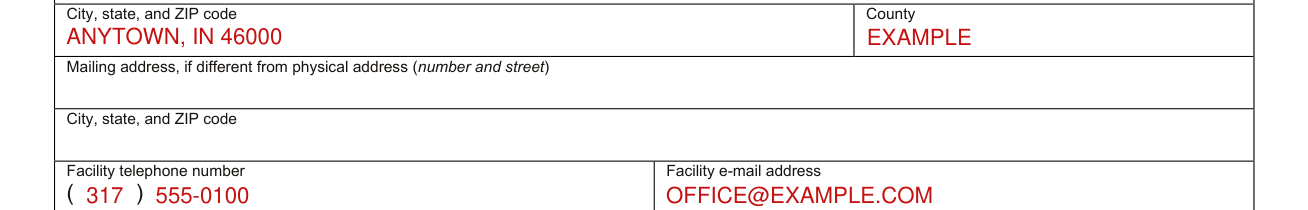
Enter the Mailing address, if different from physical address (number and street), and the City, state, and ZIP code.
If the mailing address is different than the physical address of the facility, list both addresses.
Facility telephone number and e-mail address
Enter the Facility telephone number and the Facility e-mail address.
Name of Radiation Safety Officer (RSO)
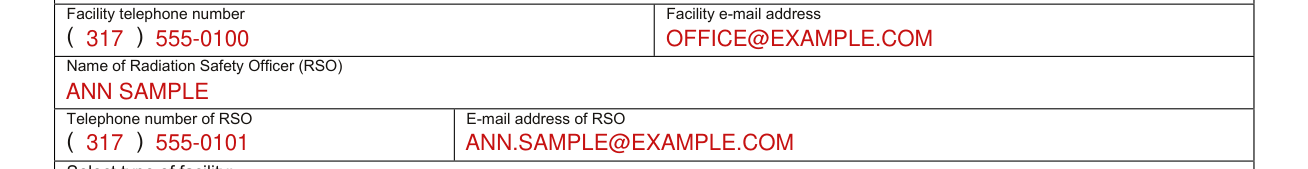
Enter the Name of Radiation Safety Officer (RSO), the Telephone number of RSO and the E-mail address of RSO.
The radiation safety officer must be an employee of the facility and is the individual responsible for radiation safety at the facility.
Select type of facility

Select type of facility: X - Dental, 3 - Educational (Schools / Colleges), 6 - Veterinarian, 1 - Hospital, 4 - Podiatric, 7 - Industrial, 2 - Physicians / Clinics / Mobile, 5 - Chiropractic, 8 - Other.
Signature of responsible individual
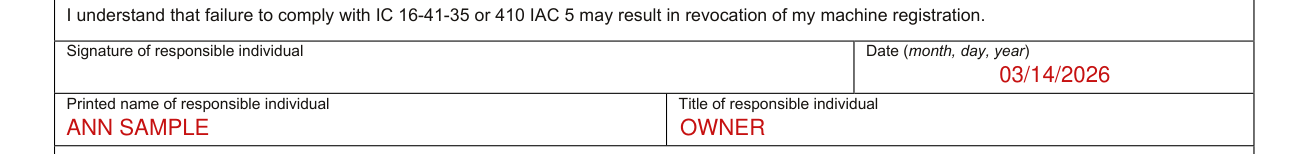
I understand that failure to comply with IC 16-41-35, or 410 IAC 5 may result in revocation of my machine registration.
Enter the Signature of responsible individual, the Date (month, day, year), the Printed name of responsible individual and the Title of responsible individual.
Personnel radiation exposure monitoring (All Facilities)
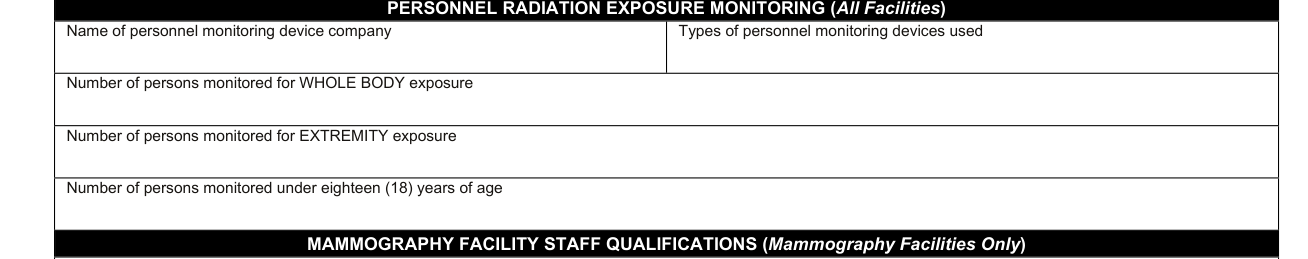
Under PERSONNEL RADIATION EXPOSURE MONITORING (All Facilities), enter the Name of personnel monitoring device company, the Types of personnel monitoring devices used, the Number of persons monitored for WHOLE BODY exposure, the Number of persons monitored for EXTREMITY exposure and the Number of persons monitored under eighteen (18) years of age.
Mammography facility staff qualifications (Mammography Facilities Only)
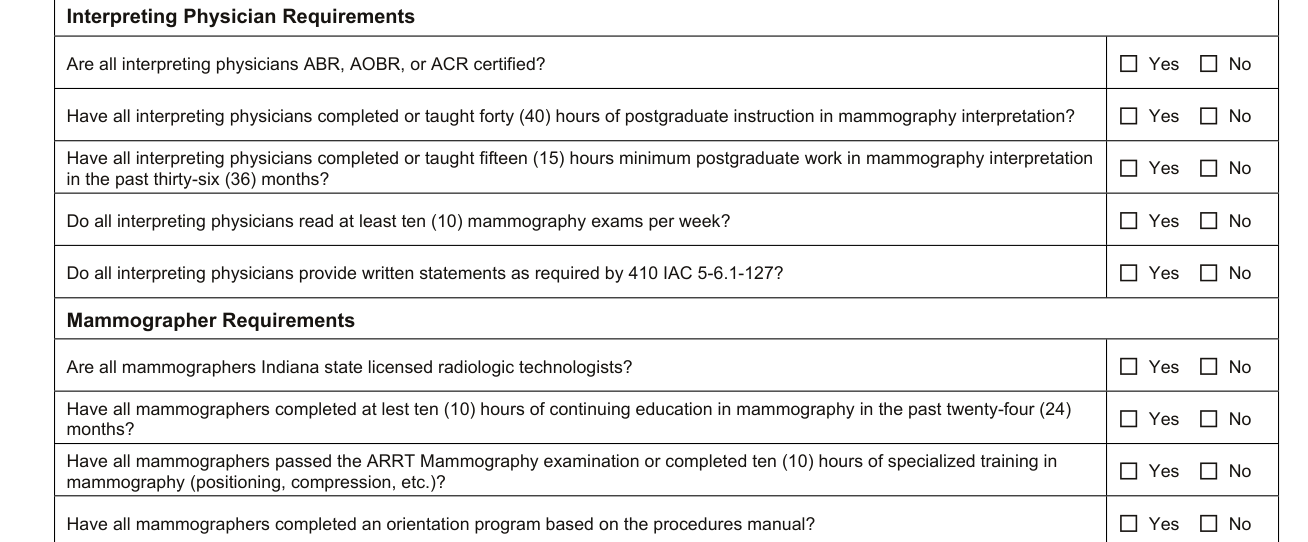
Under MAMMOGRAPHY FACILITY STAFF QUALIFICATIONS (Mammography Facilities Only), under Interpreting Physician Requirements: Are all interpreting physicians ABR, AOBR, or ACR certified? Have all interpreting physicians completed or taught forty (40) hours of postgraduate instruction in mammography interpretation? Have all interpreting physicians completed or taught fifteen (15) hours minimum postgraduate work in mammography interpretation in the past thirty-six (36) months? Do all interpreting physicians read at least ten (10) mammography exams per week? Do all interpreting physicians provide written statements as required by 410 IAC 5-6.1-127? Yes No
Under Mammographer Requirements: Are all mammographers Indiana state licensed radiologic technologists? Have all mammographers completed at lest ten (10) hours of continuing education in mammography in the past twenty-four (24) months? Have all mammographers passed the ARRT Mammography examination or completed ten (10) hours of specialized training in mammography (positioning, compression, etc.)? Have all mammographers completed an orientation program based on the procedures manual? Yes No
Staff qualifications (Human Use Facilities Only)
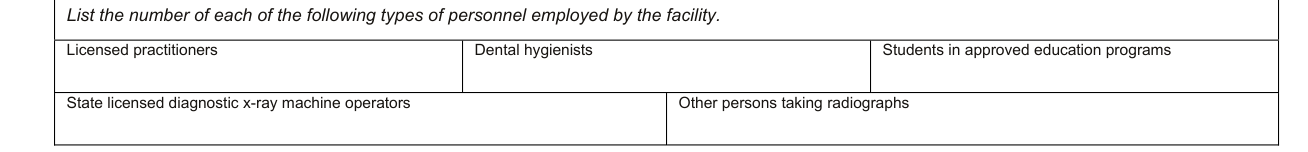
Under STAFF QUALIFICATIONS (Human Use Facilities Only [Medical, Hospital, Chiropractic, Podiatric, Dental, etc.]), list the number of the types of personnel employed by the facility: Licensed practitioners, Dental hygienists, Students in approved education programs, Other persons taking radiographs, State licensed diagnostic x-ray machine operators.
Part C facility information
Under FACILITY INFORMATION, enter the Facility registration number (from Part A) and the Name of facility (from Part A).
Machine information
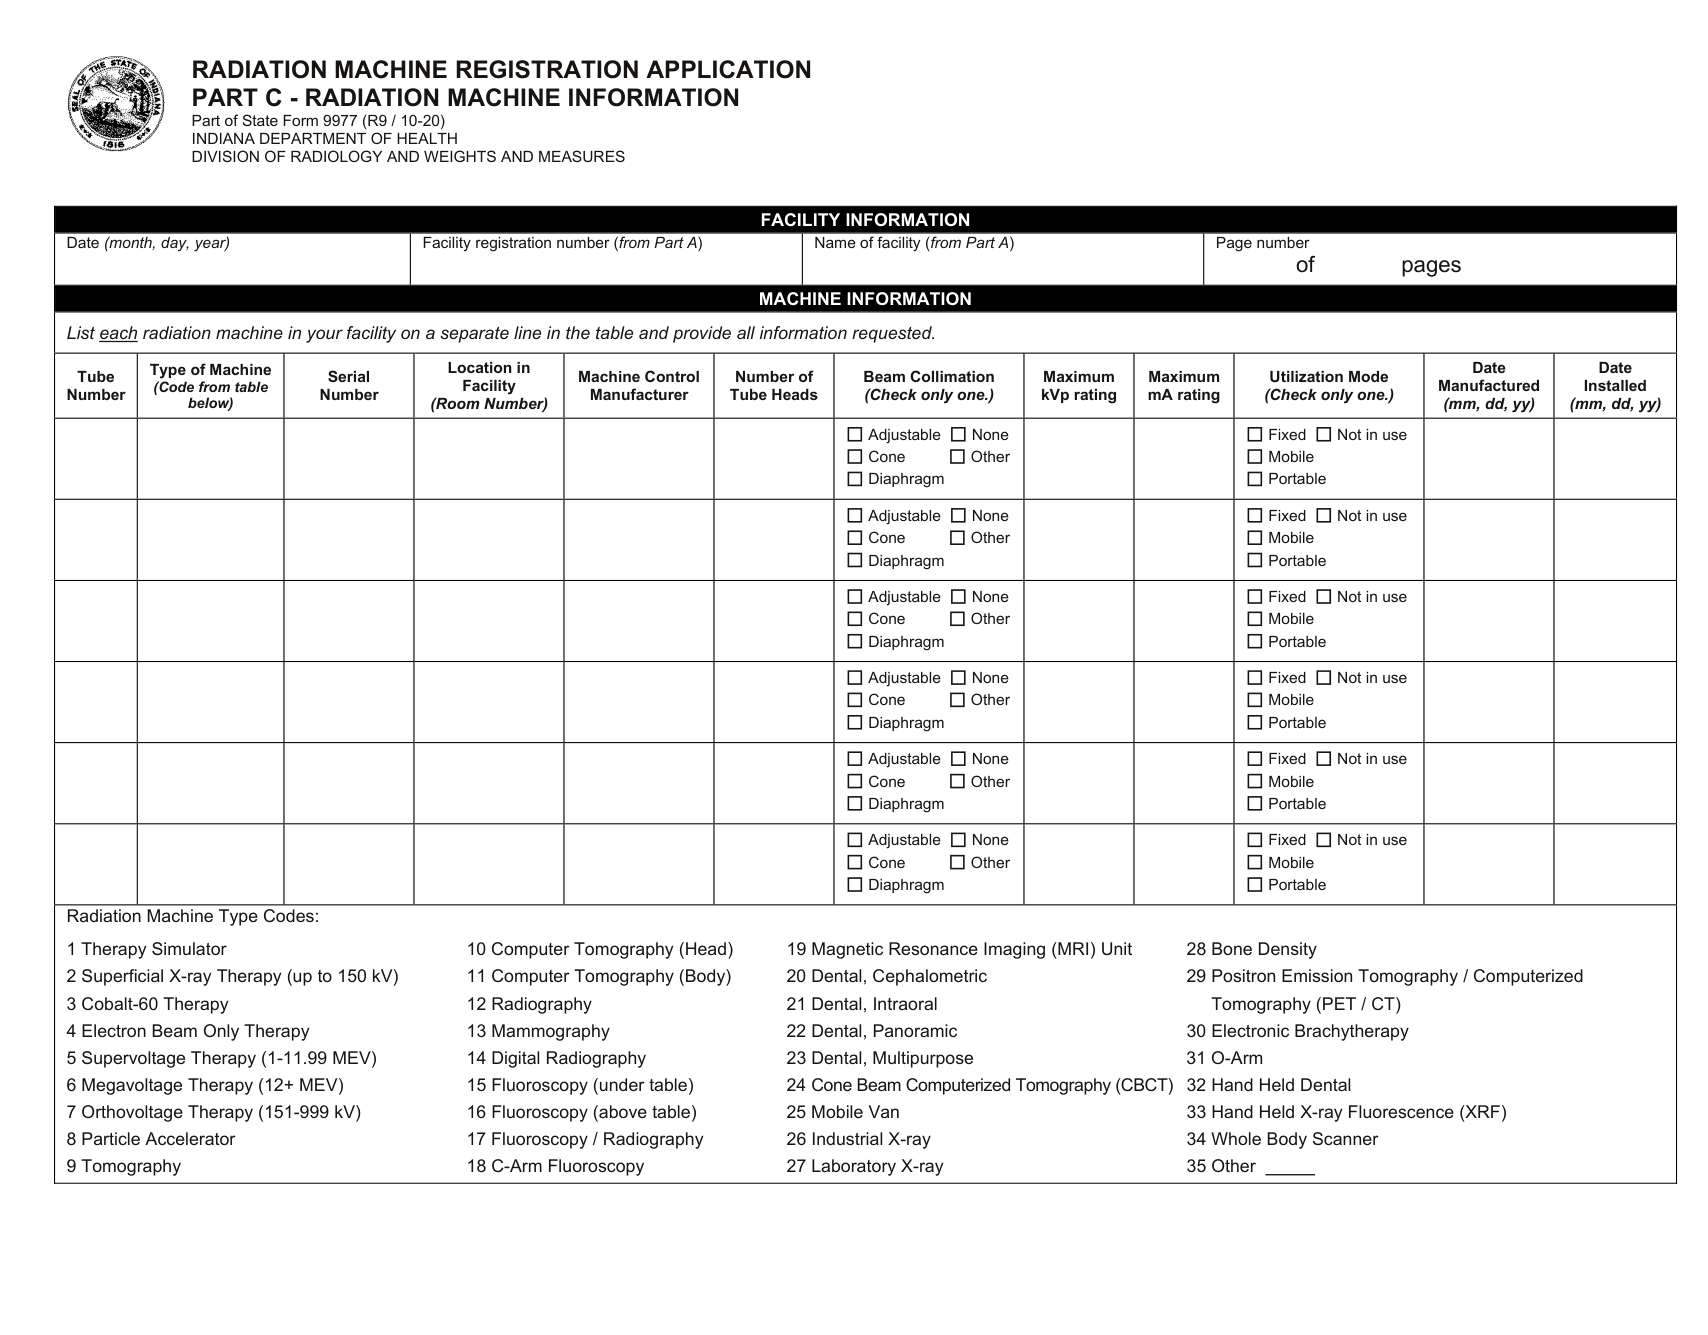
List each radiation machine in your facility on a separate line in the table and provide all information requested.
For each machine enter the Tube Number, Location in Facility (Room Number), Machine Control, Manufacturer, Serial Number, Number of Tube Heads, Beam Collimation (Check only one.), Type of Machine (Code from Radiation Machine Type Codes), Maximum kVp rating, Maximum mA rating, Utilization Mode (Check only one.), Date Manufactured (mm, dd, yy) and Date Installed (mm, dd, yy).
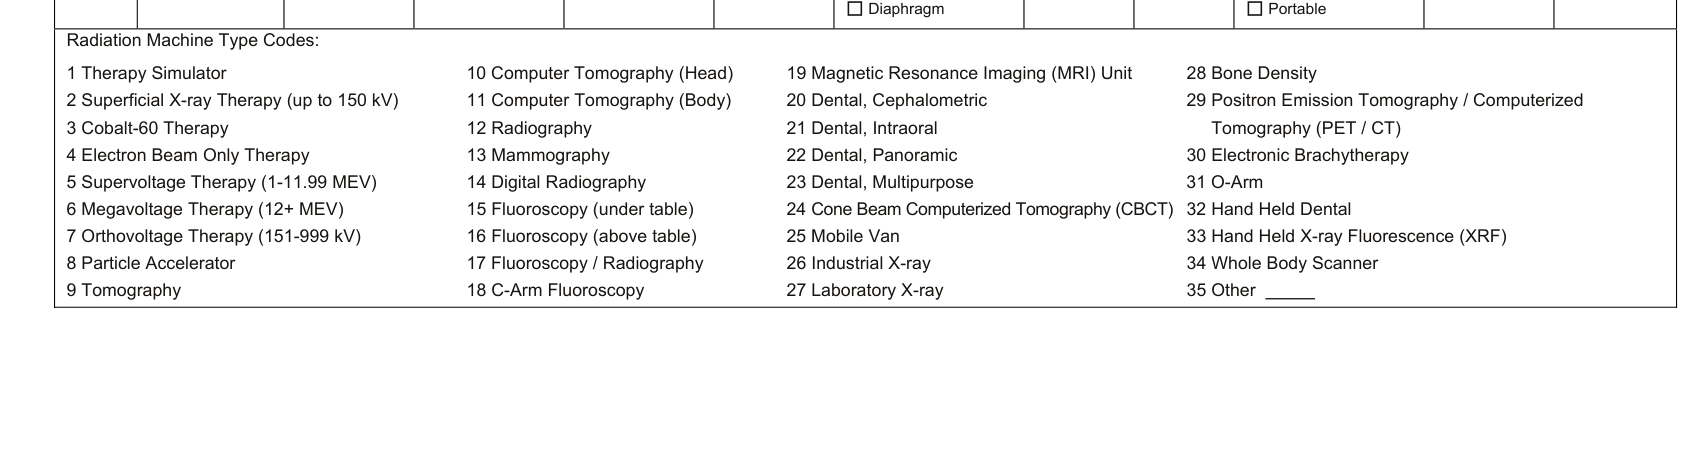
Beam Collimation (Check only one.): Adjustable Diaphragm, Adjustable Cone, Other, None.
Utilization Mode (Check only one.): Fixed, Mobile, Portable, Not in use.
On page 3, Radiation Machine Type Codes: 1 Therapy Simulator, 2 Superficial X-ray Therapy (up to 150 kV), 3 Cobalt-60 Therapy, 4 Electron Beam Only Therapy, 5 Supervoltage Therapy (1-11.99 MEV), 6 Megavoltage Therapy (12+ MEV), 7 Orthovoltage Therapy (151-999 kV), 8 Particle Accelerator, 9 Tomography, 10 Computer Tomography (Head), 11 Computer Tomography (Body), 12 Radiography, 13 Mammography, 14 Digital Radiography, 15 Fluoroscopy (under table), 16 Fluoroscopy (above table), 17 Fluoroscopy / Radiography, 18 C-Arm Fluoroscopy, 19 Magnetic Resonance Imaging (MRI) Unit, 20 Dental, Cephalometric, 21 Dental, Intraoral, 22 Dental, Panoramic, 23 Dental, Multipurpose, 24 Cone Beam Computerized Tomography (CBCT), 25 Mobile Van, 26 Industrial X-ray, 27 Laboratory X-ray, 28 Bone Density, 29 Positron Emission Tomography / Computerized Tomography (PET / CT), 30 Electronic Brachytherapy, 31 O-Arm, 32 Hand Held Dental, 33 Hand Held X-ray Fluorescence (XRF), 34 Whole Body Scanner, 35 Other.
Return Parts A, B and C of this application
Return Parts A, B and C of this application to: Indiana Department of Health, Division of Radiology and Weights and Measures, 2 North Meridian Street, 4 Selig, Indianapolis, IN 46204.
Each person having one or more radiation producing machines shall apply for registration of the machine(s) with the Indiana Department of Health before the operation of the machine(s).
More rules for State Form 9977
PLEASE TYPE OR CLEARLY PRINT ALL INFORMATION.
If you have any questions, call Mary Stiker, X-Ray Machine Inspector Coordinator, at (317) 233-4943.
Sources
[1] State Form 9977 (R9 / 10-20), Radiation Machine Registration Application, Indiana Department of Health (the Official source link on this page).