


State Form 55390 at a glance
What it is: State Form 55390 is the Indiana Application for Health Coverage.
Who signs: Fill out your application as completely as you can. It will help if you can answer all of the questions. Do not forget to sign your application on Page 1 Section 5.
If you are completing this application on behalf of someone else and you do not live in their household, provide your name and your contact information in section 33. If you do live in their household, provide your information in Section 21.
A filled-in State Form 55390 example: a woman applies for her own health coverage
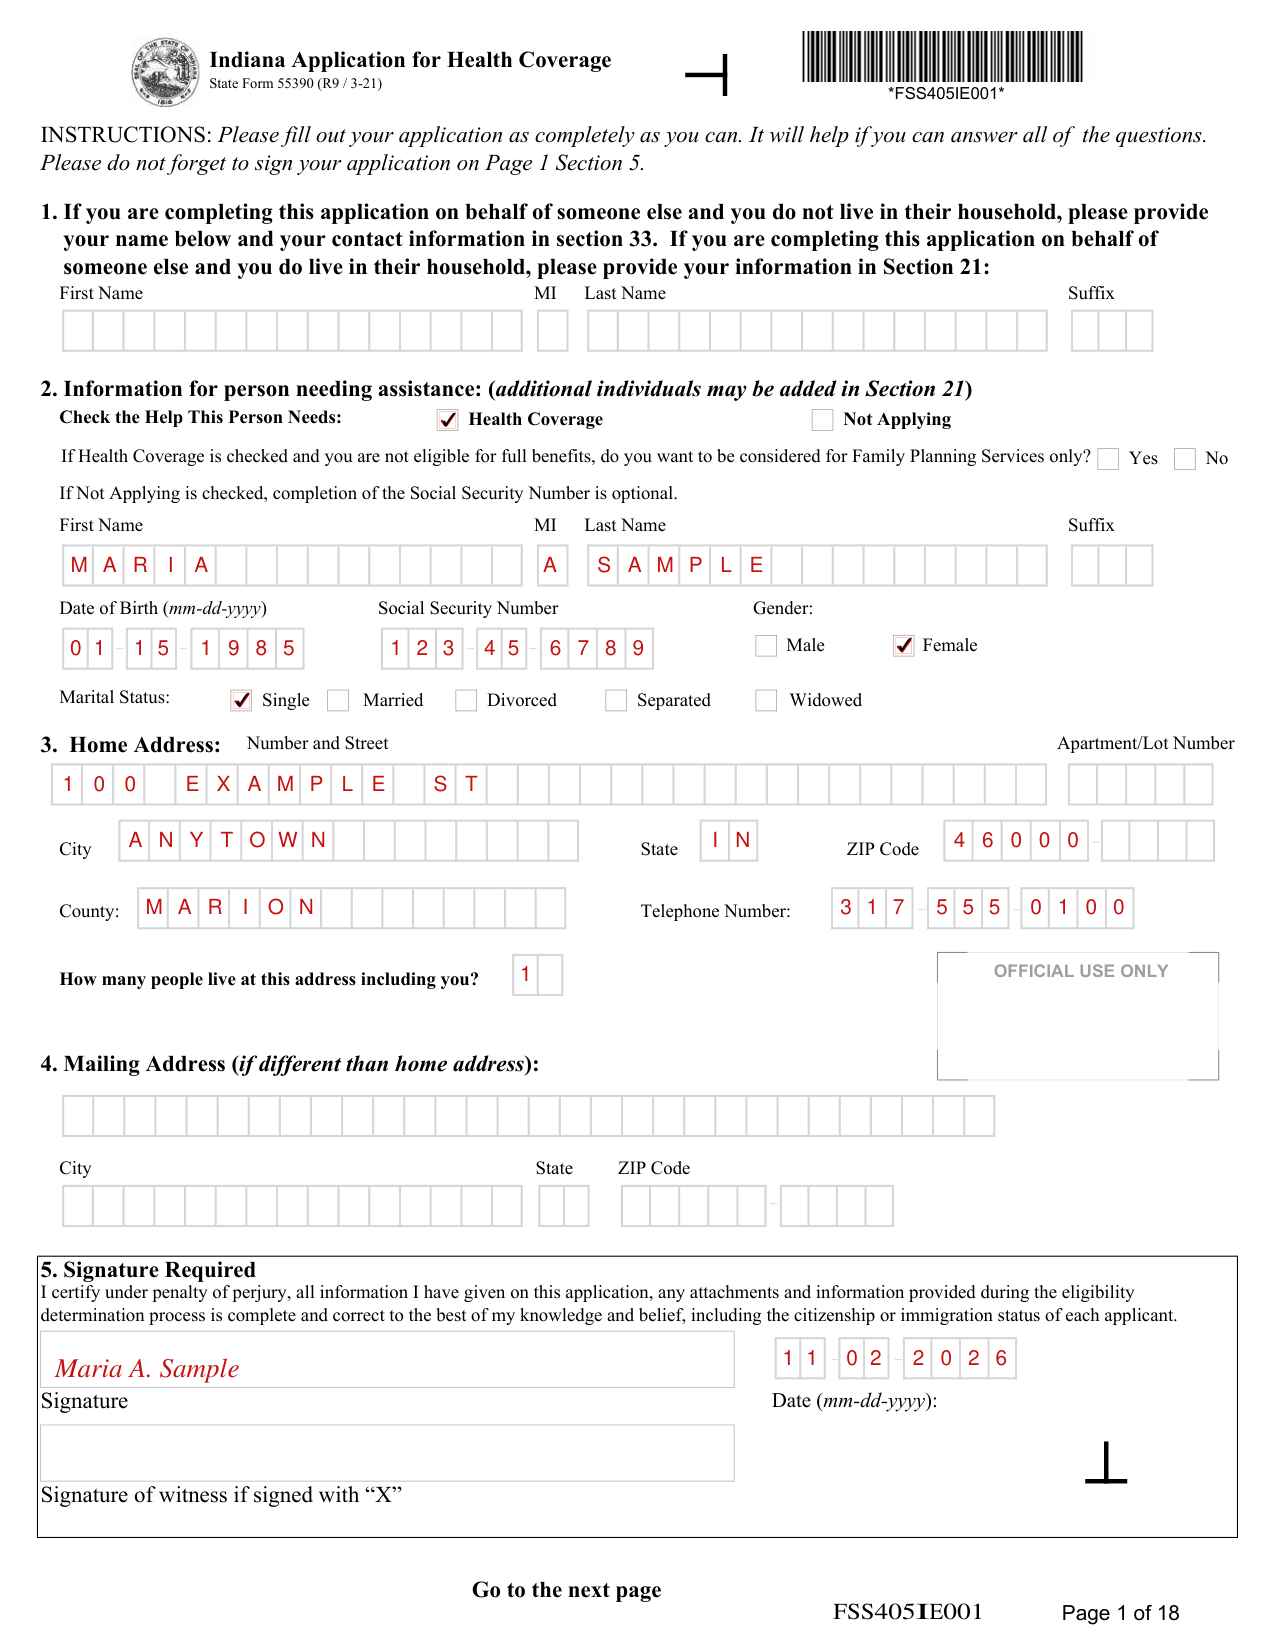
How to fill out State Form 55390, box by box
2. Information for person needing assistance

Information for person needing assistance: additional individuals may be added in Section 21.
Check the Help This Person Needs: Health Coverage or Not Applying.
If Health Coverage is checked and you are not eligible for full benefits, do you want to be considered for Family Planning Services only? Yes or No.
If Not Applying is checked, completion of the Social Security Number is optional.
Enter First Name, Last Name, MI, Social Security Number and Date of Birth (mm-dd-yyyy).
Gender: check Male or Female. Marital Status: check Single, Married, Divorced, Separated or Widowed.
3. Home Address and 4. Mailing Address
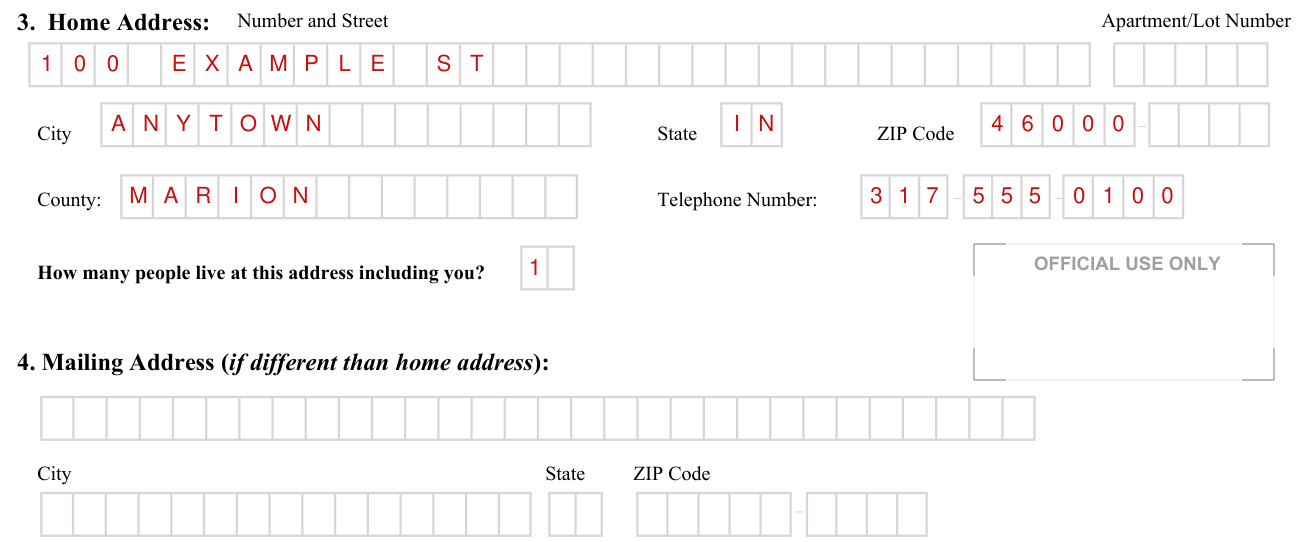
Under 3. Home Address, enter Number and Street, Apartment/Lot Number, City, State, ZIP Code, County and Telephone Number. Enter how many people live at this Home Address including you.
4. Mailing Address (if different than home address): enter City, State and ZIP Code.
5. Signature Required
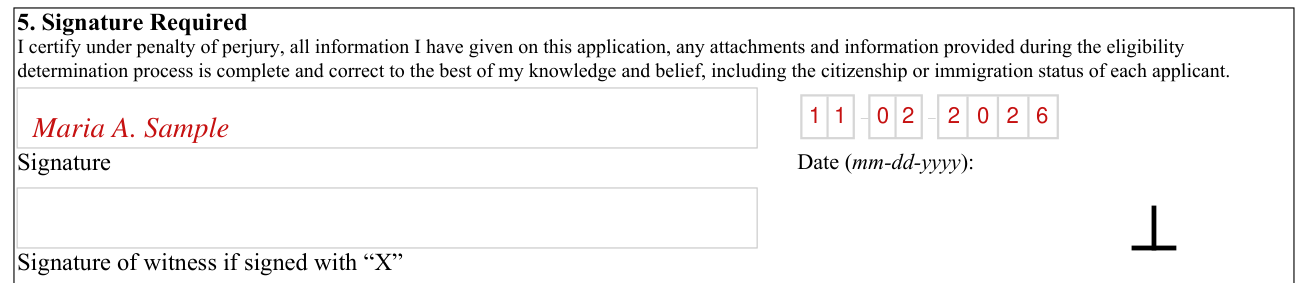
By signing you certify under penalty of perjury that all information you have given on this application, any attachments and information provided during the eligibility determination process is complete and correct to the best of your knowledge and belief, including the citizenship or immigration status of each applicant.
Enter the Date (mm-dd-yyyy). Signature of witness if signed with X.
If your situation is different
6. Ethnicity/Race (Optional)
6. Ethnicity/Race (Optional): Are you Hispanic or Latino? Yes or No. Race: select all that apply.
7. Citizenship/Immigration Information
7. Citizenship/Immigration Information: If not applying is checked, skip to Section 9. Are you a U.S. citizen or U.S. national? If no, select your immigration status: Lawful Permanent Resident, Granted Political Asylum, Parolee, No Documents available, Cuban/Haitian Entrant, Refugee, Amerasian or Other.
8. Additional Information For Person Needing Assistance
Do you live with at least one child under the age of eighteen (18), and are you the main person taking care of this child? Yes or No. Are you Pregnant? Yes or No. If yes, how many babies are expected during this pregnancy? Enter the Pregnancy begin date (mm-dd-yyyy) and Pregnancy due date (mm-dd-yyyy).
If you are age nineteen (19) or over, are you a full time student? Yes or No.
9. Tax Filing Information
9. Tax Filing Information: Are you required to file a Federal Income Tax Return? Do you plan to file a federal income tax return NEXT YEAR? (You can still apply for health insurance even if you don't file a federal income tax return.) If yes, answer questions a-c. If no, skip to question c.
a. Will you file jointly with a spouse? If yes, does the spouse live in your household?
b. Will you claim any dependents on your tax return? If yes, do the dependents live in your household?
c. Will you be claimed as a dependent on someone's tax return? Yes or No.
10. Current Employment
10. Current Employment: If you are age nineteen (19) or over, are you working at least twenty (20) hours per week? Yes or No.
Enter the Name of employer, Employer Address, Telephone number, Start Date (mm-dd-yyyy) and End Date (mm-dd-yyyy).
Are you self-employed? Yes or No. How much net income (profits once business expenses are paid) will you get from this self-employment this month?
11. Other Income
11. Other Income: check all that apply, and enter the monthly amount.
12. American Indian/Alaska Native Tribal Income
12. American Indian/Alaska Native Tribal Income: check all that apply, and enter the monthly amount.
13. Deductions and 14. Annual Income
13. Deductions: check all that apply, and give the amount and how often amount is deducted. NOTE: You shouldn't include a cost that you already considered in your answer to net self-employment in the Current Employment section.
14. Annual Income: What is your expected annual income for the current year?
15. Health Coverage Information
15. Health Coverage Information: Are you enrolled in health coverage now? If yes, check the type of coverage.
16. Tobacco Usage
16. Tobacco Usage: Have you used tobacco four (4) or more times per week in the last six (6) months? If you are eligible for the Healthy Indiana Plan (HIP) and you are a tobacco-user, you may have an increased POWER Account contribution in your second year of coverage.
17. Health Plan Selection
17. Health Plan Selection: Please answer this question if anyone is applying for health coverage. You do not have to make a selection at this time. If you have made your selection, please mark the box next to your chosen plan.
18. Hoosier Care Connect Health Plan Selection
18. Hoosier Care Connect Health Plan Selection: Please answer this question if anyone is applying for health coverage and is disabled, blind, or age sixty five (65) or older AND not receiving Medicare, Home and Community Based Services, or residing in a long term care facility.
19. Health coverage offered from a job
19. Is anyone listed on this application offered health coverage from a job? Select Yes even if the coverage is from someone else's job, such as a parent or spouse. If Yes, complete Section 32, Health Coverage from Jobs.
32. Health Coverage from Jobs: You DON'T need to answer these questions unless someone in the household is eligible for health coverage from a job.
Are you currently eligible for coverage offered by this employer, or will you become eligible in the next three (3) months? Yes (Continue). No (Stop here and go to Section 33 in the application).
20. Contact Information
20. Contact Information: Enter the E-mail address.
21. Other persons who live at the home address
21. Provide information for all other persons who live at the home address in Section 3 and all persons included on your tax return.
33. Completing the application on behalf of someone else
33. If you are completing this application on behalf of someone else, provide your contact information. If you are a representative for the person(s) needing assistance, the applicant must complete and sign the enclosed Authorized Representative form.
34. Do you want to register to vote
34. Do you want to register to vote? No or Yes. Your answer will not affect your eligibility for health coverage.
Sources
[1] Indiana Application for Health Coverage, State Form 55390 (R9 / 3-21), Indiana Family and Social Services Administration (the Official source link on this page).