Suboxone Wellcare PDF Details

Managing the treatment of opioid addiction requires careful coordination and adherence to specific medical guidelines. The Suboxone Wellcare form is a critical document in this process, designed to streamline the prescription process for Suboxanereg; and other forms of buprenorphine. This comprehensive form, required to be filled out by physicians with a Drug Addiction Treatment Act (DATA) waiver, gathers essential information about the patient, including their Member ID, name, phone number, diagnosis, and the prescribing physician’s details like DEA and NPI numbers. Physicians must indicate the specific medication and dosage requested, adhering to strict limits that prohibit doses above 32 mg per day. The form prompts for key details related to the patient's treatment history and current status, such as primary diagnosis, recent psychosocial counseling, compliance with treatment sessions, current alcohol use, opioid use within the last 30 days, and reasons for exceeding standard dosing limits, if applicable. It also requires information on planned psychosocial counseling and a urine drug screen. This document must be signed by the physician, certifying their waiver to prescribe these treatments, and submitted via fax to WellCare Pharmacy, signifying a controlled and monitored approach to opioid addiction treatment. By providing a structured format for requesting medication like Suboxone, this form plays a pivotal role in ensuring patients receive the appropriate, sanctioned care for their recovery journey.

QuestionAnswer
Form NameSuboxone Wellcare
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other nameswellmed prior authorization form, uhc wellmed prior authorization form, wellmed provider forms, wellcare frm prior form

How to Fill Out WellCare Suboxone Contact Form

WellCare Suboxone Contact Form at a glance

What it is: Contact Form completed, signed and submitted by a physician with a Drug Addiction Treatment Act (DATA) waiver for the Drug Requested.

Who signs: Sign on Physician Signature and fill in the Date.

What to bring and attach to WellCare Suboxone Contact Form

Must submit most current urine drug screen with this form.

A filled-in WellCare Suboxone Contact Form example: a physician requests Suboxone approval
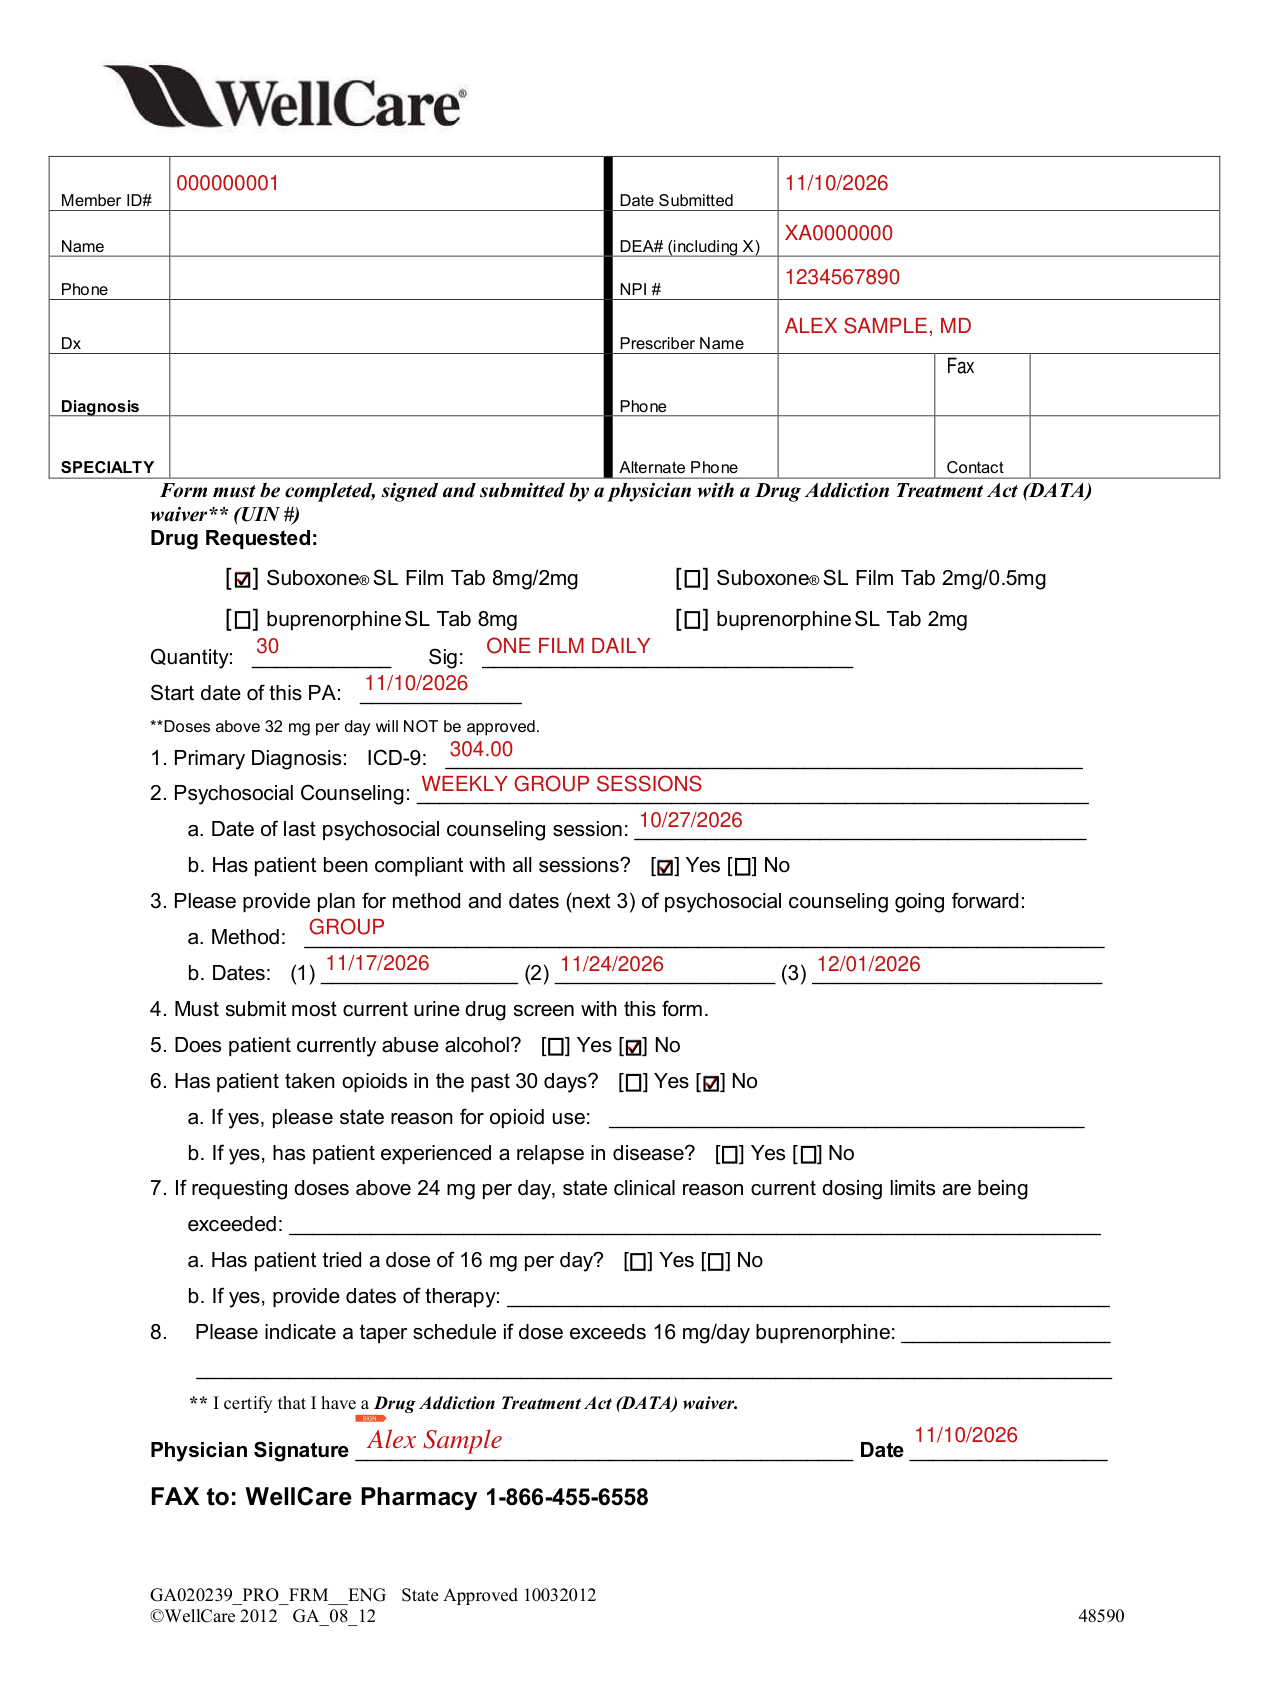
WellCare Suboxone Contact Form example filled out, example: a physician requests Suboxone approval
Dr. Alex Sample asks WellCare to approve Suboxone for a patient. The request is for Suboxone SL Film Tab 8mg/2mg, with no dose above 24 mg per day. The picture shows the filled form; all its values are invented. Nothing goes in Doses above 24 mg per day because no dose above 24 mg per day is requested. Taper schedule is left blank because the dose does not exceed 16 mg/day. The patient has taken no opioids in the past 30 days, so Opioids in the past 30 days has No ticked. The patient is compliant with all sessions and does not abuse alcohol.

How to fill out WellCare Suboxone Contact Form, box by box

Member and prescriber
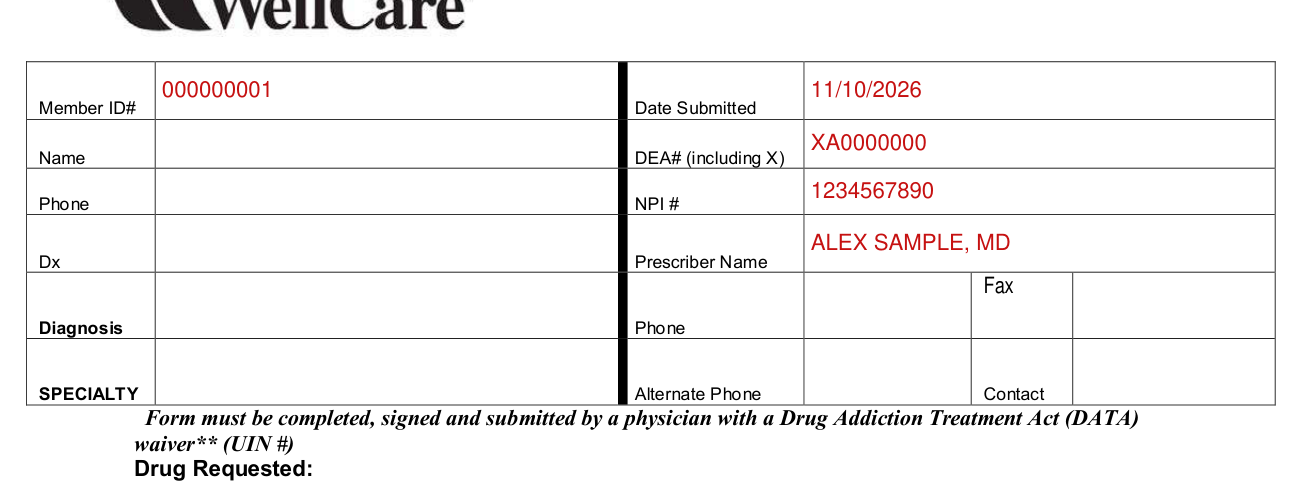
WellCare Suboxone Contact Form example filled out, member and prescriber

Fill in Member ID# and Date Submitted.

Fill in Name, DEA# (including X), Phone, NPI # and Prescriber Name.

Drug Requested

WellCare Suboxone Contact Form example filled out, drug Requested

Under Drug Requested, mark Suboxone SL Film Tab 8mg/2mg, Suboxone SL Film Tab 2mg/0.5mg, buprenorphine SL Tab 8mg or buprenorphine SL Tab 2mg.

Fill in Quantity, Sig and Start date of this PA.

"Doses above 32 mg per day will NOT be approved." (Contact Form**)

Primary Diagnosis

WellCare Suboxone Contact Form example filled out, primary Diagnosis

In box 1, Primary Diagnosis, enter the ICD-9.

Psychosocial Counseling

WellCare Suboxone Contact Form example filled out, psychosocial Counseling

In box 2, Psychosocial Counseling, fill in the date of last psychosocial counseling session and mark Yes or No for: has patient been compliant with all sessions?.

Plan for psychosocial counseling going forward

WellCare Suboxone Contact Form example filled out, plan for psychosocial counseling going forward

In box 3, provide the plan for method and dates (next 3) of psychosocial counseling going forward: Method, then Dates (1), (2) and 3).

Does patient currently abuse alcohol

WellCare Suboxone Contact Form example filled out, does patient currently abuse alcohol

In box 5, mark Yes or No for: does patient currently abuse alcohol?

Opioids in the past 30 days

WellCare Suboxone Contact Form example filled out, opioids in the past 30 days

In box 6, mark Yes or No for: has patient taken opioids in the past 30 days? If yes, please state reason for opioid use and mark Yes or No for: has patient experienced a relapse in disease?

Doses above 24 mg per day

WellCare Suboxone Contact Form example filled out, doses above 24 mg per day

In box 7, if requesting doses above 24 mg per day, state the clinical reason current dosing limits are being exceeded and mark Yes or No for: has patient tried a dose of 16 mg per day? If yes, provide dates of therapy.

Taper schedule

WellCare Suboxone Contact Form example filled out, taper schedule

In box 8, indicate a taper schedule if the dose exceeds 16 mg/day buprenorphine.

Signing as the physician

WellCare Suboxone Contact Form example filled out, signing as the physician

By signing you certify that you have a Drug Addiction Treatment Act (DATA) waiver** (Contact Form).

Sign on Physician Signature and fill in the Date.

Common questions about WellCare Suboxone Contact Form

Where do I file it?

FAX to: WellCare Pharmacy 1-866-455-6558.

Sources

[1] WellCare Pharmacy prior authorization form for Suboxone SL Film and buprenorphine SL tablets (GA020239_PRO_FRM__ENG) (the Official source link on this page).

Please rate Suboxone Wellcare

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .