


Supervision Data Form (DH-MQA 2004) at a glance
What it is: The Supervision Data Form must be updated by the physician assistant as a condition of practice.
Who signs: Sign on the Signature of Physician Assistant line and enter the Date of signature.
The Supervision Data Form must be updated by the physician assistant as a condition of practice.
A filled-in Supervision Data Form (DH-MQA 2004) example: a physician assistant reports four practice locations

How to fill out Supervision Data Form (DH-MQA 2004), box by box
Name, license number, mailing address and all current practice locations
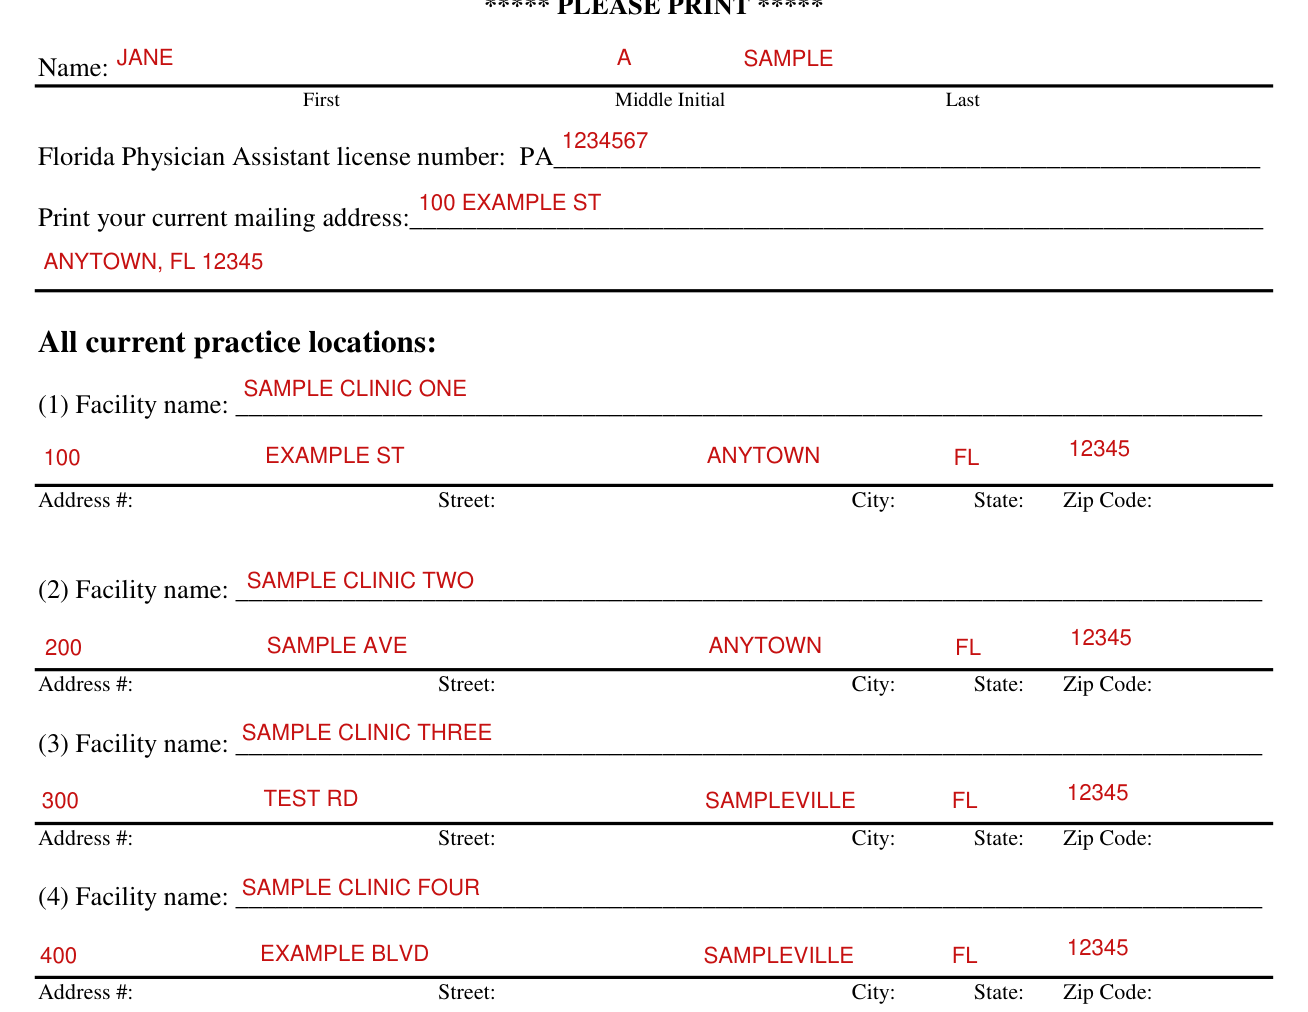
Under PLEASE PRINT, enter your Name (First, Middle Initial, Last), your Florida Physician Assistant license number (PA) and your current mailing address. List all current practice locations: for each of (1) to (4), enter the Facility name, Address #, Street, City, State and Zip Code. Make additional copies of page 1 as needed. Return all 5 pages. This Supervision Data Form will not be processed without the Physician Assistant's signature and date.
I am ADDING the following supervising physician(s)
Under I am ADDING the following supervising physician(s), enter the Name and license number of each supervising physician (ME or DO license number), the Specialty of supervising physician and the Beginning date of Supervision.
Make additional copies of page 2 as needed.
I am DELETING the following supervising physician(s)

Under I am DELETING the following supervising physician(s), enter the Name and license number of each supervising physician (ME or DO license number) and the Effective date of deletion.
Make additional copies of page 3 as needed.
I am ADDING the following practice location(s)

Enter the Facility name, Address #, Street, City, State and Zip Code for each of (1) to (8) under I am ADDING the following practice location(s).
Make additional copies of page 4 as needed.
I am DELETING the following practice location(s)
Enter the Facility name, Address #, Street, City, State and Zip Code for each of (1) to (6) practice location(s) you are DELETING.
Common questions about Supervision Data Form (DH-MQA 2004)
Who signs it?
Sign on the Signature of Physician Assistant line and enter the Date of signature.
Is there a deadline?
Upon employment, a licensed physician assistant must notify the department in writing within 30 days after such employment and after any subsequent changes in supervision.
Where do I file it?
Notify the department in writing at the Council on Physician Assistants, 4052 Bald Cypress Way, Bin #C-03, Tallahassee, Florida 32399-3253.
Sources
[1] Supervision Data Form (DH-MQA 2004, Revised 08/10) (the Official source link on this page).