

Form LHL234 at a glance
What it is: LHL234 01/07 is the Texas Standardized Credentialing Application.
Where and when to file: Pursuant to Texas Insurance Code § 1452.052, LHL234 Rev. 01/07 is promulgated by the Texas Department of Insurance. Please send this application to the carrier with whom you wish to become credentialed.
What to bring and attach to Form LHL234
Please attach hard copy or scanned documents: Copy of DEA or state DPS Controlled Substances Registration Certificate Copy of other Controlled Dangerous Substances Registration Certificate(s) Copy of current professional liability insurance policy face sheet, showing expiration dates, limits and applicant's name Copies of IRS W-9s for verification of each tax identification number used Copy of workers compensation certificate of coverage, if applicable Copy of CLIA certifications, if applicable Copies of radiology certifications, if applicable Copy of DD214, record of military service, if applicable
A filled-in Form LHL234 example: a physician completes page 1
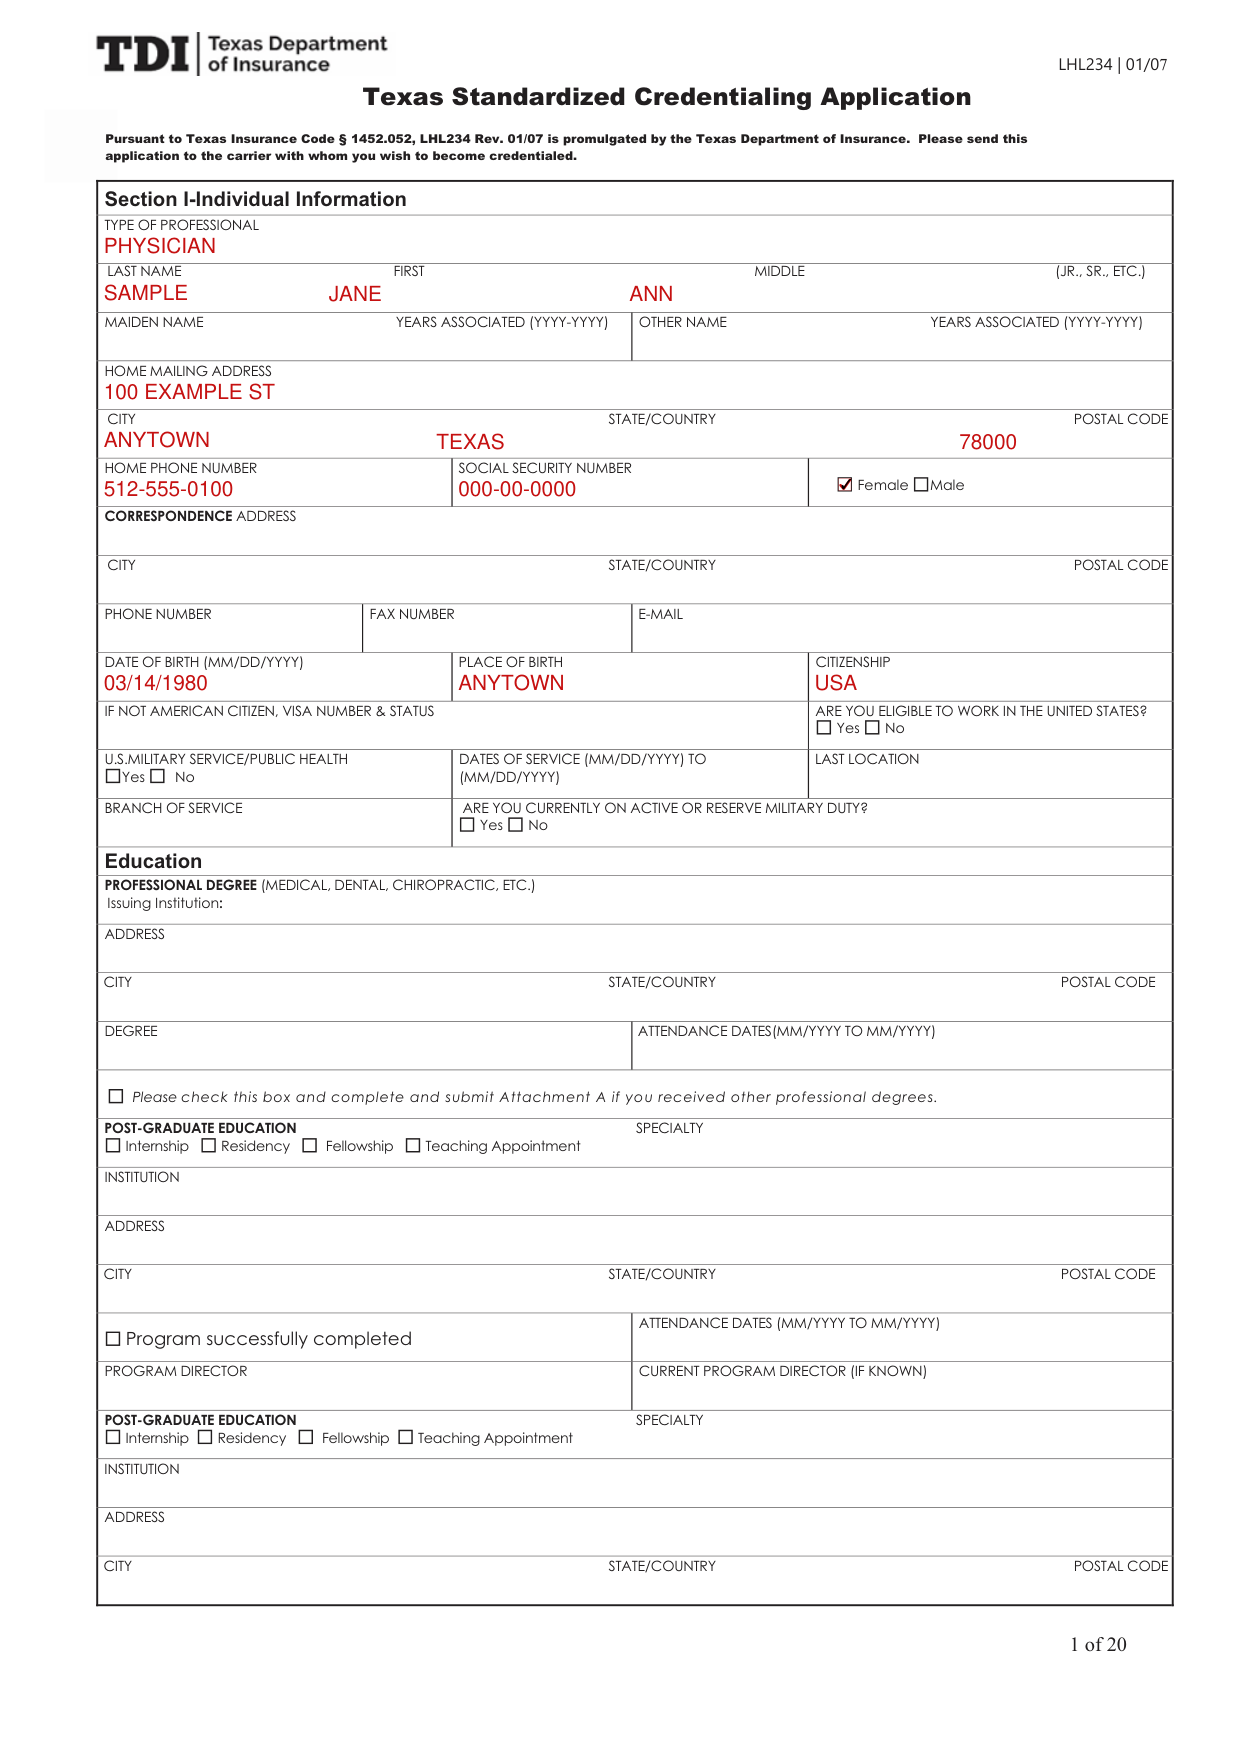
How to fill out Form LHL234, box by box
TYPE OF PROFESSIONAL and name
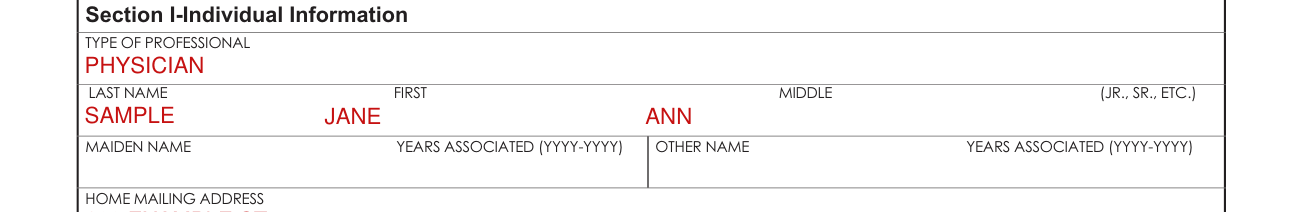
Enter TYPE OF PROFESSIONAL.
Enter LAST NAME, FIRST and MIDDLE (JR., SR., ETC.).
HOME MAILING ADDRESS, phone and sex
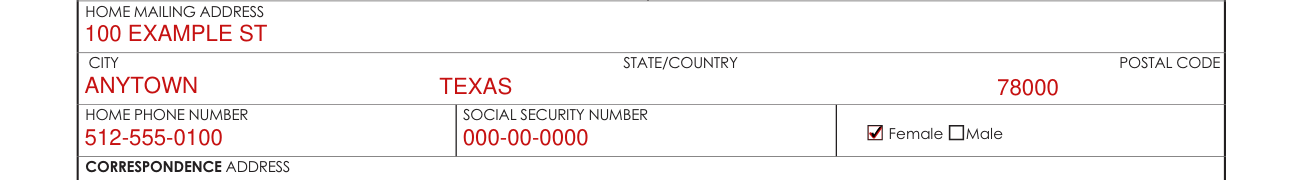
Enter HOME MAILING ADDRESS, CITY, STATE/COUNTRY and POSTAL CODE.
Enter HOME PHONE NUMBER and SOCIAL SECURITY NUMBER.
Mark Female or Male.
DATE OF BIRTH, PLACE OF BIRTH and CITIZENSHIP

Enter DATE OF BIRTH (MM/DD/YYYY), PLACE OF BIRTH and CITIZENSHIP.
More rules for Form LHL234
Any material misstatement or omission in the application may constitute grounds for withdrawal of the application from consideration; denial or revocation of Participation; and/or immediate suspension or termination of Participation.
Licenses and Certificates - Please include all license(s) and certifications in all States where you are currently or have previously been licensed.
Work History - Please provide a chronological work history. You may submit a Curriculum Vitae as a supplement. Please explain all gaps in employment that lasted more than six months.
Hospital Affiliations-Please include all hospitals where you currently have or have previously had privileges.
References-Please provide three peer references from the same field and/or specialty who are not partners in your own group practice and are not relatives. All peer references should have firsthand knowledge of your abilities.
Practice Location Information - Please answer the following questions for each practice location.
Corrections to the application are permitted at any time prior to a determination of Participation by the Entity, and must be submitted on-line or in writing, and must be dated and signed by me (may be a written or an electronic signature).
A facsimile or photocopy of this Authorization, Attestation and Release shall be as effective as the original.
Reproduction of this form without any changes is allowed.
If your situation is different
You received other professional degrees or additional postgraduate training, or have additional work history, hospital affiliations or other practice locations
Please check this box and complete and submit Attachment A if you received other professional degrees. Attachment B if you received additional postgraduate training. Attachment C if you have additional work history. Attachment D if you have additional current hospital affiliations. Attachment E if you have additional previous hospital affiliations. Attachment F if you have other practice locations.
Yes answers to any question except #16
Please use the space on page 10 to explain yes answers to any question except #16.
Malpractice Claims History 16: if yes
Malpractice Claims History 16: Have you had any malpractice actions within the past 5 years (pending, settled, arbitrated, mediated or litigated)?
If yes, please check this box and complete and submit Attachment G.
Common questions about Form LHL234
Who signs it?
Enter SIGNATURE, NAME (PLEASE PRINT OR TYPE), Last 4 digits of SSN or NPI (PLEASE PRINT OR TYPE) and DATE (MM/DD/YYYY).
Is there a deadline?
By signing you certify that all information provided in your application is true, correct, and complete to the best of your knowledge and belief, and that you will notify the Entity and/or its Agent(s) within 10 days of any material changes to the information you have provided in your application or authorized to be released pursuant to the credentialing process.
When is this form not the right one?
I understand that my application for Participation with the Entity is not an application for employment with the Entity and that acceptance of my application by the Entity will not result in my employment by the Entity.
Sources
[1] Form LHL234 (Rev. 01/07), Texas Standardized Credentialing Application, Texas Department of Insurance (the Official source link on this page).
