
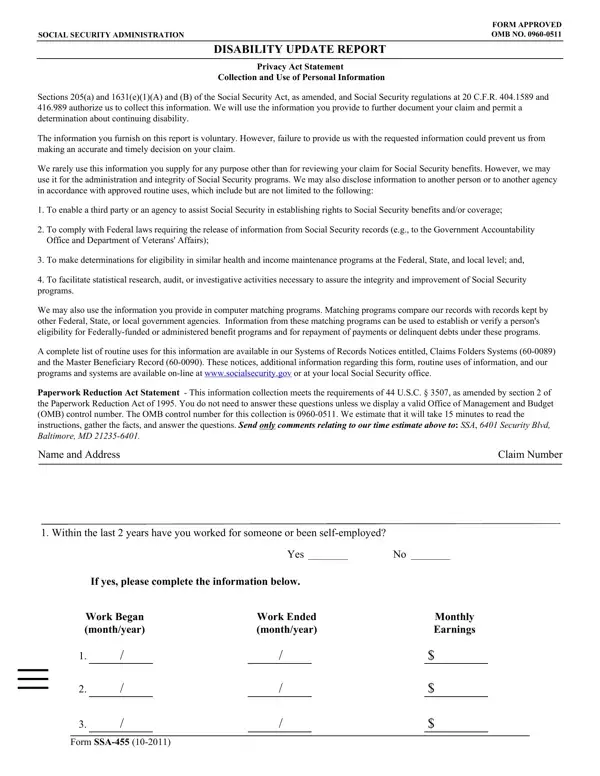
Within the last 2 years have you attended any school or work training program(s)?
Doctor or clinic: within the last 2 years have you gone to a doctor or clinic for your condition? If yes, show the date and the reason for the visit.
Hospital: if you have been hospitalized or had any surgery within the last 2 years, please list below Reason and Date (month/year).
Work: Work Began (month/year), Work Ended (month/year), Monthly Earnings.
Date report completed: Telephone Number, Date Report Completed (MM/DD/YYYY).
| Question | Answer |
|---|---|
| Form Name | Form SSA-455 |
| Form Length | 2 pages |
| Fillable? | Yes |
| Fillable fields | 52 |
| Avg. time to fill out | 9 min |
| Edition | 07-2023 |
| OMB control number | 0960-0511 |
| Other names | SSA-455, Form SSA-455, OMB 0960-0511, Disability Update Report |
| Official source | Form SSA-455 (07-2023), Social Security Administration |
Title 2 Omb No 0960 0511 Form isn’t the one you’re looking for?