

UCLA Form 30910 at a glance
What it is: Authorization for Release of Health Information, in which you authorize UCLA Health to release PHI.
Who signs: Sign on the line marked Signature of Patient / Legal Representative.
A filled-in UCLA Form 30910 example: a patient sends records to a clinic

How to fill out UCLA Form 30910, box by box
Patient Information
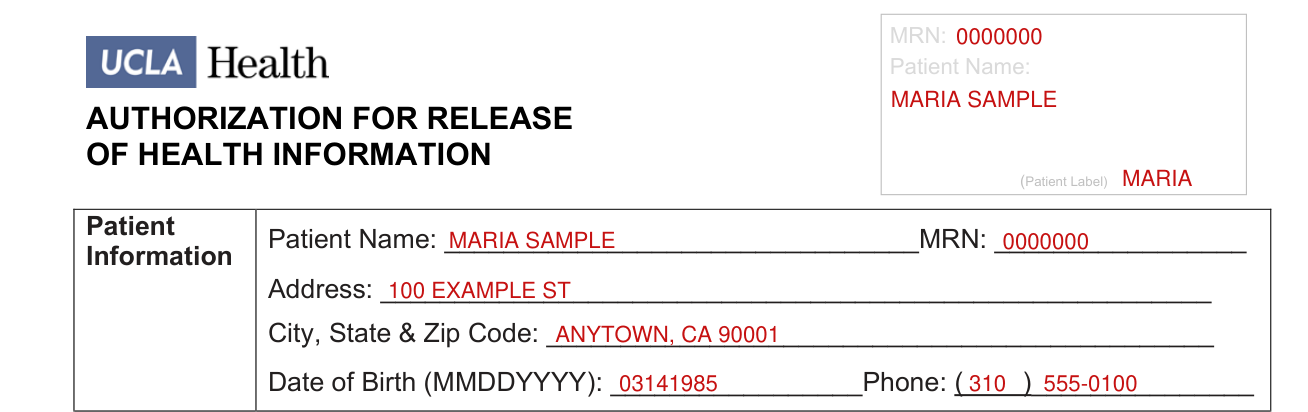
Under Patient Information, enter the Patient Name, MRN, Address, City, State & Zip Code, Date of Birth (MMDDYYYY) and Phone.
Specify Healthcare Facility

Under Specify Healthcare Facility, mark UCLA Health Hospitals/Clinics, Jules Stein Eye Institute or Resnick Neuropsychiatric Hospital.
Release Records to

Under I authorize UCLA Health to release PHI to, enter the Name of Hospital/Clinic/Person, Address, City, State & Zip Code, Phone, FAX and E-Mail Address.
Designee to pick up your records

If you would like a designee to pick up your records, fill out the Who do you want to receive records? section: I authorize the line to pick up my medical record copies, with the Relationship to patient.
Delivery Instructions

Under Delivery Instructions (please select one), select CD, E-Mail (NPH/BHS does not release via email), Paper Copy or Call Requestor when records are ready for pick up. If you would like a designee*: Designee must provide valid photo ID.
If left blank, a CD will be provided.
Purpose

Under Purpose, mark At the request of the patient/patient representative, or Other (state reason).
Type of Records
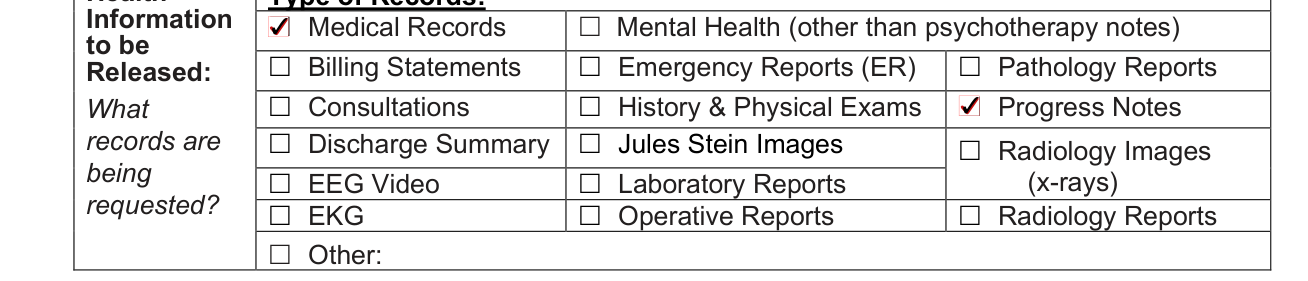
Under Health Information to be Released, mark the Type of Records: Medical Records, Mental Health (other than psychotherapy notes), Billing Statements, Emergency Reports (ER), Pathology Reports, Consultations, History & Physical Exams, Progress Notes, Discharge Summary, Jules Stein Images, Radiology Images (x-rays), EEG Video, Laboratory Reports, EKG, Operative Reports, Radiology Reports or Other.
Sensitive Information

Sensitive information will not be released unless specifically authorized: Drug and Alcohol Abuse Results, HIV/AIDS Test Results, Genetic Testing Information or Psychological/Vocational Results.
Date or time period and expiration

Under Expiration of Authorization, unless otherwise revoked, this Authorization expires on the applicable date or event you insert.
If no date is indicated this Authorization will expire 12 months after the date signed.
Specify the date or time period for the information selected under Sensitive Information: FROM MM / DD / YYYY TO MM / DD / YYYY.
Signature of Patient or Legal Representative

Sign as the Signature of Patient / Legal Representative with the Date, then enter the Printed Name and Area Code/Phone Number.
If signed by someone other than the patient, indicate relationship to the patient.
Signature of Witness or Interpreter

Signature of Witness (only if patient unable to sign), with Date or Interpreter | Interpreter ID #.
Mailing Addresses

Mailing Addresses, Please check box for medical records: UCLA HIMS, Release of Information, 10833 Le Conte Ave, CHS BH-902, Los Angeles, CA. 90095-1776, Fax: (310) 983-1468, Phone: (310) 825-6021, Email: roi@mednet.ucla.edu.
Please check box for radiology images: Image Management, Release of Information, 200 Medical Plaza B1- Level, Suite 165-11, Los Angeles Ca. 90095, Fax 310-825-3205, Phone 310-825-6425.
Please check box for mental health records: Mental Health Records, RNPH/BHS HIMS, 10833 Le Conte Ave BH239A, Los Angeles CA 90095, Fax 310-206-7682, Phone 310-267-2661 or 310-794-1530.
More rules for UCLA Form 30910
All sections of this authorization must be completely filled out before UCLA Health is permitted to disclose your protected health information.
If you have authorized the disclosure of your health information to someone who is not legally required to keep it confidential, it may no longer be protected by state or federal confidentiality laws.
If your situation is different
Walk-in Service
Release of Information Customer Service - Walk-in Service, Open Hours: 8a-4:30pm, Closed Lunch 11:30a-12:30p.
Ronald Reagan UCLA: 100 Med Plaza, Suite 140, Los Angeles, CA 90095. Santa Monica UCLA: 1260 - 15th Street, Suite 802B, Santa Monica, CA 90404.
Your rights
This authorization is voluntary. Treatment, payment enrollment or eligibility for benefits may not be conditioned on signing this authorization except if the authorization is for: 1) conducting research-related treatment, 2) obtaining information in connection with eligibility or enrollment in a health plan, 3) determining an entity's obligation to pay a claim, or 4) creating PHI to provide to a third party. You are entitled to receive a copy of this Authorization.
Sources
[1] Authorization for Release of Health Information, UCLA Form #30910 (Rev 12/19), UCLA Health (the Official source link on this page).