


Nevada Universal Prior Authorization Form at a glance
What it is: Nevada Universal Prior Authorization Form.
Who signs: Sign as the Requesting Provider, with a Signature or Stamped Signature.
The blank Nevada Universal Prior Authorization Form: print it and complete it by hand
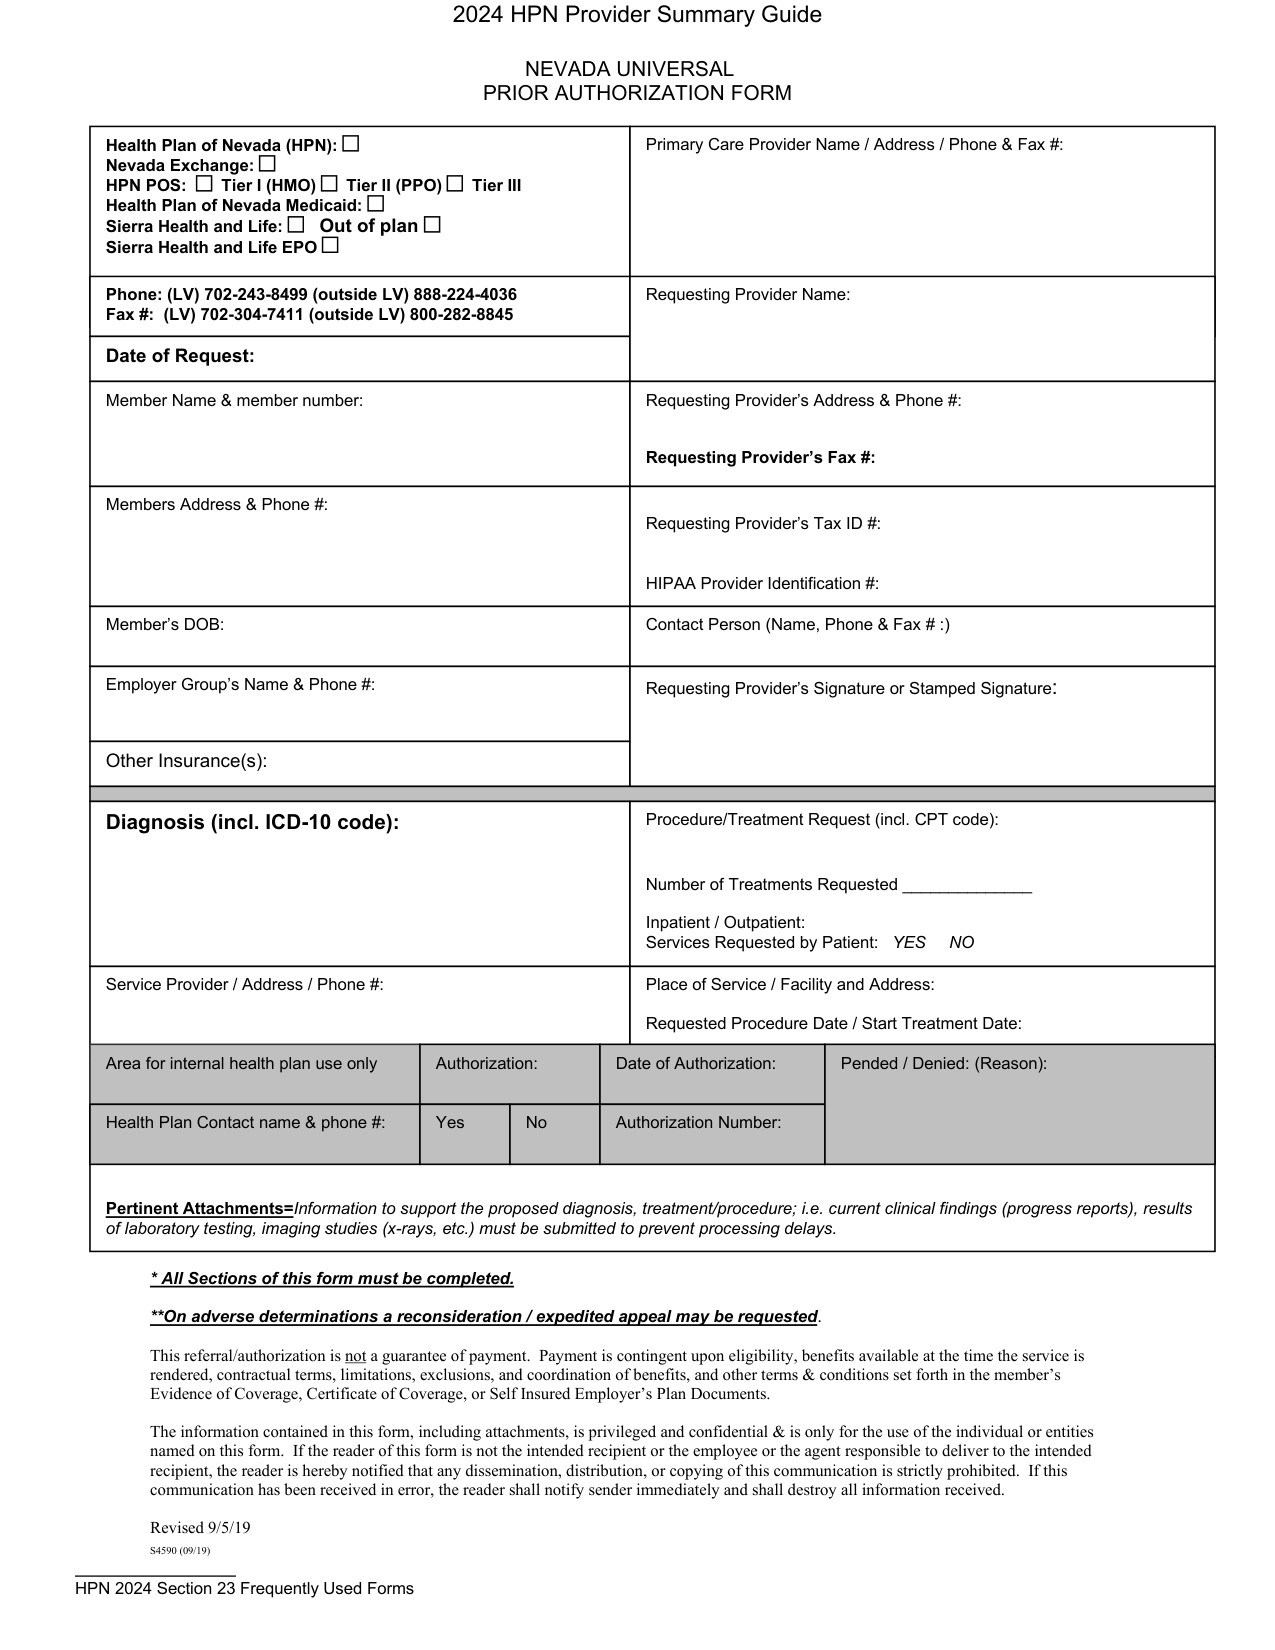
How to fill out Nevada Universal Prior Authorization Form, box by box
Health Plan of Nevada (HPN) plan
The form prints: Health Plan of Nevada (HPN), Nevada Exchange, HPN POS, Tier I (HMO), Tier II (PPO), Tier III, Health Plan of Nevada Medicaid, Sierra Health and Life, Out of plan, Sierra Health and Life EPO.
Primary Care Provider Name
Write the Primary Care Provider Name / Address / Phone & Fax #.
Write the Date of Request.
Write the Member's DOB.
Write the Employer Group's Name & Phone #.
Write the Other Insurance(s).
Requesting Provider Name
Write the Requesting Provider Name.
Write the Member Name & member number, the Requesting Provider's Address & Phone #, and the Requesting Provider's Fax #.
Write the Members Address & Phone #, the Requesting Provider's Tax ID #, and the HIPAA Provider Identification #.
Requesting Provider's Signature or Stamped Signature
Sign as the Requesting Provider, with a Signature or Stamped Signature.
Diagnosis (incl. ICD-10 code)
Write the Diagnosis (incl. ICD-10 code).
Service Provider and Place of Service
Write the Service Provider / Address / Phone #.
Write the Place of Service / Facility and Address and the Requested Procedure Date / Start Treatment Date.
Procedure/Treatment Request (incl. CPT code)
Write the Procedure/Treatment Request (incl. CPT code) and the Number of Treatments Requested; write Inpatient / Outpatient, and YES or NO for Services Requested by Patient.
Current clinical findings and management
All procedures/treatment requested require clinical information; you may use the space, and attach it to this form. Pertinent Attachments, information to support the proposed diagnosis, treatment/procedure (current clinical findings (progress reports), results of laboratory testing, imaging studies (x-rays, etc.)), must be submitted to prevent processing delays.
Area for internal health plan use only
Leave the Area for internal health plan use only blank.
More rules for Nevada Universal Prior Authorization Form
All sections of this form must be completed.
Where to get help with Nevada Universal Prior Authorization Form
The form prints Phone: (LV) 702-243-8499, (outside LV) 888-224-4036. Fax #: (LV) 702-304-7411, (outside LV) 800-282-8845.
Sources
[1] Nevada Universal Prior Authorization Form (09/19), Health Plan of Nevada (the Official source link on this page).