

VA Form 10-7959c at a glance
What it is: VA Form 10-7959c, the CHAMPVA OTHER HEALTH INSURANCE (OHI) CERTIFICATION: use this form to report any changes in your other health insurance.
Who signs: The beneficiary, sponsor or legal guardian signs on SIGNATURE (type if electronic) and enters the DATE (MM/DD/YYYY). Federal laws (18 USC 287 and 1001) provide for criminal penalties for knowingly submitting or making false statements. If there is any change in insurance status for the person, you agree to promptly notify the Chief Business Office Purchased Care.
A filled-in VA Form 10-7959c example: a beneficiary reports one employer plan
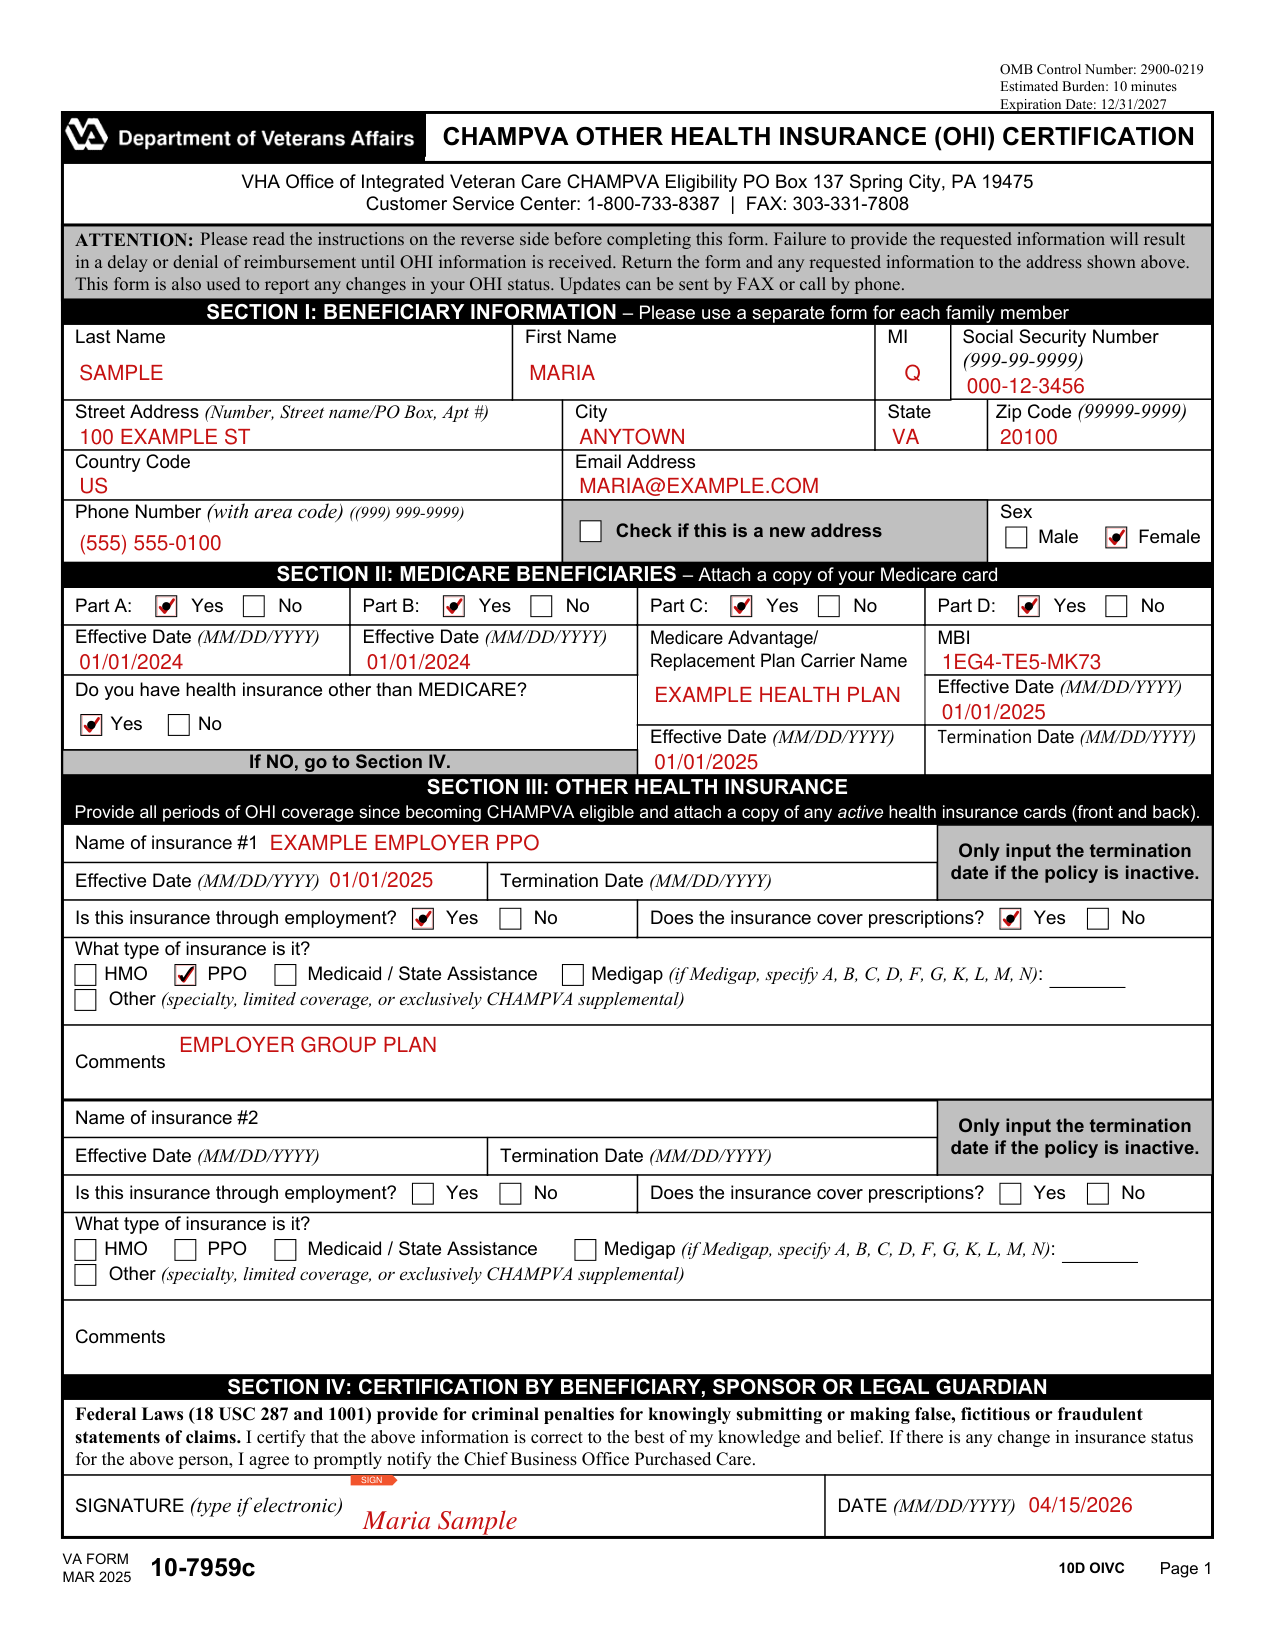
How to fill out VA Form 10-7959c, box by box
Section I: Beneficiary Information
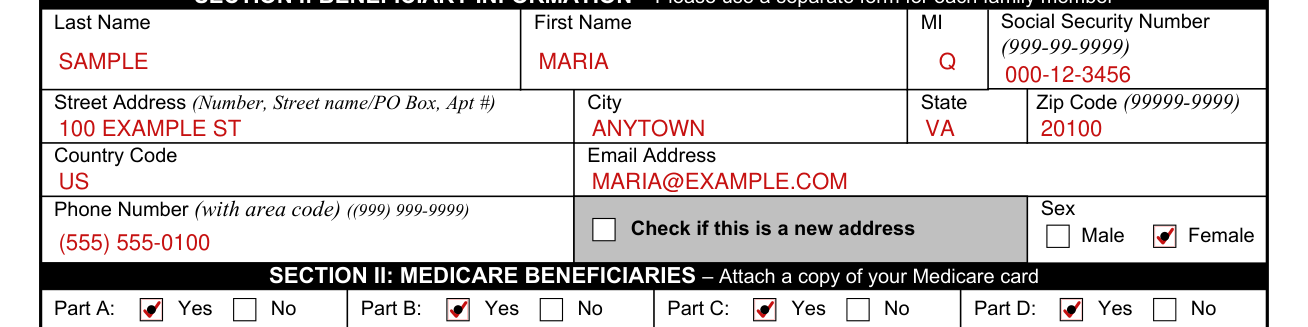
Under SECTION I: BENEFICIARY INFORMATION, use a separate form for each family member and enter the Last Name, First Name, MI and Social Security Number (999-99-9999).
Enter the Street Address (Number, Street name/PO Box, Apt #), City, State, Zip Code (99999-9999), Country Code, Email Address and Phone Number (with area code) ((999) 999-9999).
Check if this is a new address. Sex: Male or Female.
Section II: Medicare Beneficiaries
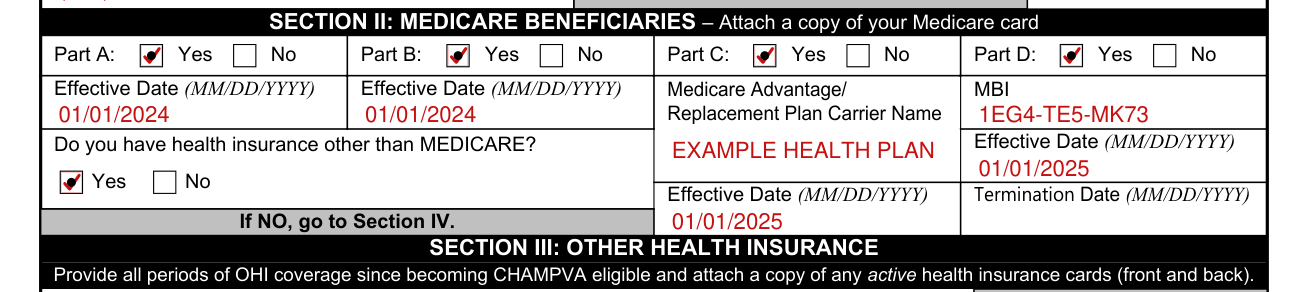
SECTION II: MEDICARE BENEFICIARIES: attach a copy of your Medicare card. Send a COPY of your Medicare card (do NOT send the original).
Part A: Yes or No. Part B: Yes or No. Part C: Yes or No. Part D: Yes or No.
Enter the Effective Date (MM/DD/YYYY) for Part A, Part B, Part C and Part D, the Medicare Advantage/ Replacement Plan Carrier Name, the MBI and, for Part D, the Termination Date (MM/DD/YYYY).
Section III: Other Health Insurance
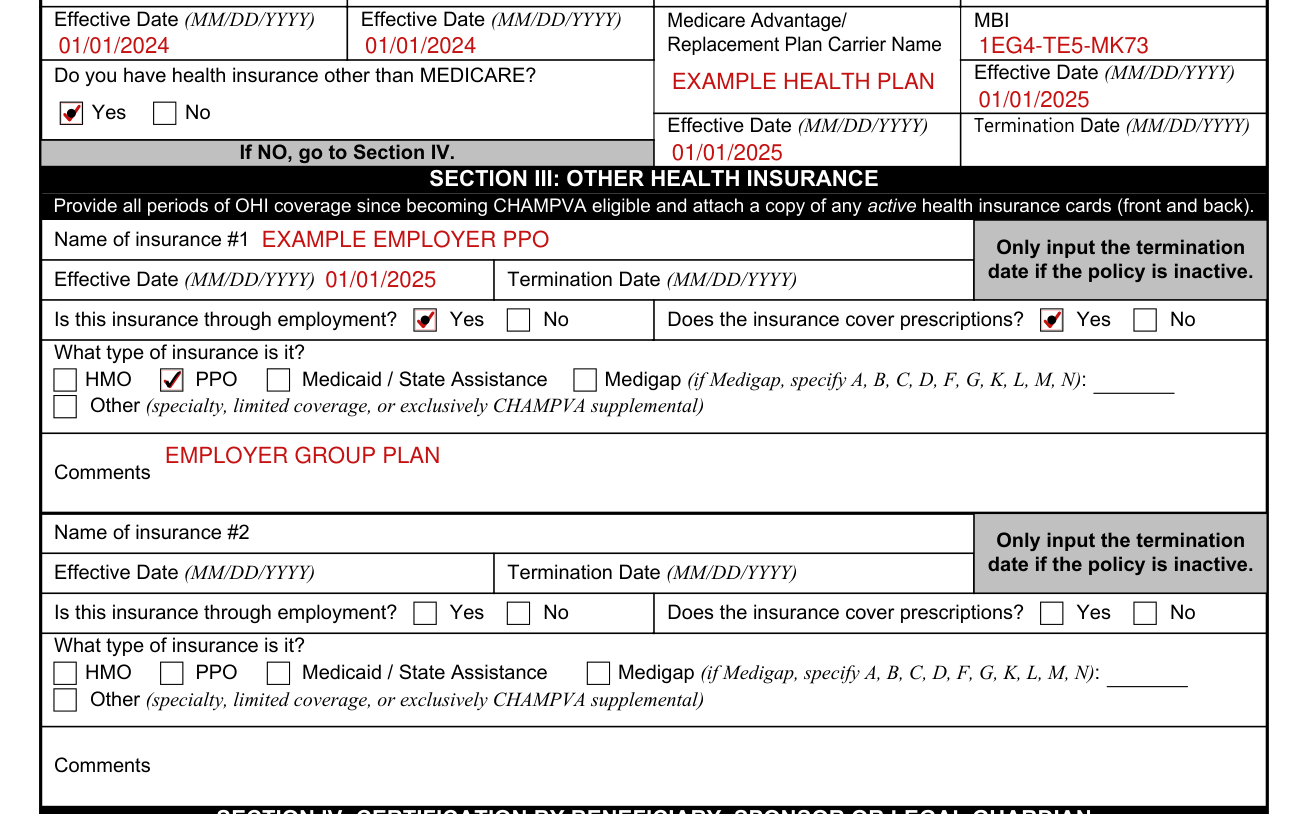
Do you have health insurance other than MEDICARE? Yes or No. If NO, go to Section IV.
SECTION III: OTHER HEALTH INSURANCE: Provide all periods of OHI coverage since becoming CHAMPVA eligible and attach a copy of any active health insurance cards (front and back). Attach A COPY of your other health insurance (OHI) member ID card (front and back).
Enter the Name of insurance #1 and Name of insurance #2, each with its Effective Date (MM/DD/YYYY) and Termination Date (MM/DD/YYYY). Only input the termination date if the policy is inactive.
Is this insurance through employment? Yes or No. Does the insurance cover prescriptions? Yes or No.
What type of insurance is it? HMO, PPO, Medicaid / State Assistance, Medigap (if Medigap, specify A, B, C, D, F, G, K, L, M, N) or Other (specialty, limited coverage, or exclusively CHAMPVA supplemental). To specify a Medicare supplement plan A, B, C, D, F, G, K, L, M, N, refer to your policy cover sheet or your insurance membership card. Add Comments.
If there are additional policies use plain bond paper and either type or legibly print your name, SSN, and the information for each item.
Section IV: Certification by Beneficiary, Sponsor or Legal Guardian

SECTION IV: CERTIFICATION BY BENEFICIARY, SPONSOR OR LEGAL GUARDIAN Federal Laws (18 USC 287 and 1001) provide for criminal penalties for knowingly submitting or making false, fictitious or fraudulent statements of claims. "I certify that the above information is correct to the best of my knowledge and belief. If there is any change in insurance status for the above person, I agree to promptly notify the Chief Business Office Purchased Care."
More rules for VA Form 10-7959c
Failure to complete all applicable sections on the front can result in a delay or denial of benefits.
Termination date: This is the date the policy ended or ceased to be active. The end date for a period shown on a card that will be reissued is not the termination date. Closing a policy will generate a true termination date.
Note: If you have OHI primary to CHAMPVA you must submit EOB's for each primary insurance along with health care claims. If your OHI does not issue EOB's i.e. some HMO's and PPO's, you must submit a copy of your active co-payment information shown on your insurance card or a document showing your co-payments with every health care claim so CHAMPVA can calculate benefit payments.
New beneficiaries and re-certification
New beneficiaries
New beneficiaries - CHAMPVA needs OHI information from the date your CHAMPVA eligibility became effective.
Re-certification
Re-certification - update OHI information every time a change is made to your OHI coverage.
Common questions about VA Form 10-7959c
Where do I file it?
Return the form and any requested information to VHA Office of Integrated Veteran Care CHAMPVA Eligibility PO Box 137 Spring City, PA 19475. Updates can be sent by FAX: 303-331-7808 or call by phone: Customer Service Center: 1-800-733-8387. Failure to provide the requested information will result in a delay or denial of reimbursement until OHI information is received.
Sources
[1] VA Form 10-7959c (MAR 2025), CHAMPVA Other Health Insurance (OHI) Certification, Department of Veterans Affairs (the Official source link on this page).
