

VA Form 21-22a at a glance
What it is: VA Form 21-22a is the Appointment of Individual as Claimant's Representative.
Who signs: Enter the Signature of Veteran/Claimant (Required) in 23A and the Date Signed (MM/DD/YYYY) in 23B. Enter the Signature of Representative (Required) in 25A and the Date Signed (MM/DD/YYYY) in 25B.
A filled-in VA Form 21-22a example: a veteran appoints an attorney
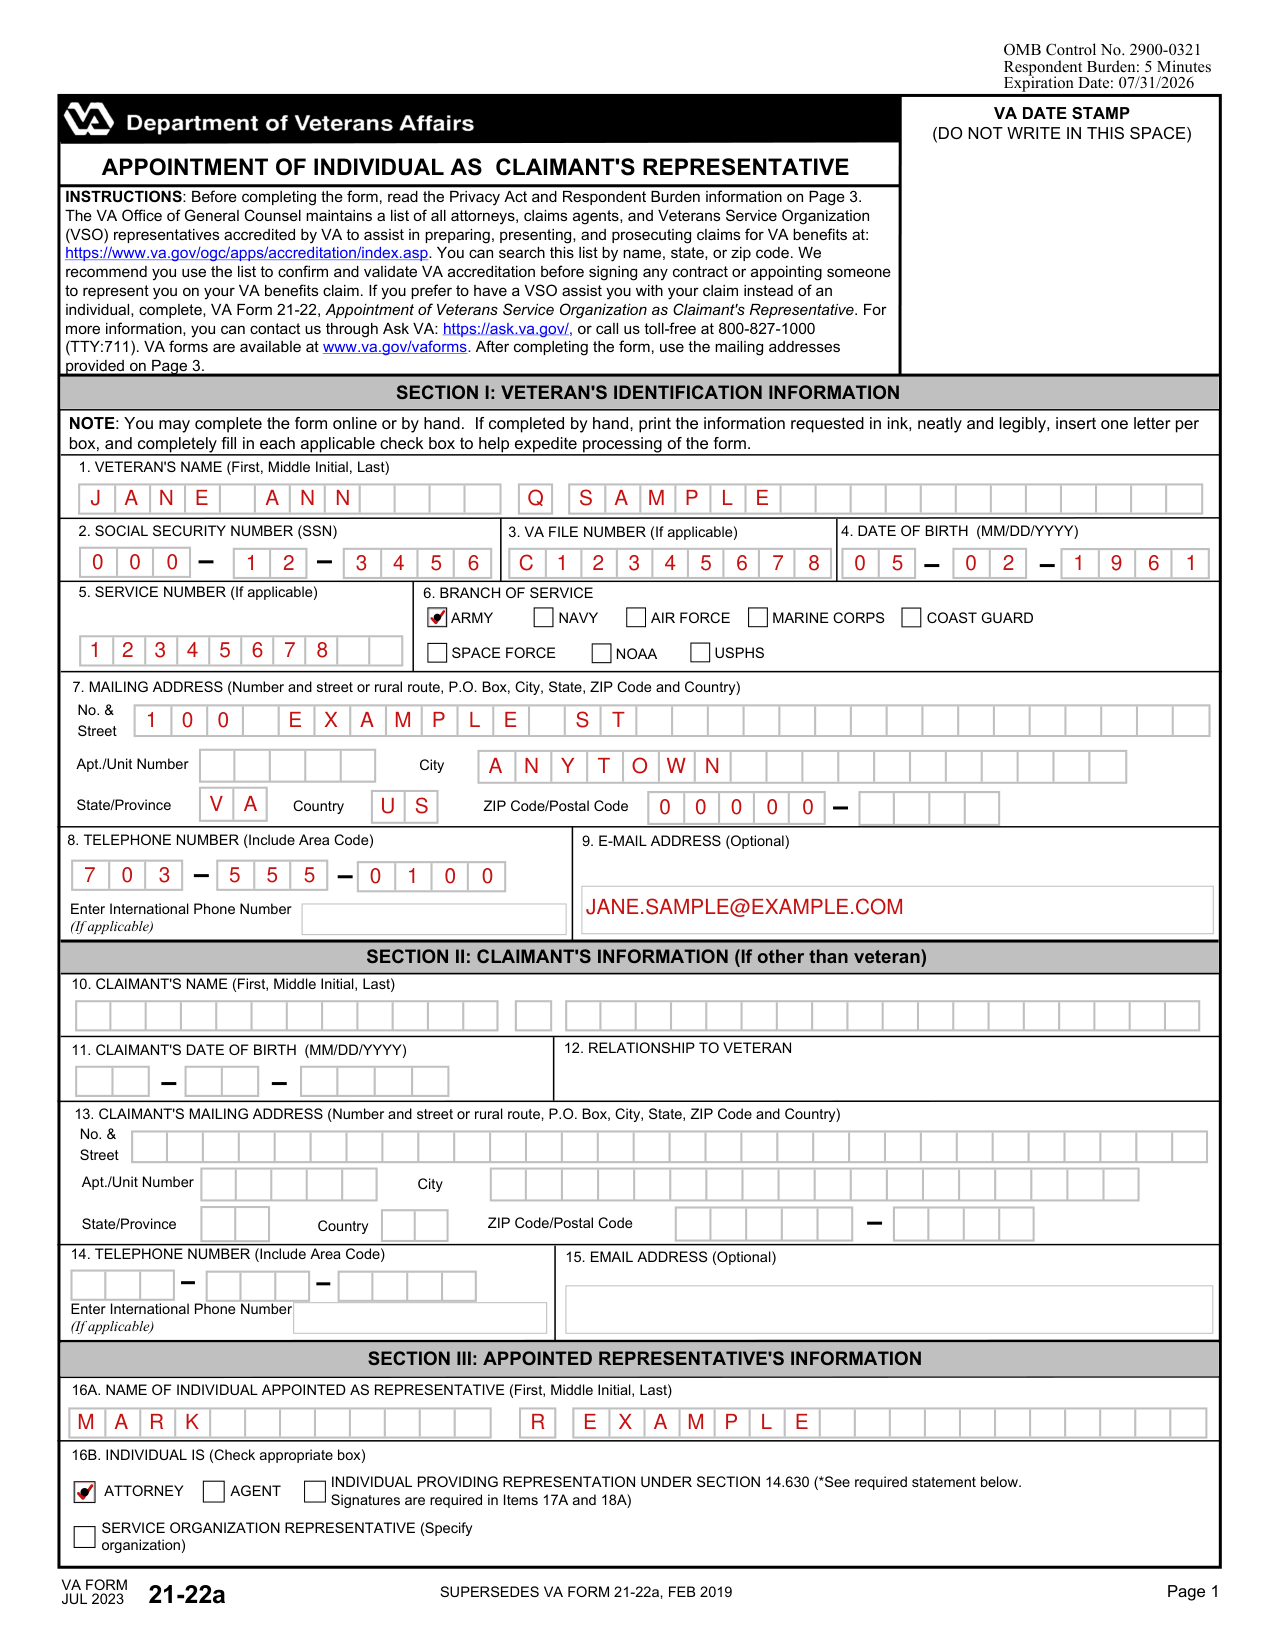
How to fill out VA Form 21-22a, box by box
Section I, veteran's identification information
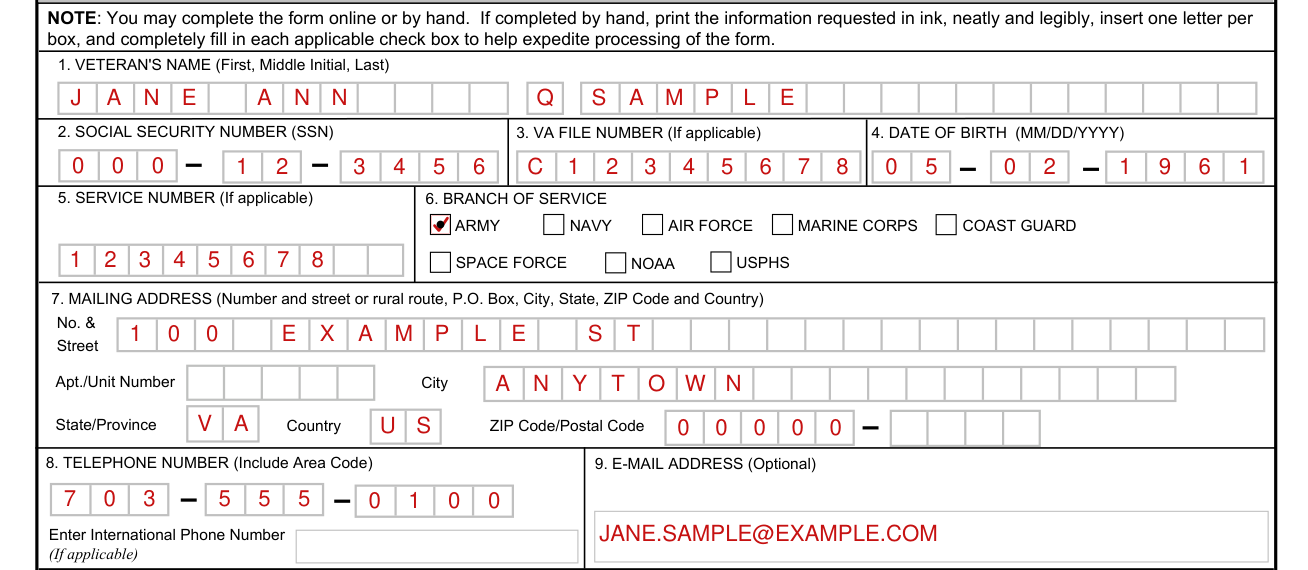
You may complete the form online or by hand. If completed by hand, print the information requested in ink, neatly and legibly, insert one letter per box, and completely fill in each applicable check box to help expedite processing of the form.
In Section I, Veteran's Identification Information, enter the Veteran's Name (First, Middle Initial, Last) in box 1.
Enter the Social Security Number (SSN) in box 2, the Date of Birth (MM/DD/YYYY) in box 4 and the VA File Number (If applicable) in box 3.
Enter the Service Number (If applicable) in box 5.
In box 6, Branch of Service: Army, Navy, Air Force, Marine Corps, Coast Guard, Space Force, NOAA, USPHS.
In box 7, enter the Mailing Address (Number and street or rural route, P.O. Box, City, State, ZIP Code and Country): No. & Street, Apt./Unit Number, City, ZIP Code/Postal Code, State/Province and Country.
Enter the Telephone Number (Include Area Code) in box 8, and the International Phone Number (If applicable).
The E-mail Address in box 9 is optional.
Section II, claimant's information (if other than veteran)
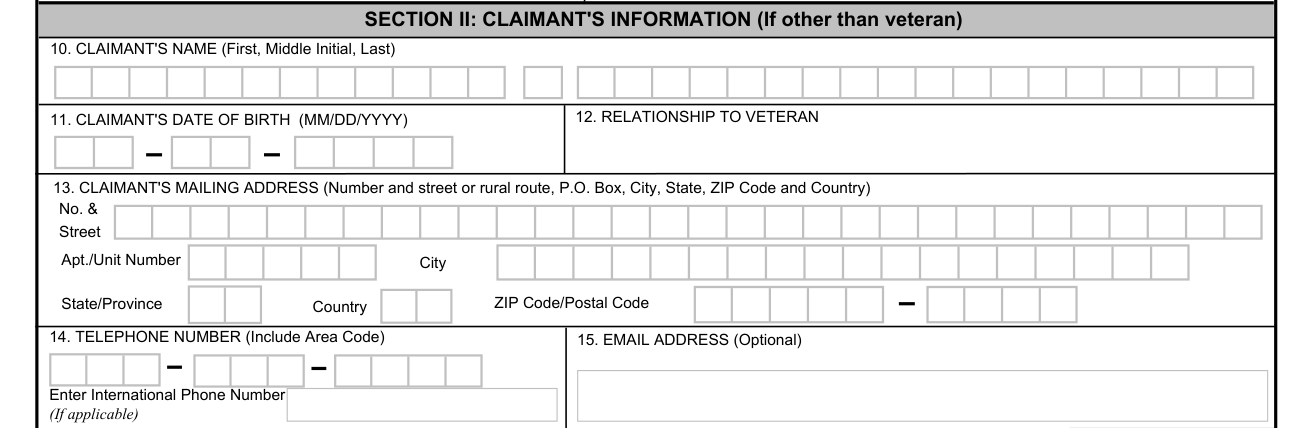
Section II, Claimant's Information, is for a claimant other than the veteran (If other than veteran).
Enter the Claimant's Name (First, Middle Initial, Last) in box 10, the Claimant's Date of Birth (MM/DD/YYYY) in box 11 and the Relationship to Veteran in box 12.
In box 13, enter the Claimant's Mailing Address: No. & Street, Apt./Unit Number, City, ZIP Code/Postal Code, State/Province and Country.
Enter the Telephone Number (Include Area Code) in box 14, and the International Phone Number (If applicable).
The Email Address in box 15 is optional.
Section III, the appointed representative
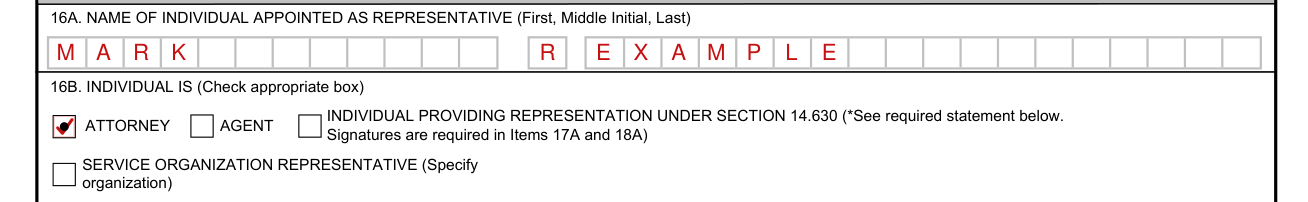
In Section III, Appointed Representative's Information, enter the Name of Individual Appointed as Representative (First, Middle Initial, Last) in box 16A.
In Item 16B, Individual Is (Check appropriate box): Attorney, Agent, Individual Providing Representation Under Section 14.630 (See required statement below. Signatures are required in Items 17A and 18A), or Service Organization Representative (Specify organization).
In 16C, enter the Address of Individual Appointed as Claimant's Representative: No. & Street, Apt./Unit Number, City, ZIP Code/Postal Code, State/Province and Country.
Enter the Telephone Number of Individual Appointed as Claimant's Representative (Include Area Code) in 16D, and the International Phone Number (If applicable).
The Email Address of Individual Appointed as Claimant's Representative in 16E is optional.
Enter the Veteran's Social Security No.
Representation under Section 14.630

An individual acting as representative under 38 C.F.R. 14.630 may not represent more than one claimant on a single claim unless an exception to that limitation has been granted by the Department of Veterans Affairs' (VA) General Counsel.
The appointment of the individual named in Item 16A authorizes that person to represent the individual named in Item 1 or 10 (if other than veteran) for a particular claim pursuant to the provisions of 38 C.F.R. 14.630.
The representative and the claimant attest by their signatures that no compensation will be charged by or paid for the individual named in Item 16A.
Enter the Signature of Veteran Named in Item 1 or Claimant in Item 10 (Required only for representation under 14.630) in 17A and the Date Signed (MM/DD/YYYY) in 17B.
Enter the Signature of Representative Named in Item 16A (Required only for representation under 14.630) in 18A and the Date Signed (MM/DD/YYYY) in 18B.
Items 20 to 22, records and address changes
20. Authorization for Representative's Access to Records Protected by Section 7332, Title 38 U.S.C. (Note: Unless I check the box below, I do not authorize VA to disclose to the individual named in Item 16A any records that may be in my file relating to treatment for drug abuse, alcoholism or alcohol abuse, infection with the human immunodeficiency virus (HIV), or sickle cell anemia.
I authorize the VA facility having custody of my VA claimant records to disclose to the individual named in Item 16A, and the firm/organization/individual(s) named in Item 19 (if approved by VA for affiliated access) all treatment records relating to drug abuse, alcoholism or alcohol abuse, infection with the human immunodeficiency virus (HIV), or sickle cell anemia.
Item 21, Limitation of Consent: My consent in Item 20 for the disclosure of records relating to treatment for drug abuse, alcoholism or alcohol abuse, infection with the human immunodeficiency virus (HIV), or sickle cell anemia is limited as follows.
Item 22: Unless I check the box below, I do not authorize the individual named in Item 16A to act on my behalf to change my address in my VA records.
I authorize the individual named in Item 16A to act on my behalf to change my address in my VA records.
This authorization does not extend to any other individual without my further written consent.
Items 23 to 25, signatures and limits
If the individual named in Item 16A is an accredited agent or attorney, the scope of representation provided before VA may be limited by the agent or attorney as indicated below in Item 24.
I authorize VA to disclose any and all of my records (other than as provided in Items 20 and 21) to that individual appointed as my representative and as indicated in Item 19.
24. Limitations on Representation - Agents or Attorneys Only (Unless limited by an agent or attorney, this power of attorney revokes all previously existing powers of attorney).
Common questions about VA Form 21-22a
What is VA form 21 22A used for?
I, the veteran named in Item 1 or the claimant named in Item 10, hereby appoint the individual named in Item 16A as my representative to prepare, present, and prosecute my claims for any and all benefits from VA based on the service of the veteran named in Item 1.
Where do I file it?
Documents may be submitted by mail, in person at aVA regional office or electronically. However, VA recommends submitting correspondence electronically as this is the fastest method of receipt. To learn more about how to submit documents and claims electronically, visit www.va.gov/disability/upload-supporting-evidence. You can also go directly to access.va.gov to digitally upload any correspondence using Direct Upload. If you prefer to mail your correspondence, please use the related mailing address. Compensation Claims: Department of Veterans Affairs Evidence Intake Center PO Box 4444 Janesville, WI 53547-4444. Pension & Survivors Benefit Claims: Department of Veterans Affairs Pension Intake Center PO Box 5365 Janesville, WI 53547-5365. Fiduciary: Department of Veterans Affairs Fiduciary Intake PO Box 95211 Lakeland, FL 33804-5211. Board of Veterans' Appeals: Department of Veterans Affairs Board of Veterans' Appeals PO Box 27063 Washington, DC 20038.
Are there fees?
Section 5904, Title 38, United States Code, contains provisions regarding fees that may be charged, allowed, or paid for services of agents or attorneys in connection with a proceeding before the Department of Veterans Affairs with respect to benefits under laws administered by the Department.
Is there a penalty?
The law provides severe penalties which include fine or imprisonment, or both, for the willful submission of any statement or evidence of a material fact, knowing it to be false.
Sources
[1] VA Form 21-22a (JUL 2023), Appointment of Individual as Claimant's Representative, U.S. Department of Veterans Affairs (the Official source link on this page).