

VA Form 21-8940 at a glance
What it is: This is the Veteran's Application for Increased Compensation Based on Unemployability, VA Form 21-8940.
Where and when to file: Mail the form to the Department of Veterans Affairs Evidence Intake Center PO Box 4444 Janesville, WI 53547-4444.
When you complete this form you are claiming total disability because of a service-connected disability(ies) which has/have prevented you from securing or following any substantially gainful occupation. Answer all questions fully and accurately. See mailing information on page 4 of this form.
A filled-in VA Form 21-8940 example: a veteran claims unemployability
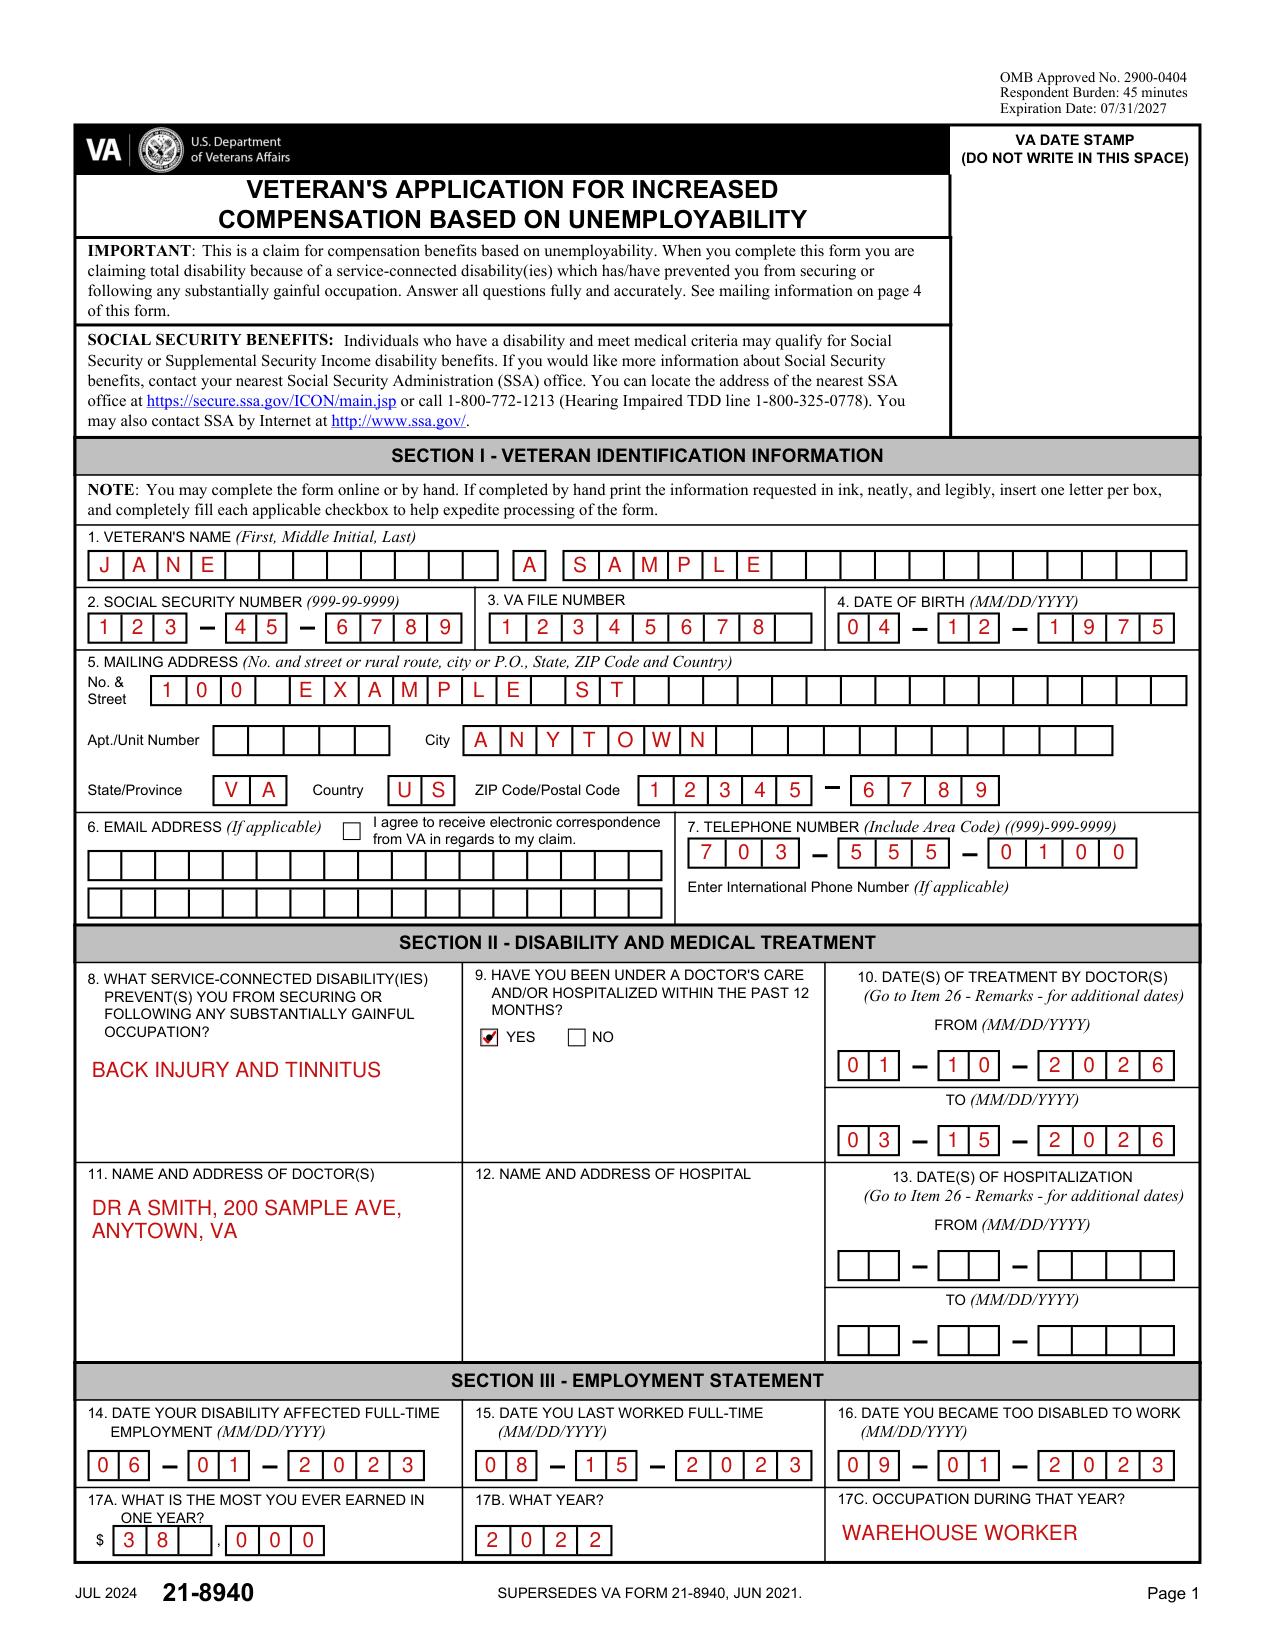
How to fill out VA Form 21-8940, box by box
Veteran identification information
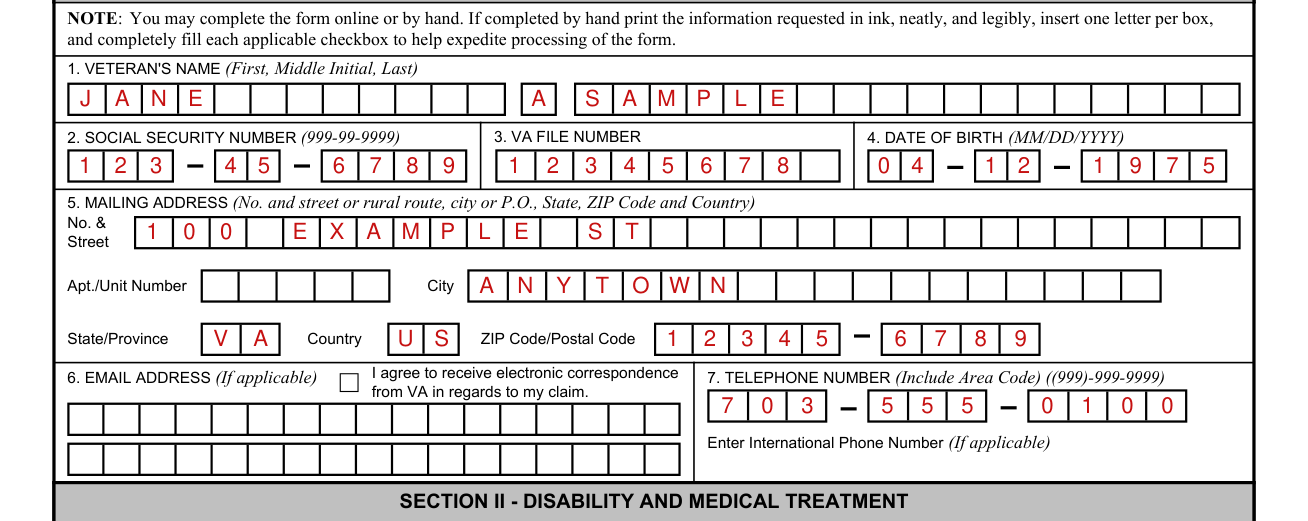
If completed by hand, print the information requested in ink, neatly, and legibly, insert one letter per box, and completely fill each applicable checkbox to help expedite processing of the form.
Enter the Veteran's Name (First, Middle Initial, Last), Social Security Number (999-99-9999), VA File Number and Date of Birth (MM/DD/YYYY).
Enter the Mailing Address (No. and street or rural route, city or P.O., State, ZIP Code and Country): No. & Street, Apt./Unit Number, City, State/Province, Country and ZIP Code/Postal Code.
Enter the Email Address (If applicable) and the Telephone Number (Include Area Code), or the International Phone Number (If applicable).
Disability and medical treatment
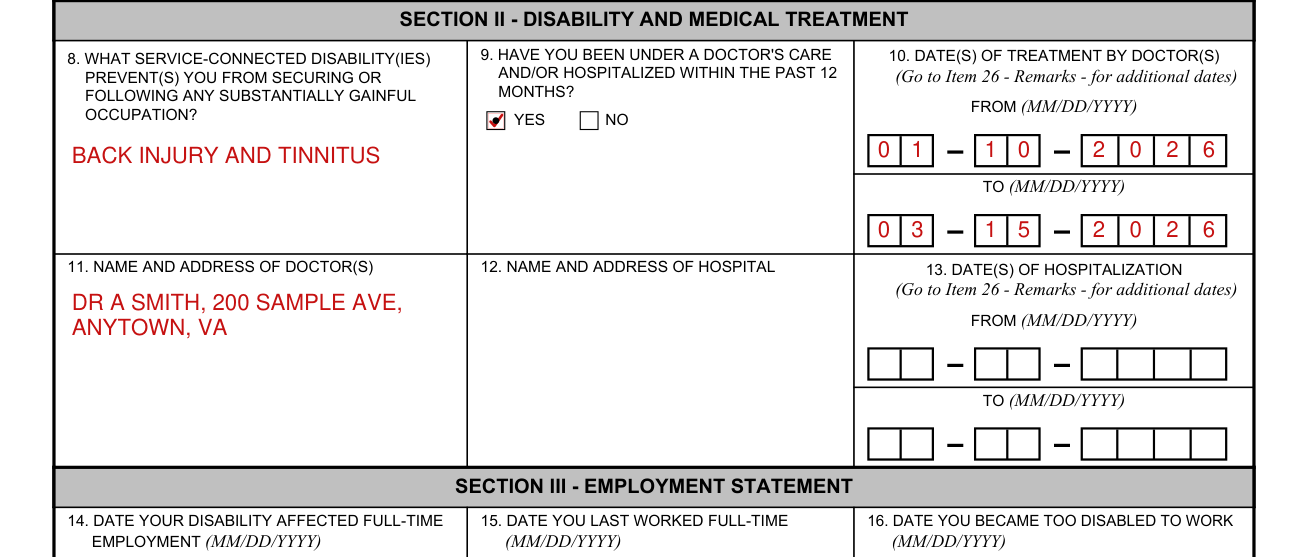
8. What service-connected disability(ies) prevent(s) you from securing or following any substantially gainful occupation? List them.
9. Have you been under a doctor's care and/or hospitalized within the past 12 months? Mark YES or NO.
In Item 10, enter the date(s) of treatment by doctor(s) FROM (MM/DD/YYYY) and TO (MM/DD/YYYY); go to Item 26 - Remarks - for additional dates.
Enter 11. Name and Address of Doctor(s) and 12. Name and Address of Hospital; for 13. Date(s) of Hospitalization, enter FROM and TO (MM/DD/YYYY) and go to Item 26 - Remarks - for additional dates.
Employment dates and earnings
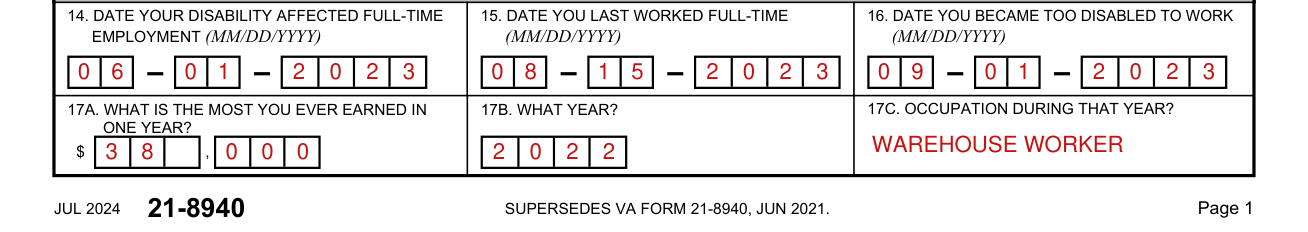
Enter the date your disability affected full-time employment (14), the date you last worked full-time (15) and the date you became too disabled to work (16), each as MM/DD/YYYY.
17A. What is the most you ever earned in one year? 17B. What year? 17C. Occupation during that year?
Employment for the last five years
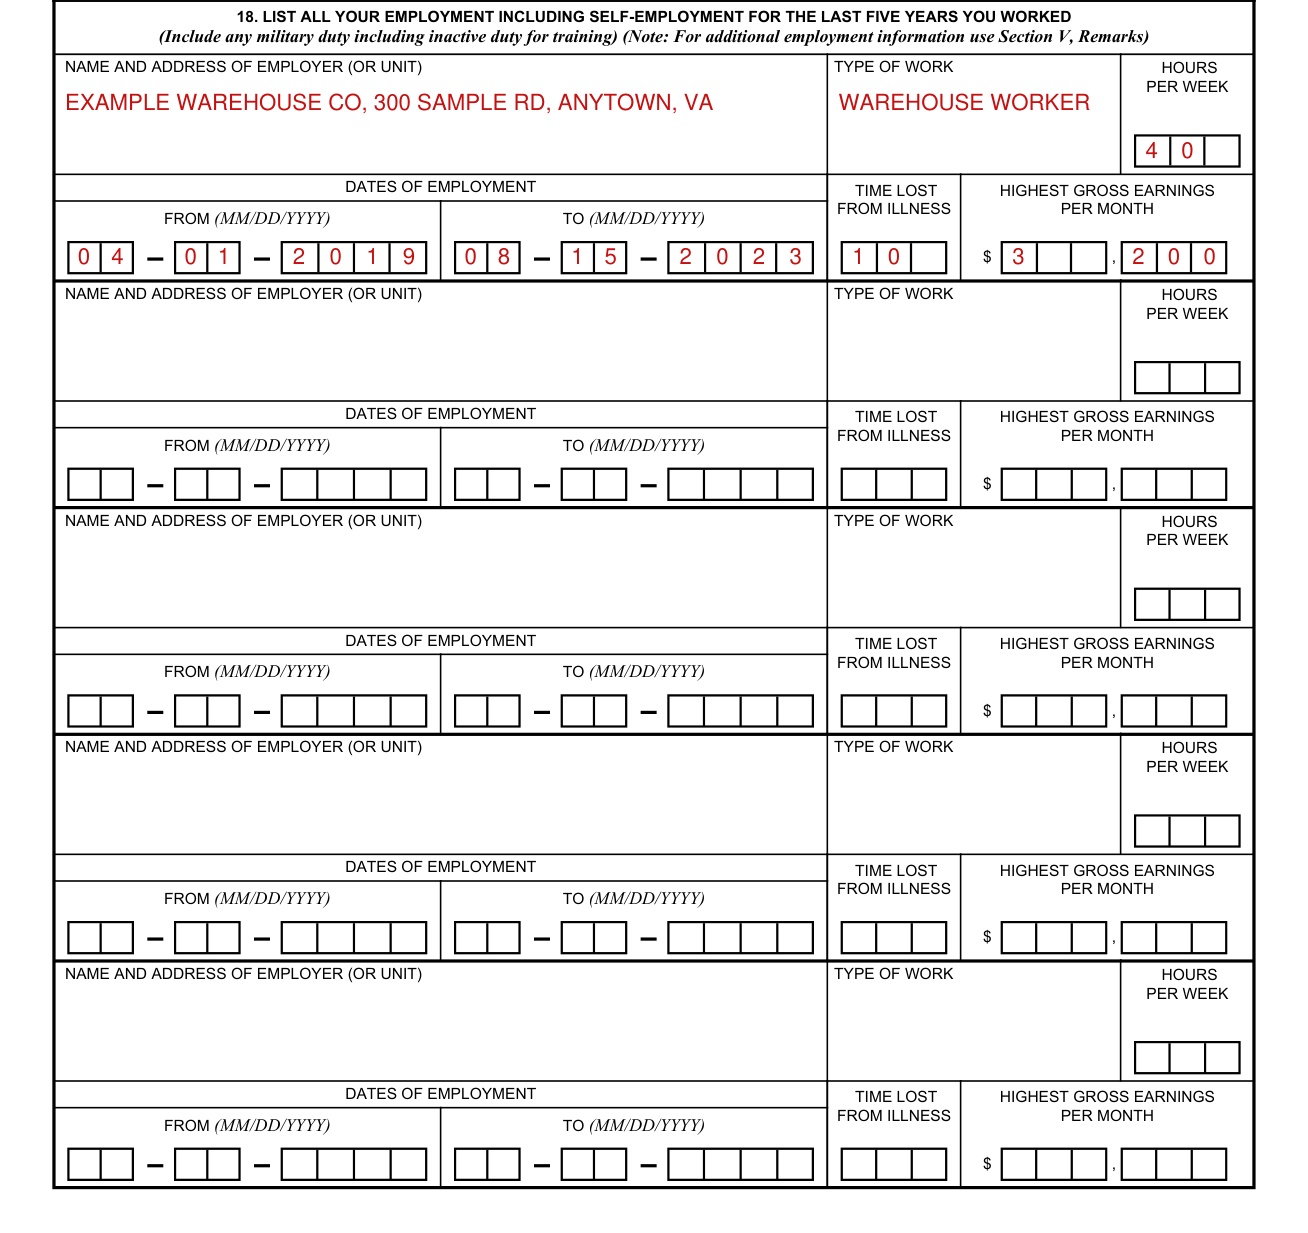
18. List all your employment including self-employment for the last five years you worked (Include any military duty including inactive duty for training); for additional employment information use Section V, Remarks.
For each employer, enter Name and Address of Employer (or Unit), Type of Work, Hours per Week, Dates of Employment FROM and TO (MM/DD/YYYY), Time Lost from Illness and Highest Gross Earnings per Month.
Earned income, benefits and employment you tried to obtain
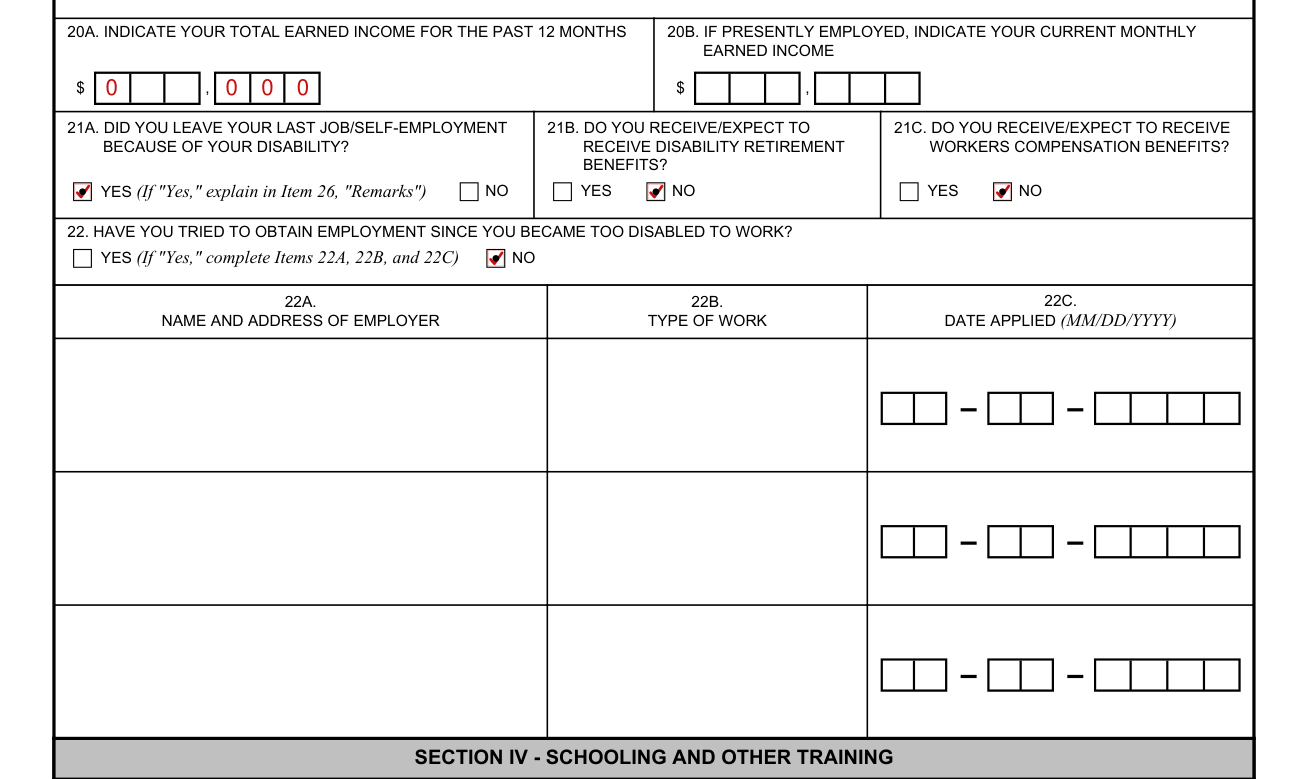
19. If you are currently serving in the Reserve or National Guard, does your service connected disability prevent you from performing your military duties? Mark YES or NO.
20A. Indicate your total earned income for the past 12 months. 20B. If presently employed, indicate your current monthly earned income.
21A. Did you leave your last job/self-employment because of your disability? Mark YES (If "Yes," explain in Item 26, "Remarks") or NO.
21B. Do you receive/expect to receive disability retirement benefits? 21C. Do you receive/expect to receive workers compensation benefits? Mark YES or NO for each.
22. Have you tried to obtain employment since you became too disabled to work? Mark YES (If "Yes," complete Items 22A, 22B, and 22C) or NO; 22A. Name and Address of Employer, 22B. Type of Work and 22C. Date Applied (MM/DD/YYYY).
Schooling and other training
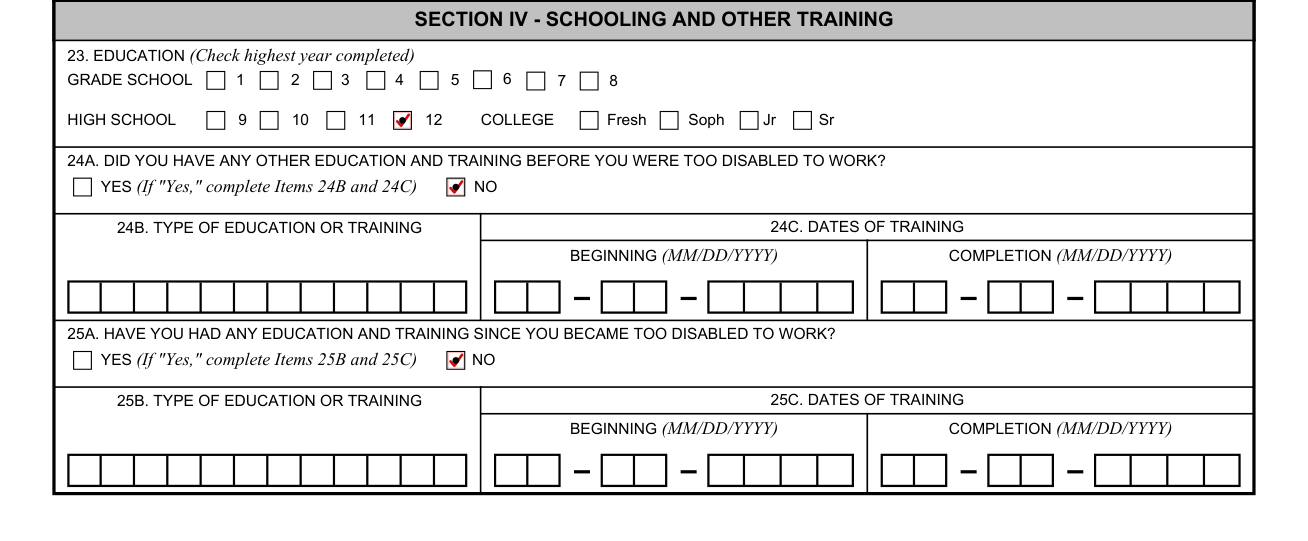
23. Education: check highest year completed.
24A. Did you have any other education and training before you were too disabled to work? Mark YES (If "Yes," complete Items 24B and 24C) or NO; 24B. Type of Education or Training and 24C. Dates of Training, Beginning and Completion (MM/DD/YYYY).
25A. Have you had any education and training since you became too disabled to work? Mark YES (If "Yes," complete Items 25B and 25C) or NO; 25B. Type of Education or Training and 25C. Dates of Training.
Remarks, signature and witnesses
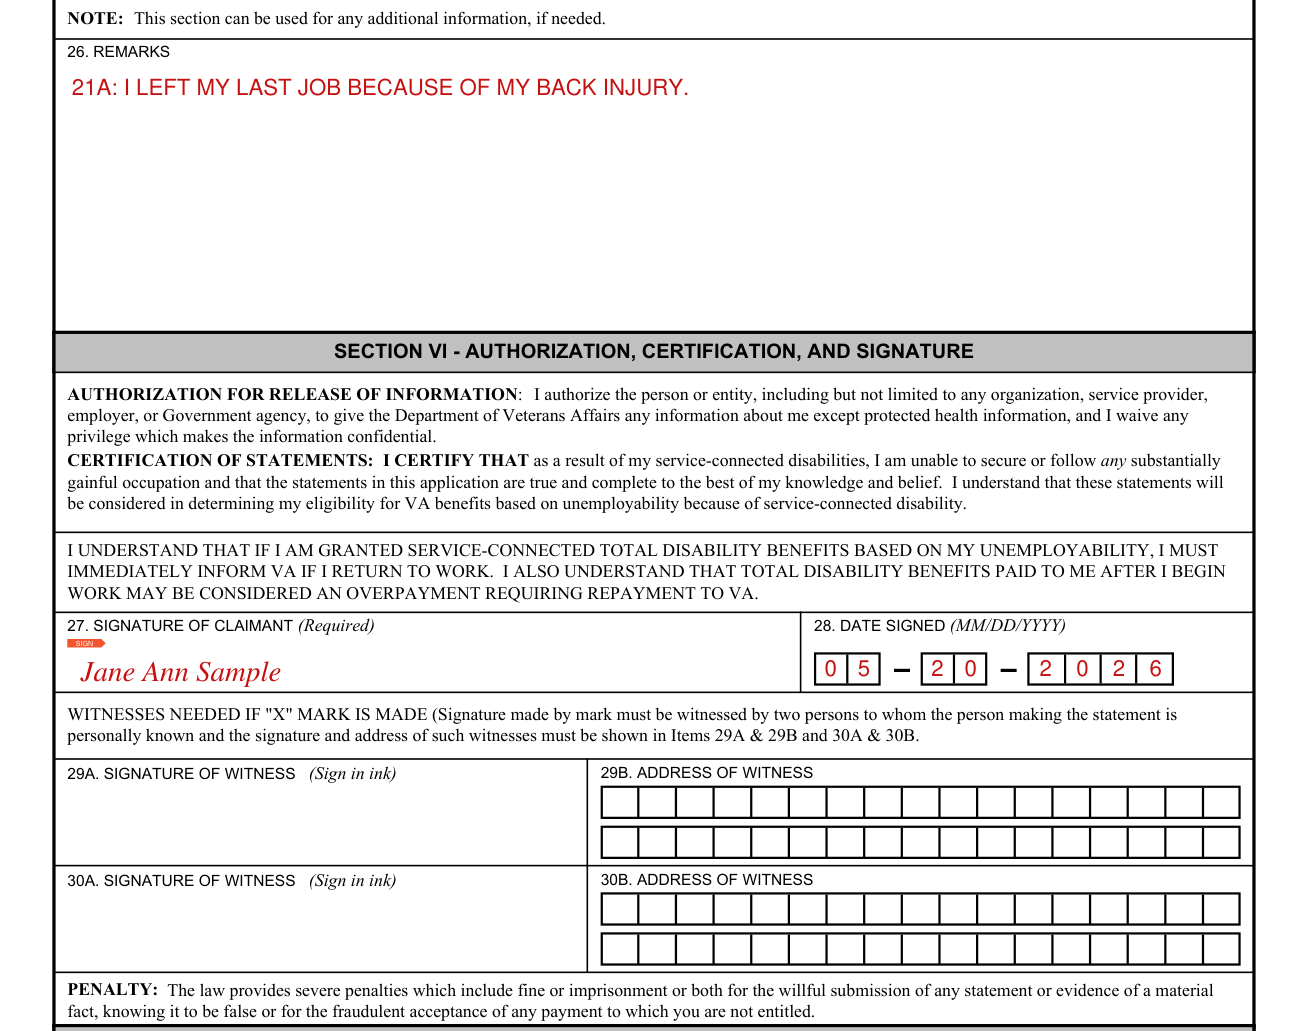
26. Remarks: this section can be used for any additional information, if needed.
By signing you certify that as a result of your service-connected disabilities, you are unable to secure or follow any substantially gainful occupation and that the statements in the application are true and complete to the best of your knowledge and belief.
Sign 27. Signature of Claimant (Required) and enter 28. Date Signed (MM/DD/YYYY).
Witnesses are needed if "X" mark is made: a signature made by mark must be witnessed by two persons to whom the person making the statement is personally known, and the signature and address of such witnesses must be shown in Items 29A & 29B and 30A & 30B.
Common questions about VA Form 21-8940
Where do I file it?
Mail the form to the Department of Veterans Affairs Evidence Intake Center PO Box 4444 Janesville, WI 53547-4444.
Is there a penalty?
The law provides severe penalties which include fine or imprisonment or both for the willful submission of any statement or evidence of a material fact, knowing it to be false or for the fraudulent acceptance of any payment to which you are not entitled.
Sources
[1] VA Form 21-8940 (JUL 2024), Veteran's Application for Increased Compensation Based on Unemployability, Department of Veterans Affairs (the Official source link on this page).
