

VA Form 28-8872 at a glance
What it is: VA Form 28-8872, JUL 2010, is the REHABILITATION PLAN.
Who signs: Sign in box 12 as the SIGNATURE OF VETERAN. Box 13 is the SIGNATURE OF COUNSELING PSYCHOLOGIST and box 14 is the SIGNATURE OF VOCATIONAL REHABILITATION SPECIALIST.
A filled-in VA Form 28-8872 example: a veteran plans one objective
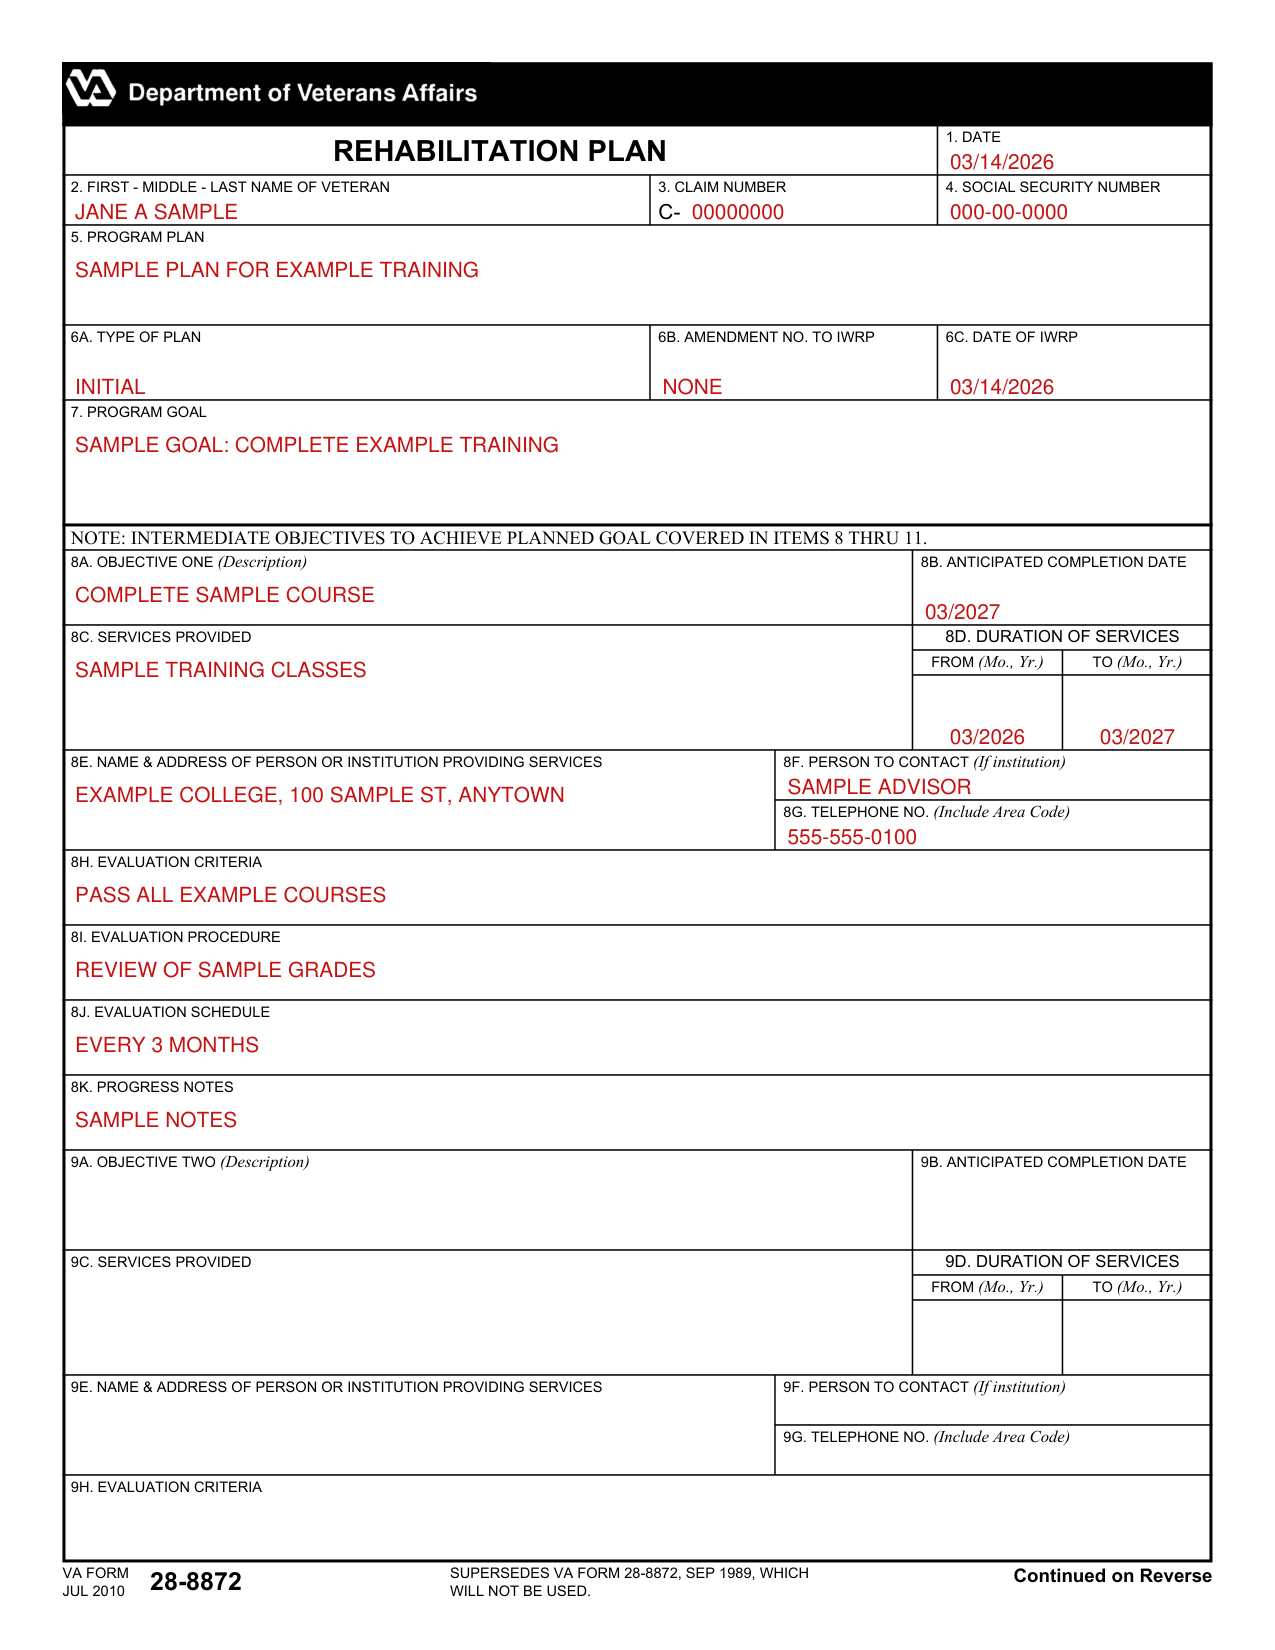
How to fill out VA Form 28-8872, box by box
Date, veteran, claim number and Social Security number
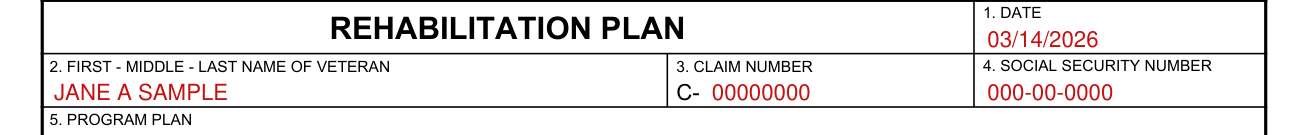
Enter the DATE in box 1, the FIRST - MIDDLE - LAST NAME OF VETERAN in box 2, the CLAIM NUMBER after C- in box 3 and the SOCIAL SECURITY NUMBER in box 4.
Program plan, type of plan and program goal
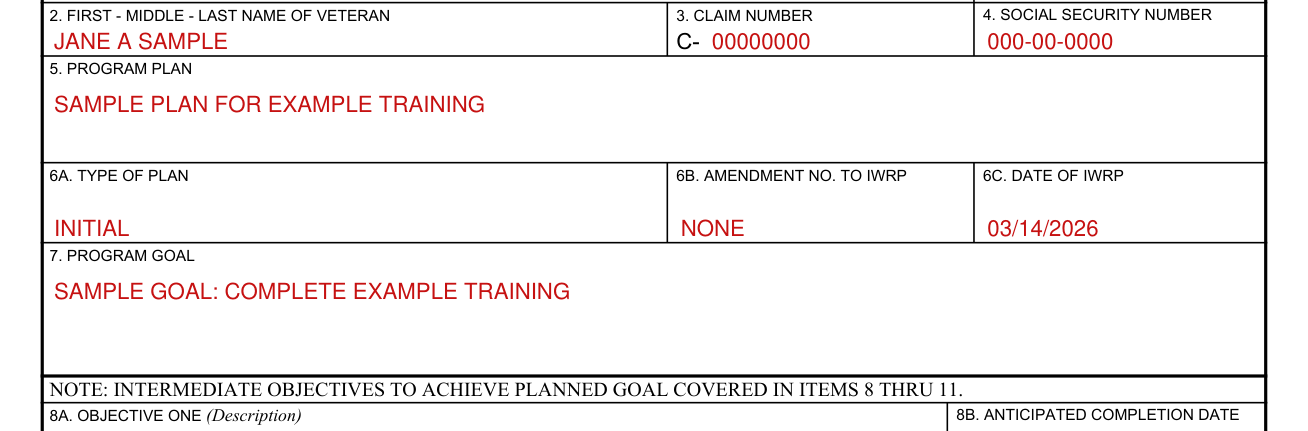
Enter the PROGRAM PLAN in box 5.
Enter the TYPE OF PLAN in 6A, the AMENDMENT NO. TO IWRP in 6B and the DATE OF IWRP in 6C.
Enter the PROGRAM GOAL in box 7. The intermediate objectives to achieve the planned goal are covered in items 8 thru 11.
Objective one

Describe OBJECTIVE ONE in 8A and enter the ANTICIPATED COMPLETION DATE in 8B.
Enter the SERVICES PROVIDED in 8C and the DURATION OF SERVICES in 8D, FROM (Mo., Yr.) TO (Mo., Yr.).
Enter the NAME & ADDRESS OF PERSON OR INSTITUTION PROVIDING SERVICES in 8E, the PERSON TO CONTACT (If institution) in 8F and the TELEPHONE NO. (Include Area Code) in 8G.
Enter the EVALUATION CRITERIA in 8H, the EVALUATION PROCEDURE in 8I, the EVALUATION SCHEDULE in 8J and the PROGRESS NOTES in 8K.
Objective two

Describe OBJECTIVE TWO in 9A and enter the ANTICIPATED COMPLETION DATE in 9B.
Enter the SERVICES PROVIDED in 9C and the DURATION OF SERVICES in 9D, FROM (Mo., Yr.) TO (Mo., Yr.).
Enter the NAME & ADDRESS OF PERSON OR INSTITUTION PROVIDING SERVICES in 9E, the PERSON TO CONTACT (If institution) in 9F and the TELEPHONE NO. (Include Area Code) in 9G.
Enter the EVALUATION CRITERIA in 9H.
ITEM 9 (CONTINUED): enter the EVALUATION PROCEDURE in 9I, the EVALUATION SCHEDULE in 9J and the PROGRESS NOTES in 9K.
Objective three
Describe OBJECTIVE THREE in 10A and enter the ANTICIPATED COMPLETION DATE in 10B.
Enter the SERVICES PROVIDED in 10C and the DURATION OF SERVICES in 10D, FROM (Mo., Yr.) TO (Mo., Yr.).
Enter the NAME & ADDRESS OF PERSON OR INSTITUTION PROVIDING SERVICES in 10E, the PERSON TO CONTACT (If institution) in 10F and the TELEPHONE NO. (Include Area Code) in 10G.
Enter the EVALUATION CRITERIA in 10H, the EVALUATION PROCEDURE in 10I, the EVALUATION SCHEDULE in 10J and the PROGRESS NOTES in 10K.
Closure statement
Enter the CLOSURE STATEMENT in box 11.
Signatures and annual review date
I CERTIFY THAT I have participated in the development of this program plan. I understand it is my responsibility to cooperate in the program and make reasonable efforts on my behalf. There will be periodic and/or an annual review of the plan, at which time the VA staff members and I will have a chance to jointly redevelop it.
Box 13 is the SIGNATURE OF COUNSELING PSYCHOLOGIST and box 14 is the SIGNATURE OF VOCATIONAL REHABILITATION SPECIALIST.
Enter the ANNUAL REVIEW DATE in box 15.
More rules for VA Form 28-8872
VA will not disclose information collected on this form to any source other than what has been authorized under the Privacy Act of 1974 or Title 38, Code of Federal Regulations 1.576 for the purpose of educational and vocational planning and to help you make the best use of your rehabilitation benefits.
Your obligation to respond is required to obtain or retain benefits.
Giving your SSN account information is voluntary. Refusal to provide your SSN by itself will not result in the denial of benefits.
Common questions about VA Form 28-8872
When is this form not the right one?
This form supersedes VA Form 28-8872, SEP 1989, which will not be used.
Sources
[1] VA Form 28-8872 (JUL 2010), Rehabilitation Plan, U.S. Department of Veterans Affairs (the Official source link on this page).
