

Vehicle Accident or Damage Report at a glance
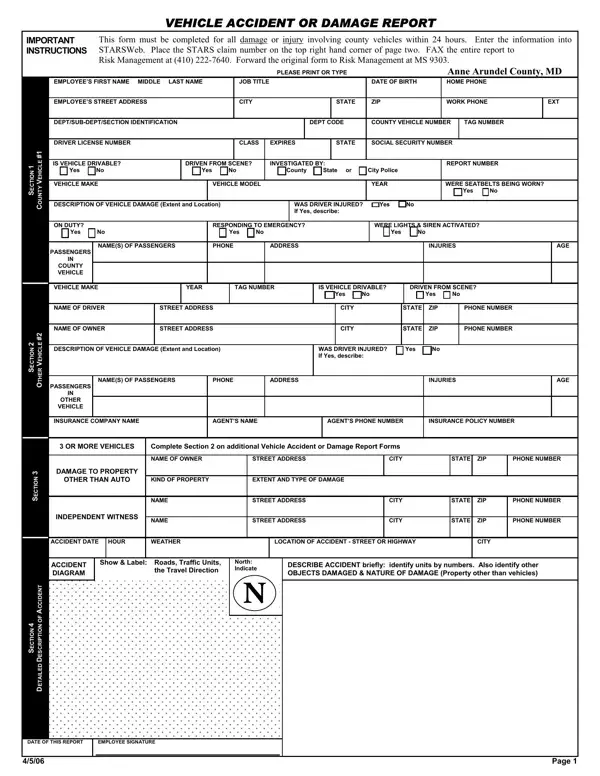
What it is: Vehicle Accident or Damage Report, Anne Arundel County, MD. Please print or type.
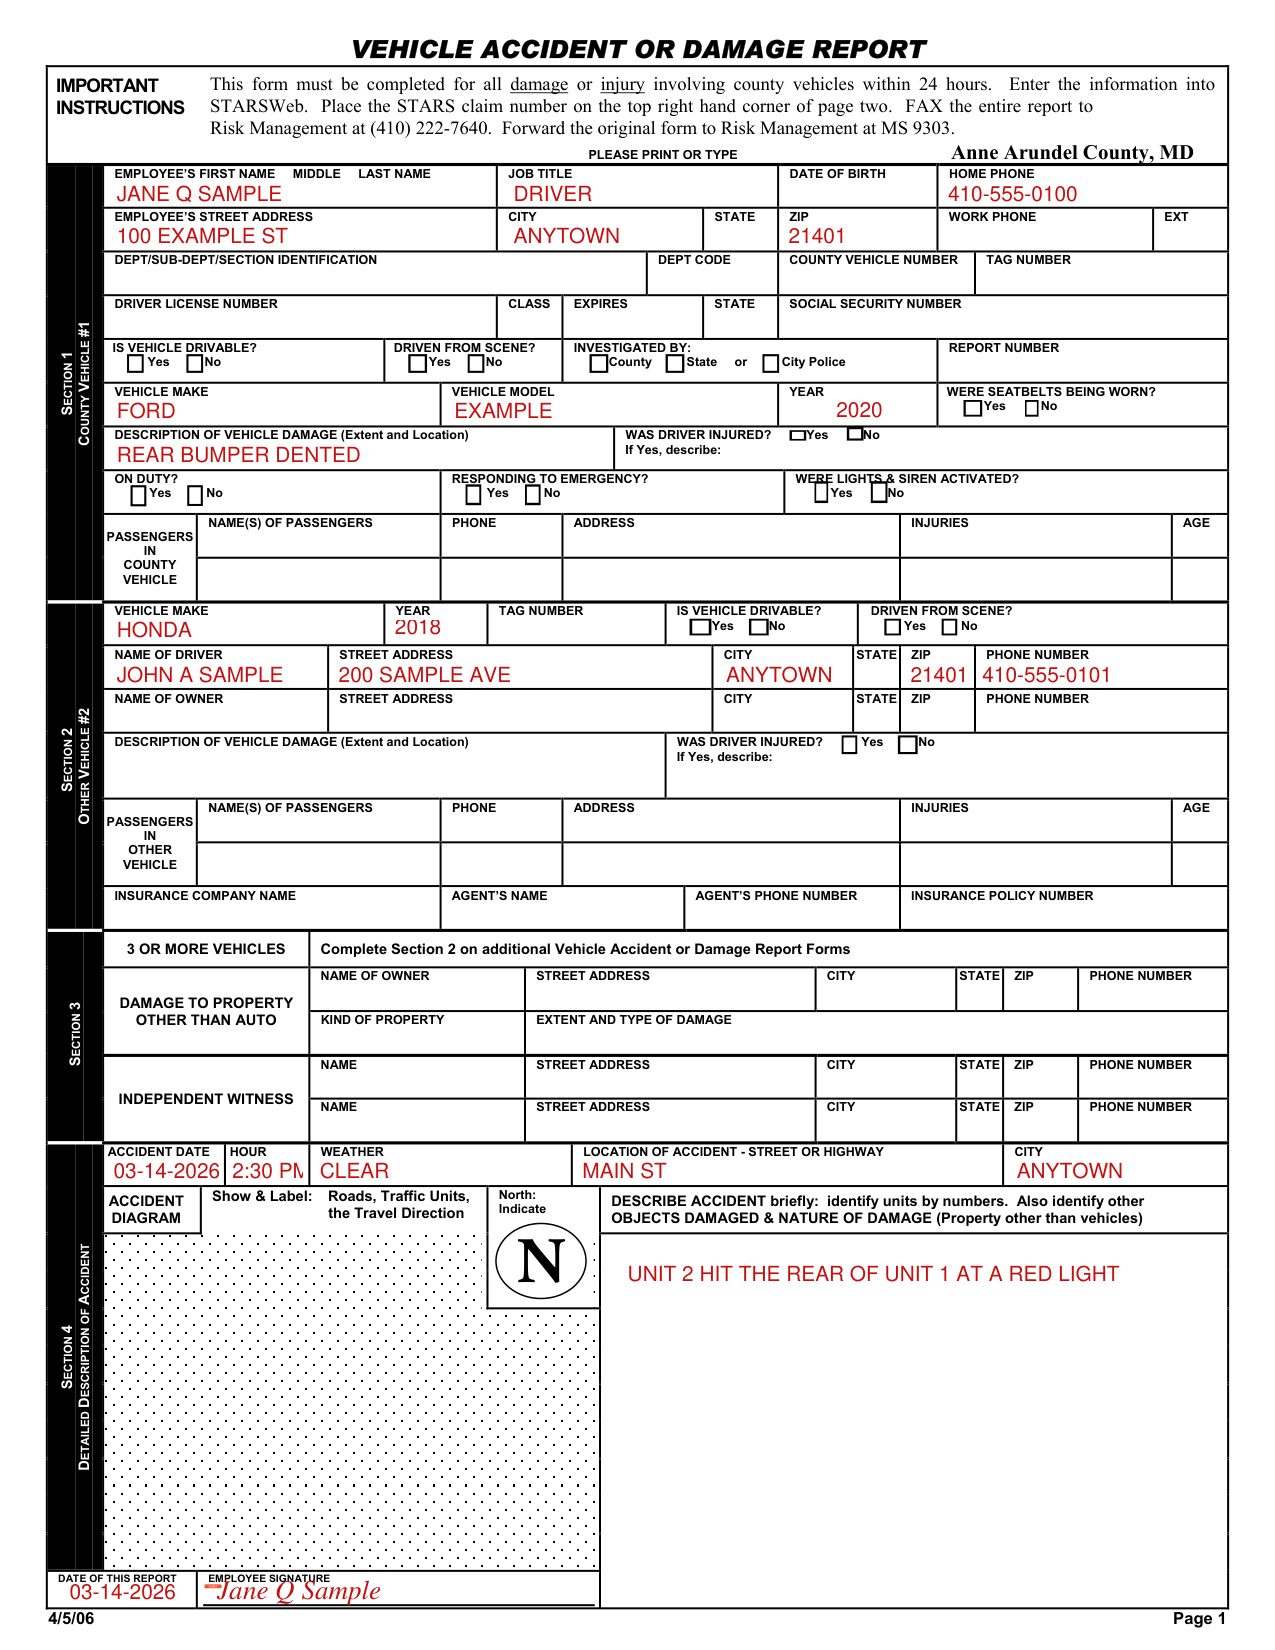
A filled-in Vehicle Accident or Damage Report example: an employee reports a rear-end accident
How to fill out Vehicle Accident or Damage Report, box by box
The employee
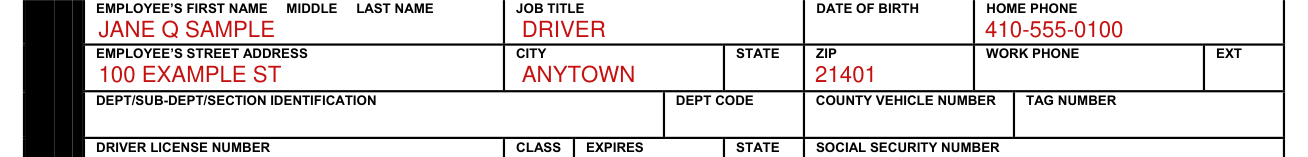
Under the employee's name, enter First Name, Middle, Last, Job Title, Date of Birth, Home Phone, Street Address, City, State, Zip, Work Phone and Ext.
County vehicle number, tag number and driver license
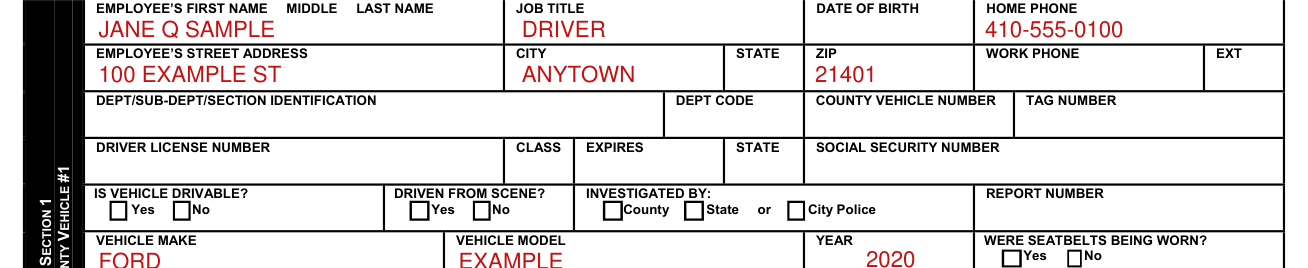
Enter the Dept/Sub-Dept/Section Identification, Dept Code, County Vehicle Number, Tag Number, Driver License Number, Class, Expires, State and Social Security Number.
Section 1, the county vehicle
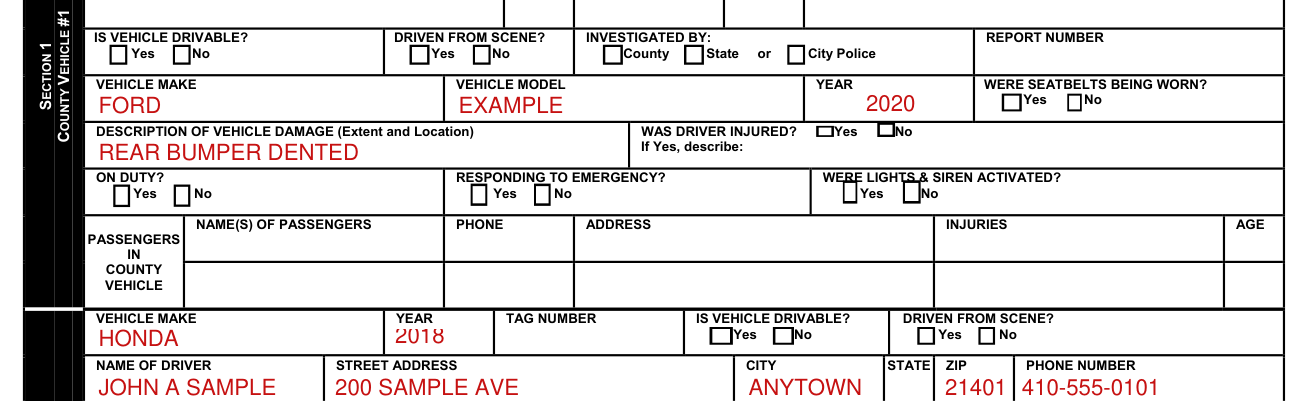
Under County Vehicle #1, mark Yes or No for Is Vehicle Drivable? and Driven From Scene?, and for Investigated By: mark County, State or City Police with the Report Number.
In Section 1, enter the Vehicle Make, Vehicle Model and Year, and mark Yes or No for Were Seatbelts Being Worn?
Enter the Description of Vehicle Damage (Extent and Location), and mark Yes or No for Was Driver Injured? If Yes, describe.
Mark Yes or No for On Duty?, Responding to Emergency? and Were Lights & Siren Activated?
For Passengers in County Vehicle, enter the Name(s) of Passengers, Phone, Address, Injuries and Age.
Section 2, the other vehicle

In Section 2, under Other Vehicle #2, enter the Vehicle Make, Year and Tag Number, and mark Yes or No for Is Vehicle Drivable? and Driven From Scene?
Enter the Name of Driver and the Name of Owner, each with Street Address, City, State, Zip and Phone Number.
Other Vehicle: Description of Vehicle Damage (Extent and Location); mark Yes or No for Was Driver Injured? If Yes, describe.
Passengers in Other Vehicle: Name(s) of Passengers, Phone, Address, Injuries and Age.
Enter the Insurance Company Name, Agent's Name, Agent's Phone Number and Insurance Policy Number.
For 3 or more vehicles, complete Section 2 on additional Vehicle Accident or Damage Report Forms.
Section 3, damage to property other than auto and independent witness

In Section 3, for Damage to Property Other Than Auto, enter the Kind of Property and the Extent and Type of Damage.
Enter the owner's Name, Street Address, City, State, Zip and Phone Number.
For Independent Witness, enter the Name, Street Address, City, State, Zip and Phone Number.
Accident date, location and description
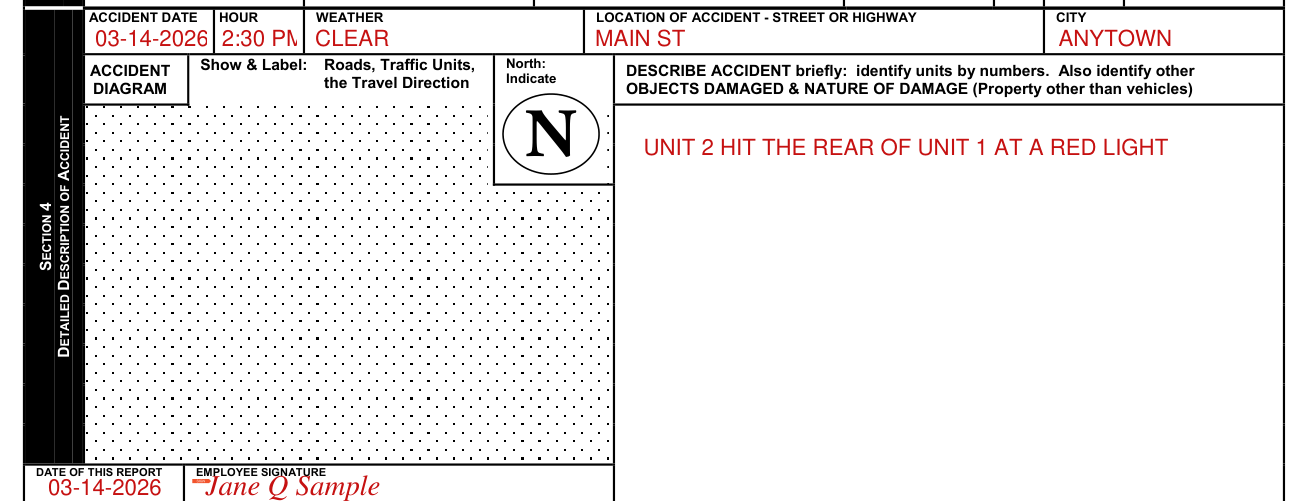
Enter the Accident Date, Hour, Weather, Location of Accident - Street or Highway, and City.
In the Accident Diagram, show and label roads, traffic units and the travel direction, and Indicate North.
Describe the accident briefly: identify units by numbers. Also identify other objects damaged and the nature of damage (property other than vehicles).
Section 4, date of this report and employee signature

In Section 4, enter the Date of This Report and sign the Employee Signature line.
Page 2, employee driver and contributing factors

Mark Yes or No for Did the Employee Seek Medical Treatment? If Yes, provide Name, Address, Phone.
Mark Yes or No for Was Workers' Compensation Incident Report Form Completed?
Enter the Hours of Continuous Duty for Employee Driver, mark Yes or No for Was the Employee Following County Procedure(s)?, and enter the Years of Experience Doing This Job.
For Factors Contributing to the Incident, check all that apply: Inattention, Attitude, Physical Impairment, Unsafe Equipment, Equipment Failure, Fatigue, Lack of Training, Improper Maintenance, Driving Too Fast for Conditions, Inexperience, or Other, Explain.
For Lighting, check the one that applies: Daylight, Dusk/Dawn, Night, Shadows or Sun/Glare.
Mark Yes or No for Has Employee Received Previous Notices or Warnings About Their Unsafe Acts or Conditions? If Yes, when, and mark Oral or Written.
Page 2, supervisor section
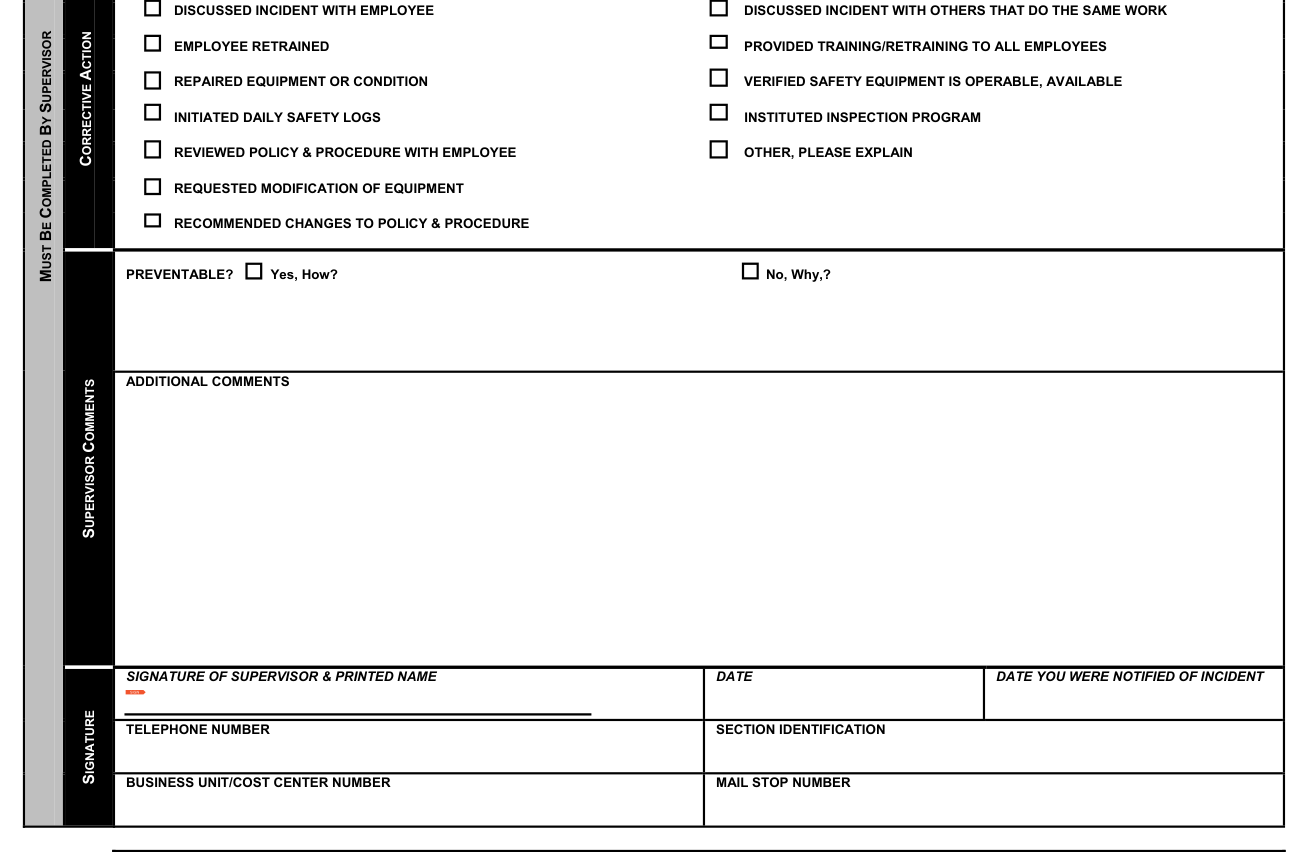
Must be completed by supervisor.
For What Action Has Been Taken to Correct or Eliminate the Unsafe Act or Condition, check all that apply: Discussed Incident With Employee, Discussed Incident With Others That Do the Same Work, Employee Retrained, Provided Training/Retraining to All Employees, Repaired Equipment or Condition, Verified Safety Equipment Is Operable, Available, Initiated Daily Safety Logs, Instituted Inspection Program, Reviewed Policy & Procedure With Employee, Other, Please Explain, Requested Modification of Equipment, or Recommended Changes to Policy & Procedure.
Mark Preventable? Yes, How? or No, Why?
Enter the Supervisor Comments and Additional Comments.
The supervisor enters the Signature of Supervisor & Printed Name, the Date, and the Date You Were Notified of Incident.
Enter the Telephone Number, Section Identification, Business Unit/Cost Center Number and Mail Stop Number.
More rules for Vehicle Accident or Damage Report
This form must be completed for all damage or injury involving county vehicles within 24 hours. Enter the information into STARSWeb. Place the STARS claim number on the top right hand corner of page two. FAX the entire report to Risk Management at (410) 222-7640. Forward the original form to Risk Management at MS 9303.
Sources
[1] Vehicle Accident or Damage Report (4/5/06), Anne Arundel County, MD (the Official source link on this page).