

Form CF-ES 2620 at a glance
What it is: CF-ES 2620, VERIFICATION OF EMPLOYMENT/LOSS OF INCOME: in order to determine the eligibility for public assistance, answer the questions on this form.
Who signs: Under Section IV - EMPLOYER INFORMATION, enter the Signature of Employer and Employer's Title.
A filled-in Form CF-ES 2620 example: a cook's last four weeks of pay

How to fill out Form CF-ES 2620, box by box
Office Address / Phone Number, Case Name and Case Number

Answer the questions in this form and return this form by the blank at the end of "In order to determine the eligibility".
Office Address / Phone Number, Case Name and Case Number/Cat/Seq. are lines of this form.
Section I - GENERAL INFORMATION
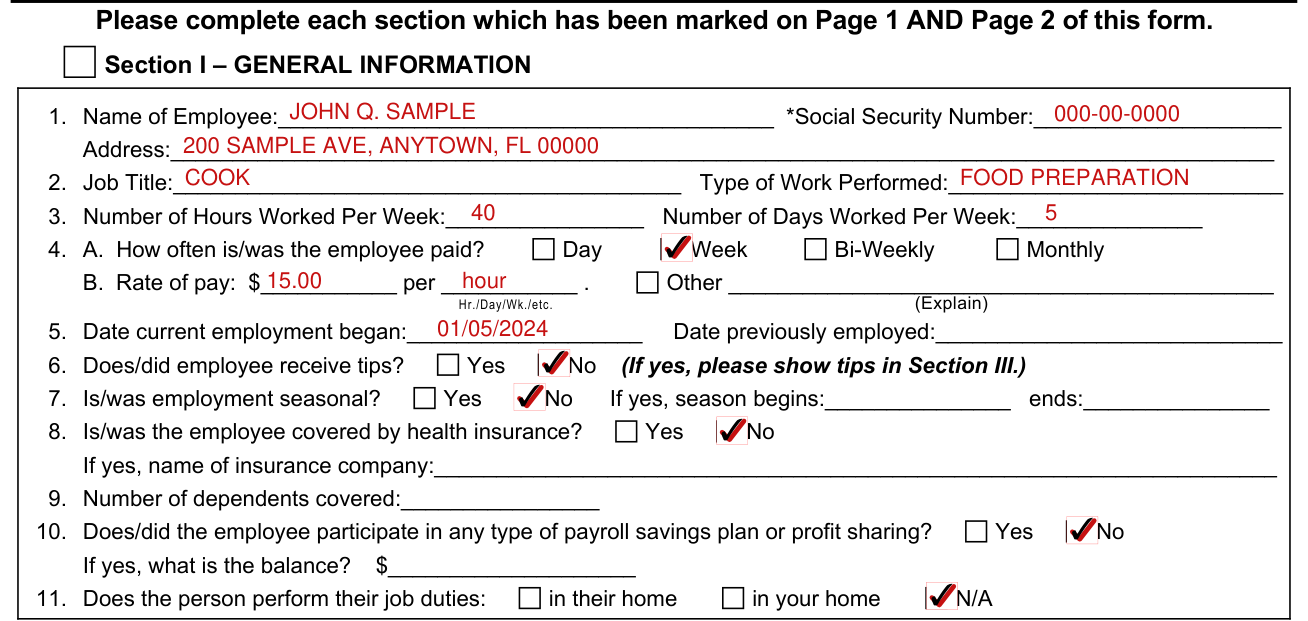
Complete each section which has been marked on Page 1 AND Page 2 of this form.
Under Section I - GENERAL INFORMATION, enter in 1 the Name of Employee and the Social Security Number.
Enter the Address, then in 2 the Job Title and Type of Work Performed and in 3 the Number of Hours Worked Per Week and Number of Days Worked Per Week. In 4, mark Day, Week, Bi-Weekly or Monthly for how often the employee is/was paid; in B, enter the Rate of pay per Hr./Day/Wk./etc. or mark Other and explain. In 5, enter the Date current employment began and the Date previously employed. In 6, mark Yes or No for tips; If yes, please show tips in Section III. In 7, mark Yes or No for seasonal employment; If yes, enter when the season begins and ends. In 8, mark Yes or No for health insurance; If yes, enter the name of insurance company. In 9, enter the Number of dependents covered. In 10, mark Yes or No for any type of payroll savings plan or profit sharing; If yes, enter the balance. In 11, mark in their home, in your home or N/A for where the person performs their job duties.
For the * Social Security Number in 1, Name of Employee: Pursuant to 42 C.F.R. § 435.910, the Department is requesting the social security number (SSN), but you are not required to provide the SSN under the law. However, if you give the SSN the Department can determine eligibility for assistance or services faster and more accurately.
Social security numbers are used by the Department for identity verification, income and eligibility verification and other purposes related to administration of our programs.
Section II - LOSS OF INCOME
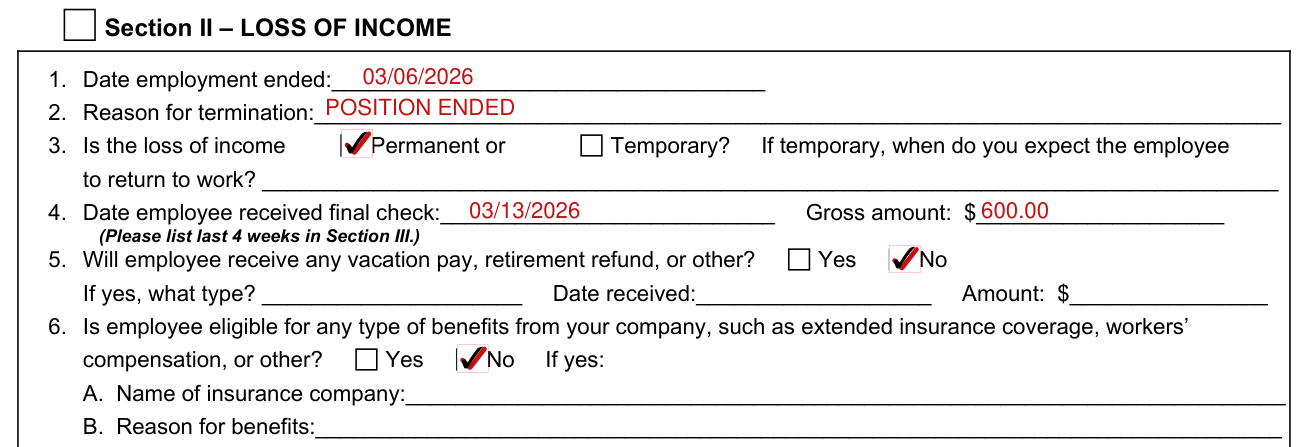
Under Section II - LOSS OF INCOME, enter in 1 the Date employment ended and in 2 the Reason for termination.
In 3, mark Permanent or Temporary; If temporary, enter when you expect the employee to return to work.
In 4, enter the Date employee received final check and the Gross amount. (Please list last 4 weeks in Section III.)
In 5, mark Yes or No for any vacation pay, retirement refund, or other; If yes, enter what type, the Date received and the Amount.
In 6, mark Yes or No for any type of benefits from your company, such as extended insurance coverage, workers' compensation, or other; If yes: A. Name of insurance company and B. Reason for benefits.
Section III - RECORD OF PAY RECEIVED
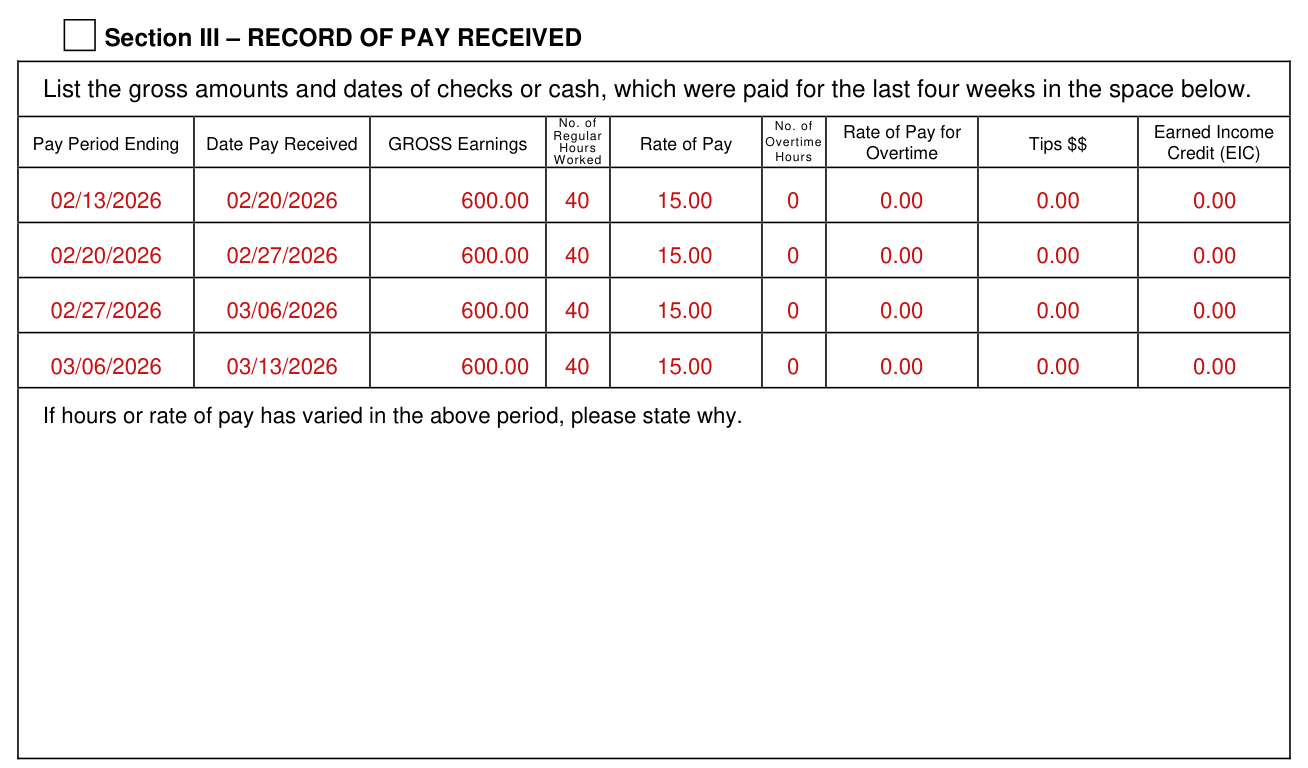
Under Section III - RECORD OF PAY RECEIVED, list the gross amounts and dates of checks or cash, which were paid for the last four weeks in the space.
For each pay, enter the Pay Period Ending, Date Pay Received, GROSS Earnings, No. of Regular Hours Worked, Rate of Pay, No. of Overtime Hours, Rate of Pay for Overtime, Tips and Earned Income Credit (EIC).
If hours or rate of pay has varied in the period, please state why.
Section IV - EMPLOYER INFORMATION
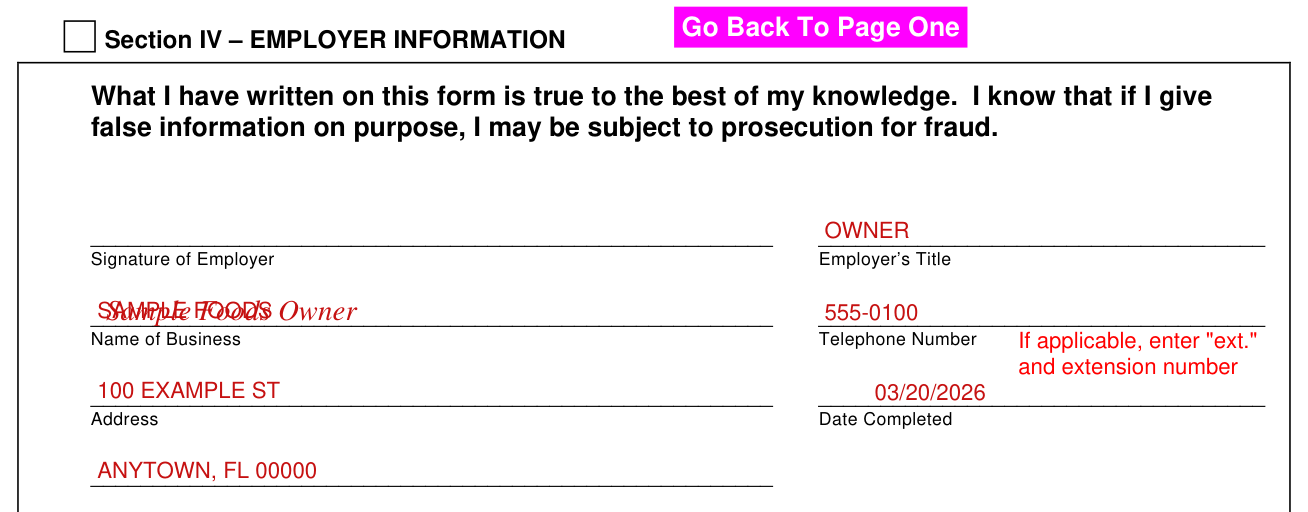
Enter the Name of Business and Telephone Number. If applicable, enter "ext." and extension number.
Enter the Address and Date Completed.
Common questions about Form CF-ES 2620
Is there a penalty?
If you give false information on purpose, you may be subject to prosecution for fraud.
What am I certifying when I sign?
What you have written on this form is true to the best of your knowledge.
Sources
[1] Form CF-ES 2620 (05/2010), Verification of Employment/Loss of Income, Florida Department of Children and Families (the Official source link on this page).
