
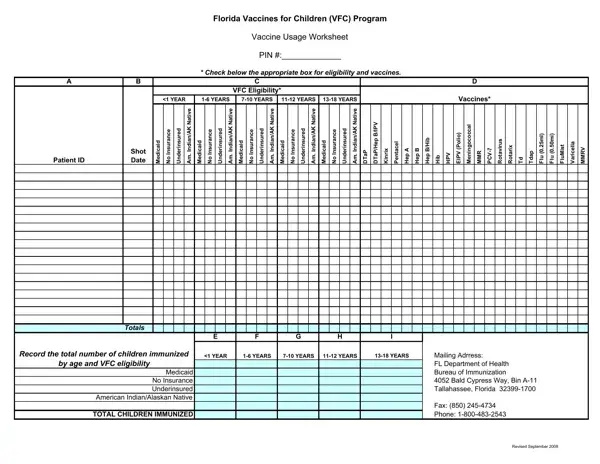
Check the appropriate boxes for eligibility and vaccines.
Privacy: this form contains patient information. To ensure patient privacy, do not send without calling a VFC Program representative at 1-877-888-7468.
Where to send: Florida Department of Health VFC Program, Immunization Section, 4052 Bald Cypress Way, Bin A-11, Tallahassee, Florida 32399-1700.
VFC eligibility: Medicaid, No Insurance, Underinsured, or American Indian/Alaskan Native.
Totals: Total Children Immunized by Age and VFC Eligibility.
| Question | Answer |
|---|---|
| Form Name | Vaccine Usage Worksheet |
| Form Length | 1 page |
| Fillable? | No |
| Fillable fields | 0 |
| Avg. time to fill out | 3 min |
| Edition | 11/2021 |
| Where to send | Florida Department of Health VFC Program, Immunization Section |
| Matches the agency's file | Yes, checked October 2, 2026 |
| Other names | Vaccine Usage Worksheet, VFC Vaccine Usage Worksheet, Florida VFC worksheet, VFC worksheet |
| Official source | Vaccine Usage Worksheet (Rev 11/2021), Florida Department of Health |
Vfc Vaccine Usage Worksheet Form isn’t the one you’re looking for?