Vita Flex Fsa Medical Claim Form PDF Details

The VitaFlex Dependent Care Flexible Spending Account Expense Claim Form plays a critical role for employees in managing the financial aspects of dependent care. Designed to facilitate the reimbursement for care expenses from the flexible spending account (FSA), this document requires detailed employee data, including company name, employee identification, as well as comprehensive dependent information. Each section of the form meticulously gathers all necessary details such as the full name, date of birth, and relationship of the dependent to the employee, aiming to ensure that all claims are legitimate and within the guidelines set by the plan. The form also emphasizes the importance of provider information, charges for care, and specifically allows for an easy submission process by accepting provider's details and signatures or a receipt in lieu thereof. This substantiation is crucial in certifying that the claimed expenses are for valid dependent care services that were incurred by an eligible participant under the plan. The form includes stern declarations from the employee, asserting that the expenses claimed have not been reimbursed by any other means and acknowledging their responsibility for the accuracy of the submitted information. Such declarations protect against fraudulent claims, safeguarding both the employer's and the employee's interests. Additionally, the form provides sections for updating contact information, ensuring that communication channels remain open and efficient. For expedient processing, it offers multiple submission options, including fax and email, demonstrating a blend of stringent verification processes with user-friendly operational measures.

QuestionAnswer
Form NameVita Flex Dependent Care FSA Claim Form
Form Length1 page
Fillable?Yes
Fillable fields28
Avg. time to fill out15 sec
Other namesvitaclaim dependent flexible spending account, vitaflex login, vita flex login, vita flex medical reimbursement form

How to Fill Out Dependent Care FSA Expense Claim Form

Dependent Care FSA Expense Claim Form at a glance

What it is: The Dependent Care FSA Expense Claim Form substantiates a claim for dependent care.

Who signs: Sign on Employee Signature and enter the Date.

Where and when to file: Online: www.vitaflex.net E-mail: claims@vitamail.com. Fax: Vita Flex Claims Dept. (650) 964-FLEX (3539) (866) 964-FLEX (3539). Mail: Vita Flex Claims Dept. 1451 Grant Road, #200 Mountain View, CA 94040.

A filled-in Dependent Care FSA Expense Claim Form example: a parent claims June care for two children
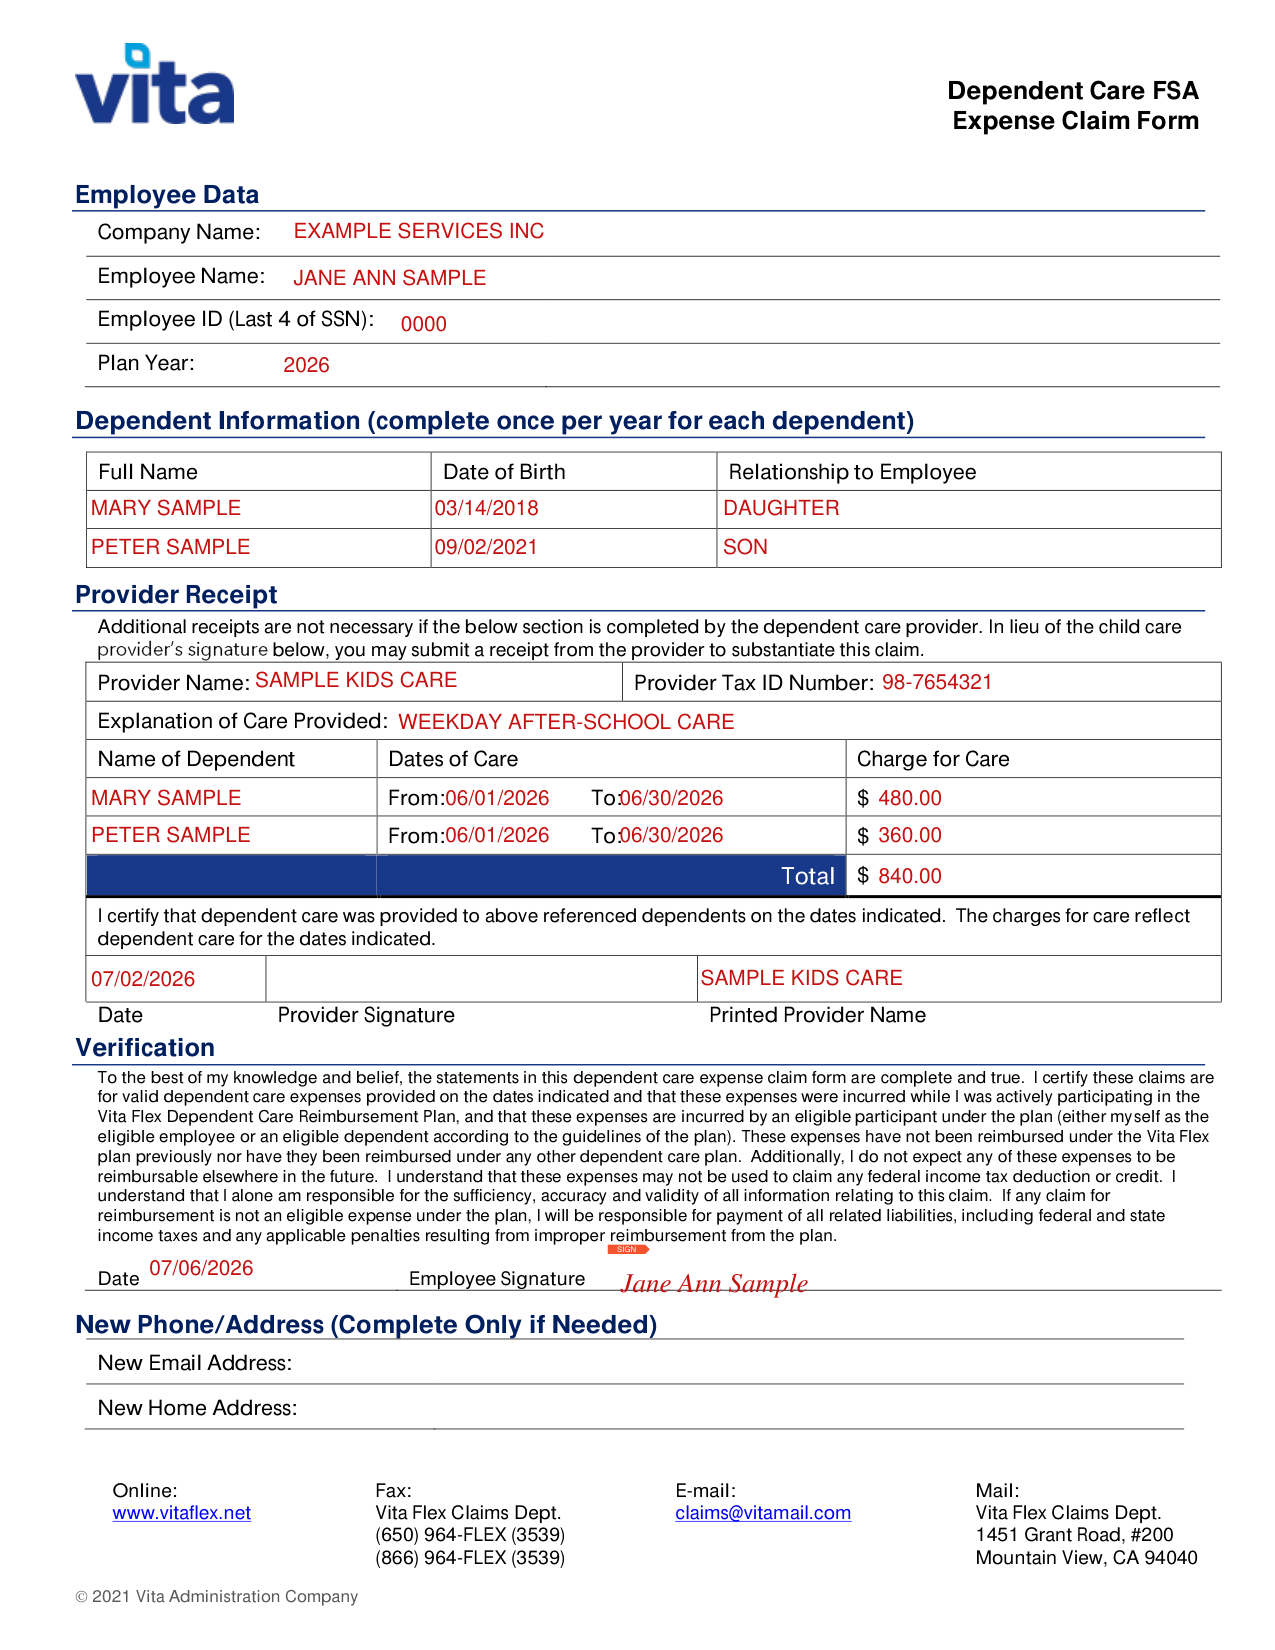
Dependent Care FSA Expense Claim Form example filled out, example: a parent claims June care for two children
Jane Ann Sample files a Vita Flex dependent care expense claim. She claims June 2026 care for two children, and their provider completed the Provider Receipt section. The picture shows page 1, and every value in it is made up. Each charge is the provider's charge for the dates shown, and the Total is the sum of the two charges. Nothing goes in New Phone/Address because her contact details have not changed.

How to fill out Dependent Care FSA Expense Claim Form, box by box

Employee Data

Dependent Care FSA Expense Claim Form example filled out, employee Data

Under Employee Data, enter the Company Name, the Employee Name, the Employee ID (Last 4 of SSN) and the Plan Year.

Dependent Information

Dependent Care FSA Expense Claim Form example filled out, dependent Information

Under Dependent Information, complete once per year for each dependent: Full Name, Date of Birth and Relationship to Employee.

Provider Receipt

Dependent Care FSA Expense Claim Form example filled out, provider Receipt

Additional receipts are not necessary if the section is completed by the dependent care provider; in lieu of that, you may submit a receipt from the provider to substantiate this claim.

Under Provider Receipt, enter the Provider Name, the Provider Tax ID Number and the Explanation of Care Provided.

For each dependent, enter the Name of Dependent, the Dates of Care From and To, and the Charge for Care in $, then the Total $.

Provider Signature and Printed Provider Name

Dependent Care FSA Expense Claim Form example filled out, provider Signature and Printed Provider Name

The provider certifies that dependent care was provided to the dependents on the dates indicated, and that the charges for care reflect dependent care for the dates indicated; with the Date, Provider Signature and Printed Provider Name.

Date and Employee Signature
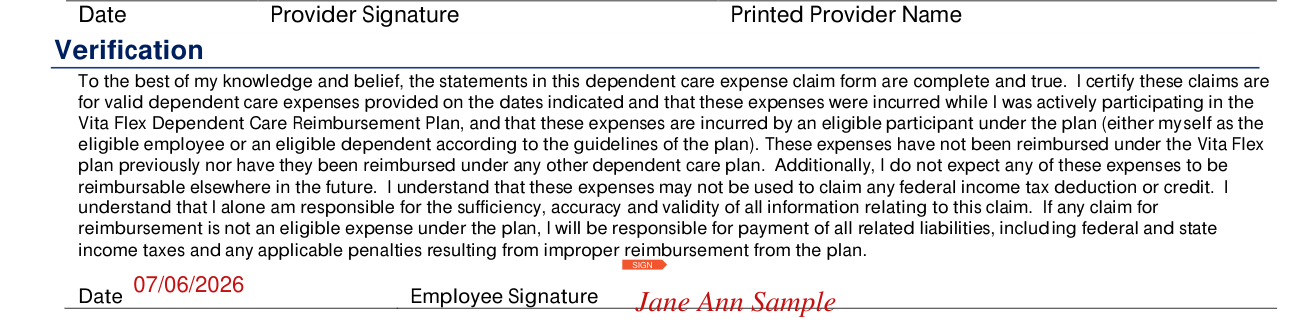
Dependent Care FSA Expense Claim Form example filled out, date and Employee Signature

To the best of your knowledge and belief, the statements in this dependent care expense claim form are complete and true. You certify these claims are for valid dependent care expenses provided on the dates indicated and that these expenses were incurred while you were actively participating in the Vita Flex Dependent Care Reimbursement Plan, and that these expenses are incurred by an eligible participant under the plan (either you as the eligible employee or an eligible dependent according to the guidelines of the plan). These expenses have not been reimbursed under the Vita Flex plan previously nor have they been reimbursed under any other dependent care plan. Additionally, you do not expect any of these expenses to be reimbursable elsewhere in the future. You understand that these expenses may not be used to claim any federal income tax deduction or credit. You understand that you alone are responsible for the sufficiency, accuracy and validity of all information relating to this claim. If any claim for reimbursement is not an eligible expense under the plan, you will be responsible for payment of all related liabilities, including federal and state income taxes and any applicable penalties resulting from improper reimbursement from the plan.

Sign on Employee Signature and enter the Date.

New Phone/Address

Dependent Care FSA Expense Claim Form example filled out, new Phone/Address

Complete New Phone/Address only if needed: the New Email Address and the New Home Address.

Common questions about Dependent Care FSA Expense Claim Form

Where do I file it?

Mail: Vita Flex Claims Dept. 1451 Grant Road, #200 Mountain View, CA 94040.

Sources

[1] Dependent Care FSA Expense Claim Form, Vita Flex (the Official source link on this page).

Please rate Vita Flex Fsa Medical Claim Form 2021 Vita Administration Company

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .