

Washington Practitioner Application at a glance
What it is: Washington Practitioner Application (WPA): send a copy of the completed application when a request is received, making sure that all information is complete, current and accurate.
Who signs: Please sign and date pages 11 and 13.
What to bring and attach to Washington Practitioner Application
This form should be typed or legibly printed in black or blue ink. If more space is needed than provided on original, attach additional sheets and reference the question being answered. Please do not use abbreviations. Current copies of the following documents must be submitted with this application: (all are required for MDs, DOs; as applicable for other health practitioners). DEA Certificate. Face Sheet of Professional Liability Policy or Certificate.
Curriculum Vitae (Not an acceptable substitute for completing the application. Dates need to be listed in mm/yyyy Format). All sections must be completed in their entirety.
Attach copies of requested documents each time the application is submitted.
A filled-in Washington Practitioner Application example: a practitioner fills out page 1
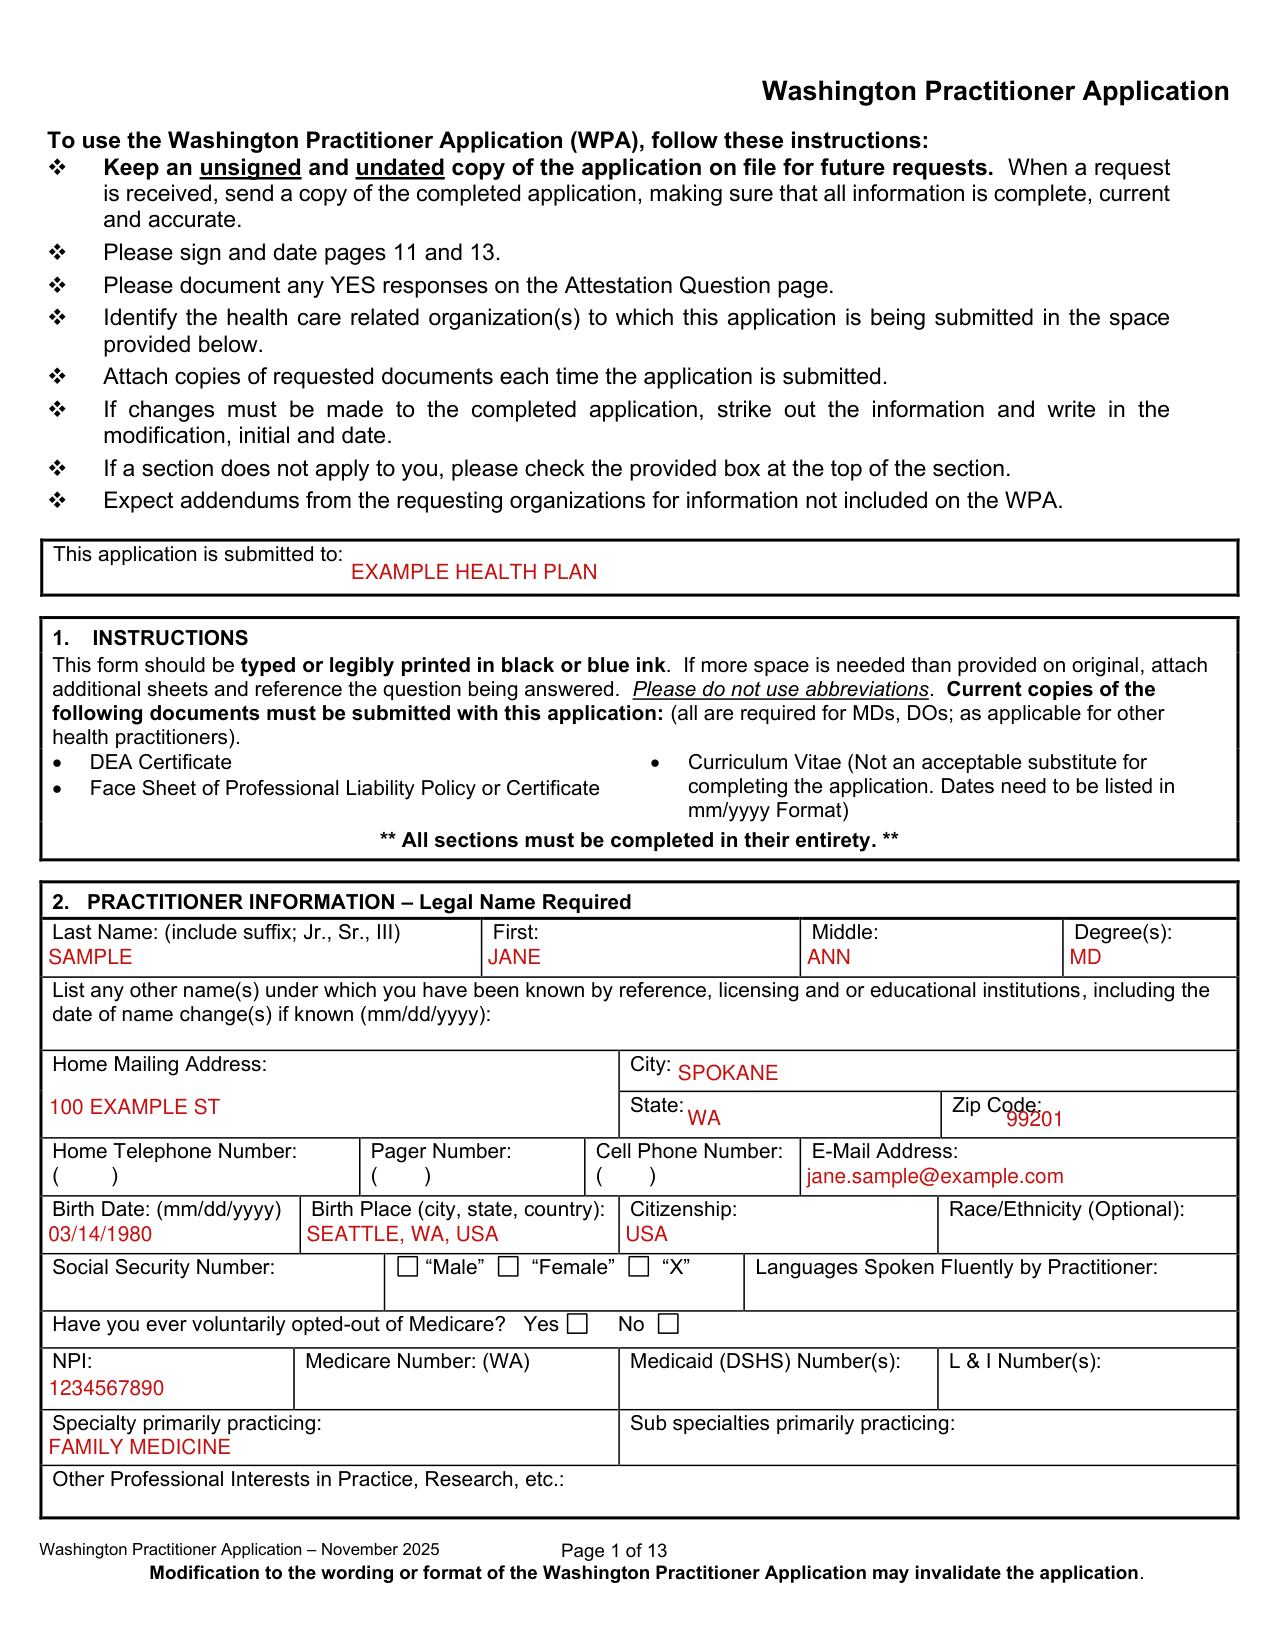
How to fill out Washington Practitioner Application, box by box
Practitioner information: legal name

Enter your legal name: Last Name (include suffix; Jr., Sr., III), First, Middle and Degree(s).
List any other name(s) under which you have been known by reference, licensing and or educational institutions, including the date of name change(s) if known (mm/dd/yyyy).
Home Mailing Address and E-Mail Address
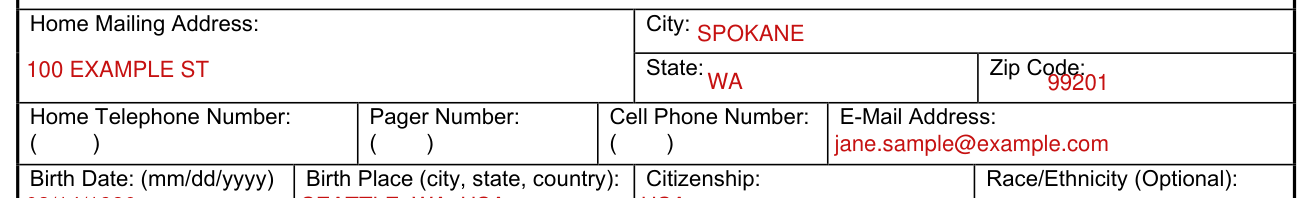
Enter the Home Mailing Address, City, State, Zip Code and E-Mail Address.
Birth Date, Birth Place and Citizenship
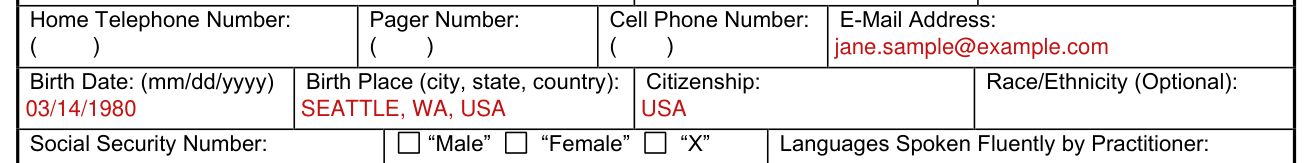
Enter the Birth Date (mm/dd/yyyy), Birth Place (city, state, country), Citizenship and Race/Ethnicity (Optional).
NPI and Specialty primarily practicing

Enter the NPI, Medicare Number (WA), Medicaid (DSHS) Number(s) and L & I Number(s).
Enter the Specialty primarily practicing and the Sub specialties primarily practicing.
This application is submitted to

Identify the health care related organization(s) to which this application is being submitted in the space provided: This application is submitted to.
More rules for Washington Practitioner Application
Keep an unsigned and undated copy of the application on file for future requests.
Please document any YES responses on the Attestation Question page.
If changes must be made to the completed application, strike out the information and write in the modification, initial and date.
If a section does not apply to you, please check the provided box at the top of the section.
Expect addendums from the requesting organizations for information not included on the WPA.
List at least three professional references, from your specialty area, not including relatives, who have worked with you in the past two years.
If you have been out of residency or fellowship for a period of less than three years, one reference must be from the Program Director. Allied Health Providers must provide at least one reference from their same discipline.
Please account for all gaps between dates of medical/professional school graduation to present not covered elsewhere within this application.
Chronologically list all work history activities since completion of professional training (use extra sheets if necessary). This information must be complete. Curriculum vitae is not sufficient.
Please answer all of the following questions. If your answer to any of the following questions is 'Yes", provide details as specified on a separate sheet. If you attach additional sheets, sign and date each sheet.
Photocopy the Professional Liability Action Detail page as needed and submit a separate page for EACH claim/event. A legible signed practitioner narrative that addresses all of the details is an acceptable alternative.
I understand that any material misstatements in, or omissions from, this statement constitute cause for denial of membership or cause for summary dismissal from the entity to which this statement has been submitted.
Common questions about Washington Practitioner Application
Who signs it?
Sign on the Signature line; a stamped signature is not acceptable.
Sources
[1] Washington Practitioner Application (November 2025), Washington Practitioner Application form (the Official source link on this page).
