


Form C-86 at a glance
What it is: Form C-86 is a Motion that parties to the claim requesting a decision by BWC or the Ohio Industrial Commission (IC) must use if any other form or application does not apply.
Who signs: Sign on the Signature of applicant line and enter the Date.
Parties to the claim include the injured worker, employer and/or their authorized representatives, and BWC.
A filled-in Form C-86 example: an injured worker asks for temporary total compensation
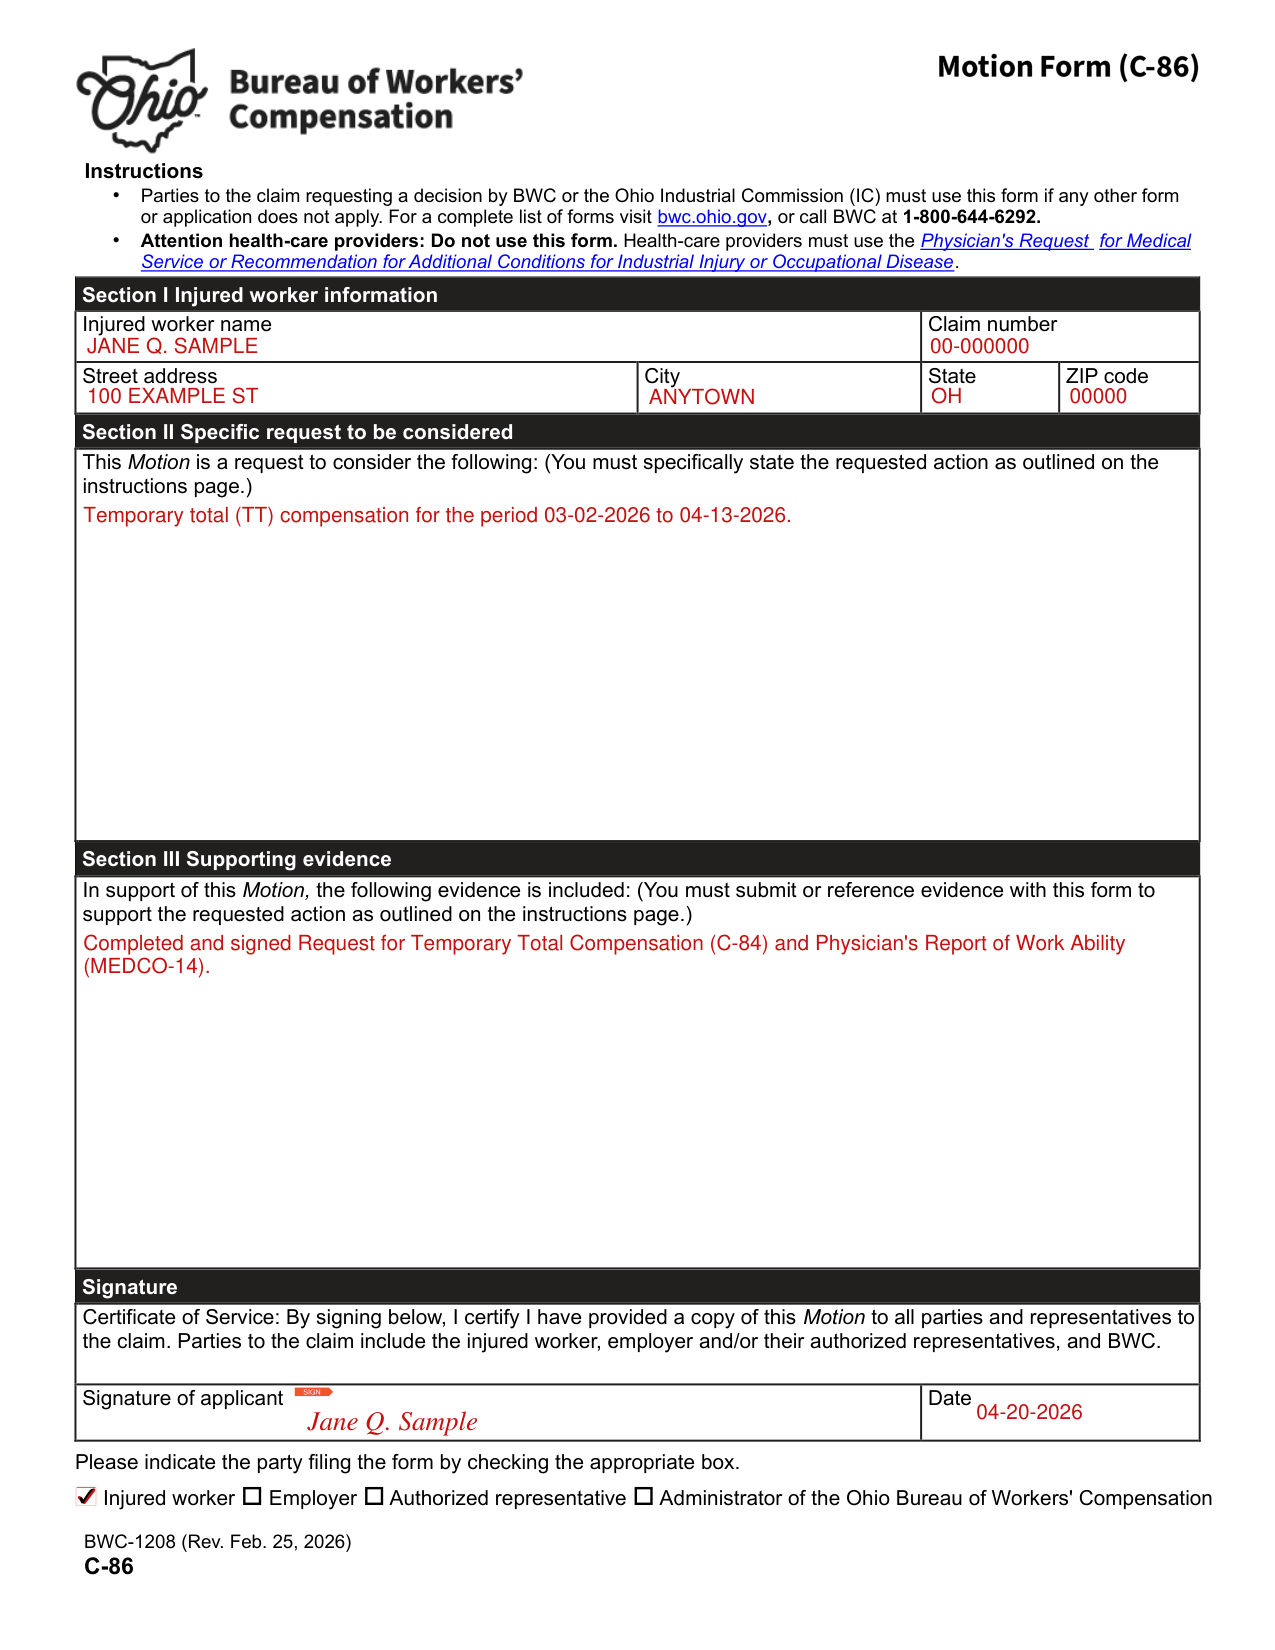
How to fill out Form C-86, box by box
Injured worker information

In Section I, Injured worker information, complete demographic information.
Enter the Injured worker name and Claim number, then the Street address, City, State and ZIP code.
Specific request to be considered
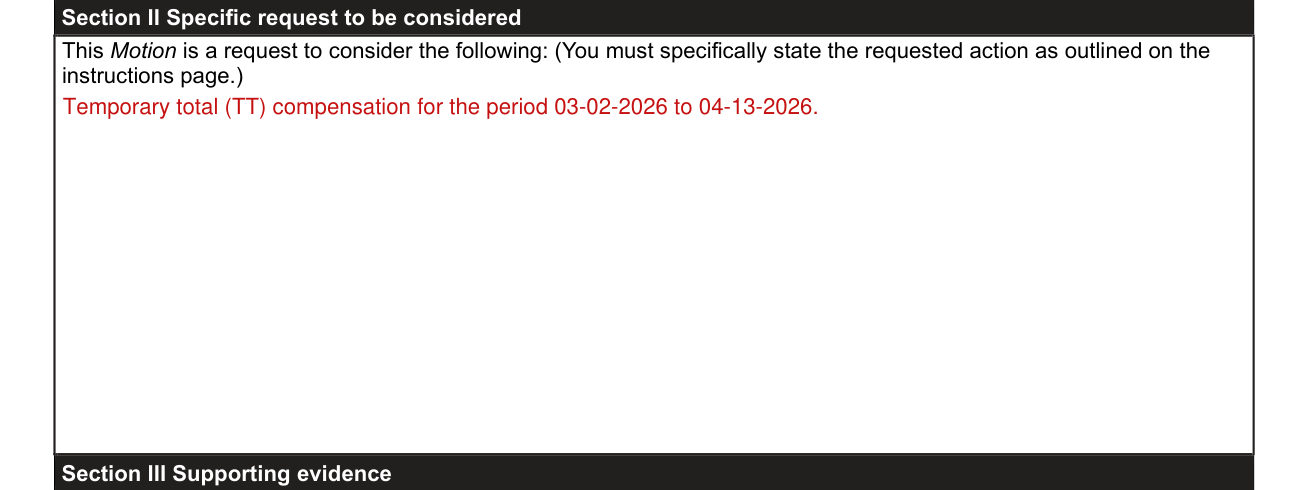
You must specifically state the requested action.
For an additional condition(s), please state the diagnosis of the medical condition(s) you wish BWC or the Industrial Commission of Ohio (IC) to consider.
If requesting a psychiatric or psychological condition, please include the statement: I am aware this motion is requesting that this claim be additionally recognized for a psychiatric or psychological condition that is a result of the injury for which the claim is allowed.
For temporary total (TT) compensation, please state the period for which you are requesting TT.
For wage adjustment, please state the current wage amount and the amount you want adjusted.
For a self-insured claim dispute, please state the issue you dispute, such as payment of medical bills compensation, authorization of treatment, allowance of medical condition, etc.
For any other issue, please state in detail the specific action you wish BWC or the IC to consider.
Injured worker's signature and date for a psychiatric or psychological condition

The statement about a psychiatric or psychological condition must be signed and dated by the injured worker: sign on the Injured worker's signature line and enter the Date.
Supporting evidence

In Section III, under "In support of this Motion the following evidence is included", you must submit or reference evidence with this form to support the requested action as outlined on the instructions page.
For an additional condition(s), please indicate documentation on file that supports your request, or attach medical documentation such as medical reports, which includes a physician statement addressing the causal relationship between the requested diagnosis and the work-related injury, diagnostic test results, radiology exam results, operative reports, etc.
If you are requesting the addition of a pre-existing condition that has been aggravated by the work-related injury, you must clearly identify it as an aggravation or substantial aggravation (depending on the date of injury) of the specific pre-existing condition.
If the date of injury is on or after Aug. 25, 2006, (substantial aggravation), you must provide objective diagnostic findings, objective clinical findings, or objective test results that show the specific pre-existing condition has substantially worsened due to the work-related injury.
If the date of injury is before Aug. 25, 2006, you must provide objective or subjective evidence or both that show aggravation, i.e., some real adverse effect on the specific pre-existing condition.
For TT, please include a completed and signed Request for Temporary Total Compensation (C-84), Physician's Report of Work Ability (MEDCO-14) or equivalent form, and any additional evidence to support your request.
For a wage adjustment, please indicate documentation on file that supports your request, or attach earning statements, pay stubs, a wage statement form, a payroll report, a W-2 or other tax forms, etc.
For a self-insured claim dispute, please indicate documentation on file that supports your request, or attach copies of authorization requests, medical bills, or other evidence.
For any other request, please indicate documentation on file that supports your request or attach specific evidence that supports the action you wish taken.
Certificate of Service and signature

By signing, I certify I have provided a copy of this Motion to all parties and representatives to the claim.
Sign on the Signature of applicant line and enter the Date.
The party filing the form

Please indicate the party filing the form by checking the appropriate box: Injured worker, Employer, Authorized representative or Administrator of the Ohio Bureau of Workers' Compensation.
More rules for Form C-86
For a complete list of forms visit bwc.ohio.gov, or call BWC at 1-800-644-6292.
Common questions about Form C-86
When is this form not the right one?
Health-care providers: Do not use this form. Health-care providers must use the Physician's Request for Medical Service or Recommendation for Additional Conditions for Industrial Injury or Occupational Disease. Do not use this form to file an appeal to a BWC or IC hearing order. Use Notice of Appeal (IC-12).
Sources
[1] Form C-86 (Rev. Feb. 25, 2026), Motion, Ohio Bureau of Workers' Compensation (the Official source link on this page).