

Form F-03211 at a glance
What it is: Form F-03211 (07/2026) is the Wisconsin Nurse Aide Registry Renewal Form for renewing your Wisconsin nurse aide certification.
Where and when to file: Section I - Nurse aide information: The nurse aide must complete this section of the form. Next, complete Section II or Section III. Section II - Employer information (Facility/Provider): The actual designated representative of the facility/provider where work was performed must complete this section of the form. Section III - Renewal via out of state reciprocity: Renew your Wisconsin certification via active, out of state registry status. Return the completed forms via fax or email to: 608-226-5524 or dhswidqa_natcep@dhs.wisconsin.gov.
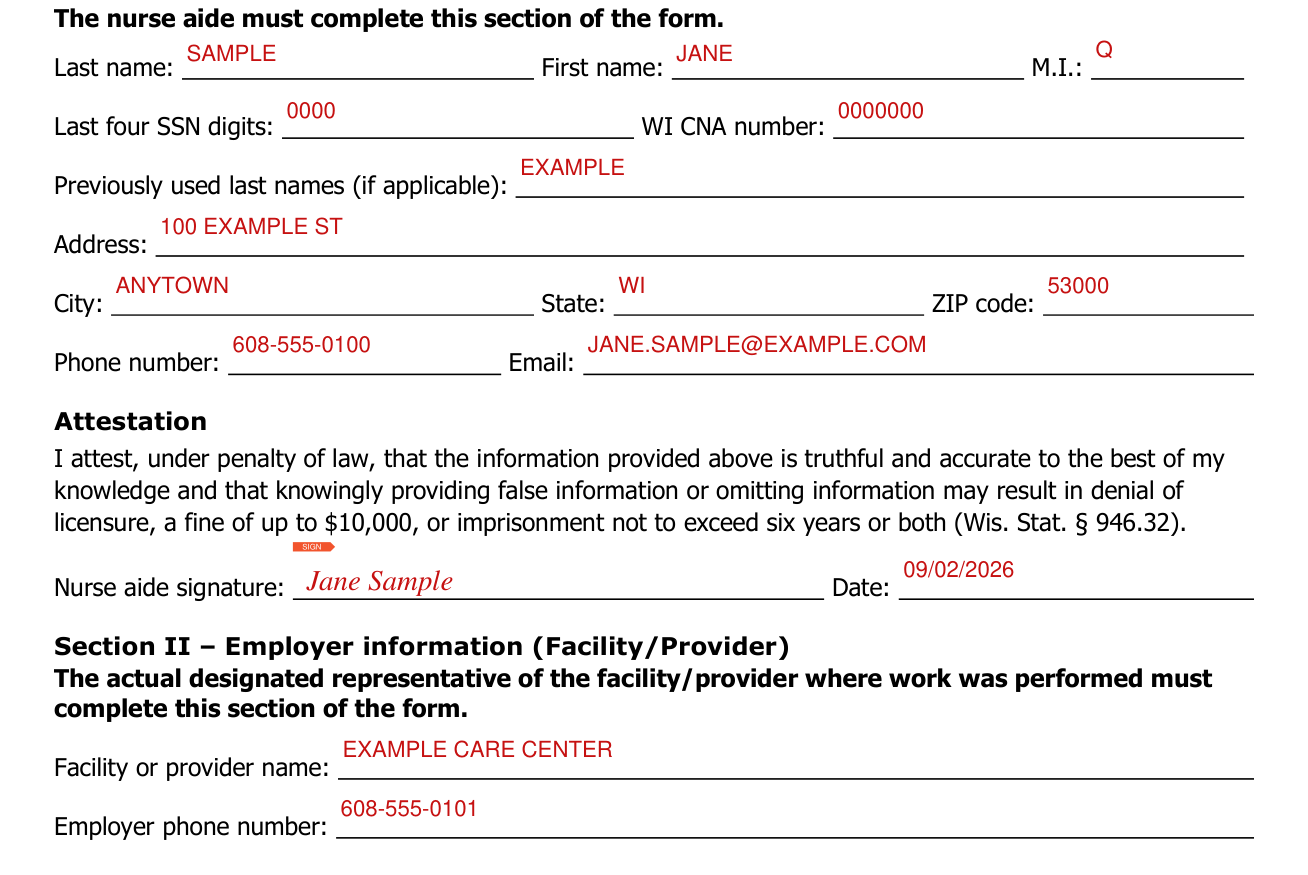
A filled-in Form F-03211 example: a nurse aide renews with an employer's certification

How to fill out Form F-03211, box by box
Section I - Nurse aide information
Only use this form if your employer is not listed as an eligible employer in your TMU account.
If you need assistance, call 608-261-9315 or email dhswidqa_natcep@dhs.wisconsin.gov.
Enter Last name, First name, M.I., Last four SSN digits, WI CNA number, Previously used last names (if applicable), Address, City, State, ZIP code, Phone number and Email. By signing you attest, under penalty of law, that the information provided in Section I is truthful and accurate to the best of your knowledge and that knowingly providing false information or omitting information may result in denial of licensure, a fine of up to $10,000, or imprisonment not to exceed six years or both (Wis. Stat. § 946.32) (checked November 8, 2026). Then sign in Nurse aide signature and enter the Date. The Facility or provider name and Employer phone number boxes are part of Section II - Employer information (Facility/Provider), which the actual designated representative of the facility/provider where work was performed must complete.
Section II - Employer information (Facility/Provider)
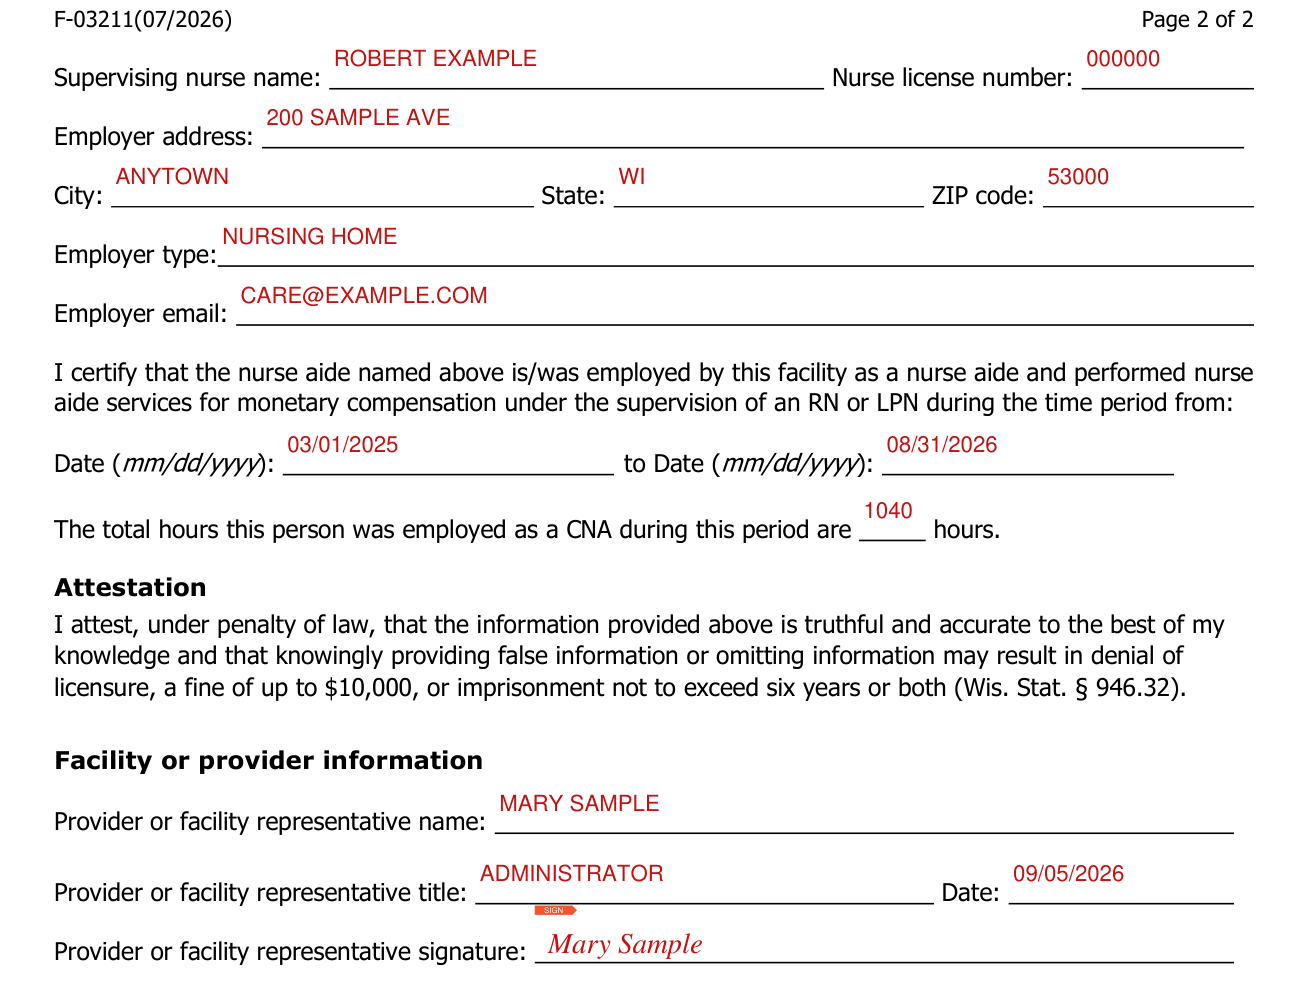
Enter the Supervising nurse name, Nurse license number, Employer address, City, State, ZIP code, Employer type and Employer email. Then enter the two Dates (mm/dd/yyyy) of the period and the total hours the person was employed as a CNA during it.
By signing you certify that the nurse aide named in Section I is/was employed by this facility as a nurse aide and performed nurse aide services for monetary compensation under the supervision of an RN or LPN during the time period set by the two Dates (mm/dd/yyyy) you enter, and that the total hours this person was employed as a CNA during that period are the hours you enter.
Under Facility or provider information, enter the Provider or facility representative name, Provider or facility representative title, Date and Provider or facility representative signature.
Section III - Renew via out of state reciprocity

Section III - Renew your Wisconsin nurse aide certification via out of state reciprocity (active status on another state's nurse aide registry).
List states where you hold active nurse aide registry status and include the registry number. For each state, enter State, Certification number and Lapse date.
More rules for Form F-03211
Federal and state regulations require that you performed nursing or nursing-related services for pay, under the supervision of a RN or LPN, during and since your last 24-month certification period.
For more information about maintaining or renewing your Wisconsin nurse aide certification visit Nurse Aide Program: Training and Registry | Wisconsin Department of Health Services).
Sources
[1] Form F-03211 (07/2026), Wisconsin Nurse Aide Registry Renewal Form, Wisconsin Department of Health Services (the Official source link on this page).
