


Advance Health Care Directive at a glance
What it is: Advance Health Care Directive under California Probate Code §§ 4600 to 4806.
Who signs: You should sign this document in the presence of two witnesses.
A filled-in Advance Health Care Directive example: a Jehovah's Witness names an agent

How to fill out Advance Health Care Directive, box by box
Your full name

Print or type your full name after I in box 1, to set forth your treatment instructions and to appoint a health-care agent in case of your incapacity.
Regarding end-of-life matters

Regarding end-of-life matters in box 3, initial one of the two choices. (a) I do not want my life to be prolonged if, to a reasonable degree of medical certainty, my situation is hopeless. (b) I want my life to be prolonged as long as possible within the limits of generally accepted medical standards, even if this means that I might be kept alive on machines for years.
Other health-care instructions
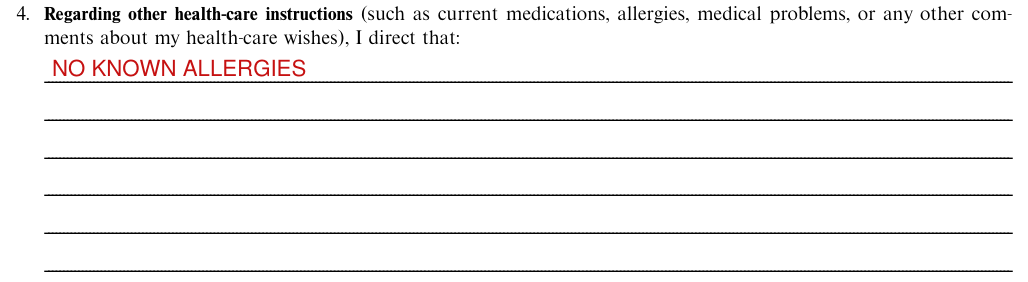
Under box 4, regarding other health-care instructions (such as current medications, allergies, medical problems, or any other comments about your health-care wishes), write what you direct.
Signature, Date and Address

Before signing this document, fill out the entire document (including the names, addresses, and telephone numbers of your health-care agents).
Sign on the Signature line, then write the Date and your Address.
Statement of witnesses

STATEMENT OF WITNESSES: "I declare under penalty of perjury under the laws of California (1) that the individual who signed or acknowledged this advance health care directive above is personally known to me, or that the individual's identity was proven to me by convincing evidence, (2) that the individual signed or acknowledged this advance directive in my presence, (3) that the individual appears to be of sound mind and under no duress, fraud, or undue influence, (4) that I am not the person appointed as the health-care agent or alternate agent by this advance directive, and (5) that I am not the individual's health-care provider, an employee of the individual's health-care provider, the operator of a community care facility, an employee of an operator of a community care facility, the operator of a residential care facility for the elderly, nor an employee of an operator of a residential care facility for the elderly."
Signature of witness / Date, then Address, for each witness.
Additional statement of witnesses

At least one of the witnesses must also sign a declaration: "I further declare under penalty of perjury under the laws of California that I am not related to the individual executing this advance health care directive by blood, marriage, or adoption, and to the best of my knowledge, I am not entitled to any part of the individual's estate upon his or her death under a will now existing or by operation of law."
Special witness requirement

If you are a patient in a skilled nursing facility, one of your witnesses must be a patient advocate or ombudsman and he or she must also sign the Statement of Patient Advocate or Ombudsman: "I declare under penalty of perjury under the laws of California that I am a patient advocate or ombudsman as designated by the State Department of Aging and that I am serving as a witness as required by Section 4675 of the Probate Code."
Health-care agent and alternate health-care agent

Box 6: Apart from the matters covered above, I appoint the person named herein as my agent to make health-care decisions for me. I give my agent full power and authority to consent to or to refuse treatment (including artificial nutrition and hydration) on my behalf, to consult with my doctors and receive copies of my medical records, and to take legal action to ensure that my wishes are honored. If my first appointed agent is unavailable, unable, or unwilling to serve, I appoint an alternate agent herein to serve with the same power and authority.
You may appoint any adult to be your agent except (1) your supervising health-care provider, (2) an operator of a community care facility or residential care facility where you are receiving care, (3) an employee of the health-care institution, community care facility, or residential care facility where you are receiving care, unless the employee is related to you by blood, marriage, or adoption or is your co-worker.
If you are a conservatee under the Lanterman-Petris-Short Act (the law governing involuntary commitment to a mental health facility) and you wish to appoint your conservator as your agent, you must consult a lawyer, who must sign a special certificate.
More rules for Advance Health Care Directive
Box 2: I am one of Jehovah's Witnesses, and I direct that NO TRANSFUSIONS of whole blood, red cells, white cells, platelets, or plasma be given me under any circumstances, even if health-care providers believe that such are necessary to preserve my life. (Acts 15:28, 29) I refuse to predonate and store my blood for later infusion.
Box 5: I give no one (including my agent) any authority to disregard or override my instructions set forth herein. Family members, relatives, or friends may disagree with me, but any such disagreement does not diminish the strength or substance of my refusal of blood or other instructions.
Sources
[1] Advance Health Care Directive (California Probate Code 4600 to 4806) (the served file; no issuer file found) (the Official source link on this page).