
X Ray Form Chiropractic PDF Details

The X-Ray Chiropractic Form from Life Chiropractic College West Health Center embodies a crucial aspect of patient care in the chiropractic field, streamlining the process for both the healthcare providers and the patients. This comprehensive document captures essential patient information including their name, date of birth, and the attending field doctor's details, alongside the doctor's signature and contact information. It mandates complete details for scheduling, including preferred days and times for the patient, ensuring direct coordination with the office to facilitate appointments efficiently. A notable feature is the inclusion of a variety of X-ray requests, from plain film and digital X-rays to specific requests for a DACBR report, each with detailed specifications for different parts of the body such as cervical, thoracic, and lumbo-pelvic areas. The form also outlines the financial responsibilities, indicating a fee for no-shows and payment options that include billing the doctor's credit card on file or having the patient pay on the day of service. Additionally, there's a sensitive acknowledgment of patient safety with a requirement for female patients to confirm the absence of pregnancy before undergoing any X-ray procedure. This diligent approach underscores the commitment to patient care, safety, and efficient administrative handling within the chiropractic health service framework.

QuestionAnswer
Form NameX Ray Form Chiropractic
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other nameschiropractic x ray order form, x ray request chiropractic form, x ray form west, x form chiropractic template

How to Fill Out X-Ray Request Form

X-Ray Request Form at a glance

What it is: Life Chiropractic College West Health Center X-Ray Request Form.

Where and when to file: FAX this form to Life Chiropractic College West Health Center at (510) 780-4511.

A filled-in X-Ray Request Form example: a doctor requests a lumbar X-ray

X-Ray Request Form example filled out, example: a doctor requests a lumbar X-ray
Dr. Jane Sample fills out the X-ray request for a patient. She orders lumbar AP,LAT (2 views) on plain film and bills her card on file. Nothing goes in Ankle, foot, knee, hand, wrist, elbow, shoulder, hip and other X rays because this request is for the lumbar spine. The picture shows the doctor's part and every value in it is made up.

How to fill out X-Ray Request Form, box by box

Patient, Dr. and mailing address

X-Ray Request Form example filled out, patient, Dr. and mailing address

Fill out all fields, list best days and time ranges for patient.

Write the Patient Name, mark M/F and enter the DOB.

Enter the Field Dr., the Field DR. Acct#, the Mailing address, the Dr. Signature and the Dr Telephone #.

Bill and Plain Film or Digital X-ray

X-Ray Request Form example filled out, bill and Plain Film or Digital X-ray

Mark Bill Doctor's credit card on file or Patient to pay on day of service.

Mark Plain Film X-ray, Digital X-ray (CD for computer) or Request for DACBR report. Note: Billed separately by mail.

Cervical, thoracic and lumbo-pelvic X rays
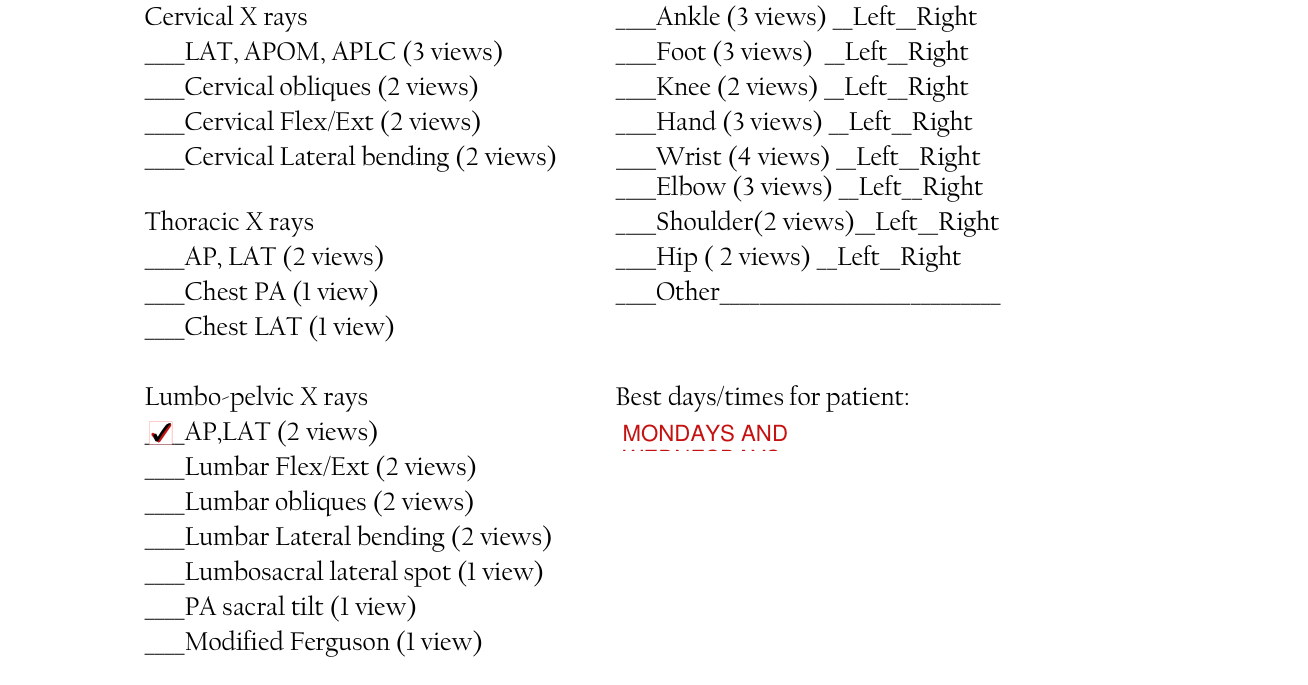
X-Ray Request Form example filled out, cervical, thoracic and lumbo-pelvic X rays

Under Cervical X rays, mark LAT, APOM, APLC (3 views), Cervical obliques (2 views), Cervical Flex/Ext (2 views) or Cervical Lateral bending (2 views).

Under Thoracic X rays, mark AP, LAT (2 views), Chest PA (1 view) or Chest LAT (1 view).

Under Lumbo-pelvic X rays, mark AP,LAT (2 views), Lumbar Flex/Ext (2 views), Lumbar obliques (2 views), Lumbar Lateral bending (2 views), Lumbosacral lateral spot (1 view), PA sacral tilt (1 view) or Modified Ferguson (1 view).

Ankle, foot, knee, hand, wrist, elbow, shoulder, hip and other X rays

X-Ray Request Form example filled out, ankle, foot, knee, hand, wrist, elbow, shoulder, hip and other X rays

Mark Left or Right for Ankle (3 views), Foot (3 views), Knee (2 views), Hand (3 views), Wrist (4 views), Elbow (3 views), Shoulder (2 views) and Hip (2 views); for Other, write the X-ray.

Best days and times and the total number of views
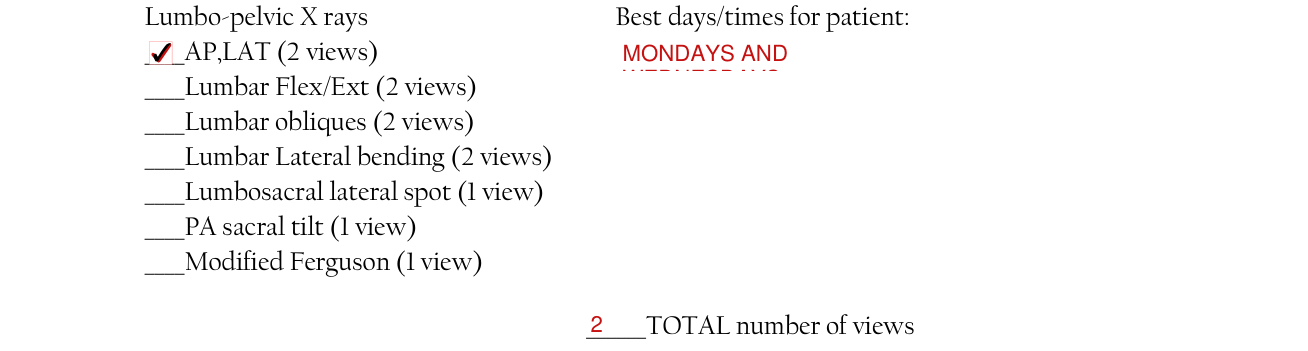
X-Ray Request Form example filled out, best days and times and the total number of views

Write the Best days/times for patient.

Write the TOTAL number of views.

Patient Signature and Female Patients

X-Ray Request Form example filled out, patient Signature and Female Patients

For use on day of x ray only by LCCW faculty: Female Patients: There is no possibility that I am pregnant today.

For use on day of x ray only by LCCW faculty: Patient Signature, Date.

More rules for X-Ray Request Form

Please do not write in the Appointment scheduled for: Date, Time lines.

Common questions about X-Ray Request Form

Where do I file it?

FAX this form to Life Chiropractic College West Health Center at (510) 780-4511. Life Chiropractic College West Health Center will schedule with your office directly. Its phone is 510 780-4559.

Are there fees?

A $25.00 fee may be charged if your patient fails to show up for their appointment. (checked November 9, 2026)

Sources

[1] Life Chiropractic College West Health Center X-Ray Request Form (the served file; no issuer file found) (the Official source link on this page).