


Reinstatement Application for Individual Life Insurance (ICC15-108250) at a glance
What it is: This is the Reinstatement Application for Individual Life Insurance.
Who signs: Under Owner Signature, the Owner signs and enters Title (If Corporate Officer or Trustee), Owner signed at (city, state) and Owner signed on (date).
A filled-in Reinstatement Application for Individual Life Insurance (ICC15-108250) example: a policyholder fills out page 1

How to fill out Reinstatement Application for Individual Life Insurance (ICC15-108250), box by box
Company, mailing and policy numbers

Mark the insurance company: American General Life Insurance Company or The United States Life Insurance Company in the City of New York. Send form(s) to P.O. Box 818005, Cleveland, OH 44181. Fax form(s) to 855-601-1834.
Enter the Policy Number(s).
A. PRIMARY INSURED

Under A. PRIMARY INSURED, enter First Name, MI, Last Name and SSN.
Mark Gender M or F, and enter Birthplace and Date of Birth.
Check yes or no for Tobacco Use: Have you ever used any form of tobacco or nicotine products? If yes, enter Type and Quantity used and check yes or no for a current user; if no, enter the date of last use.
Check yes or no for U.S. Citizen or Permanent Resident (Green Card holder). If no, enter Country of Citizenship, Date of Entry and Visa Type (Copy of Visa Required).
Check CHECK HERE IF NEW ADDRESS for a new address, and enter Address, City, State and ZIP.
Enter Primary Phone, Alternate Phone and Email.
Enter Employer, Occupation, Personal Earned Income and Net Worth. Personal Earned Income means monies received for work performed.
B. OTHER INSURED
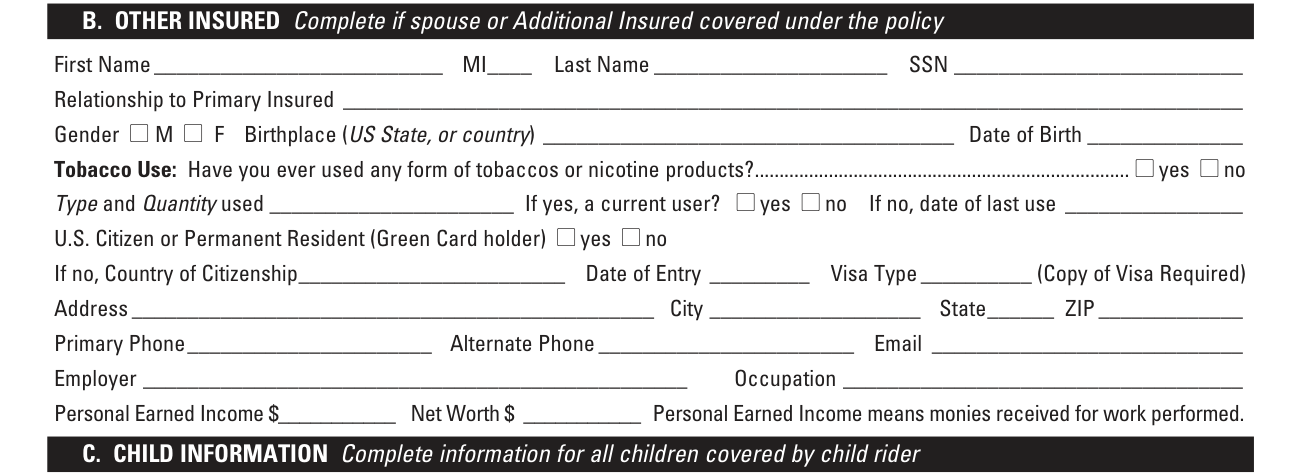
Complete B. OTHER INSURED if spouse or Additional Insured covered under the policy: First Name, MI, Last Name, SSN and Relationship to Primary Insured.
C. CHILD INFORMATION
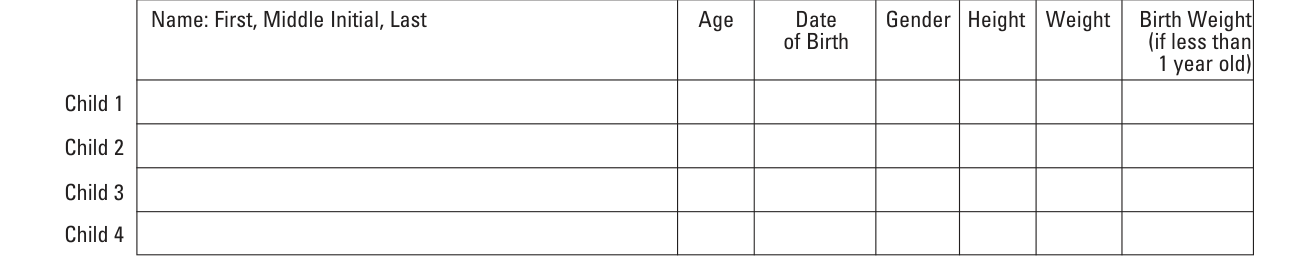
Complete information for all children covered by child rider: Name: First, Middle Initial, Last, Age, Date of Birth, Gender, Height, Weight and Birth Weight (if less than 1 year old), for Child 1, Child 2, Child 3 and Child 4.
If your situation is different
The Primary Insured is not the Owner
Complete D. OWNER INFORMATION if the Primary Insured is not the Owner: First Name, MI, Last Name and SSN/TIN.
If owner is a trust please designate information for the Name, Tax ID, Current Trustee and Date of Trust in the Special Remarks section and complete the Certification of Trust.
If the owner is a business, complete the Business Certification.
SECTION II, A. BACKGROUND INFORMATION
Under SECTION II, A. BACKGROUND INFORMATION - For all covered persons, complete questions 1 through 12 for all proposed insureds who are covered by the polic(ies). If an answer of yes applies to ANY insured provide details.
Check yes or no for each of 1 through 12. 1. Have you ever used cocaine, heroin, methamphetamine, hallucinogens, stimulants or any other habit-forming drug except as prescribed by a medical professional? 2. Have you ever sought or received medical advice, counseling or treatment by a medical professional to discontinue or reduce the use of alcohol or drugs, including prescribed controlled substances? 3. In the past five years, have you pled guilty or been convicted of any driving violations to include driving under the influence of alcohol or drugs? 4. In the past five years, have you flown as a pilot, student pilot or crew member of any aircraft, or have any intention to do so in the next two years? 5. In the past five years, have you engaged in motor sports events or racing (auto, truck, motorcycle, boat, etc.); rock or mountain climbing; skin or scuba diving; aeronautics (hang-gliding, sky diving, parachuting, ultra light, soaring, ballooning,) or have any intention to do so in the next two years? 6. Do you intend to travel or reside outside of the United States or Canada within the next two years? 7. Have you ever requested or received a pension, benefits, or payments because of an injury, sickness, or disability in the past 5 years? 8. Have you ever filed for bankruptcy, or have the intention to seek bankruptcy protection within the next 12 months? 9. Have you ever been convicted of, or currently charged with, a felony or misdemeanor? 10. Is there an intention that any party, other than the Owner or Beneficiary, will obtain any right, title, or interest in any policy issued on the life of any Proposed Insured as a result of this application? 11. Does the Owner or any Proposed Insured intend to finance any of the premium required to pay for this policy through a financing or loan agreement? 12. Is the Owner, any Proposed Insured, or any person or entity, being paid (cash, services, etc) as an incentive to enter into this transaction?
Enter the Details.
B. EXISTING COVERAGE
Under B. EXISTING COVERAGE, check yes or no for question 1: Does any Proposed Insured have any existing life insurance policies? If question 1 is answered “yes”, enter Name of Proposed Insured, Type, Year of Issue, Face Amount, Insurance Company and Contract or Policy #. Type: i= individual, b= business, g= group.
C. MEDICAL INFORMATION
Under C. MEDICAL INFORMATION, enter Height, Weight and Change of weight in last year (None, Gain or Loss) for the Primary Insured and the Other Insured, the Name and address of personal physician, and the Date, reason, findings and treatment at last visit.
Complete questions 4 through 8 for all Proposed Insureds who are covered by this policy. Provide details such as date of first diagnosis, name and address of doctor, tests performed, test results, medication(s) or recommended treatment if an answer of yes applies to ANY insured.
Check yes or no for each of 5, 6, 7 and 8. 5. Other than previously stated, have you taken any medications, had treatment or therapy or been under medical observation within the past 12 months? 6. Have you ever tested positive for the Human Immunodeficiency Virus (HIV) or been diagnosed or treated by a member of the medical profession for Acquired Immune Deficiency Syndrome (AIDS)? 7. Other than previously stated, in the past 5 years, have you been advised by a member of the medical profession concerning any abnormal diagnostic test results, been advised to see a specialist, or been advised to have any diagnostic test, hospitalization, surgery, or treatment that was NOT completed (except for those tests related to the Human Immunodeficiency Virus), or do you have any test results pending?
8. Within the last 5 years have you been treated for or been diagnosed by a member of the medical profession for any other medical, physical, or psychological condition NOT disclosed in C. MEDICAL INFORMATION? Check yes or no and enter Details.
Signing the application
Answers to the questions in this application must be true and complete to the best of your knowledge and belief. Notify the Company of any changes in the statements or answers given in the application between the time of application and delivery of any policy. Any misrepresentation contained in this application and relied on by the Company may be used to reduce or deny a claim or void the policy if: (1) such misrepresentation materially affects the acceptance of the risk; and (2) the policy is within its contestable period.
Check if you wish to be interviewed.
Under IRS Certification, under penalties of perjury, certify that: 1. the number shown on this form is the correct taxpayer identification number; 2. you are not subject to backup withholding; 3. you are a U.S. citizen or other U.S. person; and 4. the FATCA code(s) entered on this form (if any) is correct. Enter the exempt payee code, if applicable.
You must cross out item 2 above if you have been notified by the IRS that you are currently subject to backup withholding because you have failed to report all interest and dividends on your tax return.
Sign Primary Insured Signature (if other than Owner) and Other Insured Signature. If under age 16, a parent or guardian signs. If under age 16 and coverage exceeds $500,000, both parents sign. (checked November 10, 2026)
Sources
[1] Reinstatement Application for Individual Life Insurance, ICC15-108250 Rev1020, American General Life Insurance Company (the Official source link on this page).