
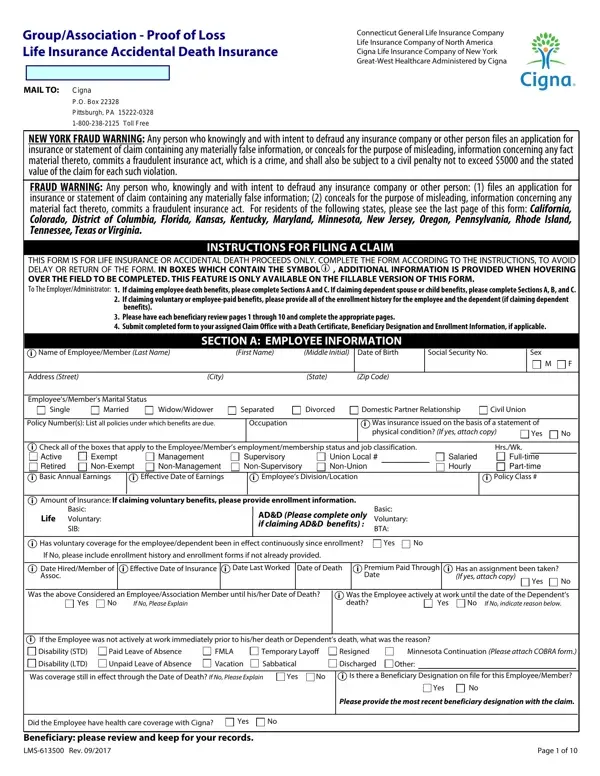

Group/Association Proof of Loss, Life Insurance and Accidental Death (LMS-613500) at a glance
What it is: Group/Association - Proof of Loss Life Insurance Accidental Death Insurance.
Where and when to file: Submit completed form to your assigned Claim Office with a Death Certificate, Beneficiary Designation and Enrollment Information, if applicable.
What to bring and attach to Group/Association Proof of Loss, Life Insurance and Accidental Death (LMS-613500)
If claiming voluntary or employee-paid benefits, please provide all of the enrollment history for the employee and the dependent (if claiming dependent benefits).
Has an assignment been taken? (If yes, attach copy)
Please provide the most recent beneficiary designation with the claim.
A filled-in Group/Association Proof of Loss, Life Insurance and Accidental Death (LMS-613500) example: an employee death claim
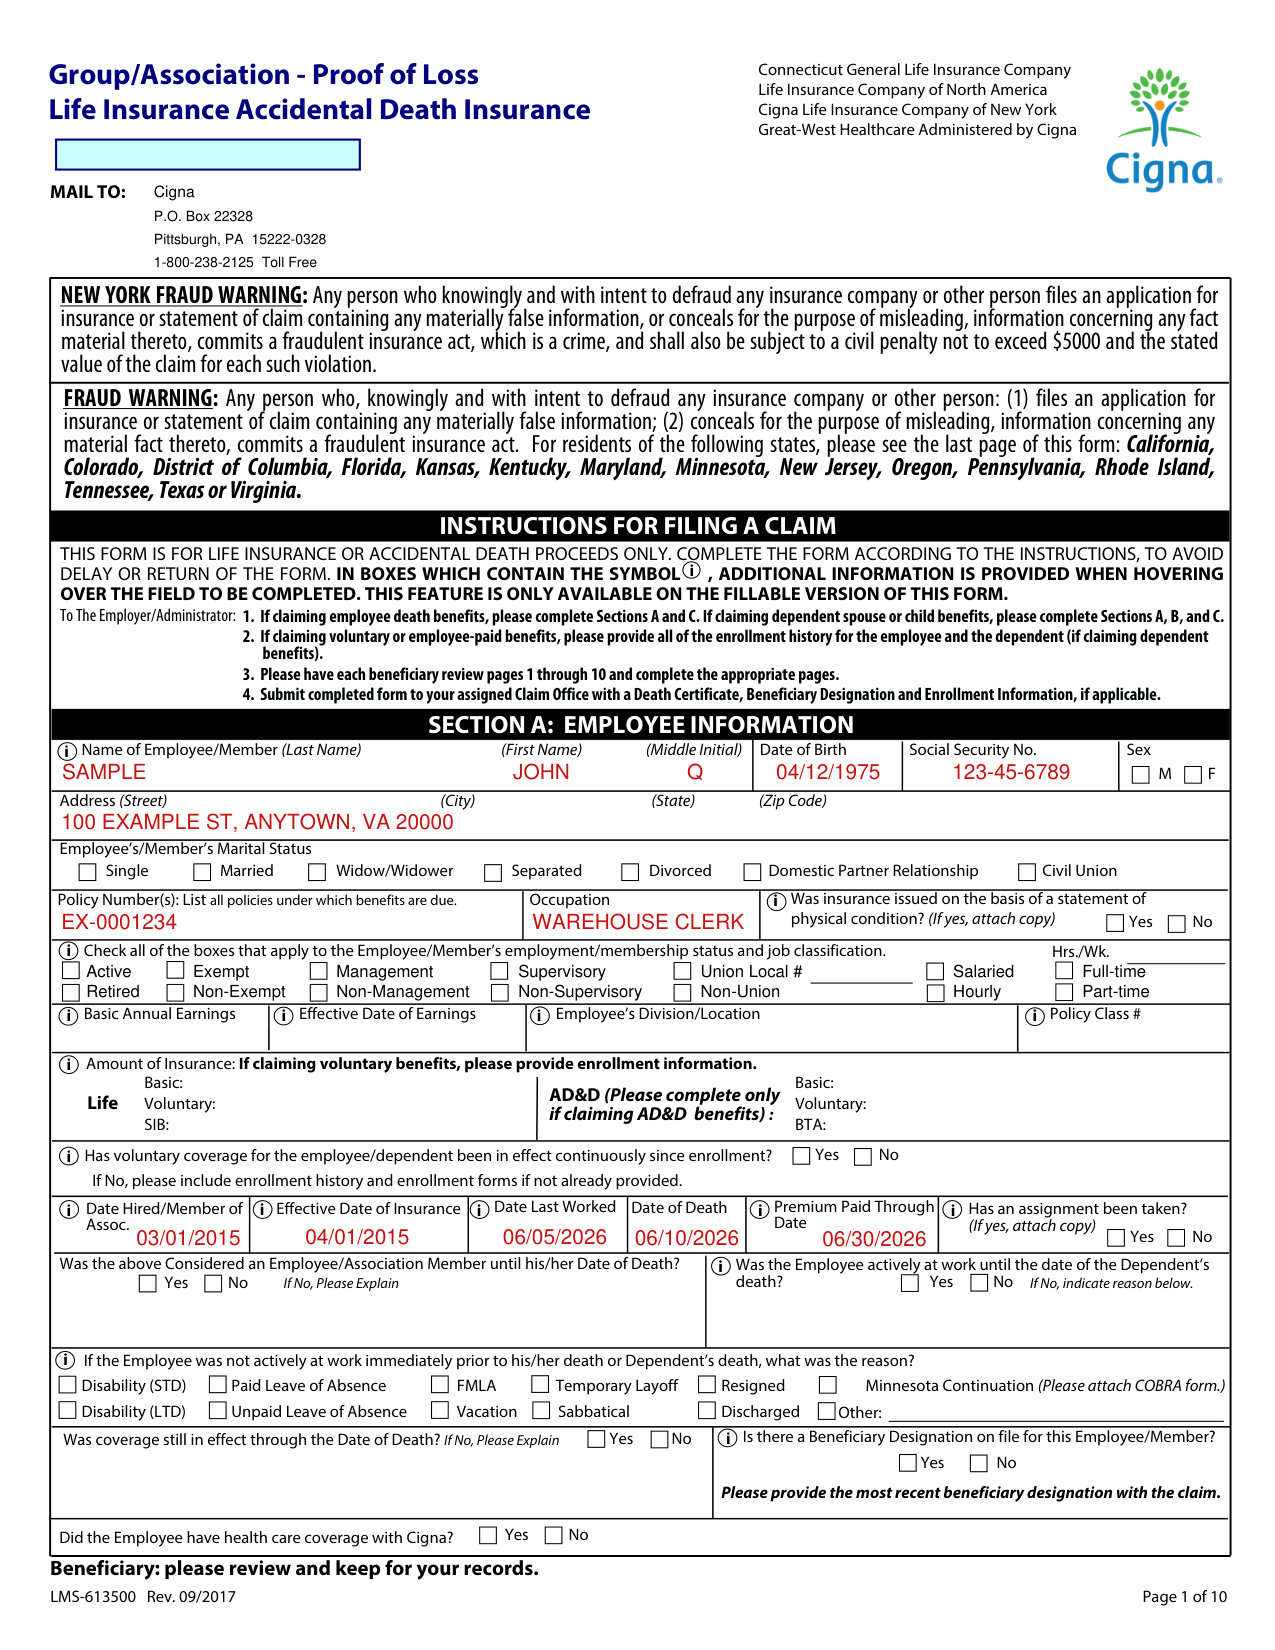
How to fill out Group/Association Proof of Loss, Life Insurance and Accidental Death (LMS-613500), box by box
Section A: Employee Information
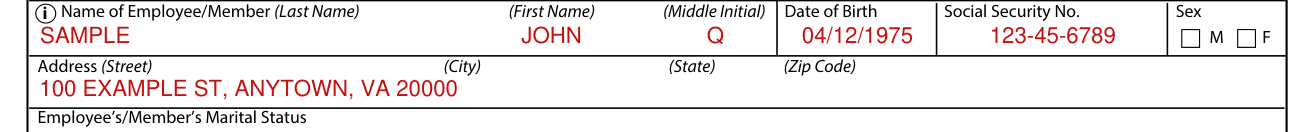
Section A: Employee Information: Name of Employee/Member (Last Name) (First Name) (Middle Initial), Date of Birth, Social Security No. and Address (Street) (City) (State) (Zip Code).
Policy numbers and dates

Policy Number(s): List all policies under which benefits are due. Occupation. Was insurance issued on the basis of a statement of physical condition? (If yes, attach copy)
Date Hired/Member of Assoc., Effective Date of Insurance, Date of Death, Premium Paid Through Date and Date Last Worked.
More rules for Group/Association Proof of Loss, Life Insurance and Accidental Death (LMS-613500)
Check all of the boxes that apply to the Employee/Member's employment/membership status and job classification.
If your insurance benefit is $5,000 or more, Cigna will automatically open a free, interest-bearing account in your name (checked November 9, 2026). If your life insurance benefit is less than $5,000, Cigna will send you a check for the total benefit amount (checked November 9, 2026).
Other situations
Section C: Employer's/Administrator's Certification
Section C: Employer's/Administrator's Certification: Name of Employer/Association, Email Address, Address (Street) City (State) (Zip), Telephone Number, Title, Date and Signature.
This is to certify that the facts as indicated on this form are true to the best of my knowledge and belief.
Accidental death
Section D: Accidental Death Information: Where and How Did the Accident Happen? Please Describe in Detail, and the Date and Time of Accident.
Beneficiary
Please have each beneficiary review pages 1 through 10 and complete the appropriate pages.
Section E: Beneficiary Information: Name of Beneficiary (Last Name) (First Name) (Middle Initial), Date of Birth and Social Security No.
Name and Address of Legal Guardian if Beneficiary is A Minor. If guardianship of the minor's estate has been established, please attach court order.
If claiming voluntary life or basic and/or voluntary AD&D benefits, please list all hospital, clinics or physicians that treated the deceased within the past 5 years.
Beneficiary Signature, Date.
I understand that I can refuse to sign this disclosure authorization; however, if I do so, Company may deny my claim for benefits pursuant to the plan.
Electronic communications
Beneficiary: Please complete and return to the Employer or Cigna if you wish to participate in electronic communications. Do not complete or return this form to the Employer or Cigna if you do not wish to participate in electronic communications.
Life insurance or accidental death proceeds only
This form is for life insurance or accidental death proceeds only. Complete the form according to the instructions, to avoid delay or return of the form. In boxes which contain the symbol, additional information is provided when hovering over the field to be completed. This feature is only available on the fillable version of this form.
Before you go
If claiming employee death benefits, please complete Sections A and C. If claiming dependent spouse or child benefits, please complete Sections A, B, and C.
Common questions about Group/Association Proof of Loss, Life Insurance and Accidental Death (LMS-613500)
Where do I file it?
Mail to: Cigna, P.O. Box 22328, Pittsburgh, PA 15222-0328, 1-800-238-2125 Toll Free.
Is there a penalty?
Rhode Island Residents: Any person who knowingly presents a false or fraudulent claim for payment of a loss or benefit or knowingly presents false information in an application for insurance is guilty of a crime and may be subject to fines and confinement in prison.
Sources
[1] Group/Association - Proof of Loss Life Insurance Accidental Death Insurance (LMS-613500 Rev. 09/2017), Cigna (the Official source link on this page).