

Advance Directive for Health Care at a glance
What it is: Advance Directive for Health Care (Living Will and Health Care Proxy): this form may be used in the State of Alabama to make your wishes known.
Who signs: Section 4. My signature: sign at Your signature. Section 5. Witnesses: two witnesses need to sign.
This form may be used in the State of Alabama to make your wishes known about what medical treatment or other care you would or would not want if you become too sick to speak for yourself.
A filled-in Advance Directive for Health Care example: a woman names her brother and sister as health care proxy

How to fill out Advance Directive for Health Care, box by box
Section 1. Living Will

Fill in the line after I: being of sound mind and at least 19 years old, I would like to make the following wishes known.
At any time you can change your mind about these directions by tearing up this form and writing a new one.
I understand that these directions will only be used if I am not able to speak for myself.
If I become terminally ill or injured

If you become terminally ill or injured: terminally ill or injured is when your doctor and another doctor decide that you have a condition that cannot be cured and that you will likely die in the near future from this condition.
Life sustaining treatment includes drugs, machines, or medical procedures that would keep you alive but would not cure you. Even if you choose not to have life sustaining treatment, you will still get medicines and treatments that ease your pain and keep you comfortable.
Place your initials by either “yes” or “no” for: I want to have life sustaining treatment if I am terminally ill or injured.
Artificially provided food and hydration (Food and water through a tube or an IV): if you are terminally ill or injured you may need to be given food and water through a tube or an IV to keep you alive if you can no longer chew or swallow on your own or with someone helping you.
Place your initials by either “yes” or “no” for: I want to have food and water provided through a tube or an IV, if I am terminally ill or injured.
If I Become Permanently Unconscious

If you become permanently unconscious: permanent unconsciousness is when your doctor and another doctor agree that within a reasonable degree of medical certainty you can no longer think, feel anything, knowingly move, or be aware of being alive.
They believe this condition will last indefinitely without hope for improvement and have watched you long enough to make that decision. At least one of these doctors must be qualified to make such a diagnosis.
Place your initials by either “yes” or “no” for: I want to have life-sustaining treatment if I am permanently unconscious.
Place your initials by either “yes” or “no” for: I want to have food and water provided through a tube or an IV, if I am permanently unconscious.
Other Directions

Other Directions: Please list any other things you want done or not done. In addition to the directions I have listed on this form, I also want the following:
If you do not have other directions, place your initials by No, I do not have any other directions.
Section 2. Health care proxy

This form can be used in the State of Alabama to name a person you would like to make medical or other decisions for you if you become too sick to speak for yourself. This person is called a health care proxy.
You do not have to name a health care proxy. The directions in this form will be followed even if you do not name a health care proxy.
Place your initials by only one answer: I do not want to name a health care proxy. If you check this answer, go to Section 3. I do want the person listed to be my health care proxy. I have talked with this person about my wishes.
Enter First choice for proxy, Relationship to me, Address, City, State, Zip, Day-time phone number and Night-time phone number.
If this person is not able, not willing, or not available to be my health care proxy, this is my next choice: enter Second choice for proxy, Relationship to me, Address, City, State, Zip, Day-time phone number and Night-time phone number.
Instructions for Proxy
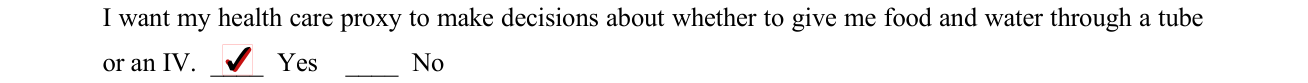
Instructions for Proxy: place your initials by either “yes” or “no” for: I want my health care proxy to make decisions about whether to give me food and water through a tube or an IV.
Place your initials by only one: I want my health care proxy to follow only the directions as listed on this form.
I want my health care proxy to follow my directions as listed on this form and to make any decisions about things I have not covered in the form.
I want my health care proxy to make the final decision, even though it could mean doing something different from what I have listed on this form.
Section 3

Section 3. The things listed on this form are what I want. I understand the following: if my doctor or hospital does not want to follow the directions I have listed, they must see that I get to a doctor or hospital who will follow my directions.
If I am pregnant, or if I become pregnant, the choices I have made on this form will not be followed until after the birth of the baby.
If the time comes for me to stop receiving life sustaining treatment or food and water through a tube or an IV, I direct that my doctor talk about the good and bad points of doing this, along with my wishes, with my health care proxy, if I have one, and with the following people:
Enter the people on the lines.
Section 4. My signature

Section 4. My signature: enter Your name, The month, day, and year of your birth, Your signature and Date signed.
Section 5. Witnesses

Section 5. Witnesses: two witnesses need to sign.
Witnesses: I am witnessing this form because I believe this person to be of sound mind. I did not sign the person's signature, and I am not the health care proxy. I am not related to the person by blood, adoption, or marriage and not entitled to any part of his or her estate. I am at least 19 years of age and am not directly responsible for paying for his or her medical care.
Enter Name of first witness, sign at Signature and enter Date; then enter Name of second witness, sign at Signature and enter Date.
Section 6. Signature of Proxy

Section 6. Signature of Proxy: I am willing to serve as the health care proxy. Signature and Date.
Signature of Second Choice for Proxy: I am willing to serve as the health care proxy if the first choice cannot serve. Signature and Date.
More rules for Advance Directive for Health Care
You are not required to have an advance directive. If you do have an advance directive, be sure that your doctor, family, and friends know you have one and know where it is located.
Sources
[1] Advance Directive for Health Care (Living Will and Health Care Proxy), Alabama Department of Public Health (the Official source link on this page).