

Walmart Group Critical Illness Claim Form at a glance
What it is: The Walmart Group Critical Illness Claim Form and Instructions is the form for filing your critical illness claim under the Wal-Mart Group Critical Illness Policy.
Where to get it: Additional claim forms are available on the website at https://www.standard.com/ahlevb/walmart/.
What to bring and attach to Walmart Group Critical Illness Claim Form
Include your certificate number. To obtain your certificate number, you may call 1-800-514-9525 or visit https://www.standard.com/ahlevb/walmart/.
To avoid delay, the patient must sign and submit the Authorization to Release Information to AHL (form ABJ21476).
A filled-in Walmart Group Critical Illness Claim Form example: a claim filed for yourself

How to fill out Walmart Group Critical Illness Claim Form, box by box
Insured's name, certificate number and address
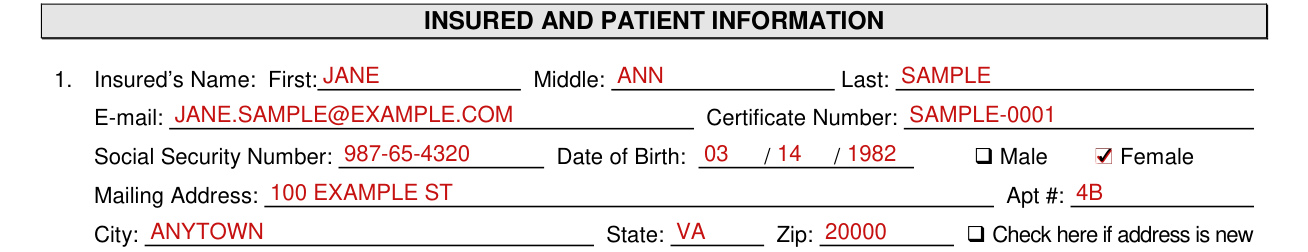
Under 1. Insured's Name, enter First, Middle and Last.
Enter the E-mail and the Certificate Number.
Enter the Social Security Number and the Date of Birth, and mark Male or Female.
Enter the Mailing Address and the Apt #.
Enter the City, State and Zip. Check here if address is new.
Daytime Phone Number, Evening/Cell Phone Number and Occupation

Under 2., enter the Daytime Phone Number and the Evening/Cell Phone Number.
Under 3., enter the Occupation.
Patient's information
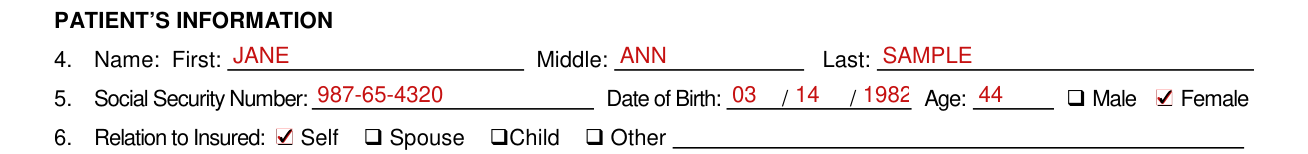
Under PATIENT'S INFORMATION, 4. Name, enter First, Middle and Last.
Under 5., enter the Social Security Number, the Date of Birth and the Age, and mark Male or Female.
Under 6. Relation to Insured, mark Self, Spouse, Child or Other.
You must also submit

You must also submit: The results of a tissue specimen, culture(s) and/or titer(s) or other diagnostic studies, which initially diagnosed the specified disease, must accompany your claim. A copy of your itemized hospital billing. A completed Attending Physician's Statement (ABJ21529WMT) is optional, but preferred for faster claim processing.
Critical Illness Benefit
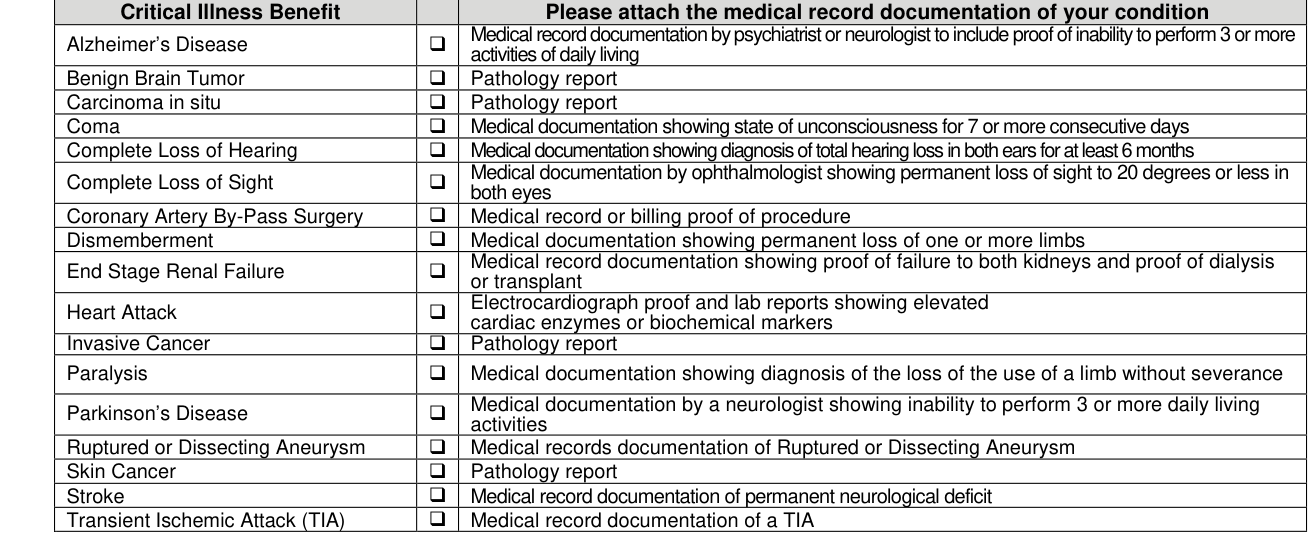
Check the benefit(s) you believe may be due based upon your condition.
Attach the medical record documentation of your condition.
Alzheimer's Disease: medical record documentation by psychiatrist or neurologist to include proof of inability to perform 3 or more activities of daily living.
Benign Brain Tumor and Carcinoma in situ: pathology report.
Coma: medical documentation showing state of unconsciousness for 7 or more consecutive days.
Complete Loss of Hearing: medical documentation showing diagnosis of total hearing loss in both ears for at least 6 months.
Complete Loss of Sight: medical documentation by ophthalmologist showing permanent loss of sight to 20 degrees or less in both eyes.
Coronary Artery By-Pass Surgery: medical record or billing proof of procedure.
Dismemberment: medical documentation showing permanent loss of one or more limbs.
End Stage Renal Failure: medical record documentation showing proof of failure to both kidneys and proof of dialysis or transplant.
Heart Attack: electrocardiograph proof and lab reports showing elevated cardiac enzymes or biochemical markers.
Invasive Cancer: pathology report.
Paralysis: medical documentation showing diagnosis of the loss of the use of a limb without severance.
Parkinson's Disease: medical documentation by a neurologist showing inability to perform 3 or more daily living activities.
Ruptured or Dissecting Aneurysm: medical records documentation of Ruptured or Dissecting Aneurysm.
Skin Cancer: pathology report.
Stroke: medical record documentation of permanent neurological deficit.
Transient Ischemic Attack (TIA): medical record documentation of a TIA.
Specified diseases
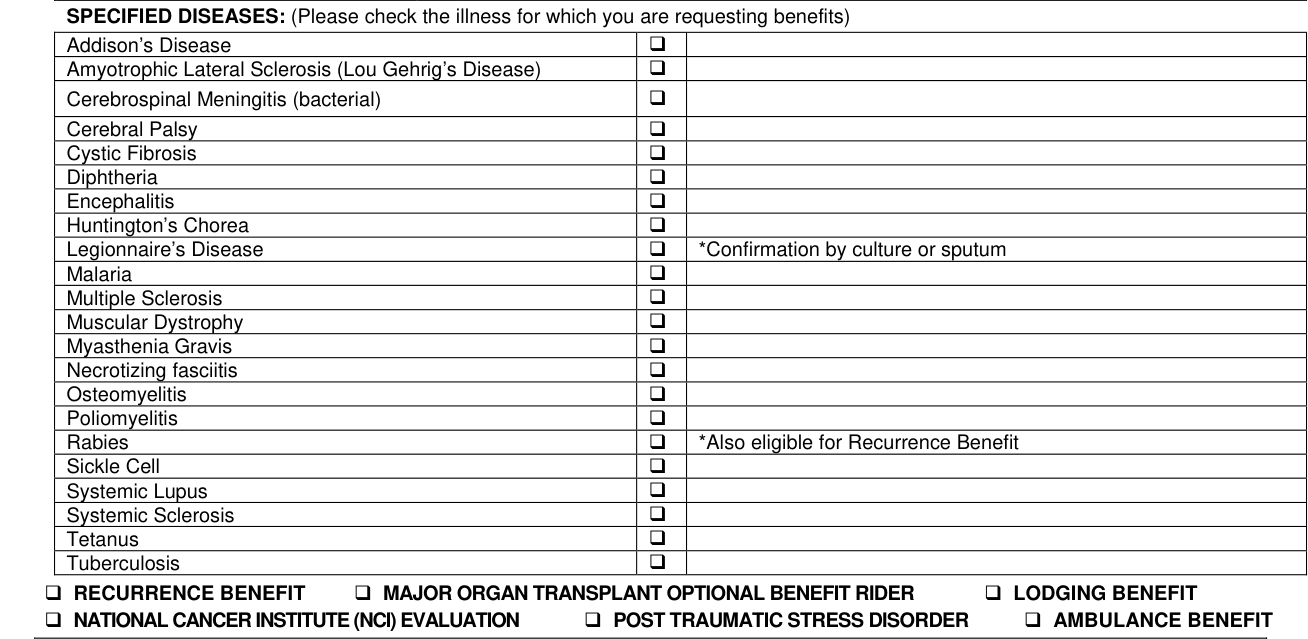
Under SPECIFIED DISEASES, check the illness for which you are requesting benefits.
Legionnaire's Disease: *Confirmation by culture or sputum.
Rabies: *Also eligible for Recurrence Benefit.
Recurrence Benefit and the other benefits

The form lists these boxes: Recurrence Benefit, Major Organ Transplant Optional Benefit Rider, Lodging Benefit, National Cancer Institute (NCI) Evaluation, Post Traumatic Stress Disorder and Ambulance Benefit.
Sign this part only if you wish to assign your benefits to a provider or a facility

Sign this part only if you wish to assign your benefits to a provider or a facility.
This part requests that American Heritage Life Insurance Company send benefits to someone other than you, to the name and address entered in it.
Enter the Name, Relationship, Provider or Facility Tax Identification Number, Address, and City, State and Zip.
Sign on the Signature of Insured line and enter the Date.
Authorization to Release Information to AHL
You authorize any physician, health care professional, hospital, clinic, laboratory, pharmacy, medical facility, health care provider, Pharmacy Benefit Manager, insurance company, the Medical Information Bureau (MIB) or other organization, institution or person that has any health related records or knowledge of you or minor dependents to disclose the entire medical record (excluding psychotherapy notes and in MAINE and VERMONT HIV related test results) to American Heritage Life Insurance Company (AHL), its duly authorized representatives, its subsidiaries or its reinsurers.
This authorization extends to any minor dependent on whom insurance is requested or claim for benefits is being made.
This information will be used to evaluate and administer your claim for benefits or to evaluate your eligibility for insurance.
This authorization shall remain in force for 24 months following the date of your signature or termination of your coverage, whichever occurs first.
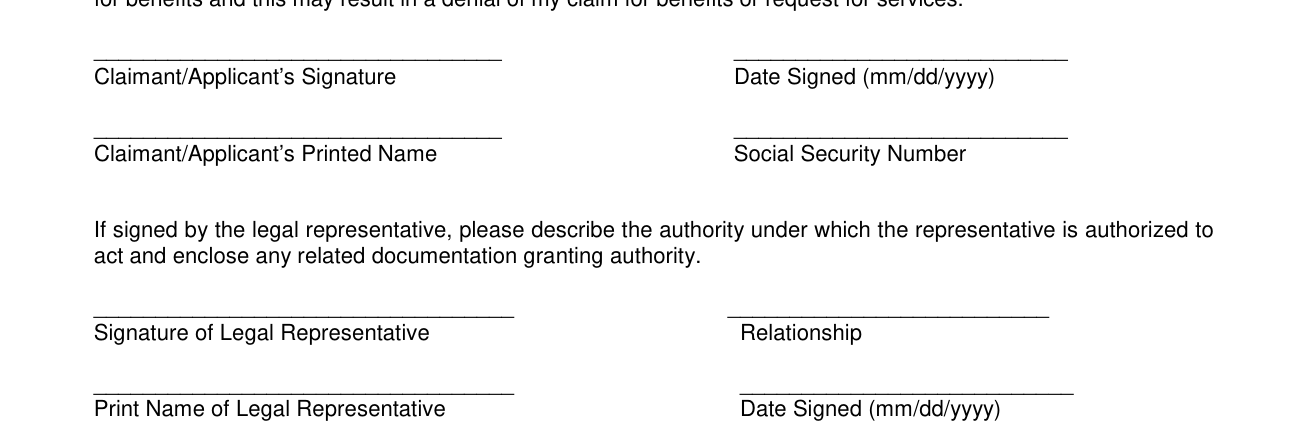
The claimant or applicant signs on the Claimant/Applicant's Signature line and enters the Date Signed (mm/dd/yyyy).
Enter the Claimant/Applicant's Printed Name and the Social Security Number.
If signed by the legal representative, describe the authority under which the representative is authorized to act and enclose any related documentation granting authority.
The legal representative signs on the Signature of Legal Representative line, and enters the Print Name of Legal Representative, the Relationship and the Date Signed (mm/dd/yyyy).
You may revoke this authorization at any time by sending a written notification to: Attn: Privacy Officer, American Heritage Life Insurance Company, 4920 San Pablo RoadS, Suite 200C, Jacksonville, FL 32224-6687.
A revocation of this authorization is not effective if AHL has relied on the protected health information or has a legal right to contest a claim under an insurance policy or to contest the policy itself.
The revocation will not apply to any information AHL requests or discloses prior to AHL receiving your revocation request.
If you choose not to sign this authorization or if you later revoke it, AHL may not be able to process your application for coverage, or if coverage has been issued, AHL may not be able to administer your claim for benefits and this may result in a denial of your claim for benefits or request for services.
More rules for Walmart Group Critical Illness Claim Form
To avoid delays in processing, fill out all sections that apply to your claim.
If you would like to receive your claim proceeds even faster, The Standard can automatically deposit them into your bank account or on your Money Network Card by completing and returning the ACH form (ABJ16661WMT), which can be found at https://www.standard.com/ahlevb/walmart/.
Common questions about Walmart Group Critical Illness Claim Form
Where do I file it?
You may fax your claim to 1-877-423-8804 or scan and electronically submit your claim through https://www.standard.com/ahlevb/walmart/. You may also mail your claim to: American Heritage Life Insurance Company, P.O. Box 41488 Jacksonville, Florida 32203-1488.
Where to get help with Walmart Group Critical Illness Claim Form
If you have any questions regarding benefits available, or how to file your claim, or if you would like to appeal any determination, contact the Walmart Claim Department at 1-800-514-9525, 8:00 A.M. to 8:00 P.M. Eastern Standard Time or visit https://www.standard.com/ahlevb/walmart/.
Sources
[1] Walmart Group Critical Illness Claim Form and Instructions ABJ10365W-8 (7/17), American Heritage Life Insurance Company (the Official source link on this page).
