

DE-101/DE-202 at a glance
What it is: DE-101/DE-202 is the Request For Application For Arizona Long Term Care System (ALTCS).
Where and when to file: To start the application process, you can call 888-621-6880 (toll-free) or register an application online at Health-e-Arizona Plus. You may also complete this form and return it using one of the methods found on page 4 of this Request for Application. Missing or incomplete information may cause a delay in the processing of your application. Bolded questions are required to be answered in order to register the application. To submit a Request for Application by phone, or for help, call 888-621-6880 (toll-free).
The person completing this form is the Customer, Spouse of the customer, or Parent of the customer (if the customer is a minor); if one of the Customer, Spouse of the customer or Parent of the customer boxes is NOT checked, the person completing this form may do what the form lists.
A filled-in DE-101/DE-202 example: a customer fills out page 1 of the ALTCS request
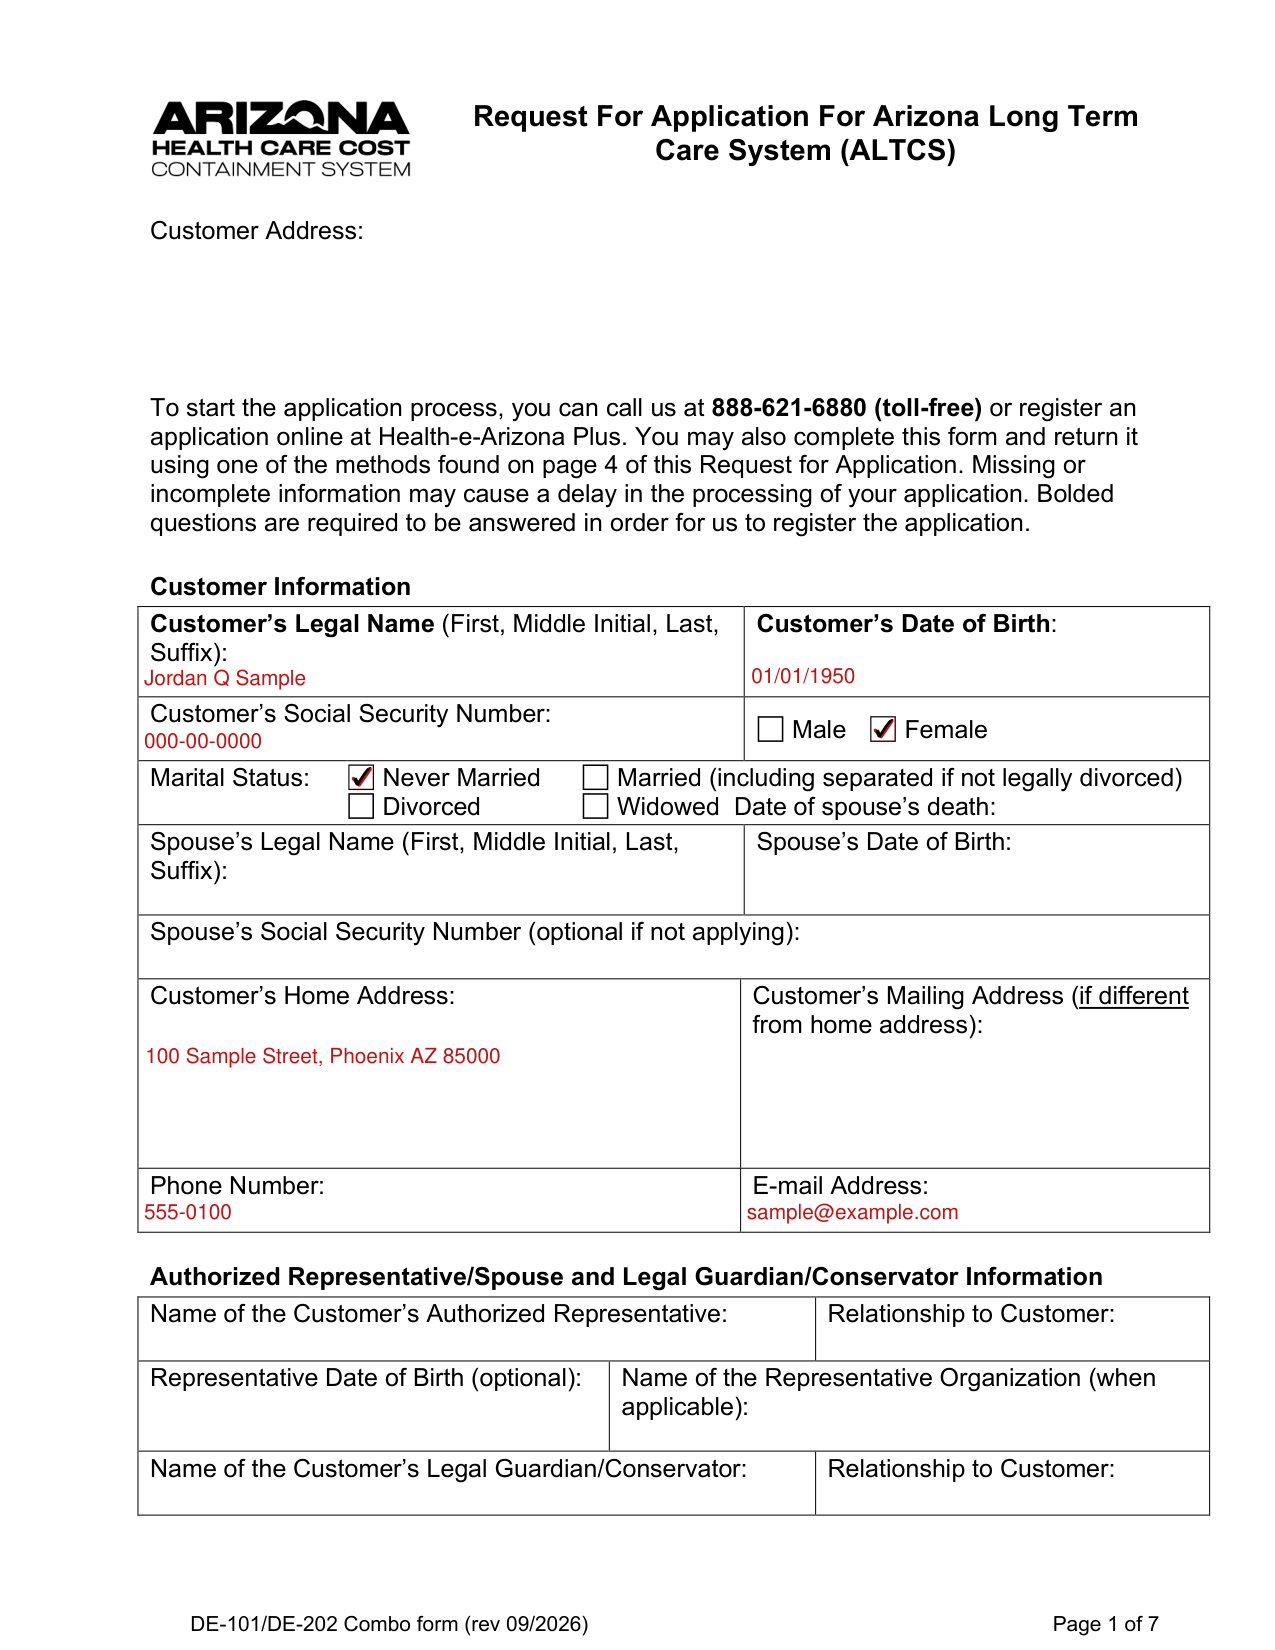
How to fill out DE-101/DE-202, box by box
Customer Information
Enter the Customer's Legal Name (First, Middle Initial, Last, Suffix), Customer's Date of Birth and Customer's Social Security Number, and mark Male or Female.
Applying and providing information is voluntary, but some information is required to make a determination. For example, you must provide or apply for a Social Security number for every applicant. (Immigrants who are not legally able to obtain a Social Security number are not required to provide one.) Therefore, if personal information is not provided, you may not be eligible for benefits.
Marital Status
Under Marital Status, mark Never Married, Married (including separated if not legally divorced), Divorced or Widowed, and for Widowed enter the Date of spouse's death. Enter the Spouse's Legal Name (First, Middle Initial, Last, Suffix), Spouse's Date of Birth and Spouse's Social Security Number (optional if not applying).
Customer's Home Address
Enter the Customer's Home Address, Customer's Mailing Address (if different from home address), Phone Number and E-mail Address.
Customer's Current Living Arrangement
Where is the customer currently residing? Mark Hospital, Nursing Facility, At Home or Other.
Enter Date Admitted, Expected Date of Discharge, the Name of the Hospital, Assisted Living or Nursing Facility, Phone Number, and Address with City, State and ZIP Code.
Accommodations for Printed Letters
Does the customer, authorized representative, or legal guardian have a visual impairment that requires an alternative format for printed letters? Mark No or Yes. If yes, enter who needs the accommodation.
If yes, what kind of alternative format do you need? Please choose one option: Readable PDF sent by secure email, Large print (larger print letters sent by U.S. mail will be provided Arial 24-point font) or Other.
Additional Questions
Does the customer need help paying for medical expenses from the last three months? Mark Yes or No. If yes, enter what months.
Is the customer pregnant or had a pregnancy end in the last 5 months? Mark Yes or No.
Is the customer receiving services from the DES Division of Developmental Disabilities? Mark Yes or No. If yes, enter the date services began.
Prior to the age of 18 was the customer diagnosed with any of the following medical conditions? Check all that apply: Autism, Cerebral Palsy, Intellectual/Cognitive Disability, Down syndrome or Seizure Disorder.
If the customer is under the age of 6, has the customer been diagnosed with Developmental Delay? Mark Yes or No.
Is the customer a trustor, trustee, or beneficiary of any type of trust? Mark Yes or No.
Has the customer sold, traded, transferred, or given away any assets within the last five years? Mark Yes or No.
Interview Information
An interview is required to complete the ALTCS application process.
The customer is not required to attend the financial interview if the legal guardian/conservator or authorized representative completes the interview for the customer.
What are the best days and times for you to complete the interview? Mark Monday, Tuesday, Wednesday, Thursday or Friday and enter the Time. Does the person completing the interview need an interpreter? Mark Yes or No. If yes, enter what language.
The person completing this form
Enter the Name of Person Completing Form and Phone Number.
If you check Customer, Spouse of the customer, or Parent of the customer (if the customer is a minor), the person completing this form must check the box on the next page and sign this form on the next page.
If one of the boxes is NOT checked, the person completing this form may complete an Authorized Representative form found at https://www.azahcccs.gov/Members/GetCovered/apply.html, attach the completed Authorized Representative form with this request for an application, check the box on the next page and sign this form on the next page.
Check the box I agree to allow you to check information sources and use it for this application, then enter Signature and Date. A request for an application may be returned without the completed authorized representative form, checking the box and signing, but may cause the application process to take more time.
Common questions about DE-101/DE-202
Where do I file it?
A completed Request for Application may also be returned by Online: Health-e-Arizona Plus, Fax (toll-free): 888-507-3313, E-mail: altcsregistration@azahcccs.gov, or Mail: AHCCCS P.O. Box 6050 MD 15023 ALTCS Phoenix AZ 85002-5520. A completed Request for Application may also be taken to a local ALTCS office in Chinle, Phoenix, Flagstaff, Tucson, Kingman or Yuma.
Sources
[1] DE-101/DE-202 Combo form (rev 09/2026), Arizona Health Care Cost Containment System (the Official source link on this page).
