

Social Worker Form 6 at a glance
What it is: Social Worker Form 6 Plan for Supervised Experience is a form of the Office of the Professions, Division of Professional Licensing Services, The State Education Department.
Who signs: In box 9, sign and date to declare and affirm that the statements made in the foregoing application, including accompanying statements are true, complete and correct. Supervisor: read the attached Appendix A and complete all of Section II. Be sure to sign the affidavit and return the entire form directly to the Applicant.
A Licensed Master Social Worker (LMSW) must be registered to practice in New York State and may only provide clinical social work services, including psychotherapy, under the supervision of a Licensed Clinical Social Worker (LCSW), licensed psychologist or licensed physician who is board-certified in psychiatry in an authorized setting. The setting is responsible for employing the LMSW and the qualified supervisor to provide clinical social work services; a LMSW cannot employ or contract with a supervisor.
A filled-in Social Worker Form 6 example: an LMSW fills in the top of Form 6
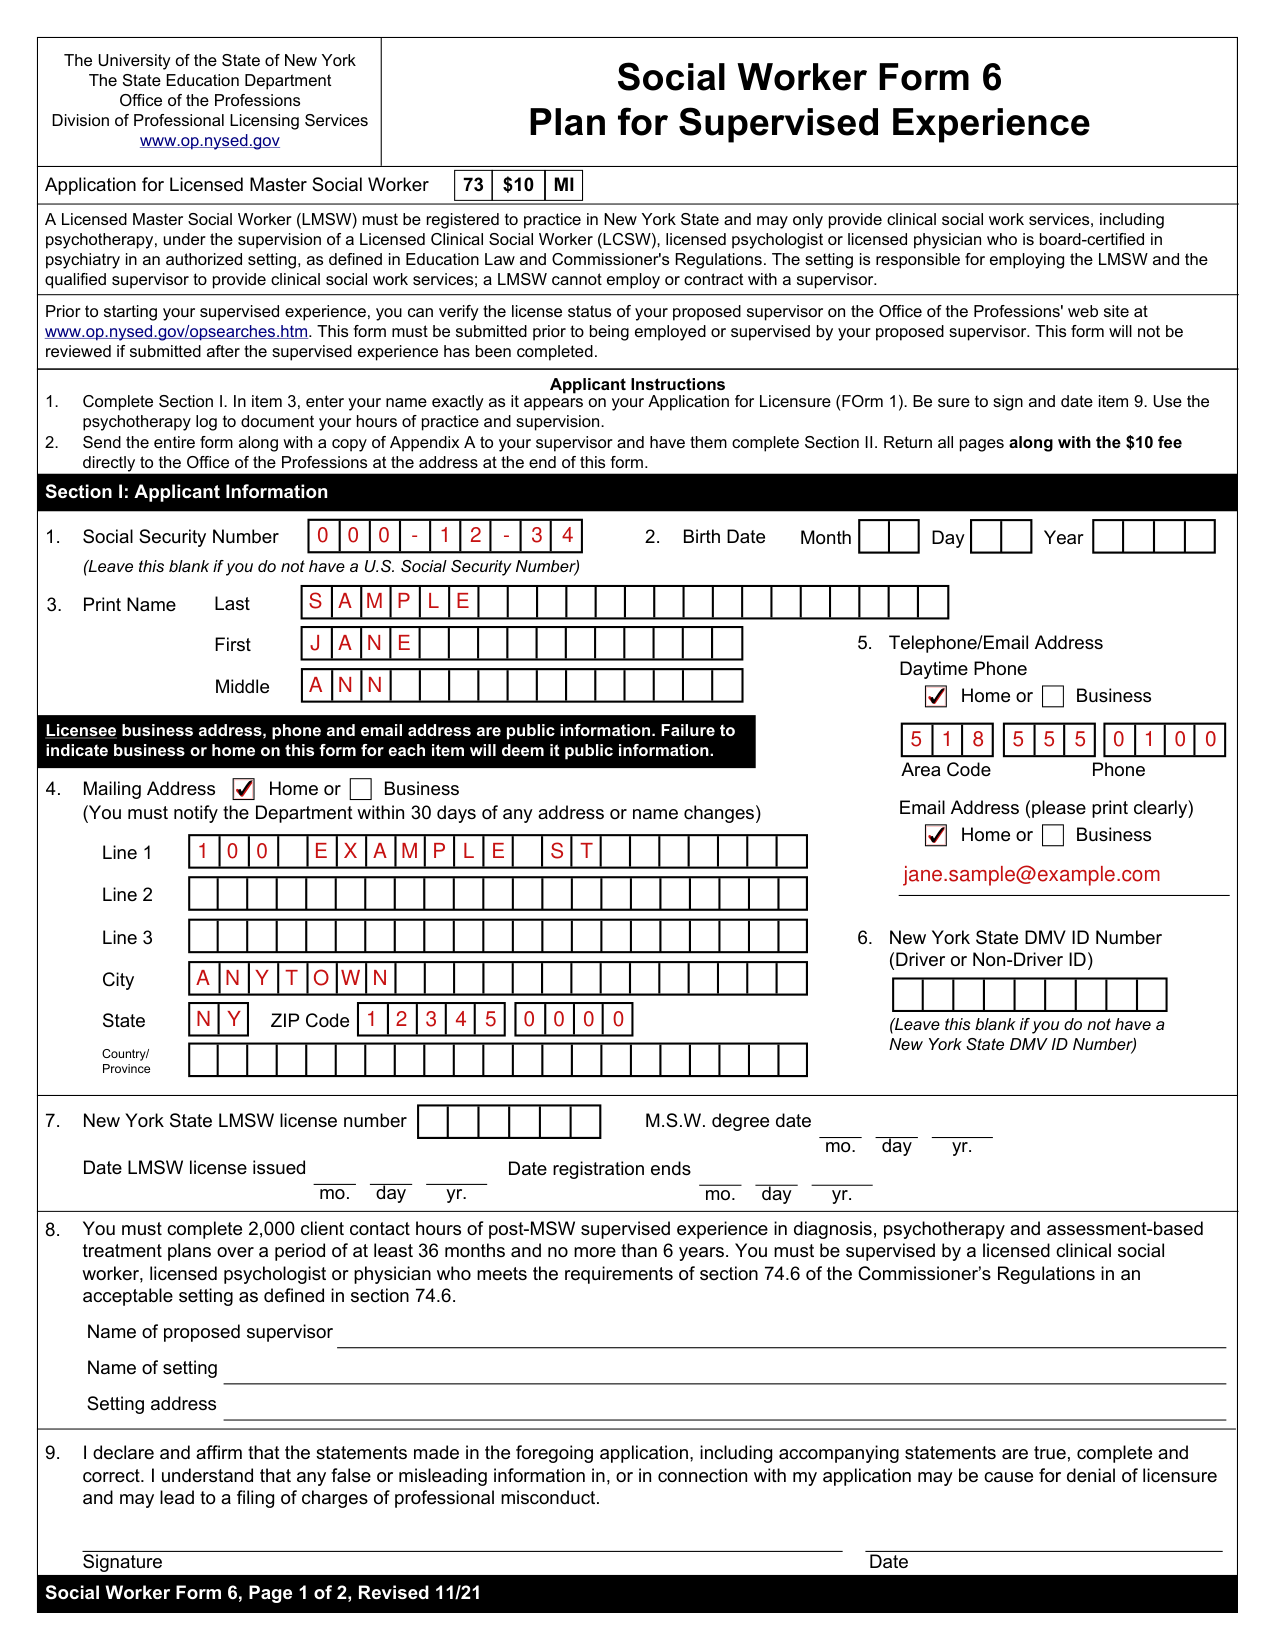
How to fill out Social Worker Form 6, box by box
Section I: Applicant Information
Prior to starting your supervised experience, you can verify the license status of your proposed supervisor on the Office of the Professions' web site at www.op.nysed.gov/opsearches.htm. This form must be submitted prior to being employed or supervised by your proposed supervisor. This form will not be reviewed if submitted after the supervised experience has been completed.
1. Complete Section I. In item 3, enter your name exactly as it appears on your Application for Licensure (Form 1). Be sure to sign and date item 9. Use the psychotherapy log to document your hours of practice and supervision. 2. Send the entire form along with a copy of Appendix A to your supervisor and have them complete Section II. Return all pages along with the $10 fee directly to the Office of the Professions at the address at the end of this form (checked November 2, 2026).
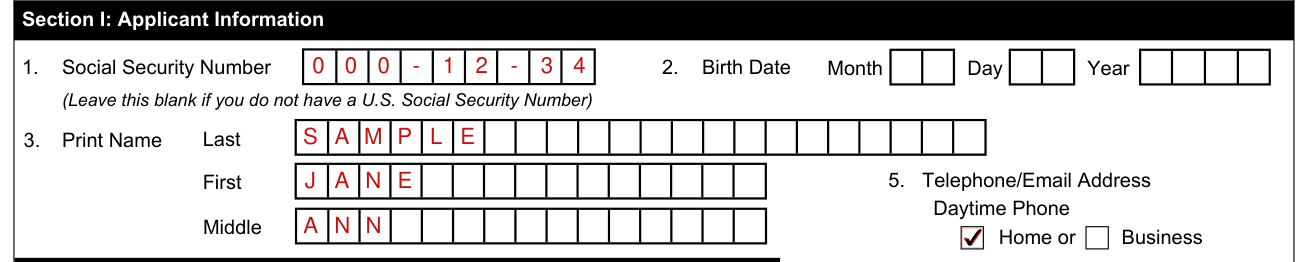
In box 1 of Section I: Applicant Information, enter the Social Security Number; leave this blank if you do not have a U.S. Social Security Number.
In box 2, enter the Birth Date as Month Day Year.
In box 3, print the name: Last, First and Middle.
4. Mailing Address Home or Business

In box 4, mark Home or Business and enter the Mailing Address: Line 1, Line 2, Line 3, City, State, ZIP Code and Country/ Province.
You must notify the Department within 30 days of any address or name changes.
5. Telephone/Email Address

In box 5, enter the Daytime Phone with Area Code and Phone, and the Email Address (please print clearly).
Licensee business address, phone and email address are public information. Failure to indicate business or home on this form for each item will deem it public information.
6. DMV ID Number and 7. LMSW license number
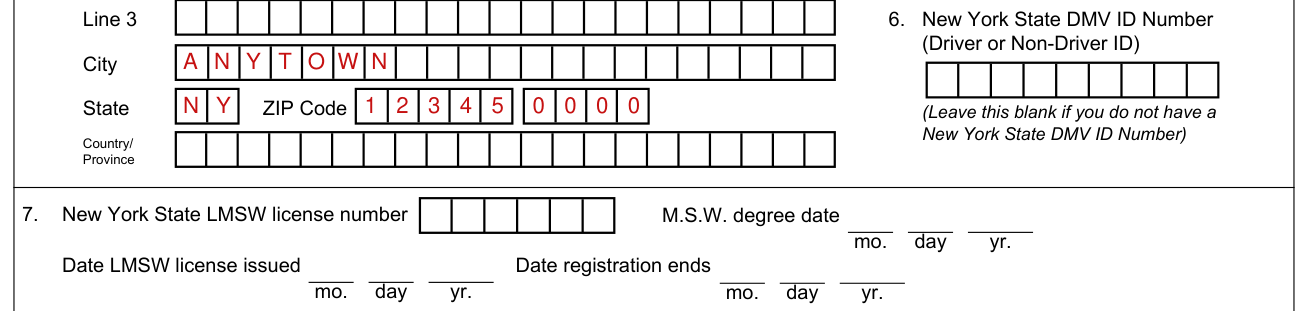
In box 6, enter the New York State DMV ID Number (Driver or Non-Driver ID); leave this blank if you do not have a New York State DMV ID Number.
In box 7, enter the New York State LMSW license number, the M.S.W. degree date, the Date LMSW license issued and the Date registration ends, each as mo. day yr.
Section II: licensed and currently registered to practice
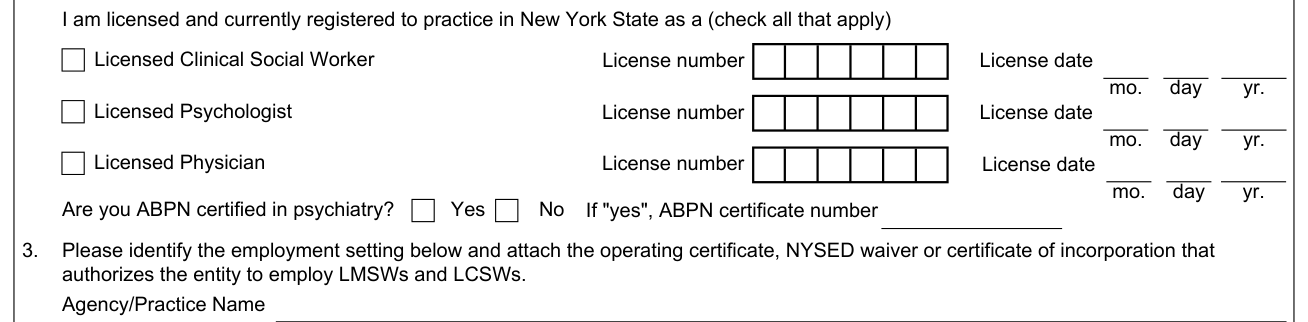
Enter the Supervisor name, and check all that apply: you are licensed and currently registered to practice in New York State.
For each of Licensed Clinical Social Worker, Licensed Psychologist and Licensed Physician that applies, enter the License number and the License date as mo. day yr.
Are you ABPN certified in psychiatry? Mark Yes or No. If yes, enter the ABPN certificate number.
Type of Setting (check one)

Enter the Agency/Practice Name and check one Type of Setting.
Check the box for a Private practice owned by supervisor (LCSW, Licensed psychologist or psychiatrist)
Check the box for a Professional entity (PLLC, PLLP, P.C.) owned by supervisor (attached consent from SED)
Sole proprietorship or other entity authorized under law (attach certificate of corporation)
Program approved by the New York State Office of Mental Health (OMH), Office for People with Developmental Disabilities (OPWDD), Office of Alcoholism & Substance Abuse Services (OASAS), Office of Children & Family Services (OCFS), Department of Corrections and Community Supervision (DOCCS), Department of Health (DOH), State Office for the Aging, or local social service or mental hygiene district (attach operating certificate)
Elementary, middle, high school or college authorized to provide psychotherapy services to students (attach copy of authorization)
Psychotherapy institute chartered by Board of Regents and authorized to provide psychotherapy to the public (attach copy of Regents Charter)
Not-for-profit or other entity authorized by waiver from the State Education Department to employ licensed professionals and provide services (attach waiver and certificate of incorporation)
Check Other and enter the description in the Other (describe) box.
Attestation: Supervisor Signature, Date, Print Name

By completing Section II, you are certifying that the person named in Section I will receive supervision that meets the requirements as defined in Education Law and the Commissioner's Regulations.
Under Attestation, the supervisor reads: I hereby certify that I have read Appendix A and that I meet the requirements to supervise a LMSW practicing clinical social work. The supervisor enters the Supervisor Signature, Date, Print Name, Address, Telephone, Fax and Email.
More rules for Social Worker Form 6
Any false or misleading information in, or in connection with your application may be cause for denial of licensure and may lead to a filing of charges of professional misconduct.
You must complete 2,000 client contact hours of post-MSW supervised experience in diagnosis, psychotherapy and assessment-based treatment plans over a period of at least 36 months and no more than 6 years.
You must be supervised by a licensed clinical social worker, licensed psychologist or physician who meets the requirements of section 74.6 of the Commissioner's Regulations in an acceptable setting as defined in section 74.6.
Enter the Name of proposed supervisor, the Name of setting and the Setting address.
Please identify the employment setting and attach the operating certificate, NYSED waiver or certificate of incorporation that authorizes the entity to employ LMSWs and LCSWs.
Enter the Agency/Practice address, the Agency/Practice Phone, Fax and Email, and the Agency/Practice web site.
The supervisor must be employed by the same agency as the LMSW and have access to all patient files and records; have responsibility for the assessment, evaluation and treatment of each patient diagnosed and treated by the LMSW practicing under his/her supervision; and each patient must consent to treatment by the supervised LMSW.
The supervision must consist of 100 or more hours of in-person individual or group clinical supervision distributed over the period of the supervised experience.
A supervisor may not have a familial relationship with the applicant, as such dual relationships may constitute a charge of unprofessional conduct under the Education Law and Regents Rules.
Client contact hour = 45 minutes of psychotherapy (shorter sessions may be combined). Supervision = at least 100 hours of in person supervision given by the attesting supervisor.
Use this weekly log to document the applicant's hours of practice and supervision for Licensed Clinical Social Work. All pages of this log must be retained by the supervisor and submitted upon request of the Department. Please copy this log as needed.
Common questions about Social Worker Form 6
Where do I file it?
If you are submitting an initial Form 6, mail this form and appropriate fee to: New York State Education Department, Office of the Professions, PO Box 22063, Albany, NY 12201, U.S.A..
Sources
[1] Social Worker Form 6, Plan for Supervised Experience, Revised 11/21, The State Education Department, Office of the Professions (the Official source link on this page).
