

Form C-4.3 at a glance
What it is: Form C-4.3 is the Doctor's Report of MMI/Permanent Partial Impairment.
Who signs: This form must be signed by the attending doctor and must contain their authorization certificate number, code letters and NPI number.
A filled-in Form C-4.3 example: a doctor's report with an EIN

How to fill out Form C-4.3, box by box
A. Patient's Information

Enter the Date of Examination, WCB Case # and Claim Admin Claim Number. Enter the Name (Last First MI), Date of Birth, SSN, Address (if changed from previous report) and Home phone #. Enter the Date of injury/illness and the Patient's Account #.
B. Doctor's Information
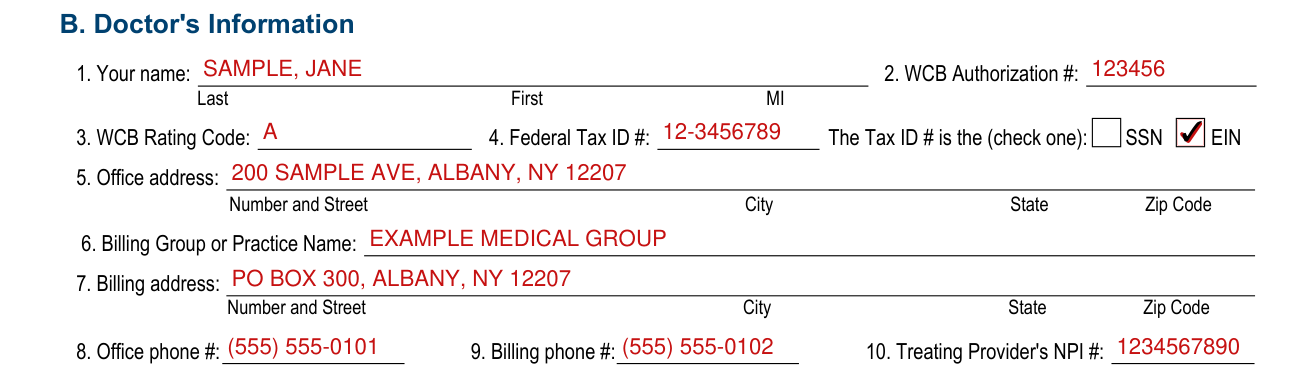
Enter your name (Last First MI), WCB Authorization #, WCB Rating Code and Federal Tax ID #. The Tax ID # is the (check one): SSN EIN. Enter the Office address, Billing Group or Practice Name, Billing address, Office phone #, Billing phone # and Treating Provider's NPI #.
C. Claim/Diagnoses Information

Enter the Employer's insurance carrier, Insurer ID and Insurance carrier's address. Enter the Diagnosis or nature of disease or injury: the ICD10 Code and the ICD10 Descriptor.
D. Maximum Medical Improvement
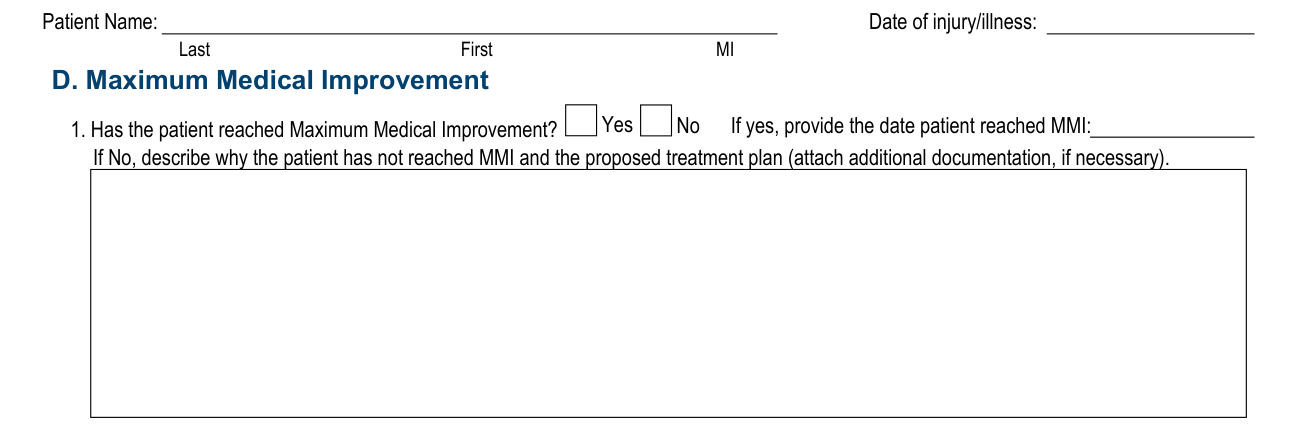
1. Has the patient reached Maximum Medical Improvement? Check Yes or No.
Yes No If yes, provide the date patient reached MMI: If No, describe why the patient has not reached MMI and the proposed treatment plan (attach additional documentation, if necessary).
A provider who finds that the patient has met MMI should so indicate and provide the approximate date of such finding (Question 1).
If the patient has not yet reached MMI so indicate (Question 1) and provide an explanation as to why additional improvement is expected and the proposed treatment plan.
For the definition of MMI, see Chapter 1.2 of the 2018 Guidelines and 2012 Guidelines.
E. Permanent Partial Impairment

1. Is there permanent partial impairment? Yes No
If there is no permanent partial impairment (Question 1) do not file this form, instead use Form C-4.2 (Dr's. Progress Report), unless requested by the Workers' Compensation Board to render a decision on MMI and/or permanent partial impairment.
List all the body parts and/or conditions that the patient was treated for with regards to the workers' compensation claims identified in Section A of the form (Question 2).
Attachment A and/or Attachment B must be completed for each body part and/or condition which you treated the patient for on the date of injury listed in Section A, Question 6.
For a permanent partial impairment where schedule award (schedule loss of use) is appropriate, complete Attachment A, except for serious facial disfigurement, vision, or hearing loss.
For a non-schedule award (classification), complete Attachment B. Serious Facial Disfigurement: C-4.3 with an attached narrative.
Permanent Partial Disability - Attachment A Schedule Loss of Use of Member
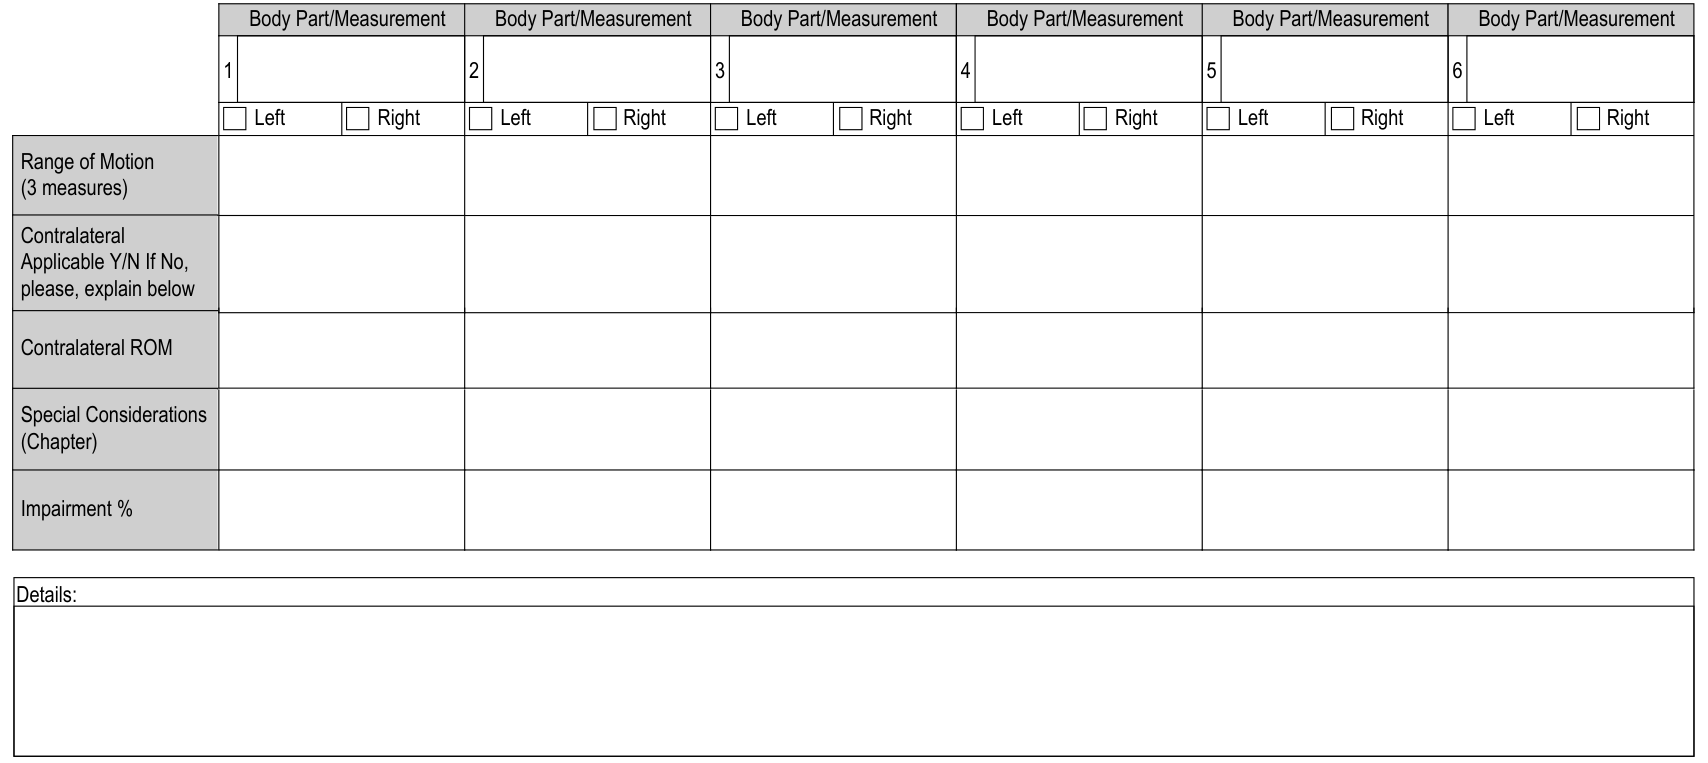
If the patient has a permanent partial impairment, complete Attachment A for all body parts and conditions for which a schedule award is appropriate (schedule loss of use).
Determine impairment % using the 2018 Workers' Compensation Guidelines for Determining Impairment.
Include in the table or attach a medical narrative with your report: the affected body part (include left or right side) and identify Guideline chapter (when special consideration exist). Measured Active Range of Motion (ROM) (3 measurements for injured body part, and use the greatest ROM). If not, please explain why. Measurement of contralateral body part ROM, or explain why inapplicable. Previously received scheduled losses of use to same body part(s), if known, stating with specificity the percentage loss of use you believe to be attributable solely to the injury being evaluated (and why), versus the percentage(s) of loss of use to the same body part(s) attributed to prior injury(ies).
Special considerations: Loading for Digits and Toes
Attach additional sheets if needed.
Range of Motion (3 measures) Contralateral Applicable Y/N If No, please, explain Contralateral ROM Special Considerations (Chapter) Impairment % Details:
Common mistake: If a scheduled loss is appropriate under the 2018 Impairment Guidelines do not complete any questions in Attachment B.
Permanent Partial Disability - Attachment B Non-Schedule Award (Classification)
Attachment B should be completed based on the patient's current condition if the provider believes there is MMI and/or permanent partial impairment or in a response to a request by the Board to render a decision on MMI and/or permanent partial impairment.
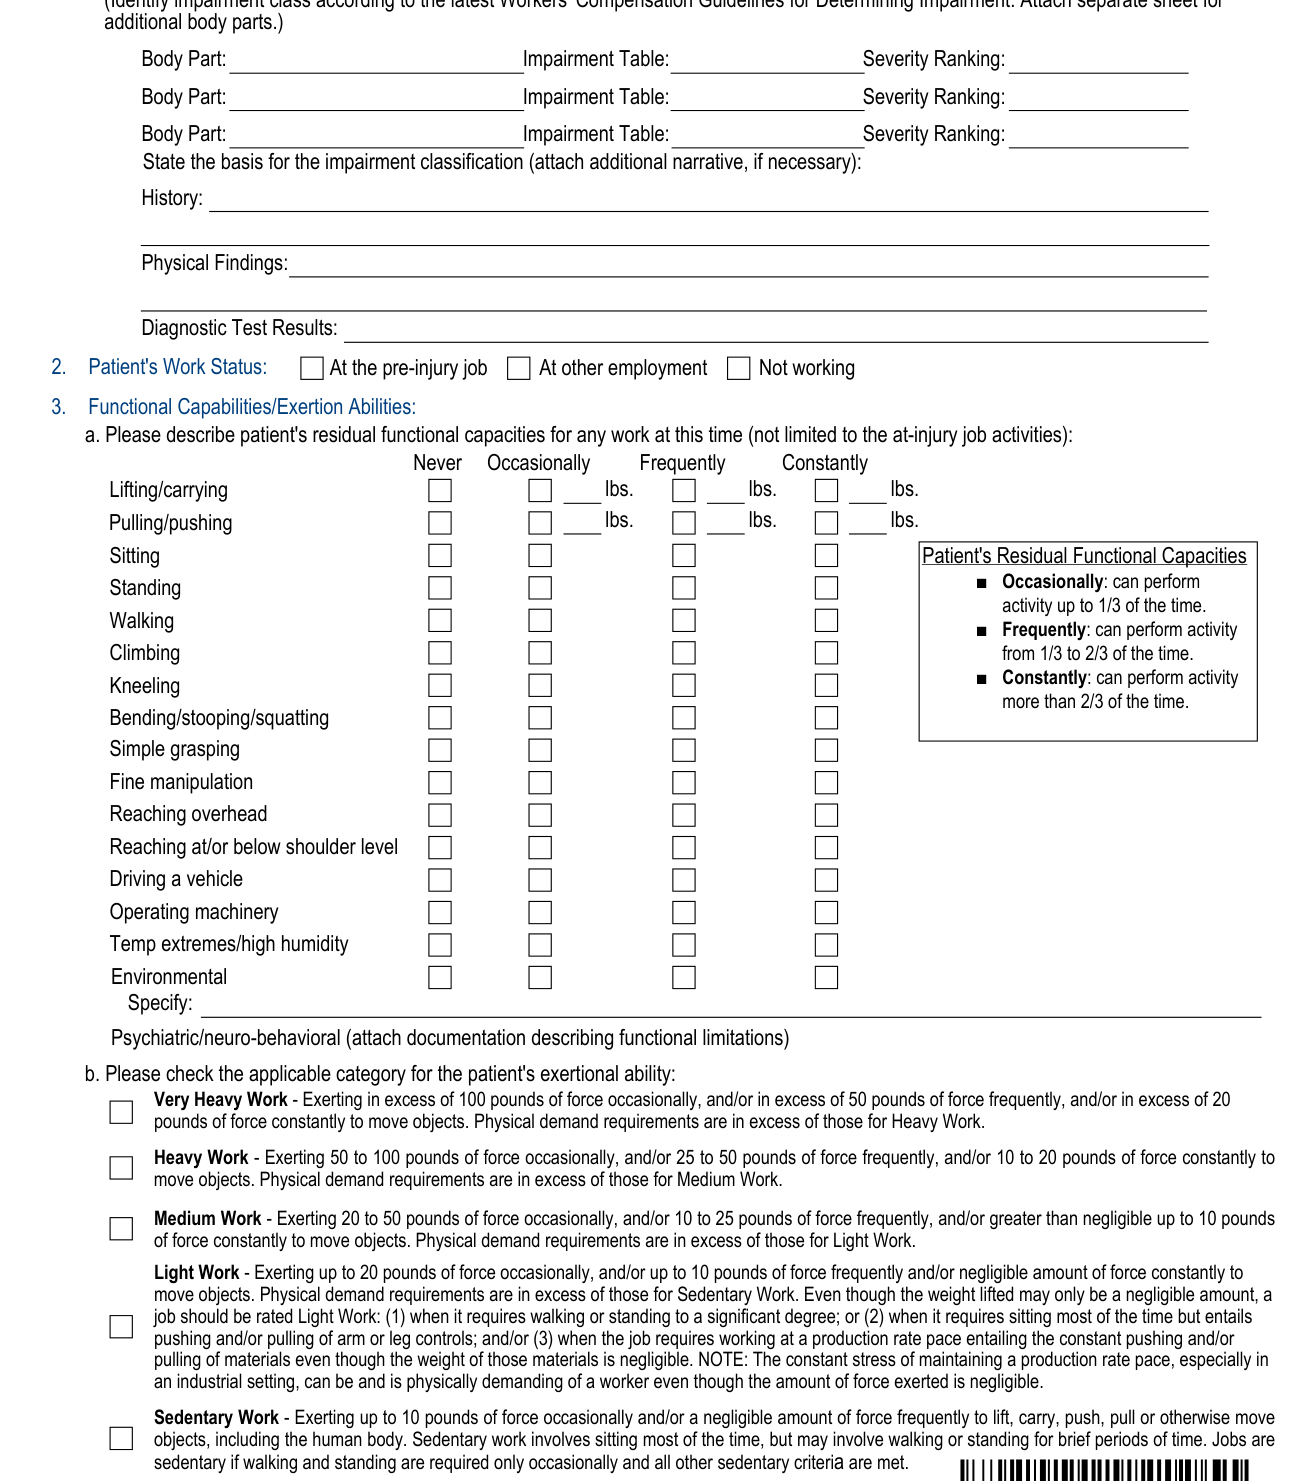
1. Non-Schedule Permanent Partial Disability: (Identify impairment class according to the latest Workers' Compensation Guidelines for Determining Impairment. Body Part: Impairment Table: Severity Ranking:
Attach separate sheet for additional body parts.)
If the patient was treated for a body part and condition that is not amendable to a schedule loss of use award, record the body part, impairment table and severity letter grade for each body part or system (Question 1) using the 2012 Guidelines.
If the patient has a non-schedule impairment of a body part or system that is not covered by an impairment guideline, follow Chapter 17 of the 2012 Guidelines and include the relevant history, physical findings, and diagnostic test results, but no severity letter grade.
State the basis for the impairment classification (attach additional narrative, if necessary): History: Physical Findings: Diagnostic Test Results:
Also state the history, physical findings, and diagnostic test results that support the impairment finding.
2. Check the Patient's Work Status: At the pre-injury job, At other employment or Not working.
3. Functional Capabilities/Exertion Abilities: a. Please describe patient's residual functional capacities for any work at this time (not limited to the at-injury job activities):
Never Constantly Frequently Occasionally: Lifting/carrying lbs. lbs. lbs. Pulling/pushing lbs. lbs. lbs. Environmental Specify: Psychiatric/neuro-behavioral (attach documentation describing functional limitations)
Measure and record the specific functional abilities and losses caused by the work-related medical impairment on Questions 3, a through f as follows: Question 3a - Rate whether the patient can perform each of the fifteen functional abilities: never, occasionally, frequently, or constantly.
Patient's Residual Functional Capacities Occasionally: can perform activity up to 1/3 of the time. Frequently: can perform activity from 1/3 to 2/3 of the time. Constantly: can perform activity more than 2/3 of the time.
b. Please check the applicable category for the patient's exertional ability:
Functional Capabilities/Exertion Abilities (continued): c. Other medical considerations which arise from this work related injury (including the use of pain medication such as narcotics):
d. Could this patient perform their at-injury work activities with restrictions? Yes No If Yes, specify:
e. Could this patient perform any work activities with or without restrictions? Yes No Explain:
f. If patient is not working, could reasonable accommodations be made to enable the patient to perform work? Yes No If Yes, explain:
4. Has the patient had an injury/illness since the date of injury which impacts residual functional capacity? Yes No If Yes, explain. Attach additional sheets if necessary.
5. Would the patient benefit from vocational rehabilitation? Yes No If Yes, explain
Board Authorized Health Care Provider signature

Sign and submit to the Board only the pages of the form that apply to this report.
This form is signed under penalty of perjury.
Board Authorized Health Care Provider signature: Name Signature Specialty Date
The provider should sign the Board Authorization at the bottom of page 2 and return to the Workers' Compensation Board.
More rules for Form C-4.3
Please answer all questions completely, attaching extra pages if necessary, and submit promptly to the Board, the insurance carrier and to the patient's attorney or licensed representative, if they have one; if not, send a copy to the patient. Failure to do so may delay the payment of necessary treatment, prevent the timely payment of wage loss benefits to the patient, create the necessity for testimony, and jeopardize your Board authorization.
Ask the patient if they have retained a legal representative. If they have retained legal representation, you are required to send copies of all reports to the patient's representative.
If your situation is different
Use this form
This form is to be used to file reports in workers' compensation, volunteer firefighters' or volunteer ambulance workers' benefits cases as follows:
Use this form: 1. When rendering an opinion on MMI and/or permanent partial impairment; or 2. In response to a request by the Workers' Compensation Board to render a decision on MMI and/or permanent partial impairment. Submit Form C-4.3 attached to electronically submitted CMS-1500 medical bill as the medical narrative. Do not send the form separately to the Board.
Common questions about Form C-4.3
Is there a penalty?
Any person who knowingly and with intent to defraud presents, causes to be presented, or prepares with knowledge or belief that it will be presented to or by an insurer, or self-insurer, any information containing any false material statement or conceals any material fact shall be guilty of a crime and subject to substantial fines and imprisonment.
Where to get help with Form C-4.3
If you have questions, please contact the NYS Workers' Compensation Board at 1-800-781-2362.
Sources
[1] Form C-4.3 (8-25), New York State Workers' Compensation Board (the Official source link on this page).
