

Form C-11 at a glance
What it is: Form C-11 is the Employer's Report of Injured Employee's Change in Employment Status Resulting from Injury.
Where and when to file: File Form C-11 directly with the Chair, Workers' Compensation Board.
A filled-in Form C-11 example: an employer reports a return to work
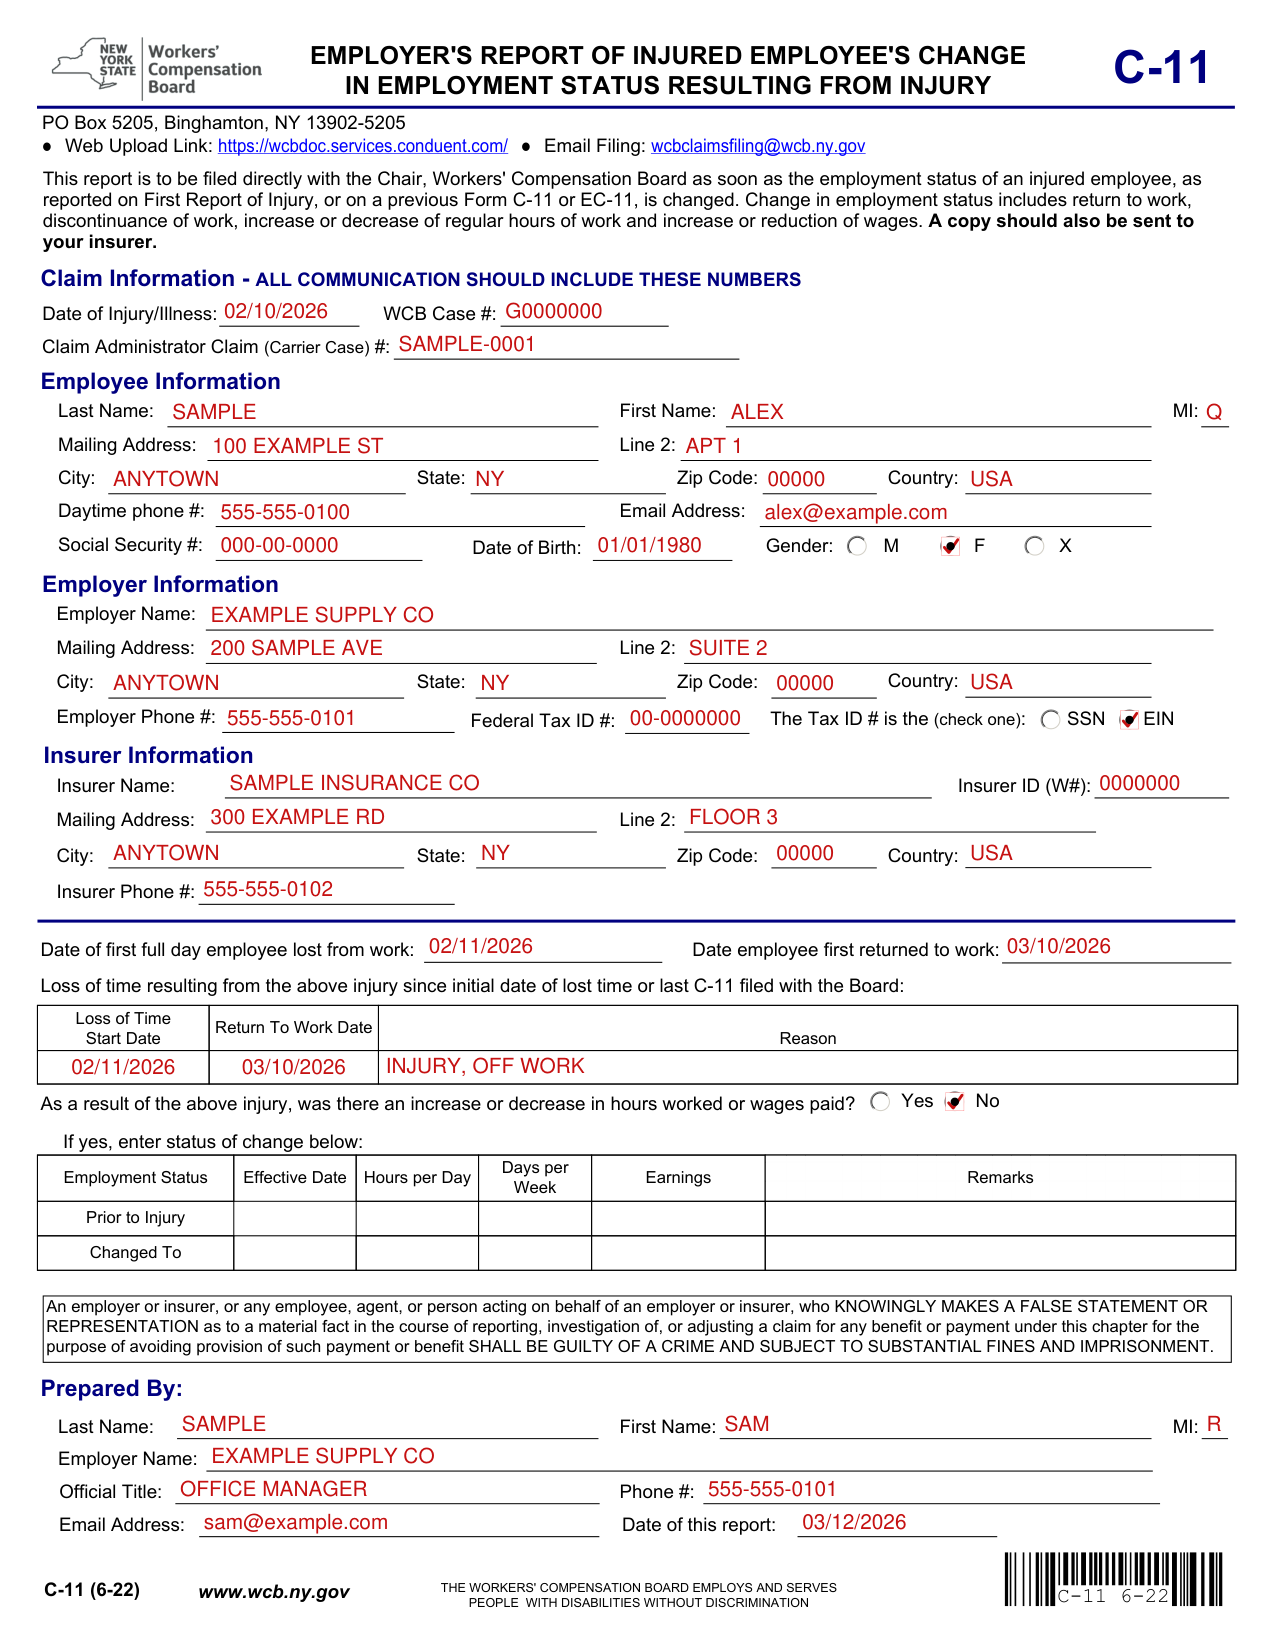
How to fill out Form C-11, box by box
Change in employment status
This report is to be filed as soon as the employment status of an injured employee, as reported on First Report of Injury, or on a previous Form C-11 or EC-11, is changed.
Claim Information
All communication should include these numbers: Date of Injury/Illness, WCB Case # and Claim Administrator Claim (Carrier Case) #.
Employee Information
Under Employee Information, enter Last Name, First Name and MI, then Mailing Address and Line 2, then City, State, Zip Code and Country.
Then enter Daytime phone #, Email Address and Social Security #, mark M, X or F for Gender and enter Date of Birth.
Employer Information
Under Employer Information, enter Employer Name and Employer Phone #, then Mailing Address, Line 2, City, State, Zip Code and Country.
For The Tax ID # is the (check one), mark SSN or EIN, then enter the Federal Tax ID #.
Insurer Information
Enter Insurer Name, Insurer ID (W#) and Insurer Phone #, and the insurer's Mailing Address with Line 2, City, State, Zip Code and Country.
Date of first full day employee lost from work
Enter the Date of first full day employee lost from work and the Date employee first returned to work.
Loss of time resulting from the above injury
For loss of time resulting from the injury since initial date of lost time or last C-11 filed with the Board, enter Loss of Time Start Date, Return To Work Date and Reason.
Hours worked or wages paid
Mark Yes or No: as a result of the injury, was there an increase or decrease in hours worked or wages paid?
If yes, enter status of change, for Prior to Injury and for Changed To, Employment Status, Effective Date, Hours per Day, Days per Week, Earnings and Remarks.
Prepared By
Under Prepared By, enter First Name, Last Name and MI, Employer Name, Official Title, Phone #, Email Address and Date of this report.
Common questions about Form C-11
What is a C-11 form?
Form C-11 is the Employer's Report of Injured Employee's Change in Employment Status Resulting from Injury. For Form C-11, change in employment status includes return to work, discontinuance of work, increase or decrease of regular hours of work and increase or reduction of wages.
Where do I file it?
File Form C-11 directly with the Chair, Workers' Compensation Board. Use PO Box 5205, Binghamton, NY 13902-5205, the Web Upload Link https://wcbdoc.services.conduent.com/ or Email Filing wcbclaimsfiling@wcb.ny.gov. A copy of Form C-11 should also be sent to your insurer.
Is there a penalty?
An employer or insurer, or any employee, agent, or person acting on behalf of an employer or insurer, who KNOWINGLY MAKES A FALSE STATEMENT OR REPRESENTATION as to a material fact in the course of reporting, investigation of, or adjusting a claim for any benefit or payment under this chapter for the purpose of avoiding provision of such payment or benefit SHALL BE GUILTY OF A CRIME AND SUBJECT TO SUBSTANTIAL FINES AND IMPRISONMENT.
Sources
[1] Form C-11 (6-22), Employer's Report of Injured Employee's Change in Employment Status Resulting from Injury, New York State Workers' Compensation Board (the Official source link on this page).
