
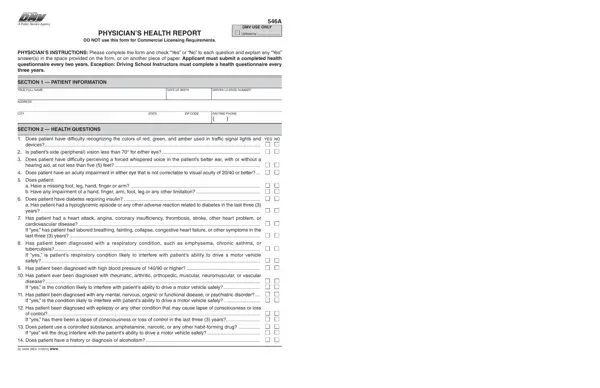

Form DL 546A at a glance
What it is: DL 546A is the PHYSICIAN'S HEALTH REPORT. DO NOT use this form for Commercial Licensing Requirements.
Who signs: By signing you certify (or declare) under penalty of perjury under the laws of the State of California that this form is true and correct, and you consent to the release of medical information by the physician named in the PHYSICIAN'S NAME box. Sign at DRIVER'S SIGNATURE X and enter the DATE.
A filled-in Form DL 546A example: a physician reports on a renewal patient
How to fill out Form DL 546A, box by box
SECTION 1 - PATIENT INFORMATION
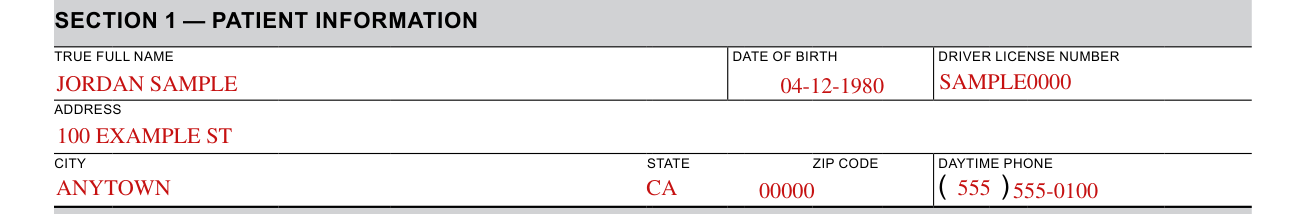
Under Section 1 - Patient Information, enter True Full Name, Date of Birth, Driver License Number, Address, City, State, Zip Code and Daytime Phone.
SECTION 2 - HEALTH QUESTIONS
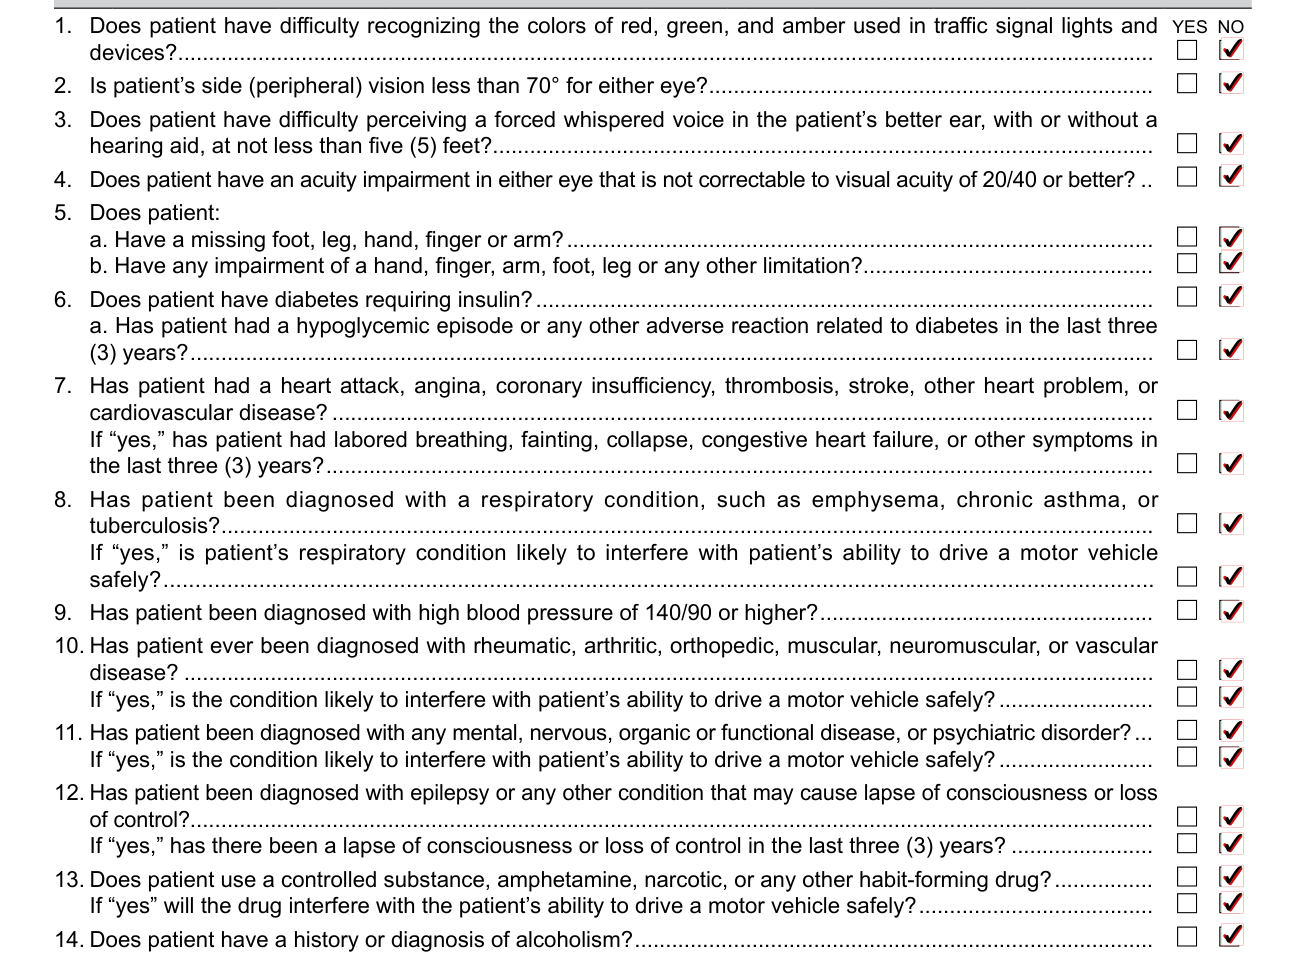
PHYSICIAN'S INSTRUCTIONS: Complete the form and check “Yes” or “No” to each question and explain any “Yes” answer(s) in the space provided on the form, or on another piece of paper. Applicant must submit a completed health questionnaire every two years. Exception: Driving School Instructors must complete a health questionnaire every three years.
1. Does patient have difficulty recognizing the colors of red, green, and amber used in traffic signal lights and devices? 2. Is patient's side (peripheral) vision less than 70° for either eye? 3. Does patient have difficulty perceiving a forced whispered voice in the patient's better ear, with or without a hearing aid, at not less than five (5) feet? 4. Does patient have an acuity impairment in either eye that is not correctable to visual acuity of 20/40 or better? 5. Does patient: a. Have a missing foot, leg, hand, finger or arm? b. Have any impairment of a hand, finger, arm, foot, leg or any other limitation? 6. Does patient have diabetes requiring insulin? a. Has patient had a hypoglycemic episode or any other adverse reaction related to diabetes in the last three (3) years? 7. Has patient had a heart attack, angina, coronary insufficiency, thrombosis, stroke, other heart problem, or cardiovascular disease? If “yes,” has patient had labored breathing, fainting, collapse, congestive heart failure, or other symptoms in the last three (3) years? 8. Has patient been diagnosed with a respiratory condition, such as emphysema, chronic asthma, or tuberculosis? If “yes,” is patient's respiratory condition likely to interfere with patient's ability to drive a motor vehicle safely? 9. Has patient been diagnosed with high blood pressure of 140/90 or higher? 10. Has patient ever been diagnosed with rheumatic, arthritic, orthopedic, muscular, neuromuscular, or vascular disease? If “yes,” is the condition likely to interfere with patient's ability to drive a motor vehicle safely? 11. Has patient been diagnosed with any mental, nervous, organic or functional disease, or psychiatric disorder? If “yes,” is the condition likely to interfere with patient's ability to drive a motor vehicle safely? 12. Has patient been diagnosed with epilepsy or any other condition that may cause lapse of consciousness or loss of control? If “yes,” has there been a lapse of consciousness or loss of control in the last three (3) years? 13. Does patient use a controlled substance, amphetamine, narcotic, or any other habit-forming drug? If “yes” will the drug interfere with the patient's ability to drive a motor vehicle safely? 14. Does patient have a history or diagnosis of alcoholism?
Visual Acuity
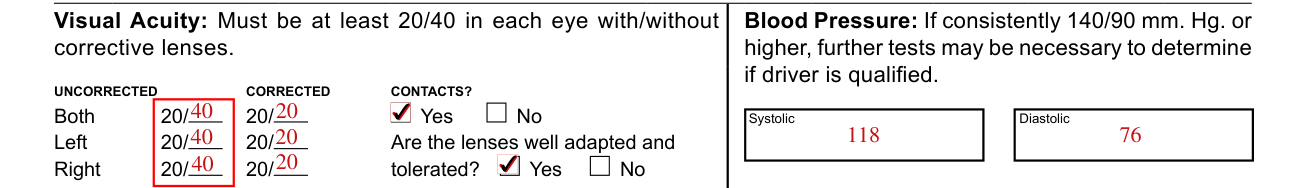
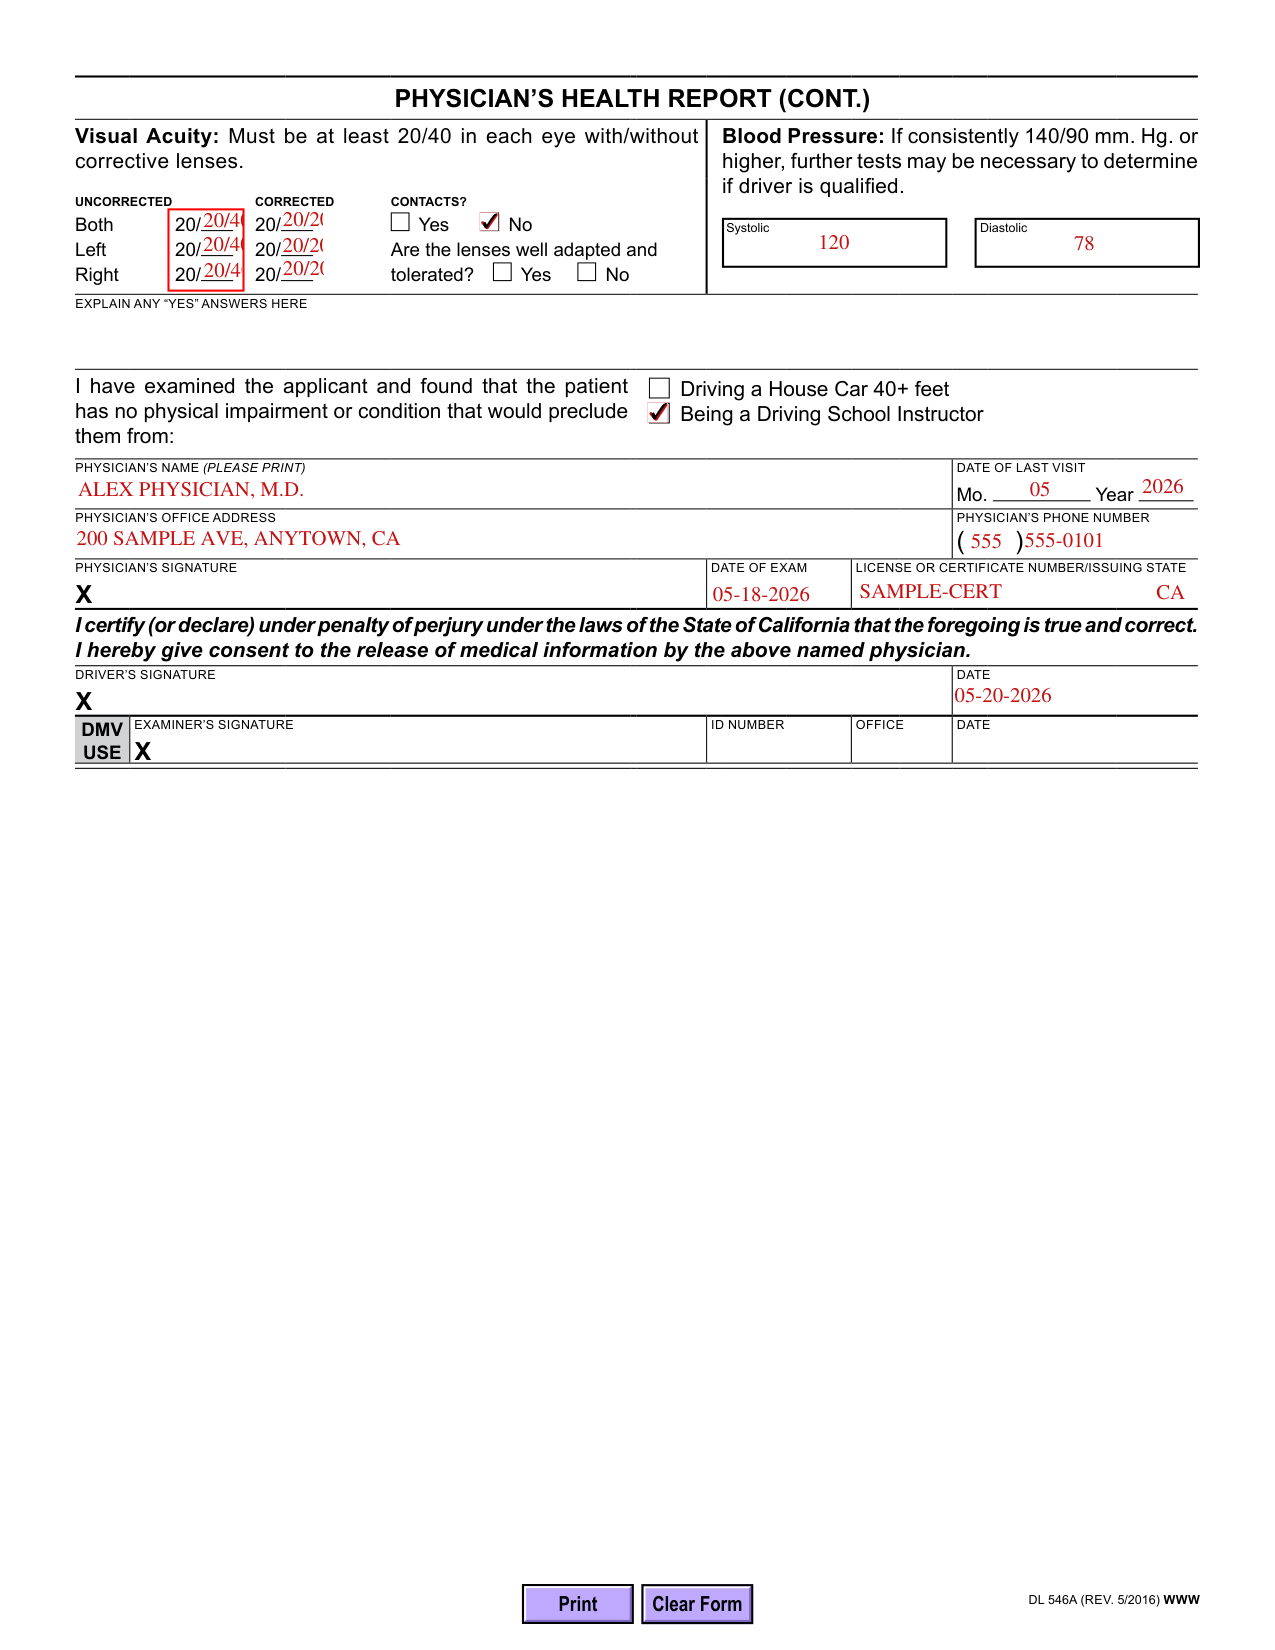
Visual Acuity: Must be at least 20/40 in each eye with/without corrective lenses.
Enter UNCORRECTED and CORRECTED for Both, Left and Right, and mark CONTACTS? Yes or No and Are the lenses well adapted and tolerated? Yes or No.
Blood Pressure
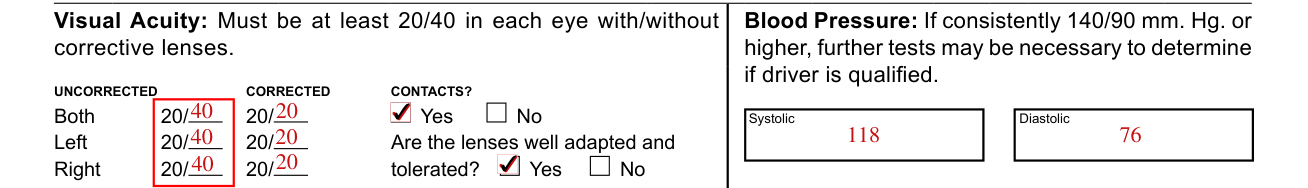
Blood Pressure: If consistently 140/90 mm. Hg. or higher, further tests may be necessary to determine if driver is qualified.
Enter Systolic and Diastolic.
EXPLAIN ANY “YES” ANSWERS HERE
EXPLAIN ANY “YES” ANSWERS HERE.
I have examined the applicant

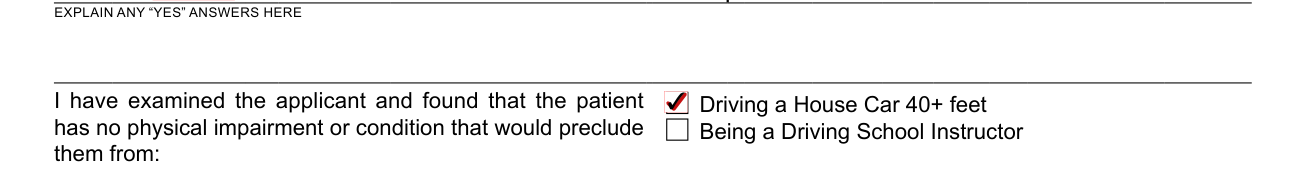
I have examined the applicant and found that the patient has no physical impairment or condition that would preclude them from: Driving a House Car 40+ feet, Being a Driving School Instructor.
The physician

Enter Physician's Name (please print), Date of Last Visit (Mo. Year), Physician's Office Address, Physician's Phone Number, Date of Exam and License or Certificate Number/Issuing State, and sign at Physician's Signature X.
The signatures

Common questions about Form DL 546A
When is this form not the right one?
DL 546A is the PHYSICIAN'S HEALTH REPORT. DO NOT use this form for Commercial Licensing Requirements.
Sources
[1] Form DL 546A (REV. 5/2016), California Department of Motor Vehicles (the Official source link on this page).