
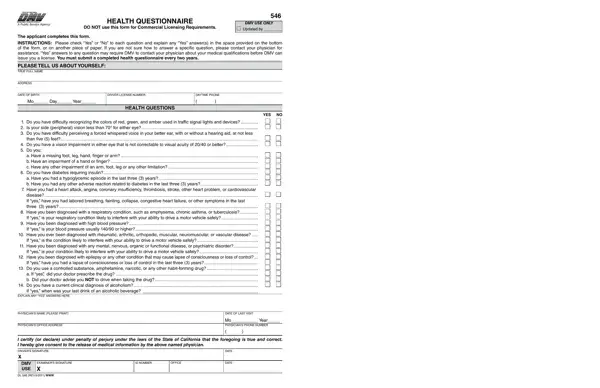

California DMV DL 546 at a glance
What it is: DL 546 is the HEALTH QUESTIONNAIRE for DMV, with Section 1 to tell about yourself and Section 2 with health questions.
Who signs: Sign on the driver's signature line and enter the date.
A filled-in California DMV DL 546 example: a driver fills Section 1 and the physician lines

How to fill out California DMV DL 546, box by box
Section 1 - Please tell us about yourself

In Section 1, enter your true full name, date of birth, driver license number, address, city, state, zip code and daytime phone.
Health questions 1 to 6

The applicant completes this form. Do not use this form for Commercial Licensing Requirements. Check "Yes" or "No" to each question and explain any "Yes" answer(s) in the space provided on the bottom of the form, or on another piece of paper. If you are not sure how to answer a specific question, contact your physician for assistance. "Yes" answers to any question may require DMV to contact your physician about your medical qualifications before DMV can issue you a license. You must submit a completed health questionnaire every two years.
In Section 2, Health Questions, check Yes or No. 1. Do you have difficulty recognizing the colors of red, green, and amber used in traffic signal lights and devices? 2. Is your side (peripheral) vision less than 70° for either eye? 3. Do you have difficulty perceiving a forced whispered voice in your better ear, with or without a hearing aid, at not less than five (5) feet? 4. Do you have a vision impairment in either eye that is not correctable to visual acuity of 20/40 or better? 5. Do you:
a. Have a missing foot, leg, hand, finger or arm? b. Have any impairment of a hand or finger? c. Have any other impairment of an arm, foot, leg or any other limitation? 6. Do you have diabetes requiring insulin?
Health questions 6a, 6b and 7 to 14

Also in Section 2, Health Questions: a. Have you had a hypoglycemic episode in the last three (3) years? b. Have you had any other adverse reaction related to diabetes in the last three (3) years? 7. Have you had a heart attack, angina, coronary insufficiency, thrombosis, stroke, other heart problem, or cardiovascular disease? If "yes," have you had labored breathing, fainting, collapse, congestive heart failure, or other symptoms in the last three (3) years? 8. Have you been diagnosed with a respiratory condition, such as emphysema, chronic asthma, or tuberculosis? If "yes," is your respiratory condition likely to interfere with your ability to drive a motor vehicle safely? 9. Have you been diagnosed with high blood pressure? If "yes," is your blood pressure usually 140/90 or higher? 10. Have you ever been diagnosed with rheumatic, arthritic, orthopedic, muscular, neuromuscular, or vascular disease? If "yes," is the condition likely to interfere with patient's ability to drive a motor vehicle safely? 11. Have you been diagnosed with any mental, nervous, organic or functional disease, or psychiatric disorder? If "yes," is the condition likely to interfere with patient's ability to drive a motor vehicle safely? 12. Have you been diagnosed with epilepsy or any other condition that may cause lapse of consciousness or loss of control? If "yes," have you had a lapse of consciousness or loss of control in the last three (3) years? 13. Do you use a controlled substance, amphetamine, narcotic, or any other habit-forming drug?
a. If "yes," did your doctor prescribe the drug? b. Did your doctor advise you NOT to drive when taking the drug? 14. Do you have a current clinical diagnosis of alcoholism? If "yes," when was your last drink of an alcoholic beverage?
Explain any Yes answers here

Explain any "Yes" answers here.
Physician's name, date of last visit, office address and phone

Print the physician's name (please print), the date of last visit, the physician's office address and the physician's phone number.
Certification and signature

By signing you certify (or declare) under penalty of perjury under the laws of the State of California that this form is true and correct.
I hereby give consent to the release of medical information by the physician named in PHYSICIAN'S NAME (PLEASE PRINT).
Sign on the driver's signature line and enter the date.
Sources
[1] California DMV DL 546, Health Questionnaire (REV. 5/2016), California Department of Motor Vehicles (the Official source link on this page).