

Form MC 194 at a glance
What it is: The Social Security Administration Referral Notice of the State of California Department of Health Care Services.
Where and when to file: You must contact the Social Security Office indicated on this referral form. DO NOT MAIL THESE FORMS TO THEM.
Part I is to be completed by the county welfare department.
For Medi-Cal, Food Stamp, and CalWORKs Recipients: each person who applies for or receives full-scope Medi-Cal, Food Stamps, or California Work Opportunity and Responsibility to Kids must have or apply for a social security number.
What to bring and attach to Form MC 194
To CWD: Please complete Part I. Retain original for your records, copy for recipient/SSA. Client must take this form to SSA. To Recipients: Read the back of this form. Take the necessary documentation to the Social Security Administration listed in Part I B. To SSA: This form is a request for the action noted in Part I C. Please complete Part II of this form and distribute as noted in Part I A. If you have any questions, the eligibility worker's name and phone number are provided.
Age, citizenship or alien status, and identity must all be documented.
One of the identification documents must be a birth or baptismal certificate established BEFORE age 5. If one is not obtainable, refer to Column A for acceptable substitutes.
Column A, Evidence of Age/Citizenship: School records, Church records, Census records (state or federal), Insurance policy, Marriage records, Draft card, U.S. passport, Other records indicating applicant's age or date and place of birth.
Column A, Evidence of Identity: Driver's license, State identification card, Voter's registration, School records, Health records (doctor's, hospital's, etc.), Any other document which shows applicant's signature, photograph, or description.
In addition, if the applicant/recipient is a U.S. citizen born outside of the U.S. or an alien, one of the items listed in Column B must be presented.
Column B: If you are now a U.S. citizen born outside the U.S., take one of the following items in addition to the item(s) required in Column A: U.S. citizen identity card, U.S. passport, Naturalization certificate, Certificate of citizenship, Consular report of birth, Form I-179 (U.S. citizen card), Form I-197 (U.S. citizen resident card).
Column B: If you are an alien, take one of the following items in addition to the item(s) listed in Column A:
Form I-151 or I-551 (Alien Registration Receipt Card), Form AR3a, I-94, I-95a, I-84, I-85, I-86, or SW-434, Letters from Immigration and Naturalization Service showing alien status. If you have a question concerning the two identification documents which you must take to the Social Security Office, please contact the Social Security Office.
A filled-in Form MC 194 example: a county worker refers an applicant for an original SSN card

How to fill out Form MC 194, box by box
A. County welfare office name and address

Enter the complete county welfare office name and address within the brackets provided.
SSA, after completion: FAX To, Mail this form to the county welfare office, or Return this form to the recipient to be returned to CWD.
B. Social Security Office Information
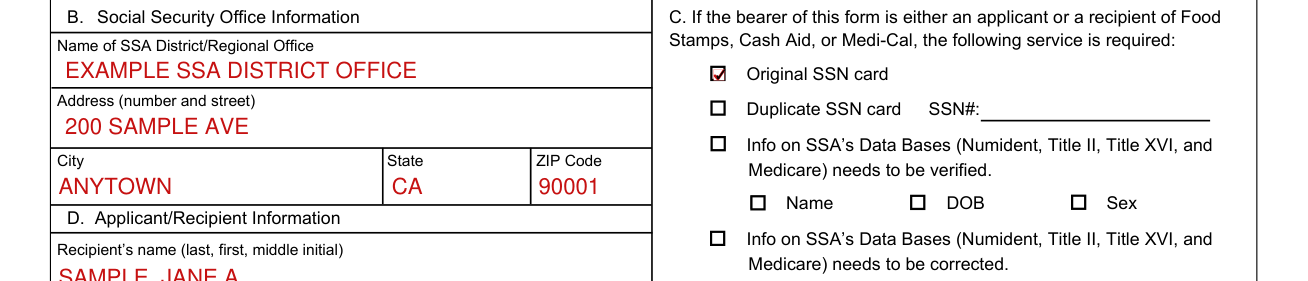
Under B. Social Security Office Information, enter the Name of SSA District/Regional Office, Address (number and street), City, State and ZIP Code.
C. Service required
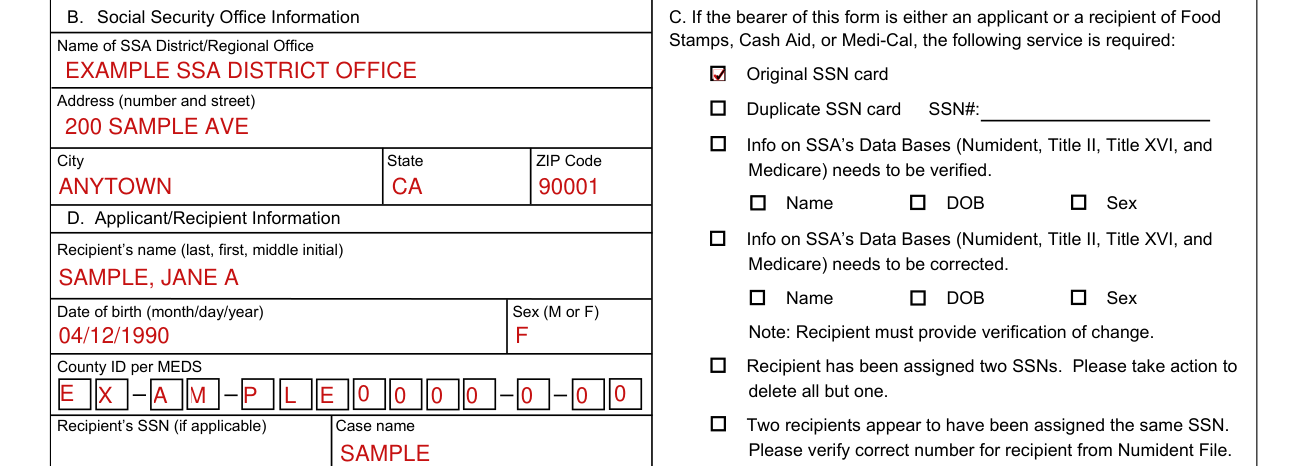
If the bearer of this form is either an applicant or a recipient of Food Stamps, Cash Aid, or Medi-Cal, the following service is required: Original SSN card, or Duplicate SSN card with the SSN#.
Info on SSA's Data Bases (Numident, Title II, Title XVI, and Medicare) needs to be verified: Name, DOB, Sex.
Info on SSA's Data Bases (Numident, Title II, Title XVI, and Medicare) needs to be corrected: Name, DOB, Sex. Note: Recipient must provide verification of change.
Recipient has been assigned two SSNs. Please take action to delete all but one.
Two recipients appear to have been assigned the same SSN. Please verify correct number for recipient from Numident File.
D. Applicant/Recipient Information
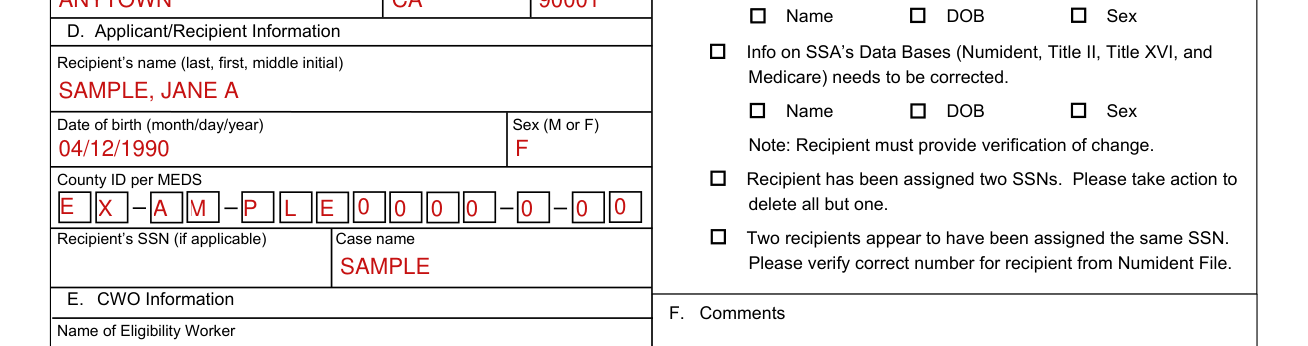
Under D. Applicant/Recipient Information, enter the Recipient's name (last, first, middle initial), Date of birth (month/day/year), Sex (M or F), County ID per MEDS, Recipient's SSN (if applicable) and Case name.
E. CWO Information

Under E. CWO Information, enter the Name of Eligibility Worker, Date form completed, E.W. Worker and E.W. phone number.
Part II: completed by the Social Security Administration
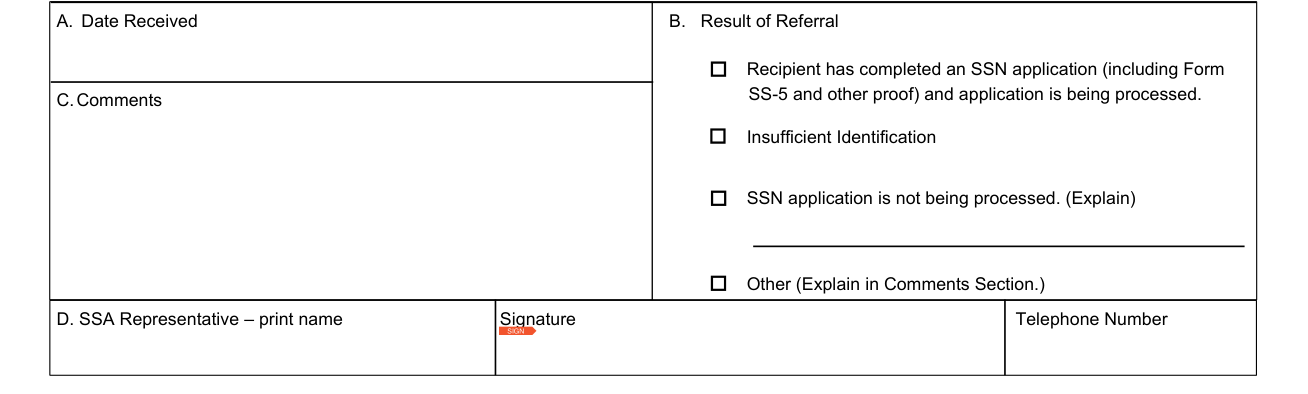
Part II is to be completed by the Social Security Administration district/regional office.
B. Result of Referral: Recipient has completed an SSN application (including Form SS-5 and other proof) and application is being processed; Insufficient Identification; SSN application is not being processed (Explain); Other (Explain in Comments Section).
Part II also has A. Date Received, C. Comments and D. SSA Representative - print name, Signature, Telephone Number.
More rules for Form MC 194
For the applicant/recipient noted on the form, either (1) the Social Security Administration does not have a social security number on file, or (2) the information provided by the Social Security Administration and the information provided to the eligibility worker do not agree.
Common questions about Form MC 194
Where do I file it?
You must contact the Social Security Office indicated on this referral form. DO NOT MAIL THESE FORMS TO THEM.
Sources
[1] Form MC 194 (07/12), Social Security Administration Referral Notice, California Department of Health Care Services (the Official source link on this page).