

Member Appeal Form at a glance
What it is: Member Appeal Form: to appeal a claim or denial of service in whole or in part, your request must be within 180 days of the initial determination.
Who signs: Sign on the Member Signature line and enter the Date.
A filled-in Member Appeal Form example: a member appeals a denied claim
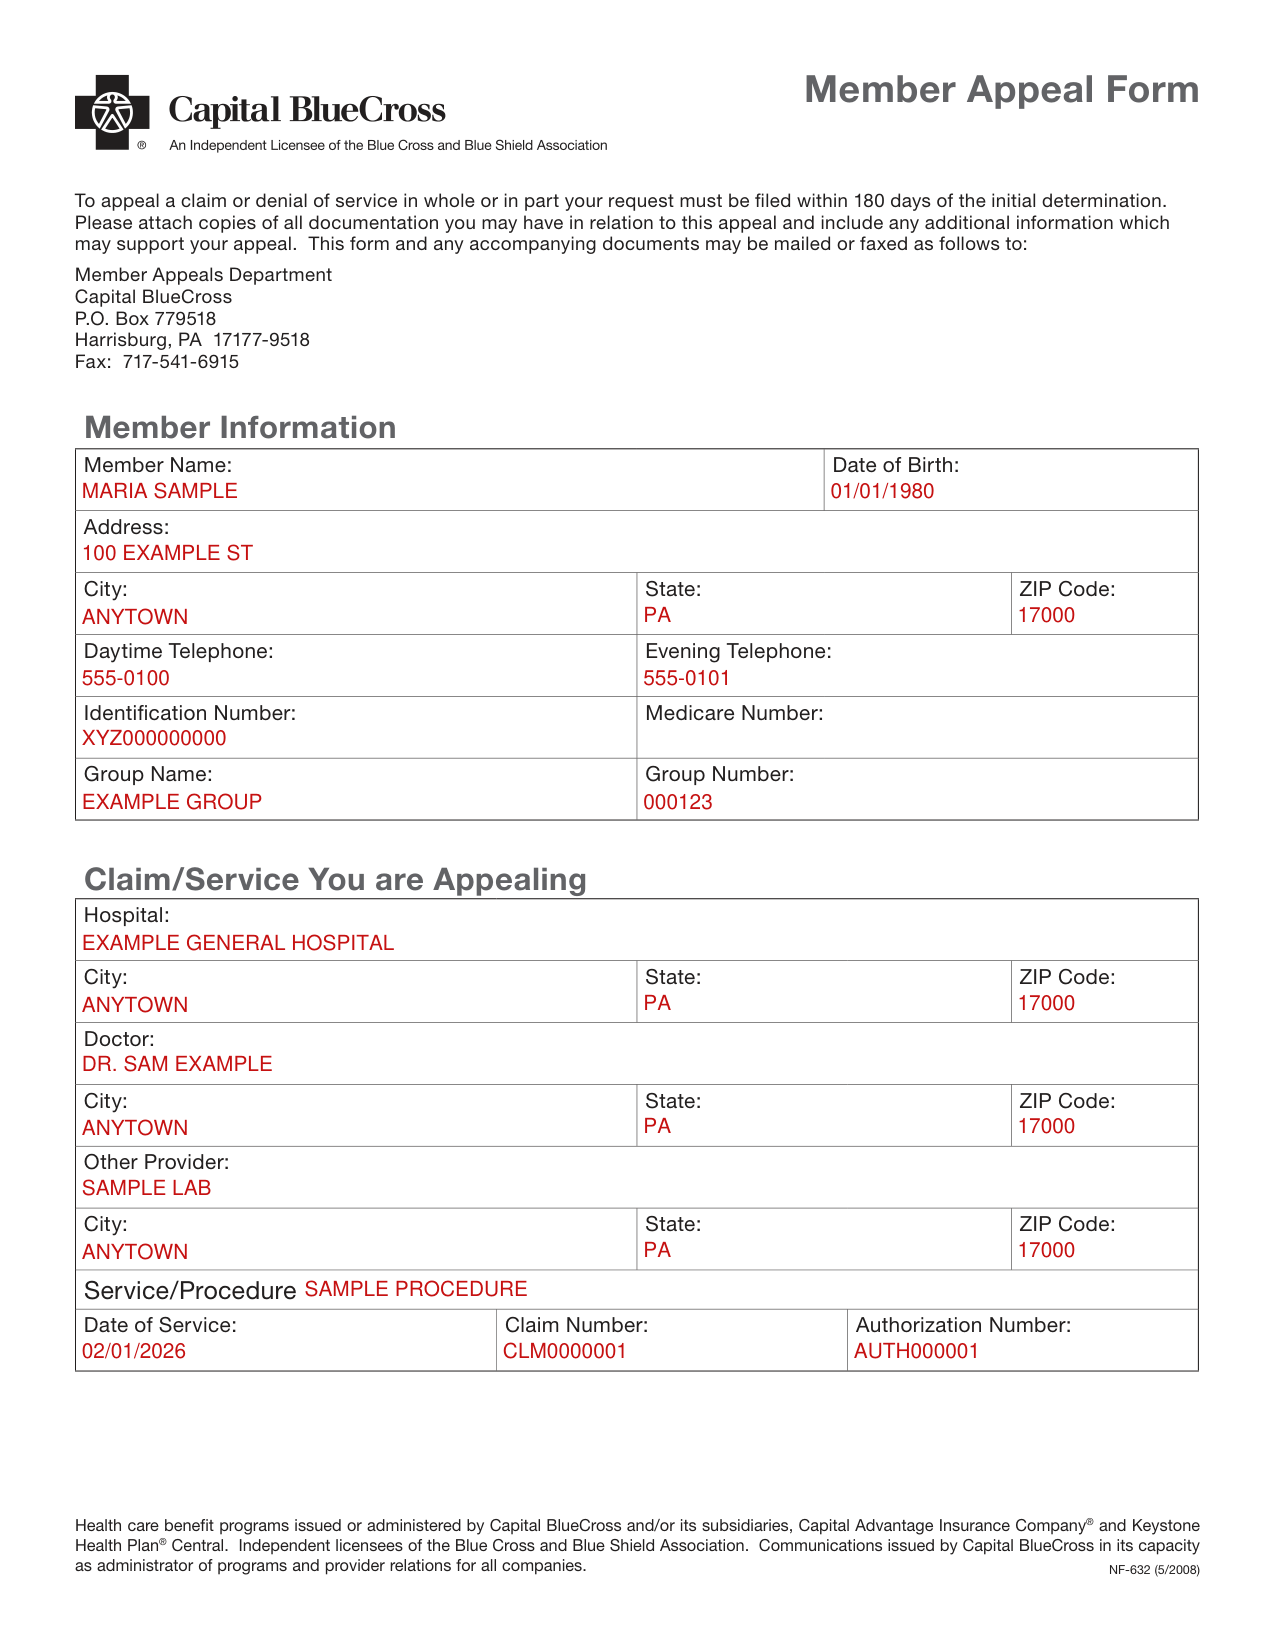
How to fill out Member Appeal Form, box by box
Member Information
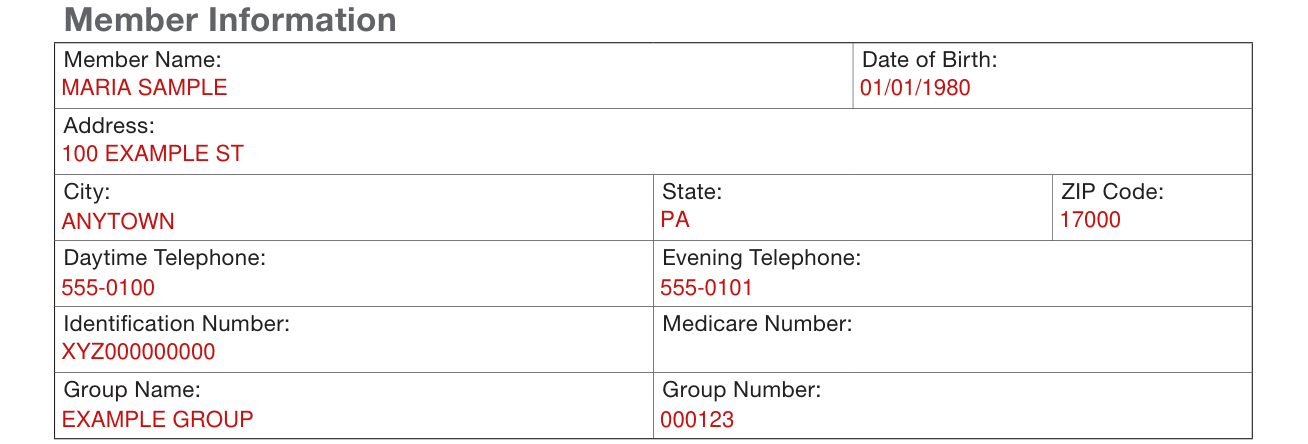
Under Member Information, enter the Member Name and the Date of Birth.
Enter the Address, City, State and ZIP Code.
Enter the Daytime Telephone and the Evening Telephone.
Enter the Identii cation Number and the Medicare Number.
Enter the Group Name and the Group Number.
Claim/Service You are Appealing
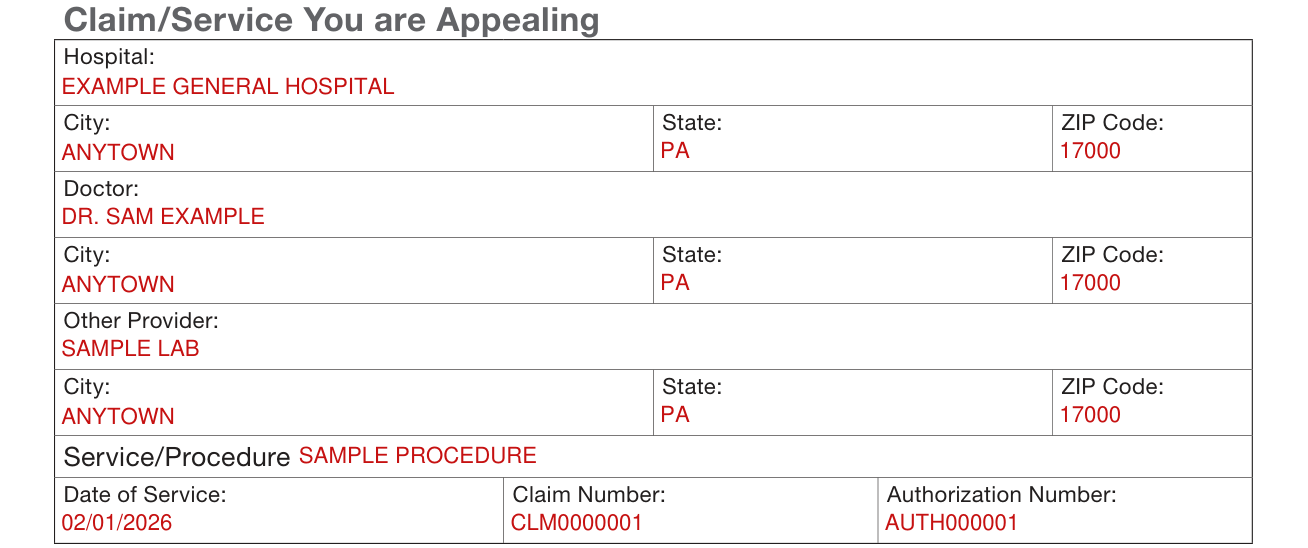
Under Claim/Service You are Appealing, enter the Hospital, with its City, State and ZIP Code.
Enter the Doctor, with the City, State and ZIP Code.
Enter the Other Provider, with the City, State and ZIP Code.
Enter the Service/Procedure, the Date of Service, the Claim Number and the Authorization Number.
Reason for the Appeal

Write the Reason for the Appeal.
Your request must be within 180 days of the initial determination. Attach copies of all documentation in relation to the appeal and include any additional information which may support the appeal. This form and any accompanying documents may be mailed or faxed to the Member Appeals Department, Capital BlueCross, P.O. Box 779518, Harrisburg, PA 17177-9518, Fax: 717-541-6915.
Member Signature

Sign on the Member Signature line and enter the Date.
More rules for Member Appeal Form
If appointing someone to represent you during the course of the appeal, your representative must complete this portion.
The member signs on Signature of Member and enters the Date.
Under Section 2, to be completed by the Representative, the representative fills in the blank after I, to accept the above referenced appointment, and fills in what they are after I am a/an of the Member.
The representative signs on Signature of Representative and enters the Name of Representative and the Date.
Sources
[1] Member Appeal Form NF-632 (5/2008), Capital BlueCross (the Official source link on this page).
